
Breakthrough T1D’s first-ever Clinical & Research Congress (CRC 2026), focused entirely on type 1 diabetes (T1D), has come to a close! Check out all our coverage below from the exciting weekend in Philadelphia, PA, where researchers, clinicians, industry leaders, healthcare professionals (HCPs), and the T1D community united to share updates across our entire mission.
Check Out our CRC Recap Video!
Updates from CRC 2026 Day 1
Islet cell therapy clinical trials, complications, automated insulin delivery, clinical adoption, and how we kicked off the conference.
Updates from CRC 2026 Day 2
Disease-modifying therapy clinical trials, early detection, advocacy, the lived T1D experience, and more.
Updates from CRC 2026 Day 3
Advanced screening technologies, Centers of Reference, diabetes stigma, and the pros and cons of islet cell therapies versus disease-modifying therapies.
Thanks for joining us throughout our coverage of our Clinical & Research Congress! And thank you to everyone who helped make this conference possible, including our sponsors, donors, supporters, and staff. We couldn’t do this without you.
We couldn’t be more proud of how our inaugural conference turned out, and we’re already looking forward to next year. Mark your calendars: CRC 2027 will take place in Washington, D.C., from October 15-17, 2027!
It’s a rainy day in Philadelphia, but the mood at CRC 2026 could not be sunnier! The attendees are positively buzzing (seriously) with how timely and impactful this meeting is. It’s the right time for a meeting focused exclusively on type 1 diabetes (T1D), and the good news is we won’t have to wait years for the next one!
CRC 2027 will take place from October 15-17 in Washington, D.C., USA. Stay tuned for more information!
Breakthrough T1D’s Clinical & Research Congress
The inaugural Breakthrough T1D Clinical & Research Congress (CRC 2026) is a groundbreaking forum uniting clinicians, researchers, scientists, healthcare professionals, industry leaders, and the T1D community. Attendees will explore cutting-edge advances in T1D science, clinical care, and more. Designed to foster collaboration and spark innovation, CRC 2026 will provide translational insights, interactive learning, and meaningful dialogue, all with one shared goal: improving lives and driving toward a world without T1D.
Islet Cell Therapies vs. Disease-Modifying Therapies: Which is Better?
Spoiler alert: There’s no right answer—there are pros and cons to both!
Peter Senior, MBBS, Ph.D. (University of Alberta) and Colin Dayan, MBBS, Ph.D. (University of Birmingham) debated the safety, costs, monitoring, potential long-term outcomes, and considerations for global access of disease-modifying therapies (DMTs) versus islet cell therapies.
Dr. Dayan made the case that islet cell therapies may be effective in the short-term, but in the long-term they might not be scalable, affordable, or deliverable globally. On the flip side, emerging DMTs may allow for a one-and-done treatment—meaning they could be far more affordable and easily accessible, especially in the pediatric population. DMTs also address the root cause of T1D from the start, rather than “putting a patch on it” later.
On the flip side, Dr. Senior argued that there are significantly more people living with established T1D compared to early-stage T1D or even within 100 days of a diagnosis—meaning that islet cell therapies, especially manufactured versions that are scalable, must be the solution since it is too late to preserve beta cells in most people. He also made the point that islet cell therapies can give patients more beta cells than a DMT would—and more beta cells meanings better outcomes, including freedom and flexibility.
Someone in the audience chimed in with an important point: Ideally, DMTs and islet cell therapies can one day be combined to maximize the benefits of each (e.g., restore insulin production and address autoimmunity against beta cells).

Key Takeaway
Both DMTs and islet cell therapies have a future in T1D—ideally one day used in combination—and have several benefits for different ages and stages.
Islet Cell Therapies
The Burden of Immunosuppression
Sabarinathan Ramachandran, Ph.D. (University of Minnesota) gave an update on immunosuppression with islet transplants. The key challenge is these transplants work, but over the long term, 50-70% of recipients lose function. He outlined the approaches investigators are taking to reduce the burden of these necessary drugs, like gene-editing, encapsulation, and engineered microenvironments.
Cellular Reprogramming
Hongkui Deng, M.D. (Peking University) presented a talk on cellular reprogramming, which involves treating cells with specific factors that turns them into a different cell type. Dr. Deng and his team developed a new, non-traditional strategy—which he called “chemical reprogramming”—that uses small molecules (instead of proteins) to reprogram cells. This approach is more efficient and easier to accomplish in the lab than traditional cell reprogramming approaches.
Using chemical reprogramming, Dr. Deng’s team turned a person’s fat cells into islet cells. The team then transplanted these islet cells back into the same person under the anterior rectus sheath, a large, easily-accessible, and well-vascularized area (meaning transplanted islets have access to blood vessels carrying nutrients and oxygen).
This person achieved substantial improvements in time in range and blood-sugar management, and no safety issues were identified during continuous monitoring. They were also already on immunosuppressants for a liver transplant. Now, more than one person has received this treatment, and Dr. Deng and his team are monitoring them closely.
Dr. Deng’s lab is also working on artificial intelligence (AI)-based approaches to scale up chemical reprogramming for islet cell therapies in addition to researching new ways to remove the need for immunosuppression.

Key Takeaways
- Reducing the need for immunosuppression is a key focus area for islet cell therapies.
- Chemical reprogramming of a person’s own fat cells into islet cells is a new and promising approach to restoring insulin production in people with T1D.
Disease-Modifying Therapies
Clinical Trial Design Post-Teplizumab
- Presenter: Jason Gaglia, M.D. (Joslin Diabetes Center, Harvard Medical School)
- We know that teplizumab (Tzield) works, but individual responses can be variable and there may be an optimal treatment window.
- Now that we have an approved DMT, the question becomes: Do we use teplizumab as a comparator in clinical trials instead of a placebo, so that everyone who participates has a chance to benefit?
- If we do, people may not want to participate if they can get teplizumab at their clinic and covered by insurance—or they may not want teplizumab at all because of the 14-day infusion, side effects, or other reasons.
- With this in mind, we do not have a clear answer yet about whether teplizumab should be used in place of a placebo in DMT clinical trials.
Disease-Modifying Therapies Highlight: Breakthrough T1D-Funded Work
Peter Gottlieb, M.D. (Barbara Davis Center for Diabetes) presented on the T1D Cures Accelerator, a global effort to develop new biological markers (or biomarkers) that can accelerate DMT clinical trials. This consortium represents a group of experts from academia, industry, the T1D community, regulatory agencies, and healthcare. The team plans to aggregate data from several DMT trials, perform large-scale AI-based analyses on available datasets, and identify and validate new biomarkers.
Carmella Evans-Molina, M.D., Ph.D. (Indiana University School of Medicine) talked about mechanisms driving beta cell stress. Her team showed that activating a protein called SERCA can delay diabetes development in animal models of T1D. She worked together with Neurodon, a company that previously received an Industry Discovery and Development (IDDP) award from Breakthrough T1D, who developed the small molecule targeted to SERCA.
Bruce Verchere, Ph.D. (University of British Columbia) is a member of The Breakthrough T1D Canucks For Kids Fund Centre of Excellence in Canada. He presented his lab’s work on a nanoparticle-based method to target a specific subset of immune cells called antigen-presenting cells (APCs). APCs activate the immune cells that are responsible for destroying beta cells, and this approach reprograms them to stop doing this. In animal models, this prevents T1D.

Key Takeaways
- Teplizumab could one day be used instead of a placebo in DMT clinical trials, but we need to work out the pros and cons for participants first.
- A new global consortium will help accelerate DMT development.
- We’re learning more about how beta cells function in the autoimmune environment, and new approaches targeting beta cells or immune cells are showing promise in preclinical studies.
Early Detection
Advanced Screening Technologies
Katsiaryna Prystupa, M.D. (German Diabetes Center) presented a machine learning analysis to sort more than 600 newly diagnosed people with T1D into three groups based on shared features like autoantibodies and insulin resistance. One group is associated with diagnosis earlier in T1D progression, when more beta cells are remaining. This work could help identify who may benefit most from DMTs.
Callie Zaborenko, Ph.D. (Indiana University School of Medicine) analyzed electronic health record (EHR) data and genetic information from adults to see whether a genetic risk score could help identify people at a higher risk of developing T1D. Adults with the highest scores were nearly ten times as likely to be diagnosed with T1D as adults with mid-range scores. This could one day help guide who is offered autoantibody testing, though more research is needed first.
Alice Carr, Ph.D. (University of Alberta) talked about the best way to assess if DMTs are working in early-stage T1D trials. Using data from TrialNet and TEDDY studies, she presented her work showing that oral glucose tolerance tests (OGTT) can estimate insulin secretion as a measure of beta cell responsiveness. This may better capture risk of T1D progression, which can help researchers choose the best participants for DMT clinical trials and understand if DMTs are working.
Kathleen Gillespie, Ph.D. (University of Bristol) and her team screened nearly 20,000 adults for islet autoantibodies and followed those with confirmed autoantibodies in the T1DRA study. The prevalence of adults who had multiple autoantibodies was similar to that in children, which supports screening in adults. The team is developing an approach to group people with a single autoantibody into tiers based on progression risk, which could help tailor individualized monitoring.
Brittany Bruggeman, M.D. (University of Florida) analyzed the TEDDY study to better understand the decline in function in the part of the pancreas that helps digest food (the exocrine pancreas) in children at risk for T1D. In kids who developed islet autoantibodies earlier, a biomarker of exocrine pancreatic function (FE-1) was lower in infancy, before autoimmunity against beta cells. Combined with other tests, this biomarker may one day help researchers better predict T1D progression.
Key Takeaway
We already have screening capabilities to identify people in early-stage T1D, and research into advanced screening technologies will allow us to better predict T1D progression and response to DMTs.
Medical Affairs
Communication and Shared Decision-Making: Old and New Challenges in T1D
The diabetes care team is made up of many disciplines. This session was presented by three psychologists and a physician focusing on the behavioral and educational aspects of T1D.
The first speaker, Ellen O’Donnell, Ph.D. (MassGeneral Brigham and Harvard Medical School) discussed the best communication tactics for children and adults in early-stage T1D. Telling a person, and their family, about an early-stage T1D diagnosis is a life-changing conversation. Thankfully, we know the best ways to communicate this information: using metaphors, graphics, and pictures, and taking into account the full context of the family (e.g., their family structure, experience with T1D, and baseline mental health). Not only do we know the best ways to have these conversations, but there are tools and resources for clinicians and healthcare providers.
Next up, Jane Speight, Ph.D. (Deakin University, Australia) talked about a topic that we need to dedicate more time to: diabetes stigma. T1D is a chronic illness, and living with it is a deeply emotional experience. When HbA1c stops being information and starts being a measure of self-worth, it has negative results. It can cause teens, parents, and adults with T1D to feel dehumanized, which has a direct result on physical and mental health.
Some alarming stats:
4 in 5
adults with T1D report experiencing diabetes stigma
98%
of teens and young adults with T1D report experiencing diabetes stigma
1 in 5
adults with diabetes report discrimination—being treated differently—because of their diabetes
Diabetes stigma is associated with lower well-being and less confidence (self-efficacy) in managing diabetes, in addition to other worse outcomes:
2-3x
the odds of having an HbA1c above 9%
Up to 2x
the likelihood of diabetic ketoacidosis (DKA)
But there is something we can do. A positive, self-fulfilling feedback loop predicated on stigma-free communications can help people do better—and this needs to be considered in every conversation.
The final speaker, Carol Levy, M.D. (Icahn School of Medicine at Mt. Sinai) got into pregnancy and T1D. We know that women with diabetes require much tighter targets to reduce maternal and fetal health risks. These risks are real and difficult to manage for the mother and the physician—and they start pre-conception and continue post-partum. Insulin requirements change dramatically throughout gestation, and there is limited real estate on the body for continuous glucose monitors (CGMs) and insulin pumps. Even with the better tools that we have today, pregnancy outcomes remain suboptimal.
The main point: Flexibility, creativity, and understanding are needed. Pregnant women are thinking about lots of things—not just their T1D management. They don’t all want to wear a pump.
Centers of Reference
Breakthrough T1D Chief Medical Officer International, Thomas Danne, M.D., Ph.D. has a very clear way of describing our challenge for the future. Cures for T1D are planes, in the air. We’re still building the plane, but it’s in the air right now. We must ensure there is a runway so that when the plane is ready to land, it can.
Right now, we’re building that runway through our Centers of Reference program, which is explored in a presentation by James Shaw, M.D. (Newcastle University).
Centers of Reference are expert multidisciplinary T1D care centers that are preparing healthcare professionals (HCPs) around the world to administer manufactured islet cell therapies to people with T1D. The goal is to make sure that expert clinical teams—who are already doing islet cell transplants at low scale—are ready to integrate these therapies into clinical practice at their institutions and train others, once they have regulatory approval.
Breakthrough T1D has created several working groups to help move these therapies forward now so they’re ready when cell therapies are (at scale). These include:
- Training and education, including a clinician training program launched with ATTD in Europe and the American College of Diabetology in the US.
- Clinical access, including reaching community clinicians, countering myths and fears, and peer review between Centers.
- Harmonizing clinical care, including team composition, patient screening, monitoring, and follow-up.
- Benchmarking and validation, including quality-assured registries and peer review.
Centers of Reference are a work in progress. They’re going to take time to get off the ground—but all the right people are working on it today.
Key Takeaways
- T1D management and care—from communicating with early-stage T1D, to reducing stigma, to working with pregnant women with T1D—requires flexibility, understanding, and care, and the full experience of the person with T1D must be considered.
- We are not waiting until cell therapies are ready to prepare the clinical infrastructure for them. That work has begun!
That’s a wrap on CRC 2026! Keep an eye out for one more recap tomorrow with everything you need to know about this inaugural conference.
This article was written by Sandy Vogt, Ph.D. and Brian Herrick.
We are two days into the first ever Breakthrough T1D Clinical & Research Congress! Day 1 was full of optimism and excitement about the meeting—it’s really ALL type 1 diabetes (T1D), which is unique—and the future of treatments and therapies for this community.
Breakthrough T1D’s Clinical & Research Congress
The inaugural Breakthrough T1D Clinical & Research Congress (CRC 2026) is a groundbreaking forum uniting clinicians, researchers, scientists, healthcare professionals, industry leaders, and the T1D community. Attendees will explore cutting-edge advances in T1D science, clinical care, and more. Designed to foster collaboration and spark innovation, CRC 2026 will provide translational insights, interactive learning, and meaningful dialogue, all with one shared goal: improving lives and driving toward a world without T1D.
Peter Senior, MBBS, Ph.D. (University of Alberta), a longtime Breakthrough T1D-funded collaborator, spoke at the beginning of the first session and his comments really set the tone for the day.
“People want to not have diabetes anymore. I think we need to keep that in mind as we move toward solutions.” – Dr. Peter Senior
CRC is 100% Focused on the Lived Experience
A guiding principle of this meeting is that it is centered around the lived experience of people with the disease. To drive this home, all of the parallel sessions were introduced by community members, sharing a story about their lives with T1D.
One video focused on how artificial intelligence (AI) has the potential to transform diabetes technology—fewer calculations means less daily burden. Here’s another perspective from Daniel Newman:
That’s our whole goal: people doing better. And CRC was filled with nearly 1,000 people—all of whom are working toward that shared goal.
With that in mind, let’s hear about the solutions, innovations, and cutting-edge work shared on day 2! As a reminder, every session is not included here—and we encourage you to attend next year to get the full CRC experience!
Check out our video recap of CRC 2026 day 2!
Unmet Needs: Where We Are and What’s Still Needed for People with T1D
The day kicked off with a symposium sponsored by Vertex Pharmaceuticals that explored the unmet needs and emerging treatments in T1D. Vertex is developing a manufactured islet cell therapy for T1D, which is currently in a phase 1/2/3 clinical trial. Jennifer Sherr, M.D., Ph.D. (Yale School of Medicine) and Dr. Peter Senior shared a wealth of data showing that outcomes have been improving for people with T1D year by year with new technology, primarily automated insulin delivery (AID)—but people still aren’t doing well enough. Even with the best technology, a study showed that a significant percentage of people still aren’t achieving ideal glycemic control, and some are still experiencing severe hypoglycemic events.
In summation: Technology has absolutely improved care, but there are still unmet needs to be addressed.
Keynote Lecture: Building Bridges Between Research, Clinical Care, and the Lived Experience in T1D
Michael Haller, M.D. (University of Florida) gave a broad overview of how the T1D screening and care paradigm has evolved—and what the future looks like. There are three key “bridges” we need to finish building: screening as clinical care, therapy options for every age and every stage, and clinical trials built around the lived T1D experience.
Key takeaways:
- We have years of data on how to screen, the populations to prioritize, the methods that yield the highest successful screenings, and the benefits.
- The priority today is scaling up: building the infrastructure to screen more people thoughtfully while keeping the experiences of the screened families front and center.
- The paradigm has already shifted; it was managing the disease, and now it’s modifying the disease.
- People with T1D need to be at the center of clinical trial design, and encouraging participation is key to catalyzing more therapy options for all.

Islet Cell Therapies
Protecting Transplanted Islets
The first islet cell therapy session of the day, chaired by Valeria Sordi, Ph.D. (IRCCS Ospedale San Raffaele), focused on how we can take manufactured islets and keep them safe from the immune system post-transplant without the need for immunosuppression. Islet cell therapy is a promising treatment for T1D but there are major barriers—one of which is the requirement for immunosuppression. This session tackled tactics for removing that barrier.
Juan Alvarez-Dominguez, Ph.D. (University of Pennsylvania) presented how he and his team developed a method to watch the cells mature by placing electrodes inside the lab-grown islets. They have learned that the cells mature very quickly—like a switch being flipped on—versus gradually.
Audrey Parent, Ph.D. (University of California, San Francisco) and Sonja Schrepfer, M.D., Ph.D. (Cedars-Sinai Medical Center) both tackled gene editing using different approaches. Dr. Parent focused on modifying existing cells to protect them from the autoimmune response while Dr. Schrepfer’s work was centered on making the transplanted cells immune-evasive. These two tactics can potentially be used together in a complementary manner.
Zimislecel: Meaningful Benefits for Participants
Michael Rickels, M.D. (University of Pennsylvania) gave an update on the clinical trial for Vertex’s manufactured islet cell therapy zimislecel. All 12 participants have improved blood-sugar levels and no severe hypoglycemic events, and 10 of 12 people are off external insulin. Participants report significantly less diabetes distress and fear of hypoglycemia, demonstrating that islet cell therapies like this have a real impact on the day-to-day experiences of living with T1D.
Islet Cell Therapies Highlight: Breakthrough T1D Centers of Excellence (CoE)
- This session was chaired by Esther Latres, Ph.D. (Senior Vice President of Research at Breakthrough T1D).
- The Breakthrough T1D Center of Excellence in Northern California: Qizhi Tang, Ph.D. (University of California, San Francisco) talked about research themes run by 13 investigators at three institutes: mechanisms and models of T1D, rebalancing the immune system (including in the context of islet transplants), and innovating in islet cell therapies.
- The Breakthrough T1D Canucks For Kids Fund Centre of Excellence: Megan Levings, Ph.D. (University of British Columbia) presented on this CoE’s work on engineering better islet cells for transplants, protecting remaining and transplanted islet cells, and measuring and reducing beta cell stress.
- The Breakthrough T1D Barbara Dewey Cammett Center of Excellence in New England: David Harlan, M.D. (University of Massachusetts Chan Medical School) discussed this Center’s goal—promote beta cell resilience to stressors. They plan to accomplish this by identifying new therapeutic targets, understanding early if these targets can translate to humans, and improving models and assays to help answer their questions.

Key Takeaways
- We know more than ever about the maturation of transplanted beta cells, and there are many promising techniques to protect them from the immune system that are working their way through the research pipeline.
- Real-life experiences show that islet cell therapies like zimislecel have benefits beyond blood-sugar control, including less daily stress.
- Centers of Excellence are Breakthrough T1D-funded research teams uniting expertise and resources to collaborate and share ideas, better understand complex T1D biology, and tackle some of the biggest challenges in islet cell therapies.
Disease-Modifying Therapies
Research Supported by the T1D Fund
William Quinn, Ph.D. (SAB Bio) presented phase 1 clinical data from four people treated with SAB-142 (humanized ATG), a DMT designed to delay or prevent progression of T1D. The therapy targets immune cells responsible for the destruction of insulin-producing beta cells while also preserving those that help balance the immune system. SAB-142 has a favorable safety profile and preserved C-peptide in all participants—while actually enhancing C-peptide in 3 of 4 people. Enrollment is ongoing for the SAFEGUARD clinical trial for people within 100 days of a T1D diagnosis, and next up is the Breakthrough T1D-funded PRISE-ATG study, led by Dr. Haller, which will study SAB-142 in people within two years of a diagnosis.
Taylor Triolo, M.D. (Barbara Davis Center for Diabetes) presented safety data around CNP-103, a DMT in clinical trials developed by COUR Pharmaceuticals. CNP-103 works by restoring balance to the immune system by training it to stop recognizing beta cells as a threat. In a study with 32 participants, early data show favorable safety and tolerability, with no severe adverse events. The trial is expanding and efficacy data is expected in late 2026 or 2027.
Key Takeaway
Data from emerging DMTs in clinical development are demonstrating favorable safety and some early hints of efficacy.
Early Detection
A session chaired by Linda DiMeglio, M.D. (Indiana University School of Medicine) tackled early risk assessment for T1D. How do we find people earlier? How can we ensure they are able to take advantage of the myriad benefits of knowing they have early-stage T1D?
First up, Andrea Steck, M.D. (University of Colorado) talked about using continuous glucose monitoring (CGM) to assess T1D risk in addition to family history and autoantibody results. And there are some specific findings on how these can be used together:
- More time above 140 mg/dl is indicative of disease progression.
- Individuals who spend more than 15% of the day above 140 had about a 60% chance of progressing to stage 3 T1D within two years, versus about 15% for those below that level.
- Combined tools improve prediction validity. A risk score using CGM data, HbA1c, family history, and autoantibody results sorted people into low risk (about 5% chance in two years), medium (13%), and high (48%).
- For children in the middle stage, spending over 10% of the time above 140 signals risk of progression, and over 20% means it’s time to evaluate for stage 3 T1D.
Last up was Greg Lipak (HealthShare Exchange), who discussed how we can use AI to find individuals who may be misdiagnosed in electronic health records.
Early Detection Highlight: Breakthrough T1D-Funded Work and Staff Making an Impact
Richard Oram, M.D., Ph.D. (University of Exeter) discussed the use of genetic risk score to identify individuals who merit observation for progression into T1D. This means looking at their DNA to calculate a risk score, which correlates to risk of developing T1D. However, it is just risk. Someone with a high-risk score may not develop T1D, but a person with a low-risk score very well could. It’s another tool we can use to help people understand their status so they can potentially reap the benefits of early detection.
Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES, Senior Vice President of Medical Affairs, took part in a panel discussing screening and early detection. The message remains the same: We’re making progress, but we need to screen more people. Global consensus is building among different aspects of screening, including the recent Breakthrough T1D-led consensus monitoring guidelines. However, we must ensure screening comes with clear, consistent communications with an action plan, so families can also have a plan.

Key Takeaways
- Early detection is more important than ever—but screening is just the first step. Confirming and monitoring are essential to turn screening results into action.
- There are more tools to find individuals at risk and in early-stage T1D than ever.
Improving Lives
Diabetic Ketoacidosis (DKA): Transforming Care with Continuous Ketone Monitoring
- Presenters: Richard Bergenstal, M.D. (HealthPartners Institute), Jennifer Sherr, M.D., Ph.D. (Yale School of Medicine), and Medha Munshi, M.D. (Harvard Medical School); supported by Abbott
- DKA is still a risk for people of all ages living with T1D because available ketone measurement methods are not widely used—and this drives up healthcare costs.
- Dual glucose-ketone monitoring will help guide care in real-time, warning people in advance so they can take action before an emergency happens.
- This technology could be particularly transformative for families, young adults transitioning to independence, people taking SGLT inhibitors, and older adults with other conditions or cognitive decline.
In a session chaired by Viral N. Shah, M.D. (Indiana University School of Medicine) that spanned multiple topics, Kalie L. Tommerdahl, M.D. (University of Washington) presented research on obesity and kidney disease in youth with T1D. Her data suggested that obesity and glycemic control affect T1D kidney health independently, which supports the notion that both need to be addressed in people with T1D for the best possible kidney outcomes.
Improving Lives Highlight: Breakthrough T1D and the T1D Fund Making an Impact
Thomas Strack, M.D. (vTv Therapeutics) presented on quantifying the population with clinically meaningful hypoglycemia-related burdens from people using AID. The results: over half of the adult T1D population have clinically meaningful hypoglycemia complications, and new interventions are needed to optimize care.
Breakthrough T1D has been studying the use of GLP-1s in T1D for years—and there are myriad benefits despite the drug still not being approved specifically for T1D. Piaopiao Li, Ph.D. (Emory University) presented data from a paper looking at real world data (not from clinical trials) to investigate how GLP-1s can affect cardiovascular disease and chronic kidney disease in T1D. The results were clear: This class of medications appear to reduce the risk of cardiovascular and renal complications without significant safety concerns. Dr. Li noted that the results should be validated in clinical trials.
Breakthrough T1D Chief Medical Officer International, Thomas Danne, M.D., Ph.D., discussed a new publication led by the Breakthrough T1D Medical Affairs team, titled “Roadmap to Fully Closing the Loop to Optimize Health in Type 1 Diabetes,” published in Diabetes Technology and Therapeutics. This manuscript defines a person-centered framework to evaluate fully closed-loop systems as they continue to evolve, emphasizing the need to simultaneously support people living with T1D in attaining glycemic outcomes while also meaningfully improving quality of life.
Key Takeaways
- Dual glucose-ketone monitoring can help people take action when ketones are rising before it becomes an emergency.
- Adjunctive therapies, including GLP-1s and SGLT inhibitors, have the potential to safely reduce heart and kidney complications in people living with T1D—but large trials have not been done yet.
- We’re getting closer to fully closing the loop in AID systems—and Breakthrough T1D and collaborators published a roadmap to help us get there.
Advocacy
Expanding Global Access to T1D Treatments and Care
- Professor Partha Kar (Portsmouth Hospitals NHS University Trust) talked about improvements in access to T1D care in India, ranging from education, to insulin, to glucose testing strips. Renza Scibilia (Senior Director of Global Responsibility) also mentioned the key role of Breakthrough T1D in advocating for better access, psychosocial health, and more.
- Carlos Antillón, M.D. (CEDYN, Mexico) presented on how global access and T1D innovations must advance together, and clinicians can help overcome barriers through advocacy, evidence generation, personalized treatment, HCP and patient education, and understanding what patients can realistically afford and sustain.
- Princess Padmaja K. Parmar (The Friends of Mewar) gave an inspiring talk on how global access to T1D supplies must be dependable and how lived experiences should guide all future work around T1D. She also highlighted the role of Breakthrough T1D in advancing research and access on a global scale.
- David Beran, Ph.D. (University of Geneva) gave a presentation around how barriers to access to T1D therapies and devices persist worldwide due to product shortages or discontinuations, with challenges in low- to middle-income countries largely driven by supply chain issues, technology costs, and more. Global advocacy and policy changes can help overcome these barriers.
“Breakthroughs matter when they reach people. Policy matters when it changes daily life. Partnerships matter when they continue beyond the conference room.” – Princess Padmaja K. Parmar
Key Takeaway
Access to T1D technology and devices is still a challenge around the world, but organizations like Breakthrough T1D are advocating for change and policies so that access can catch up with innovation.
Medical Affairs
Enrolling in Clinical Trials
Kimber Simmons, M.D. (University of Colorado) hit on a key point (and Breakthrough T1D organizational priority): clinical trial recruitment.
It is well established that clinical trials take far too long to enroll. It is also true that a new T1D diagnosis is an incredibly difficult situation for families to navigate. They must weigh placebo, randomization, side effects, and more. Then, the family has to make a decision quickly to successfully enroll within the clinical trial window.
Dr. Simmons and her team in Colorado rolled out a program to educate families about beta cell preservation in their one-week follow-ups. The results were striking. Among interested families, 24% of families enrolled in a clinical trial within 8 weeks.
Healthcare Professionals with T1D: A Unique Perspective on T1D Care
- Andrew Welch, M.D. (University of Cincinnati) talked about disruptions in diabetes supplies, including two calls to action: 1) diabetes tech companies should give people the quantity of supplies they actually need, taking into account early failures and 2) we need transparent real-world data about supply interruptions and their consequences.
- Sarah Westen, Ph.D. (University of Florida) and Marissa Hitchcock, BSN, RN, CDCES (Children with Diabetes) discussed how language matters when talking to people with T1D, especially when it comes to communicating the risk of complications and reducing diabetes stigma. Dr. Westen also told her own T1D story, including how Breakthrough T1D has supported her personally—and professionally!
- Kathryn Nagel, M.D. (Maine Medical Center) presented on how we need more data and better care for women with T1D who are pregnant, especially through psychosocial support and technologies for pregnancy-specific glycemic goals.
Medical Affairs Highlight: Breakthrough T1D-Funded Research
Emma Ospelt, MPH (T1D Exchange) presented her work on how pediatric endocrinology practices talk about clinical trial opportunities with newly diagnosed families, highlighting challenges around timely enrollment within the 100-day post-diagnosis window. The study identified different workflows in various centers, including formal processes that include initiating clinical trial conversations early versus clinics that lack dedicated staff or resources to have these conversations. In both scenarios, successful enrollment of newly diagnosed individuals in clinical trials is still not guaranteed, and clinical centers need additional support and resources to overcome these recruitment challenges.
Key Takeaways
- Recruiting for newly diagnosed trials is difficult, but with the right education, it can be done!
- Providing people with T1D with the best care possible goes beyond the clinic—it’s ensuring access to diabetes supplies, using person-centered language, and supporting women with T1D who are pregnant.
Look out for another article coming soon covering day 3 of CRC 2026. Keep an eye on our News & Updates webpage!
This article was written by Sandy Vogt, Ph.D., and Brian Herrick.
Hello from Philadelphia, PA! We could not be more thrilled that, after years and years, we have finally kicked off our inaugural Breakthrough T1D Clinical & Research Congress (CRC). This groundbreaking event is focused entirely on type 1 diabetes (T1D), and it’s happening right now!
Breakthrough T1D’s Clinical & Research Congress
The inaugural Breakthrough T1D Clinical & Research Congress (CRC 2026) is a groundbreaking forum uniting clinicians, researchers, scientists, healthcare professionals, industry leaders, and the T1D community. Attendees will explore cutting-edge advances in T1D science, clinical care, and more. Designed to foster collaboration and spark innovation, CRC 2026 will provide translational insights, interactive learning, and meaningful dialogue, all with one shared goal: improving lives and driving toward a world without T1D.
For the next three days, we’ll provide you with everything you need to know about this conference, the top takeaways, and what the path forward looks like so that people with T1D can live better, healthier lives. And in case you missed it, check out our precap on what we plan to cover.
Check out our video recap of CRC 2026 day 1!
Islet Cell Therapies: Research Supported by Breakthrough T1D or the T1D Fund
Piotr Witkowski, M.D., Ph.D. (University of Chicago) presented on the Breakthrough T1D-funded clinical trial for tegoprubart, an alternative to standard immunosuppressants, developed by T1D Fund company Eledon. Tegoprubart is maintaining its success: All 12 participants who have received an islet cell transplant are off external insulin (7 after one transplant; 5 after two) with stable blood-sugar levels, no side effects, and no toxicity in the kidneys. An upcoming clinical trial will test tegoprubart in people with T1D and chronic kidney disease (CKD)—the first time this population is eligible for an islet cell therapy.
Per-Ola Carlsson, M.D., Ph.D. (Uppsala University) provided an update on the first person treated with a partial dose of immune-evasive islet cells developed by Sana, another T1D Fund company. There were no serious side effects, and the cells continue to survive and make insulin over a year post-transplant.
Leonardo Velazco-Cruz, Ph.D. (Century Therapeutics, a T1D Fund company) presented on a manufactured immune-evasive islet cell therapy that has shown promise in animal models of T1D, advancing towards first-in-human studies and clinical-grade, scalable manufacturing. Unlike other therapies currently in clinical trials, Century’s product is both scalable and does not require immunosuppression.
Key Takeaway
We’re seeing continued progress in islet cell therapies, both in clinical trials and in preclinical development—bringing us closer to scalable solutions in which no immunosuppressants are needed.
Disease-Modifying Therapies
C-peptide
C-peptide is a biomarker of the body’s insulin production, which can be measured easily by a blood test. It’s formed when pro-insulin is cleaved into active insulin and C-peptide.
C-peptide: Why it Matters for Clinical Outcomes
- Presenter: Justin Gregory, M.D. (Sanofi)
- Based on several datasets, we know that more C-peptide means better glycemic control and fewer short- and long-term complications (especially severe hypoglycemia, diabetic ketoacidosis, and retinopathy).
- This relationship is foundational to why we are so focused on C-peptide: it matters!
- For years, Breakthrough T1D has advocated for the use of C-peptide as a validated surrogate endpoint, which would make DMT clinical trials smaller, faster, and less expensive—without cutting corners on safety.

Disease-Modifying Therapies Highlight: Work Supported by the T1D Fund
Dan McNamara, Head of Strategy and Engagement at the T1D Fund, sat down with Jason Cole, J.D., CEO of Zag Bio, a T1D Fund portfolio company focused on restoring balance to the immune system. They spoke about how expertise and funding provided by the T1D Fund can lay the groundwork for strategic partnerships that advance early-stage therapies for T1D.

Key Takeaways
- There is a positive relationship between C-peptide preservation and improved glycemic outcomes.
- T1D Fund investments in early-stage companies can accelerate DMTs (and other therapies and technologies for T1D) through capital, expertise, and support.
Early Detection
The benefits of screening for T1D are well established. Combined with follow-up and monitoring, early detection can reduce the risk of diabetic ketoacidosis (DKA) at diagnosis, connect people to clinical trials and specialists, open the door to FDA-approved therapies that can delay the need for insulin therapy, and give families time to plan and prepare.
The question now is how to increase access to screening, and how to ensure people with early-stage T1D are connected to next steps and options. That was the focus of a panel chaired by Chantal Mathieu, M.D., Ph.D. (KU Leuven, Belgium).
Key Takeaways
- The case for early detection is settled. The work now is expanding access and making screening and monitoring easier for the people who take part.
- Less painful and more convenient testing, including at home or in community settings like schools, can help more people get tested and stay engaged.
- Support should fit the family, especially if there is a family history, and should include clear communication, psychological support, and continuity of care.
- Results must be backed up by clear, consistent communication.
Improving Lives
Kerendia (Finerenone): First New Therapy in 30 Years for Kidney Disease and T1D
- Presenter: Sergio Chang Figueroa, M.D. (University of Louisville), speaking on behalf of Bayer
- The FDA recently approved finerenone (brand name Kerendia), a once-daily pill already approved for type 2 diabetes, for people with T1D and CKD—the first advance in nearly 30 years for this population.
- CKD is one of the most common complications of T1D: nearly a third of people with T1D will develop it, increasing their risk of kidney failure and heart complications.
- As part of our Improving Lives program, Breakthrough T1D strategically collaborated with Bayer to support the FINE-ONE clinical trial that led to this approval.
Making Sure Your Insulin is Still Potent
- Presenter: Maren Schinz, Ph.D. (Beyond Diagnostics AG)
- People living with T1D may wonder if their insulin is still good to use after temperature changes—and this company is developing a way to fix that.
- Studies in animal models of T1D have shown that injecting insulin that has lost some of its potency doesn’t lower blood-sugar levels as well.
- This team developed an assay that can be paired with a smartphone to check the potency of insulin in real-time.
New Publication by Breakthrough T1D’s Medical Affairs Team and Collaborators
Brynn Marks, M.D. (Senior Director of Medical Affairs), Thomas Danne, M.D., Ph.D. (Chief Medical Officer International), and several expert collaborators and Breakthrough T1D staff published a manuscript titled “Roadmap to Fully Closing the Loop to Optimize Health in Type 1 Diabetes” in Diabetes Technology and Therapeutics. This publication defines a person-centered framework to evaluate fully closed-loop systems as they continue to evolve, emphasizing the need to simultaneously support people living with T1D in attaining glycemic outcomes while also meaningfully improving quality of life.
Automated Insulin Delivery (AID) in the Era of Artificial Intelligence (AI)
- Tadej Battelino, M.D., Ph.D. (University Medical Center Ljubljana) talked through use of AI in continuous glucose monitor (CGM) data, MRIs, and other clinical metrics to predict progression or monitor the impacts of T1D.
- Todd Brusko, Ph.D. (University of Florida) highlighted complex data types generated from human samples that can be analyzed with AI to help us learn even more about what causes T1D.
- Juan Espinoza, M.D. (Northwestern University) highlighted how to best integrate AI into T1D care in clinical settings.
- Boris Kovatchev, Ph.D. (University of Virginia) presented about how digital twins—a computational model for blood-sugar changes—fueled by AI can speed clinical development of next-generation AID systems.
Improving Lives Highlight: Research Supported by Breakthrough T1D
Marcela Moscoso, Ph.D. (University of Virginia), presented a tool that tracks insulin sensitivity and estimates blood-sugar changes after meals—a step toward fully closed-loop automated insulin delivery (AID) systems that wouldn’t require meal announcements. Tested through simulations and real-world clinical trial data, the tool successfully detected expected increases in insulin sensitivity during exercise and distinguished between fast- and slow-digesting meals, laying groundwork for smarter, more automated insulin dosing in the future.
Key Takeaways
- Finerenone’s recent approval remains in the spotlight as a major advance for people with CKD and T1D.
- New predictive models and algorithms are advancing toward fully closed-loop AID systems for people with T1D, meaning one step closer to no meal announcements.
- New technology will one day give people with T1D the option to check that their insulin is still 100% potent in real-time.
Medical Affairs
As early detection, disease-modifying therapies, and islet cell therapies move forward and treatment options expand, Tandy Aye, M.D. (Stanford School of Medicine), Brynn Marks, M.D. (Senior Director of Medical Affairs at Breakthrough T1D), and Katelyn O’Brien, Pharm.D. (Boston Medical Center) participated in a session chaired by Bobby Gabbay, M.D., Ph.D. (Joslin Diabetes Center) about how the medical community needs to effectively adapt to the current and future state of T1D care.
Some high-level takeaways:
- The field is moving faster than the care system. The world of T1D is rapidly changing. The paradigm is changing, including the proliferation of screening and early detection and novel disease-modifying therapies and islet cell therapies. Clinical teams must be ready to keep pace with the current and future landscape.
- Islet cell therapies are coming—and they depend on workforce as much as science. There are severe limits to the supply of deceased donor islets (for now!) but there also aren’t enough care teams to administer them. Learn more about how we’re trying to solve this problem through Centers of Reference and Breakthrough T1D’s Interventional Diabetology program.
- Diabetes care and education specialists are an underused bridge. Fewer than 5% of Medicare beneficiaries and fewer than 7% of privately insured people get education in the first year after diagnosis. These specialists have longer visits, can close technology gaps (CGM, automated insulin delivery), and relay real-world challenges back to clinicians.
- The workforce pipeline is a concern. We need more endocrinologists.
Kick-off
Dr. Mathieu closed the Congress’s opening day by describing the future of T1D as “two paths.” One is technology, and one is disease-modifying therapies plus islet cell therapies. These are not two disparate paths—technology has the capability to keep people healthy so that when DMTs and islet cell therapies arrive at scale, people with T1D can make the most of it.


CRC 2026.
Where we are
- Technology works in the real world. Dr. Mathieu presented data from her homeland of Belgium showing HbA1c falling year over year, first with sensors (around 2017) and further with hybrid closed-loop systems. In addition to glycemic improvements, people with T1D are seeing lower risk of complications, including retinopathy and kidney disease.
- Disease-modifying therapies are here. Teplizumab, approved in November 2022, is the first therapy to delay the immune attack on beta cells. It has since expanded to children as young as one and to many countries.
- Screening is rapidly ramping up. Dr. Mathieu’s European consortium has screened about 140,000 children—and this is only increasing in Europe and across the world.
Our vision for the future
- Treat earlier in stages 1 and 2, to delay insulin therapy dependence by months, years, or decades.
- Personalize treatment using immune biomarkers that predict who will respond.
- Run more trials and build more integrated networks, like TrialNet.
- Islet cell therapies are next.
The last thing she said, and a key theme of this meeting, is the need for collaboration. We all need to set our egos aside and work together. The people in this room are responsible for the current state—and the myriad revolutions that have directly led to people with T1D doing better today. The people in the room are going to be the ones that make cures possible—but only if we work together.
Look out for articles coming soon covering days 2 and 3 of CRC 2026. Keep an eye on our News & Updates webpage!
This article was written by Sandy Vogt, Ph.D., and Brian Herrick.
After months and months of preparation, it’s finally here! Breakthrough T1D’s very first Clinical & Research Congress (CRC), a groundbreaking event focused entirely on type 1 diabetes (T1D), is happening this week from October 9-11 in Philadelphia, PA.
Bringing Together People United in Our Shared Goal
This scientific meeting is a groundbreaking event, uniting T1D researchers, scientists, healthcare professionals (HCPs), industry leaders, and community members from all parts of the globe, whose lives have been shaped by T1D in one way or another. Attendees will have the chance to discuss cutting-edge advancements in T1D discovery science, technology, treatments, and more. Our agenda is shaped by the voices of the T1D community, ensuring that the lived experience of T1D is at the center of the ongoing work toward our shared goal: improve the lives of people with T1D as we drive toward cures.
The Chairs
This inaugural meeting was organized by our expert Scientific and Clinical Advisory Board from Breakthrough T1D, including:
- Thomas Danne, M.D., Ph.D., Chief Medical Officer International
- Sanjoy Dutta, Ph.D., Chief Scientific Officer
- Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES, Senior Vice President of Medical Affairs
The CRC will be hosted in Philadelphia, where Breakthrough T1D was founded 50+ years ago. Philadelphia is a hub of medical innovation and scientific advancements, making it an ideal location for experts from across the world to convene and share T1D research, clinical progress, and milestones.
The scientific program at CRC is fully accredited. Attendees who are healthcare professionals can earn up to 12.0 CEU/CME toward licensure and certification.
What We’re Looking Forward To
Cures
- Progress in several islet cell therapy studies we’re watching closely
- Novel strategies to protect transplanted islets
- New approaches in disease-modifying therapies (DMTs) and developments in ongoing clinical studies
- Expert perspectives on general population screening for T1D
- The role of genetic risk and other advanced technologies for T1D early detection
Cures Highlight: Breakthrough T1D-Funded Work and T1D Fund Companies
Islet cell therapies will be front-and-center at CRC. Piotr Witkowski, M.D., Ph.D., will share updates from the Breakthrough T1D-funded clinical trial at the University of Chicago for Eledon’s tegoprubart, for which he serves as lead investigator. Per-Ola Carlsson, M.D., Ph.D., will discuss gene-edited islets from Sana Biotechnology. Both Eledon and Sana are T1D Fund portfolio companies.
Several other Breakthrough T1D-funded scientists will present their work on encapsulation, manufactured islets, protective immune therapies, and more, including research stemming from our Centers of Excellence.
Two T1D Fund companies, SAB Bio and COUR Pharmaceuticals, will present findings from their ongoing DMT studies, and Carmella Evans-Molina, M.D., Ph.D., will fill us in on mechanisms of beta cell stress. On the early detection front, Andrea Steck, M.D., and Richard Oram, M.D., Ph.D., will discuss continuous glucose monitoring (CGM) and genetic risk scores, respectively, in assessing early T1D risk and progression.
Improving Lives
- Recent exciting progress in T1D complications, including chronic kidney disease
- Progress in automated insulin delivery and the role of artificial intelligence
- Advancements in ketone monitoring and management
- Innovations in adjunctive therapies
Improving Lives Highlight: Breakthrough T1D-Funded Work
Boris Kovatchev, Ph.D. will present his work on “digital twin” simulation technology for AID systems, a project that has been shaped over the years by several Breakthrough T1D grants, alongside other researchers making progress toward fully closing the loop. Also featured will be Rhonda Merwin, Ph.D., discussing findings from an eating disorder study, and several presenters will cover GLP-1s and SGLT inhibitors.
Advocacy and Medical Affairs
- Developments in expanding global access to life-changing treatments
- Insights into gaps in T1D clinical care—and how we can fill them
- Strategies for clinical trial education and awareness
- Perspectives on clinical trials, pregnancy, technology, and more from HCPs living with T1D
- Discussions around scaling up islet cell therapies from a clinical perspective
Advocacy and Medical Affairs Highlight: Breakthrough T1D-Funded Work
David Beran, Ph.D., will uncover a global roadmap to improve T1D care. We’ll also hear from Jane Speight, Ph.D., who will present her work on advocating to end diabetes stigma. A number of investigators participating in Breakthrough T1D’s initial Centers of Reference rollout will also be presenting.
CRC: A Place to Come Together to Share T1D Breakthroughs
We envision this event as the go-to forum for translational updates, collaborative dialogue, and cross-sector collaboration. Our leadership and staff have worked tirelessly for months on end to bring this vision to life, and many will be in attendance participating in sessions, sharing ideas, and making sure the event runs smoothly from start to finish.
Spotlight on Breakthrough T1D and T1D Fund Staff
- Aaron Kowalski, Ph.D., Chief Executive Officer, will chair a debate covering disease modification versus replacement therapy in T1D.
- Esther Latres, Ph.D., Senior Vice President of Research, will chair a session on new research models charged with accelerating T1D science.
- Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES, Senior Vice President of Medical Affairs, will present on the recently published consensus report around general population screening for T1D.
- Stephanie Pearson, Vice President of Global Responsibility, will chair a session on global accessibility to treatments.
- Brynn Marks, M.D., Senior Director of Medical Affairs, will present a session on interventional diabetology.
- Dan McNamara, Head of Strategy and Industry Engagement (T1D Fund), will sit down with Zag Bio to discuss how the Fund is supporting their work in T1D. Zag’s lead program, which recently entered the clinic, aims to address the immune response driving T1D by rebalancing the immune system.
Updates Coming Your Way – Stay in the Know
Each day, we will share a highlight video and written recap of the previous day in the News and Updates section of our website. If you haven’t signed up already, fill out this form to get these recaps delivered to inbox every day, along with recurring news and updates throughout the year.
Check out on-site coverage from CRC on our social channels and interviews of attendees and presenters.
This is the first time in history Breakthrough T1D is hosting an event like this (and it won’t be the last!). We are thrilled to create a one-of-a-kind space where researchers and T1D community members from around the globe can connect, collaborate, share ideas, and ultimately contribute to our shared mission of a world without T1D. We can’t wait to share the exciting updates we’ll hear at CRC with our community. Thank you to our supporters for helping make this event possible. We wouldn’t be able to do this without you!
Islet cell therapies for type 1 diabetes (T1D) are in the works. In clinical trials, people are coming off external insulin—and experiencing healthy blood sugar levels. Researchers and clinicians are working hard behind the scenes to advance next-generation manufactured islet cell therapies as scalable cures. The momentum is real—and it’s more important than ever to double down, bring all the key players together, and make them a reality.
First- Versus Next-Generation Islet Cell Therapies
First-generation islet cell therapies, including those in clinical trials today, are limited to people with severe hypoglycemic events and hypoglycemia unawareness. Next-generation islet cell therapies, including manufactured versions that can be made at large scale, will, ideally, be open to expanded populations. The future we’re working toward is one where everyone with T1D who wants an islet cell therapy can get one.
The Workshop: Bringing Together Key Voices
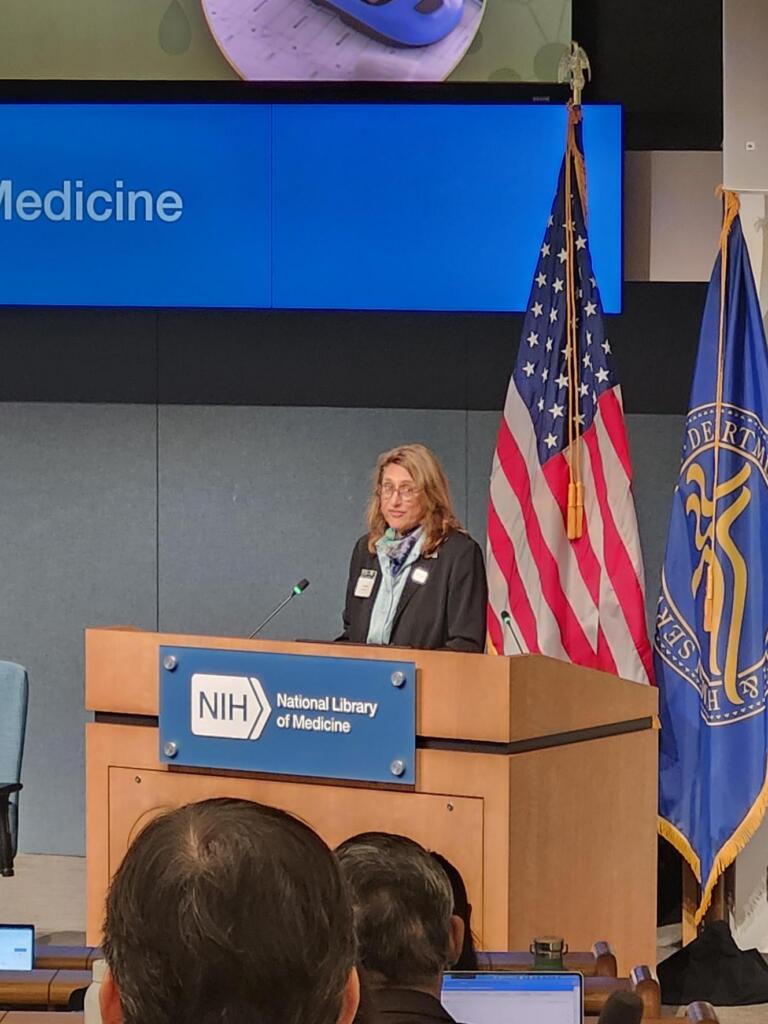
To keep the momentum going, Breakthrough T1D co-hosted a public workshop with the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) titled “Accelerating the Translation of Cell Therapy for Type 1 Diabetes.” This workshop convened researchers, clinicians, industry leaders, representatives from the U.S. Food and Drug Administration (FDA), individuals with T1D, and more to discuss best practices and recommendations for accelerating islet cell therapies for the T1D community as newer generations become available.

The planning committee included several Breakthrough T1D staff:
- Esther Latres, Ph.D. (Senior Vice President, Research)
- Nicholas Mamrak, Ph.D. (Senior Scientist, Research)
- Marjana Marinac, Pharm.D. (Associate Vice President, Regulatory Affairs)
- Chanel Press, Ph.D. (Director, Regulatory Affairs)
- Brianna Greeno (Senior Manager, Regulatory Affairs)
Key Takeaways
- Preclinical studies must be thoughtfully designed to ensure these novel islet cell therapies can be tested in human clinical trials.
- From the very beginning of their experiments, researchers must consider manufacturing requirements for nonclinical and clinical studies to effectively translate islet cell therapies to large scale.
- Real-life T1D experiences must be integrated into study designs and decision-making around next-generation islet cell therapies to ensure they create meaningful improvements to life with T1D and that the community is educated on them and is interested.
- Artificial intelligence (AI) is safely being applied to several different aspects of the islet cell therapy workflow, from forecasting responses to transplants, to optimizing manufacturing, to engineering cells.
The Conversation: Advancing Islet Cell Therapies from the Lab to Humans
The workshop broadly focused on considerations for advancing manufactured islet cell therapies, including lab-based work, large-scale manufacturing, and clinical trial design. Read on to learn more about the discussion around each topic.
Nonclinical studies gather evidence showing that new therapies are likely to work and be safe in people before moving to clinical trials. Choosing the best experimental design is key for accurate, reliable, and reproducible data, which includes identifying the right T1D model and data collection method to answer the question at hand. Presenters also shared data around islet cell source, survival, and immune protection from ongoing preclinical projects.
Large-scale manufacturing is critical to make sure there are enough islets for everyone with T1D who wants them. There are several FDA manufacturing requirements that need to be met for scalable islet cell therapies to move from preclinical studies to first-in-human studies, and these requirements change as the studies get bigger. Presenters dove into considerations for islet manufacturing in academic versus industry settings and how each is helping us learn about the optimal ways to produce lots of consistent and reliable islets at once—which is really hard to do!
We know from previous and ongoing studies that islet cell therapies work—people are reducing or eliminating their need for injected insulin. We also know that for many people with T1D, the benefits of getting an islet cell transplant outweigh the risks associated with long-term immunosuppression. Presenters considered what future clinical trials should look like: how to expand inclusion criteria, define meaningful endpoints, and educate the T1D and healthcare community to drive referrals and participation. Researchers must carefully consider manufacturing, safety, and efficacy considerations to ensure that trial designs meet requirements defined by regulators to clear a path for approval of next-generation therapies.
Researchers are taking advantage of AI and applying it to different aspects of the islet cell therapy workflow, including individually forecasting blood sugar responses one-year post-transplant to help guide informed decision-making. Researchers are also using AI to optimize islet manufacturing, from predicting how islet cells will fare under certain conditions to analyzing data and modifying processes. AI can help design novel therapies on a cellular level, meaning “smart” islet cells that could sense immune attack and deploy immune-protective measures in a targeted way.
Several members of the T1D community shared powerful stories around their lived experiences with the condition. Some panelists have lived with T1D for decades and are seeing their children go through the same thing, while others have received successful (or unsuccessful) islet cell transplants. The group covered a range of topics: day-to-day burdens, technology, experiences with immunosuppression, and how islet transplants changed their lives (with one person noting that still needing one insulin injection per day post-transplant is a dramatically positive outcome). Ensuring the voices of the T1D community are heard by people in the field driving islet cell therapies forward is key to thoughtful person-centered research and design.
Learn more about how our Participant Advisory Council uses their voices to guide clinical trials.


Why this Matters
Islet cell therapy science is advancing on three fronts at once: nonclinical research in the lab, clinical trials in humans, and large-scale manufacturing. While researchers, scientists, and clinicians are working hard pushing these efforts forward, Breakthrough T1D is helping to keep the conversation open around what’s working, how to overcome challenges, how to engage with regulators, and new partnerships and collaborations. Even more, keeping the voices of people with T1D in the mix is key to advancing islet cell therapies in a way that’s meaningful for our community. Breakthrough T1D thanks the NIDDK for co-hosting a successful event and all presenters, panelists, and attendees for contributing to critical conversations that will ultimately help accelerate next-generation islet cell therapies for type 1 diabetes.
New Publication Alert!
Breakthrough T1D spearheaded a paper titled “International consensus guidance for general population screening for islet autoantibodies to diagnose early-stage type 1 diabetes” that was published in Diabetologia. This is an important step toward integrating general population screening for type 1 diabetes (T1D) into clinical practice globally. Read on to learn more about why this is important, what experts think this should look like, and what it means for you and your family.
Early Detection, Screening, and Islet Autoantibodies
Early detection of T1D means detecting the disease before symptoms appear or insulin therapy is needed. This is done through screening blood samples to detect the presence of islet autoantibodies, which signal that the body’s immune system is attacking insulin-producing cells. If a person has two or more persistent autoantibodies, they are in stage 1 or 2 T1D, and it’s very likely they’ll develop clinical, stage 3 T1D.

Making the Case for General Population T1D Screening
In 2024, Breakthrough T1D led the way with the publication of Consensus Guidance for Monitoring Persons with Islet Autoantibody-Positive Pre-Stage 3 Type 1 Diabetes, which lays out what clinicians should do when T1D autoantibodies are detected. But it does not touch on the bigger question: who should get screened?
There is an urgent need for population-level screening because:
- Global T1D incidence is increasing.
- Early detection has substantial benefits.
- Most T1D diagnoses occur in people without any family history of the disease.
- Evidence from ongoing, large-scale studies around the globe has shown that we have a screening method that works.
Benefits of Early Detection
- Reduced risk of diabetic ketoacidosis (DKA) at diagnosis
- Option to intervene with the approved therapy Tzield (teplizumab)
- Increased eligibility for participating in disease-modifying therapy (DMT) clinical trials
- Increased early control of hyperglycemia that can reduce the risk of complications
- Time to plan, prepare, and empower educated decision-making
Breakthrough T1D convened a group of nearly 30 international experts to establish consensus that can act as a clinical roadmap to make general population screening a reality.
Key Recommendations for Clinical Adoption of General Population T1D Screening
So, who should get screened? Experts recommend that T1D screening begin in young children aged 2-4 years, with rescreening of children who test negative at ages 6-8 years and again at 10-15 years, aligned with other preventative healthcare visits. Every initial screening result should be confirmed with another test before diagnosis.
This may seem simple enough, but integrating screening into established clinical workflows will require collective effort. Healthcare systems must be fully prepared to deliver the entire screening, monitoring, and referral pathway before widespread integration. Policy and infrastructure must be in place, including established processes for confirming test results, education and monitoring of people with early-stage T1D, and referring people to specialists. In addition, healthcare professionals (HCPs) will need to effectively communicate with and provide psychosocial support to families at every step of the screening process.
The bottom line is that integrating general population T1D screening into clinics will require extensive cooperation across diverse medical settings to become a reality. But the payoff is clear: combined with Tzield and other emerging DMTs, general population screening should open the door to delaying—and eventually preventing—the onset of clinical, stage 3 T1D.
What this Means for You and Your Family
Right now, children and adults with or without a family history of T1D can participate in screening through free, research-based programs like TrialNet and ASK. Screening can be done in-person at certain locations, or screening kits can be sent straight to your home.
Based on the consensus guidance, families may consider starting to screen their children as early as ages 2-4. If the screening test detects autoantibodies, there are now concrete next steps that families can discuss with their physicians. You don’t have to wait until general population screening is integrated into clinics to take advantage of it.
Screening and Early Detection are Key to Breakthrough T1D’s Mission
General population T1D screening is a key part of our mission strategy, and more people screening means more people experiencing the benefits of early detection. To screen as many people as possible, clinicians need guidance—and this publication provides just that. We now have concrete recommendations for who to screen for T1D and when. Even more, this consensus has been signed off by almost every single one of our peer institutions, amounting to 20 global diabetes societies and organizations.
This publication is bringing conversations around general population T1D screening to the forefront. Breakthrough T1D is committed to expanding T1D early detection on a global scale, and widespread screening is one of our top priorities. We are mobilizing our resources, knowledge, and partnerships to make this a reality sooner so that more families around the world can benefit.
To accomplish our mission of a world without type 1 diabetes (T1D), one thing is clear: the more minds we have thinking about T1D, the better. That’s why Breakthrough T1D brings in interns each year, including in our Research department. Training the next generation isn’t just about career development—it’s about fresh eyes, new ideas, diverse expertise, and encouraging interest in our common goal.
Breakthrough T1D’s Research Program
The goal of Breakthrough T1D’s Research program is to advance T1D science by supporting scientists, researchers and clinicians to accelerate life-changing breakthroughs for the T1D community. Our Research team members drive this effort forward through careful consideration of the T1D research landscape—identifying gaps and solutions, establishing long-term relationships with researchers in the field, and ultimately investing in the most promising avenues toward T1D cures and treatments.
Our 2026 interns have come from diverse backgrounds, each bringing a unique perspective to the teams and projects which they contributed to over the summer. From business development, to funding landscapes, to literature reviews and analyses, each intern leveraged their skills while simultaneously learning and growing under the mentorship of our Research team members.
Read on to learn more about each intern and the projects they worked on.

Jihyun Park
Mentor: Racquel Enad, MS, MPH, Senior Manager of Research Partnerships & Alliances
Jihyun is a master’s student in biotechnology at Columbia University. With bachelor’s degrees in both Life Sciences and Statistics, she is passionate about bridging science, data, and business. She has experience in coordinating cross-functional projects and building practical and quantitative tools that improve operational efficiency and business decision-making in the biotech and healthcare sector. In her free time, Jihyun likes to explore new favorite cafes, exercise, and play the electric guitar.
Over the summer, Jihyun worked with the Research Business Development and Partnerships team to strengthen alliance management for the Industry Development and Discovery Partnerships (IDDP) Program. She built a database of IDDP company grantees and their milestones (e.g., financings, partnerships, and clinical progress) since the program began in 2004, developed a tool the team can use to stay current on grantees’ progress after their awards, and created a visualization that maps how IDDP companies connect with one another and the broader T1D industry. Together, these resources help the team measure the program’s long-term impact and identify new opportunities to support grantees.

Sophia Meininger
Mentor: Matt Whipple, Analyst, Research Strategy
Sophia is part of an accelerated program at Binghamton University, completing a dual undergraduate degree in Global Public Health and Africana Studies, and she will begin a Master of Public Health (MPH) program this fall. Her academic work and leadership experiences have shaped a deep passion for health equity, community engagement, and advocacy. Sophia has lived with T1D since she was four years old, so contributing to Breakthrough T1D’s mission was, in her words, a genuine privilege.
This summer, Sophia joined Breakthrough T1D’s program management team to build a global funding landscape for type 1 diabetes research. Over the course of her internship, Sophia researched the foundations, government agencies, and regional funders supporting T1D research with a focus on regions where the T1D research ecosystem is still taking shape. The landscape identified the leading institutions and investigators driving T1D research forward. Sophia presented her findings to the Research department, showing the funding dynamics in these regions and identifying opportunities for collaboration. Her work gave Breakthrough T1D a stronger foundation for continuing to be an international organization to connect researchers, funders, and the T1D community across borders.

Aliaa Elkallini
Mentor: Nicholas Mamrak, Ph.D., Senior Scientist
Aliaa is pursuing Bachelor of Science and M.D. degrees at the Sophie Davis School of Biomedical Education, which is part of the City University of New York (CUNY) School of Medicine. She’s specifically interested in understanding how scientific findings can be translated into meaningful improvements in patient care.
This summer, Aliaa joined Breakthrough T1D’s Cell Therapy team. Her work focused on the characterization of manufactured islets, which can vary significantly and make it difficult to compare data and reproduce findings. To address this gap, she reviewed published studies, identified where characterization practices were consistent or fragmented, and spoke with investigators to understand which information is most useful in practice. From this work, she developed two complementary frameworks: one focused on the minimum information needed to clearly characterize manufactured islets and another that adjusts expectations based on the purpose of the study. Together, these frameworks are meant to give Breakthrough T1D and investigators a more consistent way to evaluate new approaches, understand which information should be available, and compare the strength of the evidence when considering future research support.

Avi Patel
Mentor: Raquel Lopez Diez, Ph.D., Senior Scientist
Avi is an MPH candidate at Long Island University Brooklyn. She previously trained as a dentist in India, and her interests lie in health systems, health services research, and the policy levers that govern access and delivery. Avi brings expertise in epidemiology, biostatistics, health policy, and research methods, plus a clinician’s perspective from the point of care. Outside of work, she loves reading classic literature, cooking, and exploring the city’s art galleries and cafes.
Avi supported Breakthrough T1D’s Early Detection portfolio by conducting a global landscape and gap analysis of T1D screening programs. She designed and led a survey of international screening programs, examining how they are designed and implemented, and identified gaps and opportunities for improvement. To build a complete picture of the field, she drew on organizational records, published literature, and clinical trial registries, then validated the resulting data for accuracy.
Avi compared program methodology against international clinical consensus guidelines to assess how closely the field aligns with evidence-based screening practice, and she synthesized her findings into an executive-level presentation for organizational leadership, translating complex comparative data into clear, actionable recommendations. Her work gives Breakthrough T1D a stronger foundation for understanding the global screening landscape and identifying where to focus future early detection efforts.

Kenzie Li
Mentor: Gianna Strand, MS, Ph.D., Associate Director, Clinical Research
Kenzie is a master’s student at Weill Cornell Medicine in New York City, where she studies Biostatistics and Data Science. She is passionate about using data to tackle real healthcare challenges and to make clinical trials work better for the people who take part in them. She is also a talented artist across different mediums, including oil painting, marker drawing, and pen-and-ink illustration.
During her internship with the Clinical Research team, Kenzie played a key role in examining the real-world barriers and facilitators that clinical trial participants face. Kenzie worked on the final stages of data analysis, built visualizations, and incorporated information from a comparison study of similar trials in Europe. These results will help inform how Breakthrough T1D supports the design of more accessible, participant-centered trials in the future.
Kenzie also kicked off an ambitious new project: a landscape gap analysis mapping clinical T1D evidence across the globe from 1975 to 2026. Once complete, this map will let Breakthrough T1D pinpoint where research evidence is missing or outdated. This supports the Research team in identifying and focusing future mission-driven projects toward the populations and regions where they are needed most.
By investing time and mentorship in our interns, we’re essentially investing in up-and-coming thought leaders and emboldening them to take part in our mission. They remind us that progress toward a world without T1D depends on the people we bring into this challenge. “The summer interns bring a fresh perspective and creativity to their projects, giving us a better understanding of T1D and how to advance our mission,” explains Matt Whipple, one of this year’s mentors.
They are the next researchers, public health experts, doctors, advocates, and more that will help us accomplish our goal, now and in the future. Our interns advance Breakthrough T1D’s work today by bringing new ideas, questions, and energy that will carry the mission forward to tomorrow.
“Making progress toward our mission requires us to stay innovative, analytical, and open to learning. Training the next generation is important not only because we can help develop future leaders, but because we learn from them too. That exchange of ideas, perspectives, and curiosity helps move us closer to breakthroughs in T1D,” shares Racquel Enad, another mentor.
Thank you to our 2026 interns for their contributions, and we look forward to seeing what they will accomplish next!
Spotlight on Jessie Stover

Jessie Stover is the Development Manager at Breakthrough T1D’s Indiana Chapter. Stover was born and raised in Evansville, Indiana, and she now lives in Indianapolis with her two cats, Milo and Zuko. She enjoys reading, crafting, concerts, and “baking gluten-free desserts so good that no one can tell they’re gluten-free.”
Here, Stover tells her story: from type 1 diabetes (T1D) diagnosis as a toddler, to an insulin pump clinical trial, to learning how to manage her T1D as a teenager, to a new outlook on living with the condition as an adult. Breakthrough T1D thanks Stover for her bravery in sharing her story and her commitment to the T1D community.
Gummy Bears and Insulin Shots

Stover was diagnosed with type 1 diabetes when she was just 2 years old. While her family has a history of autoimmune disorders, “there is no one else in my family with T1D, so it was a big shock to my parents, and we all had so much to learn,” explains Stover.
The learning process started in the kitchen, with a container forever-full of gummy bears to treat lows, a new kitchen scale to measure and track carbs, and sugar-free versions of things Stover had always enjoyed, like Kool-Aid. Between her parents, grandparents, and school secretary, she had “quite the village.”
But, like any kid, Stover didn’t like shots, and she remembers running away from her parents when it was time for an insulin dose.
A Kiddo in a Clinical Trial
During one of Stover’s appointments with her endocrinologist in Indianapolis, she was referred to a clinical trial exploring whether young children could benefit from an insulin pump. “My mom is a very practical person, so it was almost a no-brainer for her since it meant the possibility of no more insulin shots, and it could help manage my blood sugars more smoothly,” explains Stover. No shots sounded pretty good.
By the age of 4, she was enrolled in the trial and using her first insulin pump. Stover noticed a difference immediately; the pump site insertion didn’t hurt at all because they had the option to use a numbing cream. The relief was tangible not just for Stover, but also for her primary caregiver: her mom. Using an insulin pump meant automatically calculated insulin doses, remote control of insulin dosing, and, most importantly, no more shots. Stover has been using an insulin pump ever since.
Learn More about Clinical Trials
Visit Breakthrough T1D’s clinical trials web page to learn more about how you can get involved in clinical trials. Use our clinical trial matching tool to find recruiting trials near you that you may be eligible for. Connect with a Clinical Trial Education Volunteer in your area to better understand the process and get your questions answered.
Being a Teenager is Hard Enough

As Stover grew into a teenager, she also grew into managing T1D on her own. This was when she first truly understood what her diagnosis meant. “It wasn’t new, but it was as if something finally clicked in my brain that it wasn’t going to go away, and now it was my turn to do all the work,” she explains. Coupled with stressful conversations around needing to “do better” to avoid future complications, it was a tough transition, and Stover struggled to find the resources to help her get through it. “Just because the textbook makes it look easy, and my mom made it look easy, it felt like I was expected to immediately do the same,” Stover recalls.
It all changed when someone on Stover’s diabetes care team said: “Being a teenager is hard enough. Adding T1D into the mix is like trying to stop a volcano from erupting!” For the first time, Stover felt that everything she was feeling about being a teen and managing T1D had been put perfectly into words. “I realized I was allowed to be angry, upset, and unhappy, and I didn’t have to just accept T1D and move on. Stepping back and allowing space to understand and grieve my diagnosis helped me,” she said.
This realization opened the door to more candid conversations and a stronger relationship with her parents. Stover was able to openly discuss her mental health needs and set boundaries around what she felt comfortable sharing with her parents about her T1D. “I let myself have space to have bad days and started celebrating the good. I started celebrating my diaversary and stopped trying to make other people comfortable with what I was going through, because I was the one going through it and I needed to do what I needed to do,” Stover explains.
Mental Health Guide
Check out Breakthrough T1D’s Mental Health Guide, which has everything you need to help you navigate the day-to-day of living with T1D.
A Fresh Outlook on Living With T1D

While Stover’s mindset around T1D evolved over the years, she also feels that mental health resources have improved dramatically since she was a teen. Now, she advocates for people living with T1D to take advantage of therapy or connect with others on social media who are experiencing the same thing. “There’s an entire community of people who decided diabetes wasn’t going to be invisible, and in doing so, more honest conversations can happen,” Stover explains. “We know more about chronic illness fatigue, medical trauma, and the effect of societal pressure to be ‘normal.’ If you go looking, you can find someone talking about it. Validation is a very powerful thing.”
Stover’s fortitude shined through when she was diagnosed with Celiac disease right after she graduated college. This time, things went a little differently; Stover had learned to give herself grace, and she found that figuring out how to manage a second autoimmune disease was a bit easier this time around.
In the years since Stover first started using an insulin pump, diabetes technology rapidly advanced with the evolution of pumps and continuous glucose monitors (CGMs), which, when used together, are called an automated insulin delivery (AID) system. As she grew up, Stover was hesitant to put her trust in new systems. “There are so many nuances to T1D care, and it’s been hard to wrap my head around how technology could know me better than I know myself,” Stover explains.
Yet, she eventually decided to add a CGM to her T1D management toolkit. “It is nice to be able to see how your glucose levels are trending,” Stover said. Despite living with anxiety around technology failures and hypoglycemia, Stover found a way to make CGMs work for her. She has her low alarm set when her glucose levels reach 100 mg/dL—well before the typical threshold of 70 mg/dL—so she can execute a plan of action before her blood sugars drop further. “It’s a little extra peace of mind to know that I can catch a low before it becomes a big problem.”
From kid to adult and all the ups and downs in between, Stover found how to manage her T1D in the way that works best for her.
Breakthrough T1D was (and Still is) Along for the Ride

Stover and her family were connected with other T1D families and Breakthrough T1D from the very start. There was a “tiny but mighty” team of parents who started a Breakthrough T1D Walk in Southern Indiana during Stover’s childhood, which, over time, often included many of her friends and classmates. Over two decades later, the Holiday World Walk in Indiana is still alive and well (and organized by Stover herself!).
In addition to Walk, Stover was a Youth Ambassador. “Breakthrough T1D has been a part of my life almost as much as T1D has. And now, getting to be a part of sharing the Walk with other families is truly a gift,” she says.
Word to the Wise
A word of advice from Stover: T1D is only invisible if you let it be. She encourages people living with the condition to take up space.
“Celebrate your diaversary, bedazzle your Omnipod, rock your fun patterned tapes, celebrate with diabesties. Find little ways to bring joy into it, but also take the time to feel the bad days. Take the time to learn how to let the good and bad coexist.”
Talk about T1D. Take advantage of resources. Connect with others online and in person. Give yourself grace. We can all learn a thing or two from Stover!

“We were never meant to do the job of the pancreas. Everyone carries the weight of T1D differently; everyone processes and grieves differently. There are going to be bad days, and the bad days should NEVER be punished. Grace, compassion, and a safe space to authentically be a person living with T1D will have a much better outcome. The only party at fault is the immune system that attacked the wrong thing.”
-Jessie Stover
Written by journalist Moira McCarthy, a dedicated Breakthrough T1D supporter, advocate, and volunteer.
It’s a sunny midmorning at the Travelers Championship in Cromwell, Connecticut, and J.J. Spaun and I—a golf columnist by trade—have a lot to talk about.
But first, the ritual that takes place every time we spot a “T1D in the wild.” Knowing our shared background—me, a type 1 diabetes (T1D)-mom 29 years into my daughter’s life with this and he, a person with diabetes (PWD) still in his first decade of T1D life—we hug, exchange knowing nods and of course, look at our phone graphs.
J.J. Spaun may just be one of the greatest golfers in the world; his clutch win at Oakmont in the harrowing 2025 U.S. Open raised him to a high level. His follow-up win at Valero this year sealed the deal. But first and foremost, he is one of the tribe: a mere mortal working to fit T1D around his day-to-day life.
Like most of us, he’s had ups, downs, frights, and frustrations. Because diabetes doesn’t discriminate—be you a world champion superstar, the kid just down the road or the full-time cashier at the local five and dime, J.J. Spaun has weathered a lot.
Mentally resilient and tougher
But on this early round day of this popular tournament—one he’d like to win—Spaun tells me that while his T1D diagnosis story is a gritty one, his view of life with the disease is not.
“Diabetes has made me mentally resilient; tougher,” he told me. “It’s easy to look in the face of a tough shot, or the layout of those last holes and think: ‘I’ve done tougher things than this.’ Diabetes gave me that view.”
I get that, I tell him: My own daughter is one of the toughest people I know.
Like her, Spaun isn’t Pollyanna. Because while he chooses to live well despite T1D, he’s had his bumps and he’s open about them.
An unexpected hazard
It all started with a misdiagnosis, one that spanned three years of his life, robbing him of body weight, muscle mass, self-confidence, and health.
In 2018, after a few months of sudden and jarring weight loss and an inability to find energy of focus, he saw his doctor and was diagnosed with type 2 diabetes. Like the athlete he is, he threw himself into his care, tweaking his diet and working on gaining strength. For a few months, it seemed to be working. But then he began a slide that left him 25 additional pounds thinner (weight loss he did not need) and so far from being able to stroke a ball with confidence and strength that he dropped from his prior highest ranking of 56 in the world (he was on his way up quickly) to 584.
He was eating barely any carbs at all and topping his daily calorie count at 1,200, yet his condition failed to improve.
He started to think type 2 diabetes might bring the end of his journey toward golf greatness.
“It was pretty tough,” he remembered. “I was definitely upset. Right when I started to establish myself, and I get this thrown at me.”
Type 1, not type 2
As is often the case, diabetes folks in the wild came to the rescue. First, a friend who is a physician pulled him aside and told him to get to an endocrinologist right away (he was being treated by a primary care physician).
“So I go to the endocrinologist and they do a whole bunch of tests,” he said. “Then he comes in and he says I hate to break bad news but …. You have type 1 diabetes, not type 2.
“I said ‘This is great news!’ After all, now I had my answer.” He needed insulin replacement therapy and a smart way to track his blood sugars. Armed with that knowledge and the guidance of his new endo, he began his long trek back up.
(“You know that misdiagnosis could have killed you,” I commented. His eyes grew wide at hearing someone say aloud what he long realized. “I do. I really do,” he said.)
He had much work to do though: that misdiagnosis had stripped him of weight and muscle; the new body mass he had didn’t fit with the swing physics he’d honed in the lead up to those years.
That’s when a T1D-dad named Andy Bessette, who also happened to be Executive Vice President and Chief Administrative Officer for Travelers, got word of the new (and correct) diagnosis and did what the diabetes community always does: connected, empathized, and then offered support.
“I heard he won the hole 15 ½ challenge and he donated his $10,000 to (what was then) JDRF, and I said holy sh**, why?” he said. “He was in his transition phase (From type 2 misdiagnosis to type 1 care), I matched the donation.”
A special connection
He also sought Spaun out and told him about their special connection: Bessette’s son Chris has T1D.
“I told him, let’s get you connected with Aaron Kowalski, Breakthrough T1D CEO, and get you some doctors names and all you need,” he said.
Armed with more information thanks to Bessette, Spaun forged ahead. By January 2021, he felt things shift toward the positive.
“(With insulin therapy) I was able to have carbs and produce energy so much more. My second event of that year I noticed that not only was I not running out of energy, I had enough energy to once again go to the practice range post round,” he said.
To play well, he learned, it was vital he be in range as he slept overnight, “I feel pretty poorly if I do not,” he said. He tailors pre-match dinners toward that effort.
Managing T1D on and off the course
On course, he keeps a close look at the CGM graph on his phone that the PGA made an exception for him to carry. He still treats with injections (but is pondering semi-automated insulin delivery devices) and swears by peanut butter on wheat bread for long lasting energy and Gatorade for quick acting glucose.
He eats a full meal each pre-round and chooses what to eat based on where his blood sugars have been in recent hours. Overall, he said, it’s working.
The proof is in the record. Spaun went on to win the Valero in 2022, that wildly difficult U.S. Open in 2025 and so far, this year, Valero again. His ranking is back up near 12 and he’s feeling his game is in place.
And in a funny way, he says, golf may have prepared him for life with T1D and vice-versa.
“Golf is such a finicky game, the same as diabetes,” he said. “You work so hard to try and control what is coming at you and then things happen. You have to just power forward and adjust. It’s very much the same in that way.”
A hero who’s one of us
Besette watches him closely—as both a golf enthusiast and a T1D-dad.
“He means a lot to me. And what he has to deal with? It’s hard enough to hit the balls and know the course and all that—he has all the diabetes obstacles as well. I’m so impressed by him.”
When Spaun won the U.S. Open, Besette’s first text to him will make sense to the T1D world.
“I asked him: ‘Were your levels okay?’” he laughed.
T1D—and Bessette’s friendship—also brought him another gift, via connecting him to Breakthrough T1D and the diabetes community as a whole.
“I’ve gotten so many messages from kids, adults, and parents in this community,” he said. “They label me as a hero. Parents tell me that seeing me achieve shows their child that even with diabetes, everything is possible.
“There’s always more to golf, and I think that’s my calling,” he said. We hugged tight, our bond formed for life. And as he walked away to play another round, over his shoulder he smiled and said, “Tell your daughter I’m rooting for her.”
J.J. Spaun is one of us.

