
This past week, the FDA and Sanofi, the maker of Tzield, made an important announcement. Tzield, the first disease-modifying therapy approved for delaying onset of stage 3 type 1 diabetes (T1D) in people with stage 2 T1D, has been accepted into the FDA Commissioner’s National Priority Voucher (CNPV) program for people with stage 3 T1D.
Here’s what it means—and why.
The FDA Commissioner’s National Priority Voucher (CNPV) Pilot Program
The CNPV program aims to accelerate the drug review process for companies aligned with U.S. national priorities that address a large, unmet medical need while maintaining the FDA’s rigorous standards for safety, efficacy, and quality.
This program endeavors to reduce the review time for products from 10-12 months to 1-2 months. However, the program does not guarantee approval and the FDA reserves the right to determine the best course of action for the product’s being reviewed.
On Friday, October 17, the first 9 recipients of vouchers were announced, and Sanofi received one for Tzield in stage 3 individuals.
Why Tzield?
In short: the FDA recognizes there is a large unmet need in the T1D population, and Tzield has the potential to address these needs.
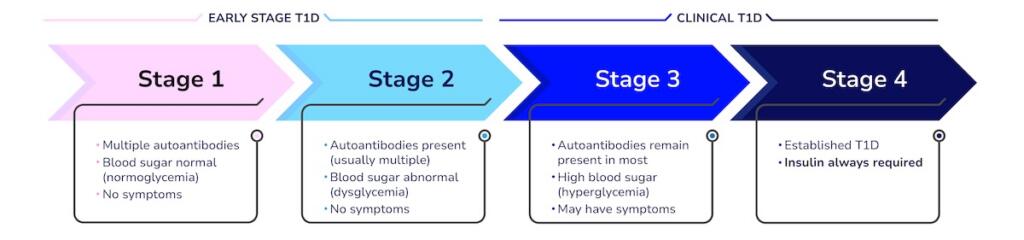
Sanofi’s Tzield is the first disease-modifying therapy approved to delay onset of stage 3 T1D in people with stage 2 T1D. (Stage 2 T1D is indicated by the presence of multiple autoantibodies and abnormal blood sugar levels, but individuals are not requiring insulin therapy yet). Tzield, which has been supported by Breakthrough T1D for decades, has been a gamechanger in T1D as it’s the first therapy for this disease that addresses the root cause of T1D, not the symptoms. It targets the T cells that are responsible for destroying insulin-producing beta cells, slowing down the autoimmune processes that cause T1D. In stage 2, this means a stage 3 diagnosis is delayed an average of 3 years.
The problem: it’s only approved for use in stage 2 T1D. The vast majority of people in stage 2 don’t even know they have early T1D because there are no external symptoms. The only way of knowing is to get screened for risk markers of T1D. While the number of individuals screened for T1D has dramatically risen in recent years, most people who may benefit from the drug progress to stage 3 before they have the chance to reap its benefits—and delay onset.
Additionally, Tzield already being reviewed under the FDA’s accelerated approval program. Sanofi is continuing to study Tzield in this patient population through the confirmatory BETA-PRESERVE phase 3 study, which will provide more information on the risks and benefits of the drug in the coming years.
Breakthrough T1D has supported the development of Tzield for decades—and supports its use in stage 3 T1D.
Preserving beta cell health is critical
T1D is caused by the destruction of the beta cells, which are the only cells in the body that make insulin. The fewer beta cells a person has, the less insulin they make.
Simply put, it’s better to have more beta cells, and longer we can keep those cells alive and making insulin, the better. There are many studies that support this, but one study in particular really demonstrated the benefits.
The PROTECT Study
In the PROTECT study, Tzield was administered to newly diagnosed children and adolescents in stage 3 T1D to see if it could slow the destruction of beta cells as measured by C-peptide. (C-peptide is a natural byproduct of insulin production and a key biomarker as we evaluate the efficacy of Cures therapies).
In this study, investigators looked at newly diagnosed individuals who were administered Tzield compared with placebo and measured their beta cell function (using C-peptide) over time. The results were clear: Tzield significantly slowed the decline of beta cell function. This has real impact on the lives of people with T1D, too. People who received Tzield and therefore had higher levels of endogenous insulin production required less insulin and spent more time in range.
In summary: more beta cells are better. Tzield has demonstrated that it can help achieve that.
What happens next?
Sanofi could hear from the FDA in the next 1-2 months that Tzield has been approved for use in stage 3 T1D. If that happens, it will mean that, for the first time, individuals diagnosed with T1D have a therapy option besides insulin. This would be a historic first, allowing people to benefit from the decline in the loss of beta cells and modify the course of T1D like the PROTECT study has demonstrated.
What we’re saying
“We know two things: there is a large, unmet need in the T1D community for more therapy options, and there is significant data demonstrating the benefits of preserving beta cell health,” said Campbell Hutton, Senior Vice President, Global Advocacy. “Breakthrough T1D applauds the FDA for accelerating the review process of a therapy that can have significant positive impact for the T1D community.”
Just last year, a Breakthrough T1D-funded researcher won the Nobel Prize in Chemistry. This year, the Nobel Prize in Physiology or Medicine went to three immunologists… including one, Fred Ramsdell, who serves as a Scientific Advisor to Sonoma, a T1D Fund company.
Another year, another researcher with ties to Breakthrough T1D winning the most prestigious award in science.
Immune tolerance 101
The recipients, Mary E. Brunkow, Fred Ramsdell, and Shimon Sakaguchi, won the award for “their discoveries concerning peripheral immune tolerance.”
So what exactly is immune tolerance?
The body’s immune system is constantly waging war against microbes, viruses, and other things that could make us sick. However, it’s important to ensure that the immune system is only attacking foreign agents, rather than our own bodies.
Immune tolerance
Immune tolerance refers to the immune system’s ability to distinguish between self and non-self, preventing it from attacking the body’s own tissues.
A key player in this process is regulatory T cells (Tregs), which help suppress immune responses that could harm the body. This was a paradigm shift that started in the late 90’s.
Immune tolerance and T1D
If reading that description made you think, “Well, it sure feels like the Treg cells in people with T1D aren’t doing their job,” you are correct. Through decades of research, we know that Tregs are pivotal in preventing autoimmunity. If we can repair or replace defective Tregs, we can, ideally, halt the progression of T1D.
In T1D, the immune system mistakenly attacks beta cells in the pancreas, which produce insulin. Our work in disease-modifying therapies has two approaches:
1. Suppressing the “bad actors”
Targeting effector T and B cells that attack beta cells. This approach often requires ongoing treatment to maintain suppression (e.g., with drugs like teplizumab, which can delay T1D onset by a median of three years).
2. Enhancing immune tolerance
Enhancing immune tolerance by boosting or inducing Tregs to recognize beta cells as self, effectively retraining the immune system to stop attacking them. We believe this could lead to a long-term or permanent rebalancing of the immune system, potentially halting disease progression rather than just delaying it.
Fred Ramsdell and Sonoma
Fred Ramsdell is a brilliant scientist with deep connections to T1D. He is a cofounder of Sonoma Biotherapeutics, the former Chief Scientific Officer, and currently the Scientific Advisory Board Chair to the company.
Sonoma is focused almost exclusively on immune tolerance. They are developing engineered Treg therapies to restore balance to the immune system to treat autoimmune and inflammatory diseases—including T1D.
The other founders include CEO Jeff Bluestone, Ph.D.—a longtime Breakthrough T1D collaborator who was influential in the development of Tzield—and Qizhi Tang, Ph.D., co-director of the Breakthrough T1D Center of Excellence in Northern California.
A Breakthrough T1D priority
Our immune tolerance work spans every area of our cures research: early detection, disease-modifying therapies, and cell therapies.
Breakthrough T1D is currently funding nearly 40 projects across disease-modifying therapies and cell therapies aimed at rebalancing the immune system through enhancing regulatory mechanisms and providing lasting beta cell protection. (This includes a person’s own beta cells and transplanted cells.)
Importantly, Breakthrough T1D has been funding work to understand the role of Tregs and the development of therapies to enhance regulation for decades, including work by Jane Buckner that identified deficits in Treg number and function in T1D in 2008, opening the door for the first clinical trial of a Treg therapy in T1D in 2011 (funded by Breakthrough T1D).
Congratulations to all the recipients for their incredible work—work that we are applying to T1D so we can hopefully rebalance the immune system for good and get to our goal of cures, soon!
A new study funded by Breakthrough T1D and published in the journal Diabetes Therapy shows that people with type 1 diabetes (T1D) and caregivers are largely willing to try next-generation therapies, drawn by the promise of reduced insulin reliance, greater normalcy, and freedom from constant disease management.
The findings highlight the importance of ensuring patient and caregiver perspectives guide regulatory decisions around the balance of a therapy’s risks and benefits.
The promise of next-gen therapies
Advances in T1D management, such as automated insulin delivery (AID) systems, mark major progress over the past decade. Despite these gains, insulin therapy remains physically, mentally, and emotionally demanding, and substantial unmet needs persist.
Next-generation therapies aim to move beyond insulin replacement through two approaches:
- Disease-modifying therapies (DMTs): Preserve insulin production by slowing or halting autoimmune destruction of beta cells.
- Cell Therapies: Restore insulin production by delivering new functional cells, with the potential for partial or complete insulin independence.
For the study, researchers interviewed people with T1D and caregivers to better understand their perspectives on the risks and benefits of these therapies.
What participants said
Participants expressed willingness to try new therapies, with 92% of adults, 70% of caregivers, and 100% of adolescents saying they would try a DMT at the time of T1D diagnosis. Every participant said they would try cell therapies.
Participants also shared their thoughts on top benefits of both DMTs and cell therapies.
- Top benefits: DMTs: Reduced insulin reliance and an extended period when a
person with T1D produces their own insulin; cell therapies: insulin independence,
more normalcy, and freedom from constant demands on diabetes.
Why this matters
To approve a product, regulators must judge whether the therapy’s benefits outweigh its
risks. This study shows that , people living with T1D and their caregivers have strong view
about which benefits matter and how much they matter. Because DMTs and cell therapies
bring significant benefits compared to insulin therapy, regulators should incorporate these
patient perspectives into regulatory decision-making.
About the study
The Breakthrough T1D Patient Preference Study is being conducted in two phases. In the first phase, researchers interviewed 26 individuals—12 adults, 4 adolescents, and 10 caregivers—about their views on DMTs and cell therapies. These insights are now shaping a large-scale survey that will measure how the T1D community prioritizes different risks and benefits. Results from that survey are expected later this year.
Type 1 diabetes (T1D) doesn’t discriminate. It affects people of all races, ethnicities, ages, and socioeconomic backgrounds. Although its exact causes are unknown, researchers have uncovered type 1 diabetes risk factors that increase a person’s likelihood of developing the condition.
Family history
Having a family history of type 1 diabetes is the highest risk factor for developing the disease—a first-degree relative (parent, sibling, or child) with T1D increases your risk up to 15-fold. However, nearly 85% of diagnoses occur in people who have no family members with the disease.
Breakthrough T1D-funded researchers have tracked data from nearly 8,000 high-risk children to estimate future risk for T1D more precisely in The Environmental Determinants of Diabetes in the Young (TEDDY) study. A family follow-up to this study focuses on screening and monitoring siblings and parents of TEDDY participants, who have an increased genetic risk for T1D. The goal is to enhance early detection and prevention programs, better understand the natural progression of T1D, and potentially identify new genetic markers that can help predict the risk of T1D development.
Early Detection
Thanks to advances in research and a better understanding of the human immune system, we are now able to identify a person’s risk for T1D many years before the onset of symptoms through a simple blood test. Screening can reduce the risk of complications at diagnosis and also help researchers better identify who is at risk. This leads to the development of disease-modifying therapies that can slow, halt, or reverse the progression of T1D.
Age
A person’s age is a type 1 diabetes risk factor. While people can experience the onset of T1D at any age, many are diagnosed in early elementary school or as preteens, with ages 10-14 having the highest occurrence of diagnoses.
Environmental triggers
Research has not found a definite environmental trigger for type 1 diabetes. Viruses and exposure to gluten, cow’s milk, antibiotics, and more have all been extensively studied, yet no certain links have been made. “The evidence has not been conclusive,” says Laura Jacobsen, M.D., Assistant Professor and Pediatric Endocrinologist at the University of Florida. “It may be because there are multiple or different triggers for different subsets of the population.”
Ethnic and geographic triggers
The risk for type 1 diabetes has historically been highest in those with white European ancestry. However, the diversity of the population with T1D is increasing, meaning the risk is going up in minority populations. Research is ongoing in this area to address this increasingly global problem. Visit the T1D Index for a detailed look at type 1 diabetes prevalence around the world.
Geographically, there are countries where the risk of T1D is higher than others, but “ultimately it is underlying genetics that impact risk,” Dr. Jacobsen said.
Researchers are still trying to understand how and why genes and environment are T1D risk factors. Breakthrough T1D continues to fund this research so that, one day, we will be able to prevent, reverse, and cure type 1 diabetes.
ADA Recap Series
This article is the second of our three-part ADA Recap Series. Breakthrough T1D was on site in Chicago, IL from June 20-23 for the American Diabetes Association’s (ADA) 85th Scientific Sessions. We’re here to report on the latest-and-greatest type 1 diabetes (T1D) advancements—including many driven by Breakthrough T1D funding. Look out for tomorrow’s article for updates on Medical Affairs.
Cures
Breakthrough T1D’s Cures program focuses on early detection, disease-modifying therapies, and cell therapies with the goal of working toward effective cures for T1D.
Cell therapies were front-and-center at ADA 2025. We have some exciting clinical trial updates and new ideas for optimizing islet transplantation.
Cell therapies
Autologous cell transplantation
Autologous cells are those removed from an individual and implanted back into the same individual. These cells can be modified in a laboratory before implantation. Autologous cells are still susceptible to autoimmunity in T1D, so cell protection strategies (gene-editing, encapsulation, immune modulation, etc.) are expected to be required.
Allogenic cell transplantation
Allogenic cells are those that are derived from a source other than the recipient, such as deceased donors or precursor-derived manufactured cells. Allogenic cell transplants require immunosuppression because they stimulate an immune response. Breakthrough T1D’s Cell Therapies program is focused on allogenic cells—specifically manufactured cells—because they can be generated at large scale.
One-year updates on Vertex’s manufactured cell therapy, zimislecel
- Presenter: Michael Rickels, M.D. (University of Pennsylvania)
- Zimislecel (VX-880) is a manufactured islet therapy that requires immunosuppression, infused into a vein in the liver in people with T1D who have impaired hypoglycemic awareness and severe hypoglycemic events.
- The phase 1/2 clinical trial, which is part of the pivotal phase 1/2/3 FORWARD-101 trial, is complete. Twelve participants received a single infusion of a full dose of cells and were followed for at least one year.
- All 12 participants achieved the primary endpoint, which was elimination of severe hypoglycemic events and HbA1c levels less than 7%. 10/12 (83%) participants are insulin independent.
- All 12 participants demonstrated sustained insulin production as measured by C-peptide, reduced external insulin therapy use, and achieved greater than 70% time in range.
- There were no serious adverse events. Mild to moderate adverse events were consistent with the immunosuppression regimen, infusion procedure, and complications from T1D.
- These data were published in the New England Journal of Medicine and represent further evidence of the curative potential of manufactured islet transplantation for T1D.
- Breakthrough T1D’s support for Doug Melton, Ph.D.—whose proprietary lab-created beta cells are now being advanced by Vertex—goes back decades, both via research grants and an investment from the T1D Fund: A Breakthrough T1D Venture.
6-month update on Sana Biotechnology’s immune-evasive islets
- Presenter: Per-Ola Carlsson, M.D., Ph.D. (Uppsala University)
- Sana’s donor-derived islet therapy engineered with Hypoimmune (HIP) technology can evade the immune system without immunosuppression.
- These cells were implanted intramuscularly in a first-in-human study into a person with T1D with no measurable insulin production.
- Six months post-transplant, this person is consistently making their own insulin, as measured by C-peptide levels. Yet, they still require external insulin therapy because they received a smaller dose of cells than the dose that would be required to achieve insulin independence. They did not experience any serious side effects, so the cells and procedure are safe and well-tolerated.
- A Mixed Meal Tolerance Test (MMTT) confirmed that these cells are not only surviving but also responding to changes in blood glucose levels.
- This is a promising first step toward a functional cure for T1D that does not require immunosuppression. Sana Biotechnology is planning on applying this technology to manufactured islets.
- Sana has received support from the T1D Fund to advance their HIP technology in islets, and Breakthrough T1D continues to work closely with them.
A new transplantation site for autologous manufactured islets
- Presenter: Hongkui Deng, M.D. (Peking University)
- Cells derived from adipose tissue (fat) can be removed from a person and chemically induced in the laboratory to become islet cells.
- Implantation of autologous manufactured islets into the sub-anterior rectus sheath in preclinical models of T1D improves glycemic control.
- In humans, this implantation site is easily accessible by an ultrasound-guided needle.
- In a first-in-human study, autologous manufactured islets were implanted into this site in a person with T1D. This person no longer needs external insulin therapy and has greatly improved blood glucose control. This person had also received a liver transplant and was taking immunosuppressants.
A new encapsulation device for immune protection of transplanted islets
- Presenter: Nicolas Laurent, Ph.D. (Adocia)
- Adoshell® is a novel islet cell encapsulation device that can shield islets from the immune system, meaning that immunosuppressants are not needed.
- The hydrogel-based device is non-degradable, easily retrievable, and allows the exchange of glucose and insulin from the vasculature surrounding the device while excluding immune cells from encapsulated islets based on pore size.
- This device showed promise in animal models, and human clinical testing is next.

Cell therapies highlight: Breakthrough T1D-funded research
Tom Bollenbach, Ph.D. (Advanced Regenerative Manufacturing Institute; ARMI) presented on challenges and solutions for large-scale manufacturing of islet cells. The goal is to generate scalable, automated manufactured islets that can be used by labs around the world to accelerate research progress using a unique, validated, and reliable cell source. Some challenges include ensuring the manufactured cells can survive shipment from the facility to research labs and maintain their insulin-producing capacity when they are used in different labs. ARMI is working with the Beta Cell Replacement Consortium to address these challenges.
Antonio Citro, Ph.D. (San Raffaele Hospital) presented his work on ensuring that transplanted islets have enough oxygen and nutrients (“vascularization”) to survive and function. Dr. Citro described an approach tested in animal models referred to as “natural scaffolds” in which all cells are removed from a donor organ, such as a lung, leaving behind blood vessel structures and other structural components. Islet cells can be injected and grafted onto this scaffold to create a mini organ of islet cells, which can then be tested for functionality before and after implantation.
Andrew Pepper, Ph.D. (University of Alberta) also presented vascularization strategies to increase the survival and functionality of transplanted islets. The implantation of a biomaterial under the skin will trigger the immune system and initiate a foreign body reaction, which results in the formation of blood vessels and structural components around the foreign object. Removal of the object leaves a hollow pre-vascularized core suitable for islet transplantation. This process can be optimized by using a biodegradable material, so no removal is required, and by the addition of “accessory cells” that help maintain a vascularized environment for islets.
Key takeaways
Cell therapies are making significant headway in clinical trials, and people receiving manufactured cells are becoming insulin independent. Researchers are tackling the biggest challenges for optimizing islet transplantation, including large-scale manufacturing, ensuring cell survival, and preventing detection by the immune system.
Disease-modifying therapies
A major focus at ADA 2025 was addressing the underlying immune mechanisms of T1D—including alterations in immune cells that facilitate beta cell destruction and other factors that contribute to autoimmunity onset. Read on for some highlights.
The role of B cells in T1D autoimmunity
- Presenter: Mia Smith, Ph.D., DVM (University of Colorado)
- B cells are a type of immune cell that can activate destructive immune cells that facilitate autoimmunity in T1D.
- B cells can become wrongly activated against insulin-producing beta cells due to converging dysregulation of factors that regulate immunity.
- These cells represent another potential target for disease-modifying therapies in T1D.
Disease-modifying therapies highlight: Breakthrough T1D-funded research
Emrah Altindis, Ph.D. (Boston College) presented on the role of the gut microbiome in T1D. His studies found that people with T1D tend to have more inflammatory bacteria in their gut microbiome. Dr. Altindis and his team identified a particular bacterial population that can enhance T1D onset in animal models due to changes in immune cells that contribute to T1D autoimmunity. These studies provide insight into additional factors that can drive immune changes in T1D.
Laura Sanz Villanueva, MSc (St. Vincent’s Institute of Medical Research), who works in the lab of Breakthrough T1D-funded researcher Professor Thomas Kay, MBBS, Ph.D., presented on a mechanistic follow-up study to the BANDIT clinical trial. The Breakthrough T1D-funded phase 2 BANDIT study showed that baricitinib, a JAK1/2 inhibitor that prevents immune cell communication, can increase insulin production as measured by C-peptide in people with recently diagnosed T1D. The present study found that baricitinib can reduce the number of natural killer (NK) cells in the pancreas, which are involved in the autoimmune destruction of beta cells. These data provide valuable insight into the mechanism of baricitinib-mediated protection of beta cells.
Key takeaways
T1D is driven by dysregulation of the immune system, which results in an attack on insulin-producing beta cells. Researchers at ADA 2025 spoked about novel factors—including B cells, NK cells, and T1D autoimmunity triggers—that may contribute to immune cell dysfunction in T1D.
Early detection
A key focus at ADA 2025 was the growing recognition of the heterogeneity of T1D, including autoantibody-negative disease onset, genetic variation, and the frequent misdiagnosis of T1D in adults, underscoring the need for greater diversity and inclusion in research and care. The expanded role of continuous glucose monitoring (CGM) and continuous ketone monitoring (CKM) was also highlighted, not only for daily management but as essential tools for understanding disease progression.
Using genetics to predict T1D risk
- Presenters: Richard Oram, M.D., Ph.D. (University of Exeter), Leslie Lange, Ph.D. (University of Colorado), Aaron Deutsch, M.D. (Massachusetts General Hospital), Josep Mercader, Ph.D.(Massachusetts General Hospital) and Eimear Kenny, Ph.D. (Icahn School of Medicine at Mount Sinai)
- Polygenic risk scores (PRS) estimate the risk a person has for developing a disease like T1D based on variations in different genes.
- Ancestry is a major influence on PRS, particularly based on differences in genes that regulate whether the immune system can distinguish between “self” and “non-self.”
- Most PRS models have been developed using data from European populations and have a limited ability to accurately determine risk in other ethnic groups, such as individuals of African and East Asian descent.
- Potential applications of PRS include incorporation into screening to better understand T1D risk, ensure accuracy in diagnostic tests, and develop precision medicine-based therapeutic approaches.
Understanding how genetic diversity contributes to T1D
- Presenters: Suna Onengut-Gumuscu, Ph.D. (University of Virginia), Dominika A. Michalek, MS (University of Virginia), Aaron Deutsch, M.D. (Massachusetts General Hospital), and Stephen I Stone, M.D. (Washington University School of Medicine), among others.
- These talks highlighted several studies conducted in diverse populations to better understand the pathophysiology of T1D.
- Work presented from Consortia, such as RADIANT, focused on rare and atypical forms of diabetes.
Controversies in CGM and benefits for early detection
- Presenters: Peter Calhoun, Ph.D. (Jaeb Center for Health Research), Michael Kohn, M.D., MPP (University of California San Francisco), Nicole Ehrhardt, M.D. (University of Washington) and Tadej Battelino, M.D., Ph.D. (University of Ljubljana)
- CGM use holds value in identifying progression in early stages of T1D prior to symptomatic onset.
- There was a call to update the clinical guidelines so that the benefits of CGM can be maximized within the T1D community—including at early and later stages of T1D.
- Integrating newer measures of blood glucose, like the glucose management indicator (GMI) and time in tight range (TITR), will be essential.
Contributions of CKM to early detection
- Presenters: Ketan Dhatariya, MBBS, M.D., Ph.D. (Norfolk and Norwich University Hospitals), Lori Laffel, M.D., MPH (Harvard University), Jennifer Sherr, M.D., Ph.D. (Yale University), and Richard Bergenstal, M.D. (HealthPartners Institute).
- It will be critical to explore whether ketone monitoring could help reduce the incidence of diabetic ketoacidosis (DKA) at stage 3 clinical T1D onset.
- Early detection of rising ketones will be important for people with T1D to take action before DKA occurs.
Early detection highlight: Breakthrough T1D-funded research and awardees
Brigitte Frohnert, M.D., Ph.D. (Barbara Davis Center for Diabetes), co-investigator with Breakthrough T1D-funded researcher Andrea Steck, M.D., presented on the evolution of CGM patterns prior to stage 3 T1D. Their longitudinal approach, with CGM data collected at three-month intervals, successfully distinguished individuals who progressed to stage 3 T1D clinical onset from those who did not. This research suggests that CGM may be beneficial for predicting clinical progression of T1D.
Anette-Gabriele Ziegler, M.D. (Helmholtz Munich) was awarded the Harold Hamm Prize for Biomedical Research in Diabetes 2025, highlighting her important contributions on T1D screening in the pediatric population.
Barbara B Kahn, M.D. (Beth Israel Deaconess Medical Center and Harvard Medical School) received the 2025 Albert Renold Award, and her role model for women in science was highlighted at the Women’s Interprofessional Network of the ADA (WIN ADA).
Key takeaways
T1D arises in diverse ways across age groups and ancestries, complicating diagnosis and treatment. At ADA 2025, experts highlighted how genetic and clinical heterogeneity demands more inclusive strategies. Tools like CGM and CKM were highlighted for their potential to enhance clinical management in the early stages of T1D.

Breakthrough T1D’s Cures team making an impact
Sanjoy Dutta, Ph.D., Chief Scientific Officer, participated in a panel discussion titled “Encapsulation vs. Naked Cell Therapy—Immune Challenges and Beta-Cell Perspectives in Diabetes Treatment.” The panelists covered different approaches to preventing immune attack of transplanted islets, including gene-editing, in addition to pros and cons of different transplantation sites.
Esther Latres, Ph.D., Vice President of Research, and Jay Tinklepaugh, Ph.D., Senior Scientist, hosted a workshop immediately after ADA titled “Islet Cells in T1D.” Breakthrough T1D-funded researchers gathered from around the world to discuss cell therapy clinical trial updates, mechanistic insights into islet function, targeted delivery of therapeutics to beta cells, and optimization strategies for islet transplantation.
Look out for tomorrow’s article for an update on Medical Affairs presented at ADA 2025!
After months of unexplainable symptoms, Katie Howell was diagnosed with type 1 diabetes (T1D) last year at age 25. Read on to learn more about how she confronted her new reality and became the first participant in New York City to enroll in the DIAGNODE-3 clinical trial.
The unexpected diagnosis

Katie Howell, a Mississippian-turned-New Yorker, has a wide array of hobbies: crafting pottery at her local ceramics studio, enjoying old movies in the theater, cozying up with a book in Prospect Park, and taking in the sun at Rockaway Beach. Katie moved to Brooklyn after completing a Master of Public Administration degree at the University of Tennessee, Chattanooga, and she’s thoroughly enjoying getting to know her new neighborhood.
Suddenly, things took a turn. Last year, Katie started experiencing symptoms of something unknown—for three months, she had no idea what was going on with her body. Then, in a moment of complete shock, 25-year-old Katie was diagnosed with type 1 diabetes (T1D). “Without a family history of T1D and without any health issues of my own, being diagnosed with a sudden, serious chronic illness could not have been more unexpected,” Katie explained.
At the time of her diagnosis, Katie was confronted with a flood of emotions. There was not a single person in her life that had T1D or could understand her experience. “…one of the most challenging parts of being diagnosed with a chronic illness is accepting it […]. This comes with a lot of hopeless feelings, and it is tough to surrender control to an incurable, pervasive, and expensive health condition,” Katie lamented.
Feeling alone and lost, she had no choice but to accept that she was dealing with a major life change—whatever that meant for the future.
Influenced
It wasn’t long before Katie took to social media to learn more about her diagnosis and connect with the T1D community. On Instagram, she stumbled upon Lauren Bongiorno, a T1D influencer. Ms. Bongiorno posted a video promoting DIAGNODE-3, a phase 3 clinical trial for the disease-modifying therapy Diamyd® for early-stage T1D.

Katie found that DIAGNODE-3 was enrolling at The Pediatric Diabetes Center at Hassenfeld Children’s Hospital at NYU Langone. After reaching out to the team at NYU, she realized that the stars had aligned: they had just opened enrollment, and after completing the necessary screening, Katie would be Participant Number One.
“It gets easier every visit!”

Katie received her first study injection in January and will get her third and final injection this month, followed by routine check-ins. This includes blood work, physical exams, and mixed-meal tolerance tests to measure her body’s ability to produce insulin.
As per the study protocol, Katie doesn’t know if she’s receiving the placebo or the study drug, Diamyd®. Still, she likes being in the study: she’s made meaningful connections with the trial team, has learned a lot about T1D, and feels that she’s making a difference—not just for herself, but also for biomedical research.
Katie’s biggest hurdles? Bloodwork and hospitals. “One challenge of this study is the routine blood work and being treated at the hospital. However, it does feel like exposure therapy. It gets easier every visit!” she exclaimed.
Finding her community
Since her diagnosis, Katie has made lasting relationships with others in the T1D community. She connected with the Greater New York Metro Chapter of Breakthrough T1D after volunteering at a Walk in NYC last fall. They introduced her to a group chat with other newly diagnosed young women, where they can ask questions, network, and learn from each other as they navigate their new realities.

“My advice to someone considering [the DIAGNODE-3] trial would be that, though the study is a commitment and an undertaking, they are taking part in discovering medical breakthroughs and T1D treatment research.”
Katie Howell
Participate in clinical trials
Clinical trials are key to bringing medical advancements from the lab to the clinic. This wouldn’t be possible without brave people with T1D, like Katie, who volunteer to participate. These studies offer the potential for life-changing treatment and move the ball forward for the T1D community.
Use our Clinical Trials Matching Tool to find a trial near you. Connect with a Clinical Trial Education Volunteer in your area to learn more about trial participation and answer any questions you may have.

When Tzield was approved by the United States Food and Drug Administration (FDA), the type 1 diabetes (T1D) community had real cause to celebrate: The first disease-modifying therapy for T1D had cleared one of the last major hurdles to becoming available.

Disease-modifying therapies
Also "DMTs" for short, these therapies prevent, slow, halt, or reverse T1D progression.
But once Tzield was on the market and covered by health insurance companies and other payers, a new hurdle emerged: a majority of healthcare providers across the country were unaware of the drug, let alone how to administer it.
The clinical guideline for Tzield infusion did not become available until a year and a half after the FDA approved the drug. To date, 500 people in the U.S. with early stage T1D have received Tzield. Compare that to the annual incidence rate of T1D in the U.S. according to the T1D Index:
According to a 2023 study in the journal Diabetes Technology & Therapeutics, Tzield isn’t the only advanced T1D therapy with a surprisingly low adoption rate.
The FDA approved the first artificial pancreas (AP) system in 2016. Less than a decade later, there are now eight such approved systems on the market. These systems—also called automated insulin delivery (AID) systems—lead to better T1D management and health outcomes—yet only 16 percent of people with T1D in the United States use them.
Similarly, the FDA approved Lantidra, the first donor-derived cell therapy for T1D, in 2023. To date, one person has received it.
Increasing adoption to improve health
Closing the gap between access to and adoption of T1D therapies is a mission priority for Breakthrough T1D.
“It’s similar to the question: ‘If a tree falls in the forest and no one is there, does it make a sound?’” said Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES, Associate Vice President of Breakthrough T1D’s Community Screening and Clinical Trial Education programs. “In this case, if you have a cutting-edge new therapy but most healthcare providers don’t know about it, don’t prescribe it, and don’t know how to administer it, does it have an impact?”
The organization recently announced the establishment of a Medical Affairs unit. The team will address the numerous challenges contributing to the slow adoption of groundbreaking T1D therapies, delaying their life-changing potential for many people living with the disease.
Challenges we are addressing:
HCPs have much greater knowledge of type 2 diabetes—or T2D—which is more prevalent.
HCPs need comprehensive guidelines to support new, approved treatment options.
There are too few clinical environments with the equipment and expertise to administer advanced T1D therapies and treatments, such as new T1D devices, therapies that require infusions like Tzield, and treatments that require implantation, such as cell therapies.
There are too few endocrinologists and certified diabetes care and education specialists with knowledge and competency in advanced T1D therapies.

With the establishment of our Medical Affairs team, we are reaffirming our organization’s commitment to creating a world where every individual with type 1 diabetes has access to life-changing therapies. By addressing systemic barriers and fostering clinical readiness, Breakthrough T1D will be pivotal in driving the timely adoption of emerging therapies and transforming care.”
As part of this organizational change, the Community Screening and Clinical Trial Education team, led by Albanese-O’Neill, will be integrated into Medical Affairs.
The team will focus on developing education materials for healthcare professionals in the U.S. and around the world; empowering people with T1D to participate in shared decision-making with their healthcare teams about emerging T1D therapies; helping to establish and socialize clinical care guidelines tailored to regional needs; and expanding clinical trial participation through community activation and HCP education.
“We have been doing a great deal of work to expand our HCP education, T1D community screening, and clinical trial education programs for more than three years now,” said Albanese-O’Neill, who has been with Breakthrough T1D as a fulltime staff member since 2022. “Given what we are seeing with adoption rates and with Dr. Danne joining us, we are now putting all of this work together in one department with a more strategic approach.”

Empowering clinicians with education
The team recently launched comprehensive, expertly redesigned HCP education and training resources.
These resources—which are accredited, free-of-charge, and live or on-demand—offer a significant focus on early detection for the earliest stages of T1D, monitoring guidance for positive test results, clinical trial opportunities, and the latest on cutting edge T1D therapy research and development, including disease-modifying therapies and islet cell therapies.
While designed specifically for healthcare professionals who can earn 4.5 credit hours of continuing medical education, the resources are available to the public. The on-demand feature means busy healthcare professionals with schedules that include all kinds of shifts imaginable can access this turn-key resource on their own time.
For a deeper dive, Breakthrough T1D’s resources will also offer live sessions, allowing time to interact with and learn from leading experts in the T1D field, including Albanese-O’Neill and Danne, in addition to those affiliated with different clinical facilities and institutions across the nation.

Our goal is to make this education as accessible as possible.”
Detecting T1D before symptoms present
A simple blood test can detect T1D in the earlier stages—before obvious symptoms develop. The biggest challenge is educating clinicians and the general population about it.
“Endocrinologists, Pediatricians, and some other specialty physicians learn about T1D screening and monitoring during their residencies, but it’s not a part of the general curriculum of the first four years of medical school,” said Lally, who built the learning management system for the new resources and is organizing the virtual offerings. “We’re working to advance that knowledge to yes, doctors, but also other clinicians whose patients could benefit.”
Many clinicians hesitate to order unfamiliar tests—especially if they are unsure what to do with the results. Most people who see any kind of healthcare provider could benefit from screening for T1D—according to a paper published in the journal US Endocrinology, roughly 85 percent of people diagnosed with type 1 do not have a blood relative with the autoimmune disease.
“Clinicians need to learn about the stages of type 1 and the specific autoantibody tests that identify type 1 versus type 2 and identifying type 1 in individuals at risk before they need insulin,” said Colleen Buggs-Saxton, M.D. Ph.D.
Buggs-Saxton, a Pediatric Endocrinologist at Wayne Pediatrics in Michigan, is the clinical leader of a Breakthrough T1D Early Detection pilot clinic. Using the new resources, she and Albanese-O’Neill are going to lead a grand rounds about T1D early detection at her institution, which is affiliated with the Wayne State University School of Medicine and healthcare system.

Clinicians should consider autoantibody testing for adults who have been diagnosed with type 2 but don’t have typical clinical features and require insulin to manage their blood sugars.”
“This is a novel way these resources can be used—as the basis of a locally and or virtually-provided grand rounds,” said Albanese-O’Neill.
While much of the emphasis of T1D early detection programs has been on children and teens, its applications are much broader—anyone can develop T1D at any age and unfortunately, misdiagnoses happen. According to an article published in the journal The Lancet, Regional Health: Europe, it is estimated that nearly 40 percent of adults older than age 30 with T1D may have been misdiagnosed with T2D.
“Most clinicians are very comfortable ordering an HbA1c test to classify people with type 2 diabetes, but they do not know what tests to order to classify people with type 1,” added Buggs-Saxton.
Grand rounds
Grand rounds are educational meetings and presentations for clinical teams at a given institution or healthcare facility to provide a summary of updates to the standards of care.

What to do with positive test results
The screening test is just the first part of T1D early detection. Clinicians also need to know what to do with positive results once they come in. Breakthrough T1D’s HCP resources offer extensive education on the topic.
Less than one year ago, Breakthrough T1D and other leading diabetes organizations developed monitoring guidance to help clinicians support people who test positive for stage 1 or stage 2 T1D. The guidelines have been endorsed by leading medical journals and organizations around the world.
”This monitoring guidance can help any clinician feel confident in providing adequate care in the early stages of type 1 and know when to refer to a specialist,” said Albanese-O’Neill.

I think of research, advocacy, and medical affairs as three legs of a stool—in terms of clinical adoption, each helps answer a different question. Research: Does it work? Advocacy: Will the regulators approve it and will insurance companies cover it? Medical Affairs: Do clinical teams have the competency and readiness to prescribe the treatment and educate and support people with T1D?”
It’s also helpful for the people who test positive for early stage T1D. Using the monitoring guidance, people can work with their healthcare team to monitor blood glucose levels to identify when insulin therapy may be needed; consider participating in clinical trials of disease-modifying therapies in development; and consider when and whether Tzield might be appropriate.
“There is currently one FDA-approved disease-modifying therapy for early-stage type 1 diabetes and additional therapies are being studied in clinical trials,” said Lally. “Identifying type 1 early gives the individual and their family time to learn more about type 1 and their options before reaching stage 3 T1D, which requires daily insulin therapy.”

Clinical trials: Increasing patient referrals
Clinical trials are a vital step for any treatment, drug, or device to make it into the hands of people with T1D. Currently, more than 300 clinical trials focused on T1D are actively recruiting participants.
Moreover, clinical trials can offer people the chance of receiving a cutting-edge treatment they may not otherwise be able to access.
Through its HCP resources and existing clinical trial resources, Breakthrough T1D is stressing the significance of investigational T1D therapies—while also clarifying common misconceptions about clinical trials.
“The clinical trial education portion of the program explains current trial opportunities and the critical need to increase diversity in diabetes research,” said Lally.
Despite the importance of clinical trials, many are delayed due to slow enrollment, adding cost and prolonging the results. A 2020 Tufts University study found that nearly 90 percent of clinicians surveyed felt comfortable talking about clinical trials.
“Unfortunately, the survey also revealed that annually, fewer than one percent of patients are referred to clinical trials,” said Lally.
So, why aren’t more clinicians referring their patients to clinical trials? Time and resources.

The most challenging part is helping patients understand what a clinical trial is, what it involves, and how previous scientific advances were only possible because of clinical trials. Healthcare providers often don’t have enough time in their busy clinics to discuss this with patients and families.”
Jacobsen, who is with University of Florida Health (UF Health), is one of the faculty members for Breakthrough T1D’s new HCP resources—specifically, the offering related to currently recruiting clinical trials for T1D disease-modifying therapies.
Jacobsen stresses that families and individuals with T1D also need specific education on the potential of receiving a placebo during a clinical trial—and why it’s an impactful part of any clinical trial.
Clinicians also may not know how to quickly get and stay up to date on current trial opportunities and how to get individuals who test positive for T1D autoantibodies involved.
“We provide a streamlined presentation about how to talk to families of people with T1D or people at risk for T1D about clinical trials,” explains Jacobsen, “We can direct families to one of several websites for more detailed information, like Breakthrough T1D’s Clinical Trial Finder.”

Cell therapies: Cures within reach
Cell therapies are one of the most promising approaches to curing T1D and one of the cornerstones of Breakthrough T1D’s cures research portfolio.
Advances in cell therapies have ramped up in recent years: participants in clinical trials of these therapies have been able to stop taking insulin. To speed this progress even more, Breakthrough T1D recently launched Project ACT (Accelerate Cell Therapies).
Cell Therapies
Also called islet cell therapies, these therapies replace destroyed beta cells so that people with T1D can again produce their own insulin.
The organization has long invested in cell therapy research and has a track record of success in making life-changing T1D therapies a reality—the prime examples being artificial pancreas systems (AP systems) and Tzield.
The work of Breakthrough T1D’s Research, Advocacy, and Medical Affairs teams—in partnership with the organization’s venture philanthropy fund, the T1D Fund—will be integral to Project ACT’s success.
Like AP systems, Tzield, and all other FDA-approved drugs, treatments, and medical devices on the market today, islet cell therapies will only become available after meeting all the required benchmarks—including clinical trials.
Clinicians who are in-the-know about clinical trials and how to help their patients enroll are but one of the numerous ways Breakthrough T1D’s Project ACT will make islet cell therapies a reality, faster.
“Clinicians are generally the most trusted source for this information, but most are not making those referrals, so the gap never closes,” said Lally. “We aim to change that.”
“We want every member of the diverse T1D community to be aware of clinical trials, how to participate, and where to find information,” added Albanese-O’Neill. “The next generation of breakthroughs depends on it.”
Editor’s note: This story co-written by Ginger Vieira, special contributor to Breakthrough T1D.
The “who” of clinical trials
People with type 1 diabetes (T1D) who choose to participate in clinical trials are central to determining whether a new treatment is effective and safe. Yet have you ever wondered who operates behind the scenes of clinical trials?
There are scientists that have researched a new drug or device for years, sometimes decades. There are healthcare professionals (HCPs) that oversee the trial at each location, administer treatments, and monitor participants’ health. There are study coordinators that manage the volunteers. There are pharmacologists, biostatisticians, ethicists, writers, and countless others who analyze and publish the data for the scientific community. It takes a village!
Focus on Hassenfeld Children’s Hospital at NYU Langone
The Pediatric Diabetes Center at Hassenfeld Children’s Hospital at NYU Langone is part of the world-renowned NYU Langone Health system, which also has adult programs for diabetes. Diamyd Medical specifically chose NYU Langone as a trial site for DIAGNODE-3.
DIAGNODE-3 is a Breakthrough T1D-funded phase 3 clinical trial of the disease-modifying therapy Diamyd®. The goal is to preserve as many healthy beta cells as possible to maintain the body’s own insulin production.
The team at Hassenfeld Children’s Hospital managing DIAGNODE-3 is led by Mary Pat Gallagher, MD, the Principal Investigator, Director of the Pediatric Diabetes Center, and associate professor in the Department of Pediatrics at NYU Grossman School of Medicine. With many years of experience under her belt, she has been involved in previous clinical trials for Diamyd®, making her a perfect fit for this final stage of testing.
The team also includes pediatric endocrinologist Dr. Casey Berman, the Sub-Investigator, in addition to Jeniece Ilkowitz, RN, CDCES, and Aashna Shah, who are the study coordinators.
I have a personal and family connection to T1D, and research allows me to have both an impact on the greater community as well as individuals.”
Managing T1D is a team effort—the clinical researchers behind the scenes want to make the process as smooth as possible for those who choose to participate in trials.
“We have a wonderful research team with people who also live with diabetes,” Jeniece continued. “You will receive extra support as you learn to live with your new diagnosis, as we will support you as well as communicate with your primary diabetes provider.”
A deeper dive into the science
Diamyd® is an immune modulator that prevents attack on the body’s insulin-producing beta cells by reprogramming the immune system to ignore GAD (glutamic acid decarboxylase). In T1D, GAD can give rise to autoantibodies, which tell the immune system to destroy beta cells.
This therapy is targeted toward people with newly diagnosed T1D who also have the genetic marker associated with GAD —about 40% of the T1D population.
Diamyd® works by injecting GAD directly into lymph nodes, where immune cells live until they’re needed. If certain types of immune cells are exposed to GAD over and over again, they eventually become tolerant and stop destroying the beta cells.
DIAGNODE-3: The phase 3 trial
Researchers are now testing Diamyd® in phase 3 clinical trials (DIAGNODE-3), the final step before seeking approval from the U.S. Food and Drug Administration (FDA). Results from previous trials have been so promising that Diamyd® has received Fast Track Designation and Orphan Designation from the FDA, solidifying it as a potentially life-changing disease-modifying therapy for newly diagnosed T1D.
To participate in DIAGNODE-3, you must be between 12-28 years old and have been diagnosed with stage 3 T1D within the last six months, meaning you have symptoms associated with high blood sugar and require insulin therapy. You also must test positive for a specific genetic marker (HLA DR3-DQ2) to participate.
Over a two-month period, participants will receive three ultrasound-guided injections into a lymph node located in the groin, followed by a 22-month follow-up. A topical anesthetic can be used as required. While a mild reaction at the injection site (itching, redness, etc.) is expected, to date none of the participants in all the trial phases has discontinued treatment due to injection issues.
For every two participants receiving Diamyd®, one will receive a placebo (a treatment with no therapeutic effect for comparison). Researchers will measure C-peptide, a lab test that shows a person can still produce their own insulin, in addition to HbA1c and continuous glucose monitor (CGM) data to determine whether the drug is working. Based on previous trials, researchers predict that Diamyd® will significantly improve blood glucose management, reduce risk of complications, and overall increase quality of life.
We need your help—get involved!
Clinical trials are critical to get new medicines from the lab into the clinic in a safe and effective way. We know that trials are daunting—signing up to receive a treatment that’s still under investigation can be a difficult decision. Yet, if you choose to participate in a clinical trial, you can have access to new therapies and knowledgeable clinicians, learn more about T1D, and benefit the broader T1D community. Also, because there are only 13 DIAGNODE-3 clinics in the U.S., you may be eligible to receive travel reimbursement.
Meet the team and get screened!
Still feeling unsure? Jeniece, one of the study coordinators at Hassenfeld Children’s Hospital at NYU Langone, suggests starting simple.
“As you wait for the results, you can speak to family and friends with the added knowledge as well as think about your life and how this can fit into it,” she explained. “We truly want to help people living with diabetes and be able to have as many options as possible to help them manage their disease in the future.”
Learn more about DIAGNODE-3 by visiting the study’s website. While there are 60 clinic locations in the U.S. and Europe and more than 200 people with T1D enrolled so far, only one person has enrolled at NYU Langone. If you or anyone you know in the NY Metro Area would be interested in participating, please contact the research team at NYU to learn how to get involved. They are recruiting throughout 2025.
Breakthrough T1D’s role
A pillar of Breakthrough T1D’s Cures Program is disease-modifying therapies: those that can slow, halt, or reverse the course of T1D, such as Diamyd®. These interventions are most impactful at the earlier stages of T1D with the hopes of preserving as many beta cells as possible so that the body can produce its own insulin.
Breakthrough T1D’s funding of the DIAGNODE-3 clinical trial aligns with our dedication to early detection and screening. Identifying the presence of T1D autoantibodies as early as possible allows for a larger window of intervention and increases the chances of preserving healthy beta cells with disease-modifying therapies. While DIAGNODE-3 is the first therapy to target a specific genetic subpopulation of T1D, we anticipate that it won’t be the last, which underscores the importance of getting screened to understand your genetic T1D background.
DIAGNODE-3 is just one of the many different clinical trials that Breakthrough T1D funds.
To promote education and awareness of clinical trials, Breakthrough T1D has assembled a group of Clinical Trial Education Volunteers (CTEVs) who engage with the T1D community.

One CTEV, Alecia Wesner, used her expertise and personal experience with T1D to connect Diamyd Medical, the NYU Pediatric Diabetes Center, the Breakthrough T1D NY Metro Chapter, and Breakthrough T1D National, bringing together critical players who can facilitate participation and spread the word about the DIAGNODE-3 clinical trial.
Without people like Alecia, getting the message out about potentially life-changing trials would be far more difficult. We thank Alecia for her efforts and the clinical trial participants of the T1D community for moving science forward for the benefit of all.
While we look back on 2024, we can reflect upon the incredible progress we’ve made in advancing breakthroughs toward cures and improving everyday life with T1D.
This wouldn’t have been possible without each and every one of you and your continued support of our mission as we drive toward cures for T1D.
Here are the top 11 advances that together, we made happen in 2024:
Breakthrough T1D announced the launch of Project ACT, an initiative aimed at accelerating breakthroughs in T1D cell replacement therapies that do not require broad immunosuppression. Recent advances, such as Vertex’s stem cell-derived islets, have been made possible by Breakthrough T1D’s Cell Therapies program as part of our drive toward cures. The goal of Project ACT is to push research, development, regulatory policies, access, and adoption to increase the rate at which cell therapies without the need for broad immunosuppressants will become available to people with T1D.
Why this matters: Immunosuppressive drugs are a barrier to access to cell replacement therapies because of their toxic side effects, which is why islet transplants are currently only available to people with severe low blood sugar (hypoglycemic) unawareness and episodes. By striving toward a future where we realize the benefits of cell replacement therapies without the downsides of the current regimen of immunosuppressants, we will make islet replacement therapies broadly accessible to the T1D community.
Vertex’s clinical trial of VX-880, a first-generation stem cell-derived islet replacement therapy for people with severe hypoglycemia (requiring the use of immunosuppressants), has transitioned into a phase 1/2/3, or pivotal, trial. This news comes after Vertex shared incredibly promising data in the earlier phases of the trial, including 11 of 12 participants reducing or eliminating the need for external insulin.
The upcoming trial will expand to 50 people who will get a single, target dose of VX-880. The primary endpoint will be insulin therapy independence without severe hypoglycemic events after one year. This is the final clinical testing stage before Vertex can seek FDA approval.
Breakthrough T1D has a decades-long relationship with Vertex and the leading scientists behind stem cell-derived islet therapies, an advancement that would not have been possible without Breakthrough T1D funding and support. The T1D Fund had invested in Semma Therapeutics, which was acquired by Vertex Pharmaceuticals in 2019, eventually leading to the active clinical development of VX-880 in T1D.
Why this matters: This is the first time a scalable cure for T1D is entering phase 3 clinical trials—a significant win and a huge step toward accelerating the delivery of cell therapies to members of the T1D community!
Tegoprubart: Transplant Survival Without Standard Immunosuppressive Drugs
Tegoprubart, an anti-CD40L immunotherapy that limits the immune response, is being tested in a Breakthrough T1D-funded study in people with T1D and severe hypoglycemia who have received deceased donor islets. Eledon Pharmaceuticals announced promising initial results in which two of three people achieved insulin therapy independence. According to the study, tegoprubart is safer for both people and transplanted cells in comparison to broad immunosuppressants, with milder side effects and greater islet survival. To further support this effort, the T1D Fund: A Breakthrough T1D Venture invested in Eledon.
Cell Pouch: A Home for Transplanted Islets
Breakthrough T1D has been supporting the development of Cell Pouch, an implantable device from Sernova that provides a safe, immune-protected environment for transplanted islet cells. In phase 1/2 clinical trials, all six people who received donor islets within the Cell Pouch achieved sustained insulin therapy independence with immunosuppressants, including long-term islet survival and function over five years without harmful side effects.
Why this matters: Standard of care immunosuppressive drugs that help avoid transplant rejection come with unwelcome side effects, such as increased risk of infection and malignancy and toxicity to kidneys, nerves, and islet cells themselves. Breakthrough T1D is focused on finding alternative ways to keep transplanted islet cells alive and healthy so that cell replacement therapies can become more tolerable and accessible.
In a major effort spearheaded by Breakthrough T1D, the first internationally recognized clinical guidelines for those who test positive for T1D autoantibodies have been published. These include guidance on monitoring frequency, education, and psychosocial support in addition to recommended actions for healthcare professionals (HCPs) when the risk of T1D progression is high. The guidelines were cooperatively developed with over 60 international experts spanning ten countries.
Why this matters: Previously, there had been no consensus on monitoring guidelines for people who test positive for T1D autoantibodies. Standardization of clinical recommendations means that individuals, families, and HCPs have tangible next steps to monitor early T1D progression and catch life-threatening complications sooner.
- Breakthrough T1D is leading a campaign to secure a recommendation for T1D screening from the U.S. Preventative Services Task Force (USPSTF), the main authority for preventative care. Approval would require T1D screening to be covered by insurance—an important step forward in expanding access.
- Driven by Breakthrough T1D’s advocacy efforts, The Centers for Medicare and Medicaid Services (CMS) established a unique ICD-10 code for stage 2 T1D. ICD-10 codes are used by HCPs to classify and document diagnoses, symptoms, and procedures. These codes provide a unified way for doctors and providers to indicate what diseases or conditions a person has in their electronic health record (EHR), empowering HCPs to document accurate diagnoses and provide the best possible care.
Why this matters: T1D early detection is critically important to prevent life-threatening complications at diagnosis and to give people necessary resources to make informed decisions about their health. Integrating T1D screening into the U.S. healthcare system will increase access to care.
The past year has seen some important advances in glucose management therapies and devices:
- Cadisegliatin, an activator of a blood sugar regulator in the liver, is being investigated in a phase 3 clinical trial (TTP399) as an adjunct therapy to insulin for people with T1D, although it is currently placed on clinical hold. vTv Therapeutics, the trial sponsor, is also a T1D portfolio company.
- The Omnipod 5 app is now available for the iPhone, making it easier to control the Omnipod without the need to carry a controller. It can also integrate with the Dexcom G6 continuous glucose monitor (CGM).
- Eversense 365 is the first FDA-approved year-round sensor that can easily integrate with automated insulin delivery (AID) systems. Other sensors require replacement after 10-14 days.
Why this matters: While advancements in glucose management have been pivotal in improving health outcomes for people with T1D, access remains a challenge. AID systems are globally underutilized, and not everyone has the necessary technology to connect devices. Breakthrough T1D is working to not only support advances in glucose management but also increase access.
Related content: While Breakthrough T1D consistently strives to improve the lives of those living with T1D, as an organization we have made incredible progress in the development of AID systems, also called the artificial pancreas systems. Read a historical perspective written by Breakthrough T1D volunteer Doug Lowenstein that covers conception to FDA approval of the first artificial pancreas systems, which changed the lives of people with T1D.
An inquiry spearheaded by the Breakthrough T1D affiliates in the U.K. uncovered risks of developing T1D eating disorders (T1DE), including bulimia, anorexia, or insulin restriction to lose weight. There is a significant gap in education and clinical guidelines for HCPs, a lack of internationally recognized criteria for T1DE diagnosis, and insufficient care integration, leading to preventable complications and healthy years of life lost. Breakthrough T1D recognizes the importance of spreading awareness and support for T1DE, and much work is needed to improve the lives of those living with T1DE.
Why this matters: There is an urgent need to change the way T1DE is approached, including integrated physical care with mental health services to get people with T1DE the access to care that they need.
In a study that included people with T1D, finerenone (Kerendia®) has been shown to improve cardiovascular outcomes in adults with heart failure. The drug is already approved in the U.S. to treat kidney and cardiovascular disease in people with T2D. Based on these results, Breakthrough T1D is supporting a clinical trial (FINE-ONE) in conjunction with Bayer to investigate the use of finerenone for T1D with the hopes of reducing kidney complications.
Why this matters: Kidney and cardiovascular disease remain significant challenges for those with T1D, especially given the FDA’s recent rejection of an SGLT inhibitor to lower blood glucose in people with T1D and chronic kidney disease. Yet, a new clinical trial (SUGARNSALT) will better assess the benefits versus risks.
Breakthrough T1D is advocating for the regulatory approval of C-peptide, a biomarker for insulin production by beta cells, to be used as an endpoint in clinical trials. An endpoint can accurately predict a meaningful benefit in clinical trials for disease-modifying therapies (DMTs; treatments that can slow, halt, or reverse T1D). To support this endeavor, Breakthrough T1D scientists and an expert consensus panel published research with evidence supporting C-peptide as an endpoint. Breakthrough T1D is continuing to engage with regulators, coordinate with industry, and assess more clinical trial data to drive this effort forward.
Why this matters: Current clinical trial endpoints (HbA1c, hypoglycemia, and complications) are not the best way to gauge the clinical benefits of T1D therapies. If C-peptide gets regulatory approval to be used as an endpoint, clinical trials could be smaller and shorter while still accurately assessing the advantages of a DMT. This means that drug development can move more quickly, and people with T1D will be able to access therapies sooner.
Related content: Two years ago, the T1D community received the incredible news that Tzield® had become the first FDA-approved disease-modifying therapy that can significantly delay T1D onset. Breakthrough T1D volunteer Doug Lowenstein recounts the life-changing drug’s journey nearly 100 years after the discovery of insulin.
The T1D Index is a data simulation tool that measures the global health impact of T1D, bridging gaps in our knowledge of public health statistics. T1D Index 2.0 has new and improved functionality, including advanced simulation capabilities, validation of data, and enhanced user experience. Breakthrough T1D contributed to both the development and improvement of the T1D Index.
Why this matters: The T1D index is critical in defining the intercontinental scope of T1D, driving us toward country-specific solutions and improved global health outcomes.
Earlier this year, JDRF rebranded to Breakthrough T1D. While our mission remains the same, our name needs to better reflect who we are and where we’re going. Our new brand aligns with our mission to accelerate life-changing breakthroughs for those of every age living with T1D as we work toward a world without it.
Why this matters: The proof is in the name—each day we strive to increase and accelerate breakthroughs in T1D, and it’s critical for our brand to accurately reflect our mission.
It’s certainly been an exciting year! While we still have more work to do, it’s crucial to celebrate our wins, both big and small, to see how far we’ve come in our push to make T1D a thing of the past.
Together, we’re accelerating breakthroughs for people with T1D, and the support of the T1D community drives our mission forward every single day, leading the way to lifechanging therapies and cures. Let’s see what 2025 has in store!
It’s early October, which means the Nobel Prizes are being awarded in several categories. These prestigious awards recognize outstanding contributions in Peace, Literature, Physics, Chemistry, Physiology or Medicine, and Economic Sciences. They go to the best and brightest people with the best and brightest ideas.
This year, the prizes recognize work that is, in several ways, connected to Breakthrough T1D and the work we are doing to cure type 1 diabetes (T1D) and improve the lives of those living with it.
microRNAs
The 2024 Nobel Prize in Physiology or Medicine was awarded to Victor Ambros and Gary Ruvkun for the discovery of microRNA and its role in post-transcriptional gene regulation.
But what is it?
The DNA in our body has between 20,000 and 25,000 genes. Our body constantly activates those genes, which allows it to function. For example, there is a gene that tells the beta cells to start creating insulin in response to elevated blood glucose levels.
This is called gene expression—it’s when the body produces something, usually a protein, to do something specific in the body. Gene expression happens when the DNA of a gene is copied to form messenger RNA, or mRNA, which is then turned into a protein that has a unique function. This is orchestrated in a highly tissue-specific manner, creating diverse cell types like muscle, nerve, beta cell, and more.
In 1993, we learned that molecules called microRNAs regulate gene expression. They can hamper or promote it. By measuring the presence of microRNAs and using them as a biomarker, we can learn a lot about what is going on inside the body, what genes are being expressed, and in which cell types.
How does this apply to type 1 diabetes?
Breakthrough T1D is actively funding research into the use of microRNAs to advance our mission. In fact, we are currently funding $2.6 million in grants related to microRNAs. Specifically, we’re exploring their use as biomarkers of disease progression and as a therapeutic target to interfere with the autoimmunity behind T1D.
Biomarkers
Biomarkers are, put very simply, things in the body that can be measured. Pulse, body temperature, and blood pressure are all biomarkers. In T1D, there are a handful used in common parlance: blood glucose level, HbA1c, time-in-range, autoantibody status, and more. We want to validate the use of microRNAs as a biomarker of disease progression.
We know through years of work that early detection has many benefits. This includes being educated on what T1D is, preparing for a potential diagnosis, the ability to benefit from a disease-modifying therapy to delay onset, and preventing potentially life-threatening complications at onset. microRNAs have the potential to increase our understanding of disease progression and identify how quickly a person is progressing.
Type 1 diabetes occurs in stages. Today, biomarkers of progression, like autoantibody status, don’t paint the whole picture. If a person tests positive for 2 autoantibodies, that means they are almost 100% likely to develop T1D at some point—but we don’t know how fast. We can measure blood glucose levels, but that is a single data point for dysglycemia. It doesn’t tell us how healthy the beta cells are.
microRNAs have the potential to paint a much more detailed picture. We are funding research to discover whether we can use microRNAs to learn exactly where a person is in their progression to stage 3 T1D and how quickly it’s happening.
In summary—we believe microRNAs can enhance the predictive value on top of the current biomarkers for T1D. They can be a very useful tool in measuring progression and helping people in stages 1 and 2 of T1D.
microRNAs as a therapeutic target
Type 1 diabetes is an autoimmune disease—a disease where the body’s immune system destroys its own cells. In T1D, the T-cells in the immune system destroy the insulin-producing cells in the pancreas.
Our research into stopping disease progression focuses mainly on two areas: modifying the immune system and modifying the beta cells. microRNAs can potentially help us fix the dysregulation in the immune system, slowing down or halting the autoimmune attack.
Breakthrough T1D-funded researchers discovered that blocking microRNA-146a in mice can prevent the T-cells from damaging the beta cells. Preventing damage to the beta cells prevents T1D from progressing. Our hypothesis: if we can block microRNA-146a, we can slow down or halt disease progression. This specific study is in a pre-clinical setting, and if it goes well, it could move into clinical trials in the near future.
David Baker – Nobel Prize in Chemistry
David Baker, a breakthrough T1D-funded researcher, was awarded half the 2024 Nobel Prize in Chemistry for computational protein design.
Baker’s prize acknowledges his work in discovering a way to create new proteins that have never existed before. These proteins can potentially be used to treat diseases, make new vaccines, and more. A few years ago, we saw a potential application to T1D.
There haven’t been any groundbreaking changes in insulin since the discovery of synthetic insulin in the late 1970’s. Breakthrough T1D wants to change that—and is funding researchers, like David Baker, to figure out what the next generation of insulins can look like.
Baker received two grants from us from 2016-2021 to use a computer model to create new, glucose-responsive insulin (GRI). GRI is insulin that can be administered, exist in the blood stream, and only be active when it is needed. Baker’s grant was one of many projects we are pursuing in GRI. This work continues to this day, and there are even GRIs in human clinical trials.
What’s next?
This year’s Nobel Prizes show that we are focusing on the same things the Nobel Committee is focused on: the best and brightest scientists and the best and brightest research. Hopefully, one day, we’ll see a T1D scientist win a Nobel Prize for curing this disease.
Want to learn more?
Visit our Funded Research page, where you can read about every single grant we fund—including David Baker’s work in GRI and the many grants currently being funded to study microRNAs.

