
What’s Happening?
In an exciting update for the type 1 diabetes (T1D) community, Tzield—the first disease-modifying therapy approved by the FDA to delay progression of stage 2 T1D—has now been approved by the FDA for use in stage 3 T1D. People aged 8-17 with stage 3 T1D will soon be able to get Tzield in clinics (with a prescription) if they have been diagnosed within the last 8 weeks. This makes it the first disease-modifying therapy approved for individuals in stage 3 T1D.
Breakthrough T1D thanks the FDA for recognizing the urgent need for disease-modifying therapies in T1D and for advancing access to Tzield for individuals with stage 3 T1D through a complete and rigorous review of the data and Sanofi for their commitment to the T1D community.
How Did This Happen?
Regulators at the FDA thoroughly reviewed data from the PROTECT clinical trial to support Tzield’s approval. The PROTECT study demonstrated that Tzield could safely and effectively preserve insulin-producing beta cells in newly diagnosed children and adolescents with stage 3 T1D. Clinical data shows that individuals with more beta cell function also have better diabetes-related outcomes, like improved HbA1c, more time in range, less hypoglycemia, and less insulin use.
Tzield was approved through FDA’s accelerated approval pathway, demonstrating FDA’s recognition of the urgent needs faced by those living with T1D. This means that based on the available data, the FDA has determined the drug is safe and reasonably likely to provide a clinical benefit and can be available while an additional clinical study happens. Based on the experience with Tzield in stage 2 and the robust evidence in stage 3, input from an external advisory committee was not needed.
Tzield is the first drug approved for stage 3 T1D—a major milestone for the field. Many disease-modifying therapies for stage 3 T1D are currently in clinical trials and at various stages of the drug development pipeline. This also marks the first time a disease-modifying therapy has been granted approval based on C-peptide, a marker of beta cell function. Breakthrough T1D has supported efforts to advance C-peptide as a clinical trial endpoint for nearly 10 years.

The Importance of Beta Cells
Beta cells are the cells in the pancreas that make insulin. In people with T1D, these vital cells are destroyed by the immune system. Thanks to years of research, including many studies funded by Breakthrough T1D, there is a significant amount of evidence showing that there are meaningful benefits to preserving beta cell function in people with T1D who are already using insulin. These include reduced hypoglycemic events, less insulin, reduced burden of care, and improved HbA1c. Learn more about C-peptide and the benefits of preserving beta cell function.
Tzield is Addressing an Unmet Need
Tzield was granted accelerated approval because FDA recognizes there is a large unmet need in the T1D population—and the potential for Tzield to help meet these needs.
In 2022, Sanofi’s Tzield also became the first disease-modifying therapy approved to delay the onset of stage 3 T1D in people with stage 2 T1D. Tzield, which has been supported by Breakthrough T1D for decades, has been a game changer in T1D as it’s the first therapy for this disease that addresses the root cause of T1D, not the symptoms. It targets the T cells that are responsible for destroying insulin-producing beta cells, slowing down the autoimmune processes that cause T1D. In people with stage 2 who receive Tzield, a stage 3 diagnosis is delayed by an average of 2 years. In April 2026, FDA expanded Tzield’s indication in stage 2 to include children as young as 1 year of age and older.
The vast majority of people in stage 2 don’t even know they have early T1D because there are no external symptoms. The only way to know is to get screened for risk markers of T1D. While the number of individuals screened for T1D has dramatically risen in recent years, most people progress to stage 3 before they have the chance to reap the benefit of Tzield delaying onset. Now that Tzield is approved for stage 3 T1D, people will have more opportunities to preserve insulin-producing beta cells, even if they didn’t identify their T1D early.

“The approval of Tzield for individuals ages 8-17 with stage 3 type 1 diabetes is an exciting milestone that reinforces the importance of beta cell preservation and provides an opportunity to change the course of the disease for those living with T1D,” said Aaron J. Kowalski, Ph.D., Breakthrough T1D CEO. “For the first time, individuals diagnosed with type 1 diabetes in stage 3 will have the option to treat the disease rather than just the symptoms. Breakthrough T1D thanks the FDA for recognizing the urgent unmet need in T1D and granting Tzield accelerated approval in the U.S. We are also grateful for Sanofi’s continued study of Tzield, and we look forward to the results of the confirmatory clinical research.”
What Happens Next?
Sanofi is conducting a new clinical trial, called BETA PRESERVE, to support full approval of Tzield for stage 3 T1D. This study will provide additional safety and efficacy data from children and adults with T1D up to 25 years old with stage 3 T1D treated with Tzield or placebo.
There are two primary endpoints: HbA1c levels and days without mealtime insulin. If you or anyone you know may be interested in participating, contact a study site near you to learn more and see if you are eligible.
The Bottom Line
For the first time, individuals diagnosed with T1D have a therapy option besides insulin that addresses the root cause of the disease. This is a historic first, modifying the course of T1D and allowing people to benefit from preserved beta cell function, as the PROTECT study has demonstrated.
This is incredibly exciting, but we are not done. We will continue to work to ensure individuals in stage 3 T1D all over the world, not just the U.S., have access to more therapies to help them do better.
Breakthrough T1D has been supporting the evolution of Tzield for decades, and we support its use in stage 3 T1D. We thank the FDA for recognizing the urgent unmet needs in T1D, and we are grateful to Sanofi for their continued research. Read more about the journey of Tzield from the lab and into clinics (written by Breakthrough T1D supporter Doug Lowenstein).
ADA’s 86th Scientific Sessions
This event is one of the largest diabetes conferences in the world, bringing together over 11,000 attendees to share and learn about cutting-edge research and advancements toward cures. Each year, Breakthrough T1D-funded researchers highlight their work, demonstrating the progress we’re making toward achieving our mission. Leading experts will present over 100 studies spanning cell therapies, disease-modifying therapies (DMTs), diabetes technology, treatments, and more!
ADA 2026 has officially come to a close! We’re excited to report on the final two days of the conference, with even more updates spanning Cures and Improving Lives. Read on to learn about Breakthrough T1D-funded research making an impact and highlights from our on-site staff, especially in cell therapies.
Check out the updates from days 3 and 4 across Cures and Improving Lives:
Quick Primer on T1D Immunology Terms
- Antigen: part of a beta cell that the immune system mistakenly recognizes as “non-self” and mounts an immune response against.
- Antigen-presenting cell (APC): Immune cell that “presents” beta cell antigens on their surface to T cells, which then learn to attack the beta cells.
- T cells: The destructive immune cells that directly attack beta cells.
- Regulatory T cells (Tregs): help control and resolve immune responses but are less functional and effective in T1D.
Cell Therapies
Cell Therapies Highlight: Breakthrough T1D-Funded Clinical Trial for Tegoprubart Continues to Hit Milestones
Piotr Witkowski, M.D. (University of Chicago) gave an update on the Breakthrough T1D-funded clinical trial for Eledon’s tegoprubart, an immune therapy being tested with donor-derived islet cell transplants. All 12 participants are off external insulin. They are not experiencing severe hypoglycemic events or unexpected adverse events, there are no signs of the body rejecting the transplanted cells, and there are no signs of kidney toxicity.
Islet Size Matters
- Presenter: Julia Panzer, Ph.D. (City of Hope)
- In humans, islets have a range of sizes.
- Older adults with T1D tend to have smaller islets, but we don’t know if islets are shrinking or if more small islets are being generated.
- Based on islets isolated from donor pancreases and sorted by size, smaller islets are less responsive to changes in glucose, and they are preferentially targeted by T cells (the immune cells that attack insulin-producing beta cells).
- This work provides insight into how T1D may progress differently with age based on changes in islet size.
Cell Therapies Highlight: Research Funded by Breakthrough T1D or the T1D Fund
Jessica Weaver, Ph.D. (Arizona State University) presented about how we can learn lessons from placental immunology to train the immune system to ignore beta cells in T1D. During pregnancy, specialized cells in the placenta (called trophoblasts) teach the mother’s immune system to ignore the developing baby. Dr. Weaver is testing if trophoblasts can be successfully transplanted in mice in an encapsulation device her team optimized through computational modeling to improve cell survival. The goal is to eventually see if trophoblasts can be co-implanted with islet cells so that they send signals to the immune system to ignore them.
Leonardo Ferreira, Ph.D. (Medical University of South Carolina) presented on a dual cell engineering strategy for T1D. In this approach, manufactured beta cells are engineered to display a unique protein fragment on their surface. Tregs are then engineered to recognize that same unique fragment. When implanted together, the Tregs can turn down the activity of any destructive immune cells that become activated against the protein fragment. In mouse models, this method has proven to be successful, and Dr. Ferreira is finding even more ways to modify these cell types to enhance their functions. The idea is to translate this into a new manufactured islet cell therapy approach that would also modify a person’s immune cells so that immunosuppression is not required.
Julie Sneddon, Ph.D. (University of California, San Francisco) studies how precursor cells turn into beta cells during development. Her work provides insights into how we can harness this knowledge to optimize beta cell manufacturing in the lab for large-scale islet cell therapies.
Quinn Peterson, Ph.D. (Mayo Clinic) focuses on manufacturing all the different cells of the islet, in addition to beta cells, for islet cell therapies. His work in T1D mouse models showed that implanting beta cells with alpha cells (which secrete glucagon) allows them to function better with fewer cells. This could have implications for how we optimize islet cell replacement therapies.
Peng Wang, Ph.D. (Mount Sinai Icahn School of Medicine) presented his work on a small molecule called harmine, which can promote the function and expansion of beta cells in T1D mouse models. The goal is to use harmine in the context of manufactured islet cell transplants to improve their maturation and function to make these therapies more effective.
Leonardo Velazco-Cruz, Ph.D. (Century Therapeutics, a T1D Fund portfolio company) presented on the company’s manufactured islet cell therapy product, CNTY-183, which is engineered with Allo-evasion 5.0 technology so that immunosuppression is not needed. Dr. Velazco-Cruz reported that Century Therapeutics has developed a scalable, bioreactor-enabled differentiation process that can produce consistent, functional manufactured islets. In mouse models, engineered islets were protected from the immune system and maintained insulin production as measured by C-peptide. The company will continue to develop its product for eventual translation into humans.

Advocacy Staff Making an Impact
Clem Cypra, Director of Health Policy, presented a poster from our Advocacy team on how well insurance claims capture hypoglycemia in people with T1D. This is especially important because an eligibility requirement for islet cell therapy clinical trials is severe hypoglycemia, and payers often use claims data to understand who may qualify for new therapies. The team found that claims capture significantly lower rates of hypoglycemia in people with T1D compared to rates reported in clinical studies and published reports. Therefore, relying on claims alone may result in coverage decisions that are not in line with real-world care for people with T1D, and additional research is needed to fully uncover the impact of hypoglycemia on the T1D community.

Key Takeaways
- Breakthrough T1D-funded cell therapy research is advancing on two fronts: helping transplanted islet cells survive and function without lifelong immunosuppression, and manufacturing better islet cells at scale.
- The clinical trial studying tegoprubart at the University of Chicago continues to impress, with all 12 participants off external insulin and no signs of rejection or kidney toxicity.
- Across the funded portfolio, researchers are engineering the immune system to tolerate beta cells while others refine how islet cells are created in a lab.
- Together, this work is moving the field toward manufactured islet cell therapies that could one day restore insulin production without immunosuppression.
Disease-Modifying Therapies
Cell engineering approaches to turn down autoimmunity
- Presenter: Justin Spanier, Ph.D. (University of Minnesota)
- The interaction between APCs and T cells is critical to the autoimmune process.
- Dr. Spanier presented on two different cell engineering strategies to disrupt this interaction.
- The first approach involves developing an antibody that binds to beta cell antigens on the surface of APCs, which physically blocks T cells from interacting with it.
- The second approach involves engineering Tregs to interact with beta cell antigens on the surface of APCs so that, again, T cells cannot interact.
- Dr. Spanier is further refining these approaches with the ultimate goal of finding new ways to suppress autoimmunity in T1D.
Disease-Modifying Therapies Highlight: Breakthrough T1D-Funded Research
Jacqueline Burke, Ph.D. (Northwestern University) spoke about the development of a “tolerozome,” a nanoparticle loaded with an immune-modulating agent (rapamycin) that can train the immune system to ignore beta cells. Her approach is unique in that tolerozomes are delivered specifically to immune cells, meaning that other surrounding cells are unchanged. Even more, this approach can be applied to islet cell transplants (to prevent attack on transplanted cells) or early-stage T1D (to preserve the body’s beta cells). Data from animal models of T1D support the potential for these approaches with limited toxicity, and ongoing studies will assess long-term tolerozome dosing and combination with manufactured islets.
Spotlight on Breakthrough T1D-Funded Research: Uncovering Biological Mechanisms in T1D
T1D Pancreases have Tissue-Wide Biological Alterations
- Presenter: Dirk Homman, M.D., Ph.D. (University of Miami)
- Dr. Homman presented his work on full-scale assessment of the entire pancreases of people with T1D (obtained through the Breakthrough T1D-sponsored nPOD program).
- Using histology and single-cell computational methods, he found that T1D pancreases have tissue-wide alterations that are not limited to islets.
- These findings will provide a better basis for our understanding of T1D pathology and help researchers adapt mouse models of T1D to better mimic biological changes that occur in humans.
Beta Cells are Stressed
- Presenter: Farooq Syed, Ph.D. (Arthur-Riggs Diabetes and Metabolism Research Institute)
- Beta cells have increased signaling through specific stress-response pathways, which may contribute to their ability to provoke an autoimmune response.
- Dr. Syed explored how stress pathways can influence large-scale changes in beta cell genes, further uncovering how molecular alterations in the beta cells themselves may contribute to autoimmunity.
Key Takeaways
- Disease-modifying therapy research is focused on retraining the immune system in a targeted way to ignore the beta cells so they can continue to produce insulin.
- These strategies include engineering various agents, including antibodies, modified Tregs, nanoparticles, and more that may protect transplanted islets or preserve beta cells in early-stage T1D.
- Foundational research is also deepening our understanding of the disease itself: T1D pancreases show tissue-wide alterations beyond the islets, and beta cells under stress may help provoke the autoimmune response.
- Together, we are going down the path to new ways to slow or stop the autoimmune attack at the heart of T1D.
Early Detection
Global Pediatric Screening Inequities
- Presenter: Jean Claude Katte, M.D., Ph.D. (University of Exeter)
- The Young Onset Diabetes in Sub-Saharan Africa study found that most people diagnosed with T1D in this geography did not have any autoantibodies detected.
- T1D screening tools based on autoantibody detection were developed using white populations with a European ancestry.
- This suggests that our current screening model and staging framework may not be suitable for people from all geographies since there appears to be biological variability.
- Dr. Katte also highlighted significant inequities in access to care in Africa and other geographies.
- Breakthrough T1D is committed to helping close these gaps through our Advocacy work around the globe, including our ALIGN-T1D initiative.
Monitoring Youth with One Persistent Autoantibody
- Presenter: Nicole Sheanon, M.D., M.S. (Cincinnati Children’s Hospital Medical Center). Dr. Sheanon is also a part of our Mission Impact Volunteer program.
- Around 15% of youth with a single autoantibody detected and no symptoms will go on to develop T1D.
- The first three years after autoantibody detection are the most critical monitoring window.
- Healthcare professionals (HCPs) should look out for any changes in health that may signal progression of T1D, including changes in HbA1c levels or the development of an additional autoantibody.
- Education is critically important so that families know to remain aware of the potential risk of T1D development, even if it’s low.
- For more, take a look at published consensus guidance for monitoring of early-stage T1D, which was published a few years ago and spearheaded by Vice President of Medical Affairs Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES.

Early Detection Highlight: Breakthrough T1D-Funded Researchers and Staff
Holly O’Donnell, Ph.D. (Barbara Davis Center) presented on the psychosocial impact of T1D diagnoses (early-stage and clinical) on families. Dr. O’Donnell found that communicating with families about the risk of T1D progression can be a challenge, and education efforts need to be individualized and repeated to be effective. Families with a greater understanding of T1D risk also tend to have more anxiety, especially for those who have a family history of the disease. Dr. O’Donnell is currently working on a Breakthrough T1D-funded study to adapt a cognitive behavioral therapy to reduce anxiety around risk of progression for families with children in early-stage T1D. For more, see Dr. O’Donnell’s o-demand seminar for HCPs.
Dr. Albanese-O’Neill spoke about recommendations for T1D screening and monitoring. She covered a range of topics, including the global T1D screening landscape, ICD-10 diagnosis codes for early-stage T1D, and the potential benefits and of screening, early detection, and follow-up monitoring. Dr. Albanese-O’Neill also discussed the importance of clinical trials, especially for DMTs targeted toward early-stage or newly diagnosed individuals, and she urged the HCPs in the audience to encourage research participation in their clinics. She closed with information about our early detection pilot clinics and international consensus guidelines for general population T1D screening, developed by Dr. Albanese-O’Neill with expert collaborators.

Key Takeaways
- Current screening methods may miss people elsewhere, so we must adapt our screening and staging frameworks need to ensure it works across the globe.
- Breakthrough T1D is working to close these gaps through Advocacy efforts around the world, including the ALIGN-T1D initiative.
- The first three years after detection are the most important monitoring window for youth who have a single autoantibody.
- Although it does have marked benefits, learning about T1D risk early can be emotionally difficult for families. Breakthrough T1D-funded research is developing tailored support to help them cope.
Improving Lives
The State of T1D in Adults
- Presenter: Marissa Hitchcock, BSN, RN, CDCES (Children with Diabetes)
- The global prevalence of T1D is increasing by 2-3% each year.
- 21% of adults with T1D are meeting HbA1c targets of less than 7%, and 64% are using diabetes technology.
- Cardiovascular events occur 10 to 15 years earlier in T1D adults, and 30-40% of adults develop kidney disease within 25 years of diagnosis.
- There are not enough options for adults with T1D to reduce their risk for heart and kidney disease; while GLP-1 receptor agonists and SGLT inhibitors are showing promise in clinical trials, they are still not approved and widely accessible.
- Major gaps in care for this population include healthcare access and affordability, psychosocial support, socioeconomic disparities, and representation in clinical trials.
- We need to do more for adults with T1D, and a major priority of Breakthrough T1D is funding research into devices and therapies that can improve blood sugar and weight management and reduce complications so T1D adults can do and feel better.
Improving Lives Highlight: Breakthrough T1D-Funded Researchers and Staff Making an Impact
Courtney Ackeifi, Ph.D., Senior Scientist, hosted a networking event for building partnerships with scientists and clinicians working on cardiometabolic therapies for T1D. In a short presentation, she highlighted the urgent need for cardiometabolic therapies for the T1D community and opportunities to partner with Breakthrough T1D to accelerate progress in this area. Anyone who is interested can check out our funding opportunities.
Key Takeaways
- It is critical that we continue to invest in complications research, especially as adults with T1D are encountering earlier and higher rates of heart disease and kidney disease. We need more options.
- There are still significant gaps that are preventing everyone from having access to the therapies that work best for them- Major gaps remain in access, affordability, mental health support, and clinical trial representation for adults with T1D.
- Breakthrough T1D is working to close these gaps so there are more options for people with T1D and they are accessible.
Advocating for Children with T1D
Lauren Figg (Stanford University) presented on how the medical community can advocate for children with T1D to get adequate access to care. Social needs, including basics like food, clothing, and shelter in addition to whether they can afford insulin or other supplies, should be document in electronic health records so HCPs can provide the appropriate support. Figg also suggested that HCPs be aware of local community resources, deliver information through multiple ways (verbal, printed, etc.), and follow up with families to ensure they are getting the T1D care they need.

That’s a wrap on ADA 2026! For more, tune in on Wednesday, June 10, at 6 PM Eastern Time on our social channels for a live Mid-Year Mission Update from our leadership—including highlights from ADA, recent advances, and what we can look forward to for the rest of 2026.
Coming soon: A full ADA 2026 recap with everything you need to know about the conference. Keep an eye on our News & Updates webpage!
ADA’s 86th Scientific Sessions
This event is one of the largest diabetes conferences in the world, bringing together over 11,000 attendees to share and learn about cutting-edge research and advancements toward cures. Each year, Breakthrough T1D-funded researchers highlight their work, demonstrating the progress we’re making toward achieving our mission. Leading experts will present over 100 studies spanning cell therapies, disease-modifying therapies (DMTs), diabetes technology, treatments, and more!
Reporting live from New Orleans, LA! Breakthrough T1D is on site at ADA 2026 with leading scientists, clinicians, healthcare professionals, industry partners, and more to hear about exciting updates in type 1 diabetes (T1D) research—including work supported by Breakthrough T1D.
Read on for everything you need to know from the first two days ADA 2026, including key takeaways from panels and sessions featuring Breakthrough T1D staff and noteworthy highlights from Breakthrough T1D-funded researchers—both past and present—whose work was front-and-center.
Check out the updates from days 1 and 2 across Cures and Improving Lives!
Cell Therapies: Breakthrough T1D Staff at the Forefront
Sanjoy Dutta. Ph.D., Chief Scientific Officer, participated in a panel discussion about advancing manufactured islet cell therapies for widespread clinical use. A major theme was that eligibility requirements for clinical trials are too narrow—which means that less people have the chance to benefit and trials don’t progress as quickly. Patient-reported outcomes will be important to demonstrate to regulators that many people with T1D can and want to benefit from islet cell replacement therapy, and we need established, systemic methods in place to take the T1D community’s opinions into account.
The panelists also discussed the current challenges surrounding immunosuppression, which is one of the barriers to clinical trial participation, and ongoing efforts to develop novel cell protection strategies. Immunotherapies in development for early-stage T1D may be applicable in islet cell transplant settings, including approaches that retrain the immune system to ignore beta cells—an area that Breakthrough T1D is invested in.
To accelerate progress in manufactured islet cell therapies, the panelists agreed that the top priorities are:
- More companies exploring novel approaches
- Expanding eligibility criteria for trials—and incoporating the perspectives of the T1D community into regulatory decisions—so we can build more evidence around the safety and efficacy of manufactured islet cell therapies
- Additional frameworks to help guide the field, like our cell therapies roadmap and upcoming publications from Breakthrough T1D staff around manufacturing and preclinical considerations
- Optimizing manufacturing processes to reduce costs and ensure access for people who want these therapies
- Optimizing cell therapy products by reducing or eliminating the need for immunosuppression and finding the best transplant site for survival

Brynn Marks, M.D., Senior Director of Medical Affairs, chaired a session about the promise and perspective of islet cell replacement therapies for kids with T1D. Notably, Melena Bellin, M.D. (University of Minnesota) spoke about insights from children with pancreatitis who require full pancreas removal and receive transplants of their own healthy islet cells into their livers. In comparison to adults, children who receive this type of dual transplant have higher rates of islet survival and function and are more likely to stop needing external insulin. Laura Jacobsen, M.D. (University of Florida) spoke about practical clinical expectations for cell therapies and DMTs based on the data we have in adults and what this might mean for kids. Finally, Jane Speight, Ph.D. (The Australian Center of Behavioral Research in Diabetes) closed out with a talk about psychosocial considerations for pediatric islet cell transplantation.

Key Takeaways
The data surrounding islet cell therapies is very exciting, but we have more work to do until manufactured products are accessible to everyone with T1D who may want them. We are at the very beginning of considering what these therapies might look like in the pediatric T1D population.
Disease-Modifying Therapies
C-peptide
C-peptide is a biomarker of the body’s insulin production, which can be measured easily by a blood test. It’s formed when pro-insulin is cleaved into active insulin and C-peptide.
The Potential for a New and Improved C-Peptide
- Presenter: Samuel Sangqu Wu, Ph.D. (University of South Florida)
- C-peptide has the potential to be a validated endpoint for DMT clinical trials, and researchers like Dr. Wu are looking into new ways to help make this possible.
- Time to minimal residual C-peptide (TMRCP) is defined by how much longer people will have measurable C-peptide—meaning how long they will continue to make insulin.
- Dr. Wu applied this metric to six TrialNet studies and found that extrapolating TMRCP identified the same treatments as effective as each original analysis.
- TMRCP may be another metric to define the clinical meaningfulness of C-peptide, meaning it could be an alternative endpoint to consider for future DMT trials.
- Breakthrough T1D supported these efforts.
TEPLI-REAL: Evaluating Real-World Outcomes of People Treated with Tzield
- Presenter: Stephen Gitelman, M.D. (University of California, San Francisco)
- The purpose of this study was to understand populations who pursue treatment with Tzield and post-treatment outcomes through review of electronic health records.
- Diagnosis of T1D is heterogeneous, with people having either autoantibodies or dysglycemia (abnormal blood sugar) detected first, or others having both detected at the same time.
- These diagnostic pathways influence Tzield initiation. Those who had dysglycemia and autoantibodies detected at the same time had the shortest median time to start treatment.
- Most people who initiated Tzield were adolescents, and 94% of people who started treatment completed the full 14-day course.
- This study offers important considerations for healthcare professionals (HCPs) regarding how T1D diagnosis influences Tzield treatment in routine practice.
Decoding Immune Mechanisms and Engineering the Immune System in T1D
- Todd Brusko, Ph.D. (University of Florida) presented on spatial locations of different immune cells that contribute to the autoimmune process in T1D pancreases—and the underlying mechanisms that influence this.
- Kyle Gaulton, Ph.D. (University of California, San Diego) uncovered single-cell changes in pancreatic cells from T1D pancreases using advanced genomic methods.
- Mohammad Haj Dezfulian, Ph.D. (University of Pennsylvania) mapped T1D antigens contributing to autoimmunity by taking a closer look at T cells, which play a role in destroying insulin-producing beta cells.
- Remi Creusot, Ph.D. (Columbia University) presented on a different approach to retraining the immune system to ignore beta cells, starting with precursors to immune cells.
- Together, these studies are deepening our understanding of how and where the immune system attacks insulin-producing beta cells in T1D—and uncovering new ways to retrain it.
Disease-Modifying Therapies Highlight: Research Supported by Breakthrough T1D or the T1D Fund
Kenneth Brayman, M.D., Ph.D., FACS (University of Virginia) presented work on two Breakthrough T1D-funded projects. The first centered around the preclinical optimization of a potential immune therapy for T1D called IgM. Dr. Brayman and his team found that this therapy can retrain the immune system to ignore insulin-producing beta cells in mouse models of T1D, and he expanded on the mechanisms by which this happens. In humans, this could be another way to promote beta cell survival.
The second study that Dr. Brayman presented, which is funded by Breakthrough T1D in conjunction with his collaborator Gordon Laurie, Ph.D. (University of Virginia), focused on a new potential drug called N-104, which mimics a compound that was found to be decreased in people with T1D. The data presented show that, in mouse models, N-104 may suppress autoimmunity while simultaneously promoting beta cell regeneration—marking a new potential DMT worth exploring further.
Christoph Bausch, Ph.D. (SAB Biotherapeutics, a T1D Fund portfolio company) presented data from the phase 1 study of SAB-142, a humanized ATG. This potential DMT preserved C-peptide, improved time in range, and reduced insulin therapy use. Even more, it can be safely re-dosed with mild side effects related to the infusion procedure. Next up is the phase 2b SAFEGUARD study, which is currently enrolling and will further explore the safety and efficacy of SAB-142. The ultimate goal is to delay or halt T1D progression.
Alok Joglekar, Ph.D. (University of Pittsburgh) presented on a novel DMT approach that involves engineering different types of T cells in the body to suppress self-reactive T cells that are causing destruction of insulin-producing beta cells. His approach is designed to be antigen-specific, meaning selectively shutting down only the beta-cell-destroying T cells while leaving the rest of the immune system intact.

Key Takeaways
Understanding the key immune mechanisms underlying T1D pathogenesis is a major focus of T1D researchers, and they are turning this knowledge into novel strategies for potential DMTs. To expedite DMT clinical trials, time to minimal residual C-peptide may be a clinically meaningful measure of beta cell preservation. Real-world data about who is initiating Tzield treatment—and when—is providing HCPs with important information about the pathway to Tzield initiation in routine clinical practice.
Early Detection
Clinical Implementation of Pediatric T1D Screening and Monitoring
- Presenter: Sarah Lydia Holly, BSN, RN (Children’s National Hospital)
- Six pediatric endocrinology centers worked together to increase T1D screening and monitoring rates in kids through quality improvement and operational strategies.
- Between June 2024 to February 2026, the teams implemented patient and HCP education strategies, integration of screening and monitoring in clinical workflows, defined pathways for follow-up, and multidisciplinary coordination.
- The teams exceeded their goal and screened 1700+ people. No cases of diabetic ketoacidosis (DKA) reported, 85% engaged in long-term monitoring, and 73% were offered Tzield.
- This study demonstrates the feasibility of screening and monitoring in routine pediatric care, and this can facilitate early intervention and DKA prevention.
Early Detection Highlight: Breakthrough T1D Staff
Raquel Lopez Diez, Ph.D., Senior Scientist, hosted a Breakthrough T1D Reception for the T1D Genetic Risk Score (GRS) Consortium. The session brought together investigators and collaborators to discuss upcoming projects and future directions related to the T1D GRS Consortium, with dedicated conversations around genetics in non-European ancestry populations and adult-onset disease. The attendees exchanged ideas, identified areas for collaboration, and shaped priorities for the Consortium moving forward.
Key Takeaways
Screening and Early Detection has proven benefits, and the more people screened, the more people can avoid DKA at diagnosis, take advantage of a therapy to delay onset, and more. This is a major priority for Breakthrough T1D, and we support general population screening efforts.
Improving Lives
Discontinuation of Roche’s Dual GLP-1/GIP Receptor Agonist for T1D
- Presenter: Jeremy Pettus, M.D. (University of California, San Diego)
- Roche conducted a phase 2 clinical trial to evaluate changes in glycemic control in overweight or obese adults with T1D treated with their drug acmopatide (CT-868).
- People treated with acmopatide demonstrated reduced HbA1c levels, weight, insulin dose, and blood pressure compared to placebo.
- Despite these improvements, Roche decided to discontinue research into acmopatide and abandon plans for a phase 3 clinical trial.
- However, there are other companies studying GLP-1s in people with T1D. For example, Lilly has an ongoing clinical trial that is fully enrolled. Learn more below.
GLP-1/GIP Receptor Agonists: The Good News
Eli Lilly’s phase 3 trials for tirzepatide for glycemic control in adults with T1D and obesity or overweight (SURPASS-1-T1D and SURPASS-2-T1D) are fully enrolled, with results expected in the coming months. The Breakthrough T1D-funded ADJUST-T1D trial demonstrated glycemic and metabolic benefits for people with T1D and obesity or overweight using an AID system treated with semaglutide. A few days ago, top experts in the field published a consensus on safe use of this class of drugs in the T1D population—including authorship by Brynn Marks, M.D., Senior Director of Medical Affairs—which means that we are providing healthcare professionals (HCPs) with the education needed to bring these therapies safely to the T1D community (more to come on this later). We and others will continue to push for additional research solidifying the safety and efficacy of GLP-1/GIP receptor agonists and advocate for approval for the T1D community.
GLP-1 Receptor Agonists for Kids
- Presenter: Michelle Van Name, M.D. (Yale University)
- There is clear evidence in adults with T1D that GLP-1 receptor agonists can improve weight and glycemic control and reduce the risk of heart and kidney complications, and more clinical evidence is needed for the adolescent population.
- Adolescents with T1D could benefit from this class of drugs because they tend to have insulin resistance and live with overweight or obesity, and those who develop T1D earlier in life have a greater lifetime risk of long-term complications.
- Currently enrolling clinical trials (T1-DISCO and Obesity Complicating T1D: GLP-1 Analogue Anti-Obesity Treatment) in young adults living with T1D and obesity are investigating the impacts of GLP-1s on cardiovascular outcomes.
- Dr. Van Name’s mentor was Bill Tamborlane, M.D., a long-time champion for the T1D community and Breakthrough T1D supporter who recently passed away.

Improving Lives Highlight: Breakthrough T1D-Funded Researchers and Breakthrough T1D Staff
Richard Pratley, M.D. (Advent Health) presented on the unique needs of the heterogenous population of older people living with T1D. It can be especially challenging for HCPs to set glycemic targets because of variable life expectancies, lifestyle differences, presence of other health issues, and a lack of evidence surrounding blood glucose management for this population. Dr. Pratley recommends that goals for glycemic targets in older adults with T1D should be individualized, and T1D technology can significantly reduce hypoglycemic events. And he emphasized an important point—there aren’t enough therapies to reduce the risk of heart and kidney complications, which older adults are especially vulnerable for. Dr. Pratley is executing a Breakthrough T1D-funded clinical trial to repurpose cardiorenal drugs that work in T2D for T1D.
Viral Shah, M.D., a Breakthrough T1D-funded researcher, presented an evidence synthesis on ketone monitoring and treatment, which was co-authored by experts in the field including our Vice President of Medical Affairs, Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES. The team collected real-world or hypothetical clinical situations related to DKA to create a framework that HCPs can follow to determine the best course of action. This includes considering who is the intended population for ketone monitoring, when and how to check ketones, defining clinical parameters for elevated ketones, and follow-up steps for management. This effort is critically important because rates of DKA are increasing around the globe, as detailed in the preceding presentation by Guillermo Umpierrez, M.D. Ketone management is a Breakthrough T1D priority, and our Medical Affairs team previously spearheaded a publication outlining international expert recommendations on continuous ketone monitoring in T1D.
Dr. Albanese-O’Neill and Jonathan Rosen, Ph.D., Director of Research, were co-authors on two posters reporting on a multinational survey of adults using T1D technology with severe hypoglycemia exploring how they are doing in their daily lives. The participants reported sub-optimal health and significant impairments in productivity, highlighting the remaining unmet needs for the T1D community despite recent advances—showcasing why the work we do to improve the lives of those living with T1D is so critically important.

Key Takeaways
GLP-1s are top of mind for researchers—they have proven benefits for adults with T1D, and ongoing clinical trials will provide more evidence for their use in younger populations. We need to do more for older adults with T1D, from individualized approaches to glycemic targets to developing more therapies to prevent heart and kidney complications. Last but not least, DKA rates are increasing around the world, and Breakthrough T1D is actively involved in efforts to guide HCPs on ketone management—which is especially important with continuous ketone monitoring on the horizon.

Look out for another article soon wrapping up days 3 and 4 of ADA 2026!
It was identified in the late 1960s. Since then, studies have shown that it is a biomarker for beta cell function. In other words, it’s a measure of beta cell health and insulin production. If it’s low (or you have none), it indicates that your pancreas is producing little or no insulin. There was even a test to measure it in humans 50 years ago. What is it?
C-peptide.
It is a fragment generated during the process of making the active form of insulin that gets released from the pancreas into the body, and it can be easily measured in the blood or urine. C-peptide is an important biomarker that is critical to developing new disease-modifying therapies for type 1 diabetes (T1D).
Biomarkers and surrogate endpoints
A biomarker, or a biological marker, is anything that can be used to measure what’s going on in the body.
Biomarkers are used by doctors to help monitor your health and are often used by researchers to study how the body responds to new therapies. In some cases, biomarkers can be used as a clinical trial endpoint, something that is measured in a clinical study to objectively determine if a therapy is effective.
To be used as a clinical trial endpoint, a biomarker must be a surrogate endpoint, meaning the biomarker has been proven to predict a clinical benefit (that is to say, the biomarker is a surrogate for other clinical benefits). For example, HbA1c is a surrogate endpoint for the risk of diabetes-related eye, kidney, or nerve complications. Surrogate endpoints are important because they allow us to see the effects of a drug much faster, easier, and sometimes more clearly than other endpoints.
Regulators at the U.S. Food and Drug Administration (FDA) and other regulatory agencies around the world classify surrogate endpoints based on the strength of the evidence that they can predict clinical benefit. See below for the different categories of surrogate endpoints and what each means.
| Type of surrogate endpoint | Able to predict clinical benefit? | Able to support drug approval? |
|---|---|---|
| Exploratory | Preliminary evidence | Not at all |
| Reasonably likely | Good but not conclusive evidence | Accelerated approval with post-marketing studies needed to confirm benefit |
| Validated | Definitive evidence | Full approval |
For example, it is very well established that HbA1c is a good predictor of diabetes-related complications. The evidence is robust enough that HbA1c is considered a validated surrogate endpoint, and it has been used to support approval of many T1D therapies.
Challenges with current T1D clinical trial endpoints
Regulators have said the endpoints that can be used for drug approval in T1D trials today are HbA1c, low blood-sugar events, and rates of disease complications. For disease-modifying therapies (DMTs)—those that can change the course of T1D—reaching these endpoints in clinical trials can be a major challenge, especially when tested in people recently diagnosed with T1D.
There are multiple reasons for this. First, measuring the effects of new drug on HbA1c levels is difficult because insulin therapy can also cause improvements in HbA1c, and we need to distinguish between the effects of the two. Second, low blood-sugar events are relatively uncommon, especially if someone experiences a honeymoon period after diagnosis. Third, complications take years to develop, and trials would have to be decades long to directly see a drug’s effects on long-term outcomes. Therefore, trials that use these endpoints often require prohibitively (1) large numbers of enrolled subjects and/or (2) long follow-up, which makes moving DMTs through the pipeline more challenging than ever. Compounding the challenge, large or lengthy trials are expensive, which could hinder industry investment in T1D therapies.
Why C-peptide is important
For more than 40 years, C-peptide has been known as a biomarker for beta cell function. And for 25 years, the research field has agreed it should also be used as a validated surrogate endpoint to predict clinical benefits in DMT clinical trials.
Using C-peptide, DMT studies could require fewer participants, take less time, and cost less money, all while still being able to demonstrate the clinical benefits of a new therapy. This is especially critical for emerging therapies aimed at people in stage 3 T1D—when insulin therapy is needed—who currently don’t have any options to preserve beta cells and delay disease progression. Ultimately, C-peptide as a validated surrogate endpoint would unlock DMTs for the T1D community. In fact, without C-peptide, it will be incredibly difficult for DMTs to move through the drug development pipeline at a reasonable pace—or at all.
Despite widespread scientific consensus, regulators do not yet agree that C-peptide is a validated surrogate endpoint that can support full approval. In recent years, the FDA has stated that C-peptide could be used as a reasonably likely surrogate endpoint that could support accelerated approval. If granted accelerated approval, additional post-marketing studies are required to confirm the drug’s benefits. And the confirmatory trials must use the same old endpoints that are so challenging to study: HbA1c, low blood sugar events, or disease complications. This is a big step forward, but for many companies, the bar is still too high to invest in T1D therapies.
Based on FDA recommendations, almost every DMT trial in stage 3 T1D uses C-peptide as the study endpoint, and the FDA recently agreed to consider C-peptide as a reasonably likely surrogate endpoint that could support accelerated approval for two different therapies from two different companies.
First, the FDA agreed that C-peptide data from the DIAGNODE-3 trial, which investigated whether retogatein (rhGAD65) could preserve beta cells, could potentially support accelerated approval. Second, the FDA is currently reviewing data from the Tzield PROTECT study, which also assessed C-peptide to see if Tzield could preserve beta cells, and the FDA has granted Tzield priority review for stage 3 T1D. Each of these examples demonstrate that regulators believe in the potential of DMTs to change the lives of the T1D community, and they opened the door for C-peptide to accelerate the pace of these therapies. While the interim results from DIAGNODE-3 were negative and the Tzield review is still ongoing, we see clear signs that C-peptide makes the development of DMTs possible.
However, regulators don’t yet consider C-peptide to be a validated surrogate endpoint, and it therefore can’t be used to approve a new drug.
So why isn’t C-Peptide a validated surrogate endpoint?
The story goes back more than 20 years.
Early consensus
In 2001, the American Diabetes Association (ADA) held a workshop to identify appropriate outcome measures in T1D clinical trials. Clinicians and researchers at the workshop agreed that C-peptide is not just a measure of beta cell function, but also directly predicts benefits of other outcomes, including improved HbA1c, lower risk of low blood sugar (called hypoglycemia), and lower risk of diabetic eye disease.
Researchers concluded that drugs that can preserve C-peptide, and therefore beta cell function, would also improve these other clinical outcomes. The results were clear: A consensus-driven conclusion determined that C-peptide is the appropriate outcome measure for T1D clinical trials to preserve beta cell function.
Unfortunately, regulators were not convinced. At the time, researchers could only point to a few investigational drugs that showed the beneficial effects of preserving beta cell function (measured by C-peptide), and some of the most important studies could not definitively prove that C-peptide predicted benefits. Regulators needed more data.
Many more clinical trials
Now, there have been dozens of clinical trials of disease-modifying therapies in stage 3 T1D, and nearly all of them use C-peptide, which scientists can rely on to demonstrate the beneficial effects of preserving beta cells. A meta-analysis, funded by Breakthrough T1D and Diabetes UK through the Critical Path Institute’s Trial Outcome Marker Initiative (TOMI), showed that disease-modifying therapies that preserve beta cell function are effective at improving metabolic outcomes in stage 3 T1D. This, said the authors, “support[s] the use of C-peptide as a surrogate endpoint in clinical trials.”
Breakthrough T1D is a founding member of the Critical Path Institute’s (C-Path) Type 1 Diabetes Consortium. C-Path is a nonprofit organization dedicated to improving and streamlining the process of drug development, and with support from Breakthrough T1D, launched its T1D Consortium (T1DC) in 2017. Initially, the T1DC worked to get regulatory endorsement of diabetes-related autoantibodies as biomarkers to be used in the development of therapies that can delay or prevent T1D. This was achieved by receiving regulatory qualification from the European Medicines Agency (EMA) and published acceptance from FDA. Now, the T1DC is working to develop clinical trial simulation tools to improve T1D prevention and new-onset T1D clinical trials, as well as generating new evidence for the role of C-peptide in clinical trials.
Making the case for C-peptide
A publication, authored by world-renowned investigators (one of which was in the publication that followed the 2001 ADA workshop!) and five Breakthrough T1D employees, summarizes the totality of evidence to date for C-peptide as a validated surrogate that predicts clinical benefits of DMTs in T1D. This publication summarizes data from many different types of studies to make the case for C-peptide. The research presented includes:
- Longitudinal studies (Diabetes Control and Complications Trial (DCCT/EDIC))
- Cross-sectional studies (Scottish Diabetes Research Network Type 1 Bioresource Study (NT1BIO))
- Beta cell transplantation studies (Collaborative Islet Transplant Registry)
- Meta-analysis of clinical trials of DMTs to preserve beta-cell function (TOMI Study)
All of these have identified benefits from the preservation or restoration of beta cell function as measured by C-peptide.
Even more, for the first time ever, last year the FDA participated in a public workshop about C-peptide with researchers, scientists, Breakthrough T1D, companies, and people living with T1D. During this workshop, the FDA gave clear directions to the research community about the evidence needed for them to consider C-peptide a validated surrogate endpoint that can be used for DMT approvals.
As a result of this workshop, C-Path’s T1DC spun out a C-peptide data analytics working group with the key players in the field—including the FDA—that has been working hard over the past year to compile the evidence that the FDA requested. Right now, the FDA is reviewing the statistical analysis plan for C-peptide data. Once approved, the group will move forward, put their analysis plan into action, and submit their results.
The greatest opportunity to intervene with DMTs exists early in the autoimmune process. This requires an endpoint that can identify clinically meaningful impacts in early-stage disease. C-peptide is that endpoint.
Breakthrough T1D hopes that regulators will agree.
What’s happening?
The U.S. Food and Drug Administration (FDA) approved Tzield (teplizumab-mzwv) for use in children in stage 2 type 1 diabetes (T1D) ages one and older. This is a huge win for the T1D community!
Breakthrough T1D applauds the FDA for this approval and Sanofi for their commitment to new therapies for the T1D community.
For the first time, kids and their families have an approved therapy that addresses the underlying autoimmunity behind T1D—and not just the symptoms.
What does that mean? It means that families at risk for advancing to stage 3 T1D, which is when insulin therapy is required, can get an incredible gift: an average of two extra years without T1D.
Aaron Kowalski, Ph.D., CEO of Breakthrough T1D, celebrated the decision.

“Tzield’s approval for use in children ages one and older marks a defining moment in the treatment of type 1 diabetes,” said Aaron Kowalski, Ph.D., Breakthrough T1D CEO. “By expanding the population eligible for this disease-modifying drug, we are taking a meaningful step toward changing the trajectory of type 1 diabetes. Intervening earlier and slowing the disease’s progression will provide the gift of time to young children and their caregivers, potentially improving lifelong outcomes. I am immensely proud of Breakthrough T1D’s role in advancing the research that made Tzield possible. Breakthrough T1D applauds the FDA for today’s important decision to expand Tzield’s use and thanks Sanofi for its continued commitment to therapies for the type 1 diabetes community.”
How we got here
Tzield was approved for use in individuals 8+ in stage 2 T1D in 2022. Since then, we have been working to expand the eligible population. This expansion effort includes individuals in stage 3 T1D, who can preserve endogenous insulin production for longer when they take Tzield and, most notably today, children in stage 2.
Now, kids, arguably the most vulnerable patient population, can have a 14-day Tzield infusion and hit the pause button on T1D for an average of two years.
Screen, screen, screen!
Screening for T1D is more important than ever for families with children ages one and older. We encourage all families to screen their young kids—with a family history of T1D or without—because early detection of T1D is the only way to take advantage of Tzield and delay the need for insulin therapy by years. This could mean more years of healthy life spent just being a kid—no insulin pumps, no risky blood sugar highs and lows, no worried parents, no carb counting.
Screening resources for T1D
Interested in having your child screened for T1D? Check out our screening and early detection resources to learn more about your options for research-based screening programs. It’s easy—screening kits can be sent straight to your home.
We know that our community members are screening for T1D and taking advantage of Tzield, and we are thankful that this therapy has given people more years of life without constant, daily T1D management.
Tzield in action: Breakthrough T1D’s Chris Dunn
Chris Dunn is a parent of four children, two who live with T1D. Knowing that immediate family connections are a risk factor for developing T1D, Chris and her children without T1D participated in screening. Much to her surprise, Chris learned that she was in stage 2. Chris made the informed decision to get Tzield because she knew that it could delay her need for insulin therapy.
We are incredibly encouraged and excited that kids under 8 can experience the same benefits.
A day decades in the making
The decision would simply not have been possible without decades of Breakthrough T1D work, from funding discovery research to driving clinical development to working with regulators. Breakthrough T1D had a hand in the development of Tzield from the very beginning:
- Breakthrough T1D gave a Career Development Award to Kevan Herold, M.D., who had just started his faculty-level career at The University of Chicago, in 1988-1990. He showed, in an early study, that it’s possible to prevent autoimmune diabetes with an anti-CD3 antibody (which, later, became a humanized version, Tzield). He has gone on to receive more than 15 grants from Breakthrough T1D and was the lead on the clinical trial that demonstrated that Tzield could delay the onset of T1D in people almost certain to develop the disease. This was the first-ever study in humans to show a delay in the onset of T1D.
- We funded clinical trials in recent-onset disease, which were published in 2002, 2005, and 2013, and a phase III trial run by MacroGenics (it was called MGA031 at the time). MacroGenics received a Breakthrough T1D Industry Discovery and Development Program grant from 2006-2011.
- In 2012-2019, we funded, with the National Institutes of Health (NIH), the Immune Tolerance Network—an international clinical research consortium—that did a clinical trial of Tzield and identified who is likely to respond to the drug.
- Breakthrough T1D has also been a longstanding and passionate advocate for the Special Diabetes Program (SDP), an NIH program funded by Congress that enabled the creation of TrialNet—the largest clinical network for T1D. In 2010, with NIH, Breakthrough T1D, and the American Diabetes Association funds, TrialNet ran the clinical trial of Tzield in at-risk individuals, led by Dr. Herold.
- The T1D Fund: A Breakthrough T1D Venture made a strategic investment in Provention Bio in 2017 that brought the company into T1D for the first time—and they eventually acquired Tzield. That investment has helped catalyze hundreds of millions of dollars toward clinical development, regulatory work, and launch preparation that made this moment possible.
You can read more about the development of Tzield in Beating the Odds: The Improbable Story of How Perseverance, Belief, and Luck Led to the Approval of the First Life-Changing Immune Therapy for Type 1 Diabetes by Doug Lowenstein.
Looking forward
This news is incredibly encouraging, and the approval of Tzield for children ages one and older is a major step forward. Our work is not done. Tzield is still under review for people with stage 3 T1D—when insulin therapy is required—supported by the positive PROTECT Study that showed that Tzield significantly slowed the decline of beta cell function. We look forward to hearing the FDA’s decision for this population.
It doesn’t stop here. Tzield is approved for children and adults ages 8+ in Canada, the European Union, the United Kingdom (called Teizeild), China, Israel, Saudia Arabia, the United Arab Emirates, and Kuwait. However, Tzield is not yet available for young children ages 1+ in these countries, and our international partners and affiliates are working hard to expand its availability on a global scale so that more families around the world have the chance to benefit.
We will also continue to invest in next-generation disease-modifying therapies (DMTs) that have the potential to change the lives of people with T1D. We are funding early-stage companies, clinical trials and preclinical work through grants, while our colleagues at the T1D Fund are making equity investments in the most promising T1D biotech companies. Together, we are driving the field forward and bringing transformative DMTs through the pipeline. We envision a future where multiple DMTs are approved and available to preserve as many beta cells as possible for as long as possible. Thanks to the FDA’s decision, we have taken an important step in bringing Tzield—and more healthy years of life—to more people.
This article was written by Brian Herrick and Sandy Vogt, Ph.D.
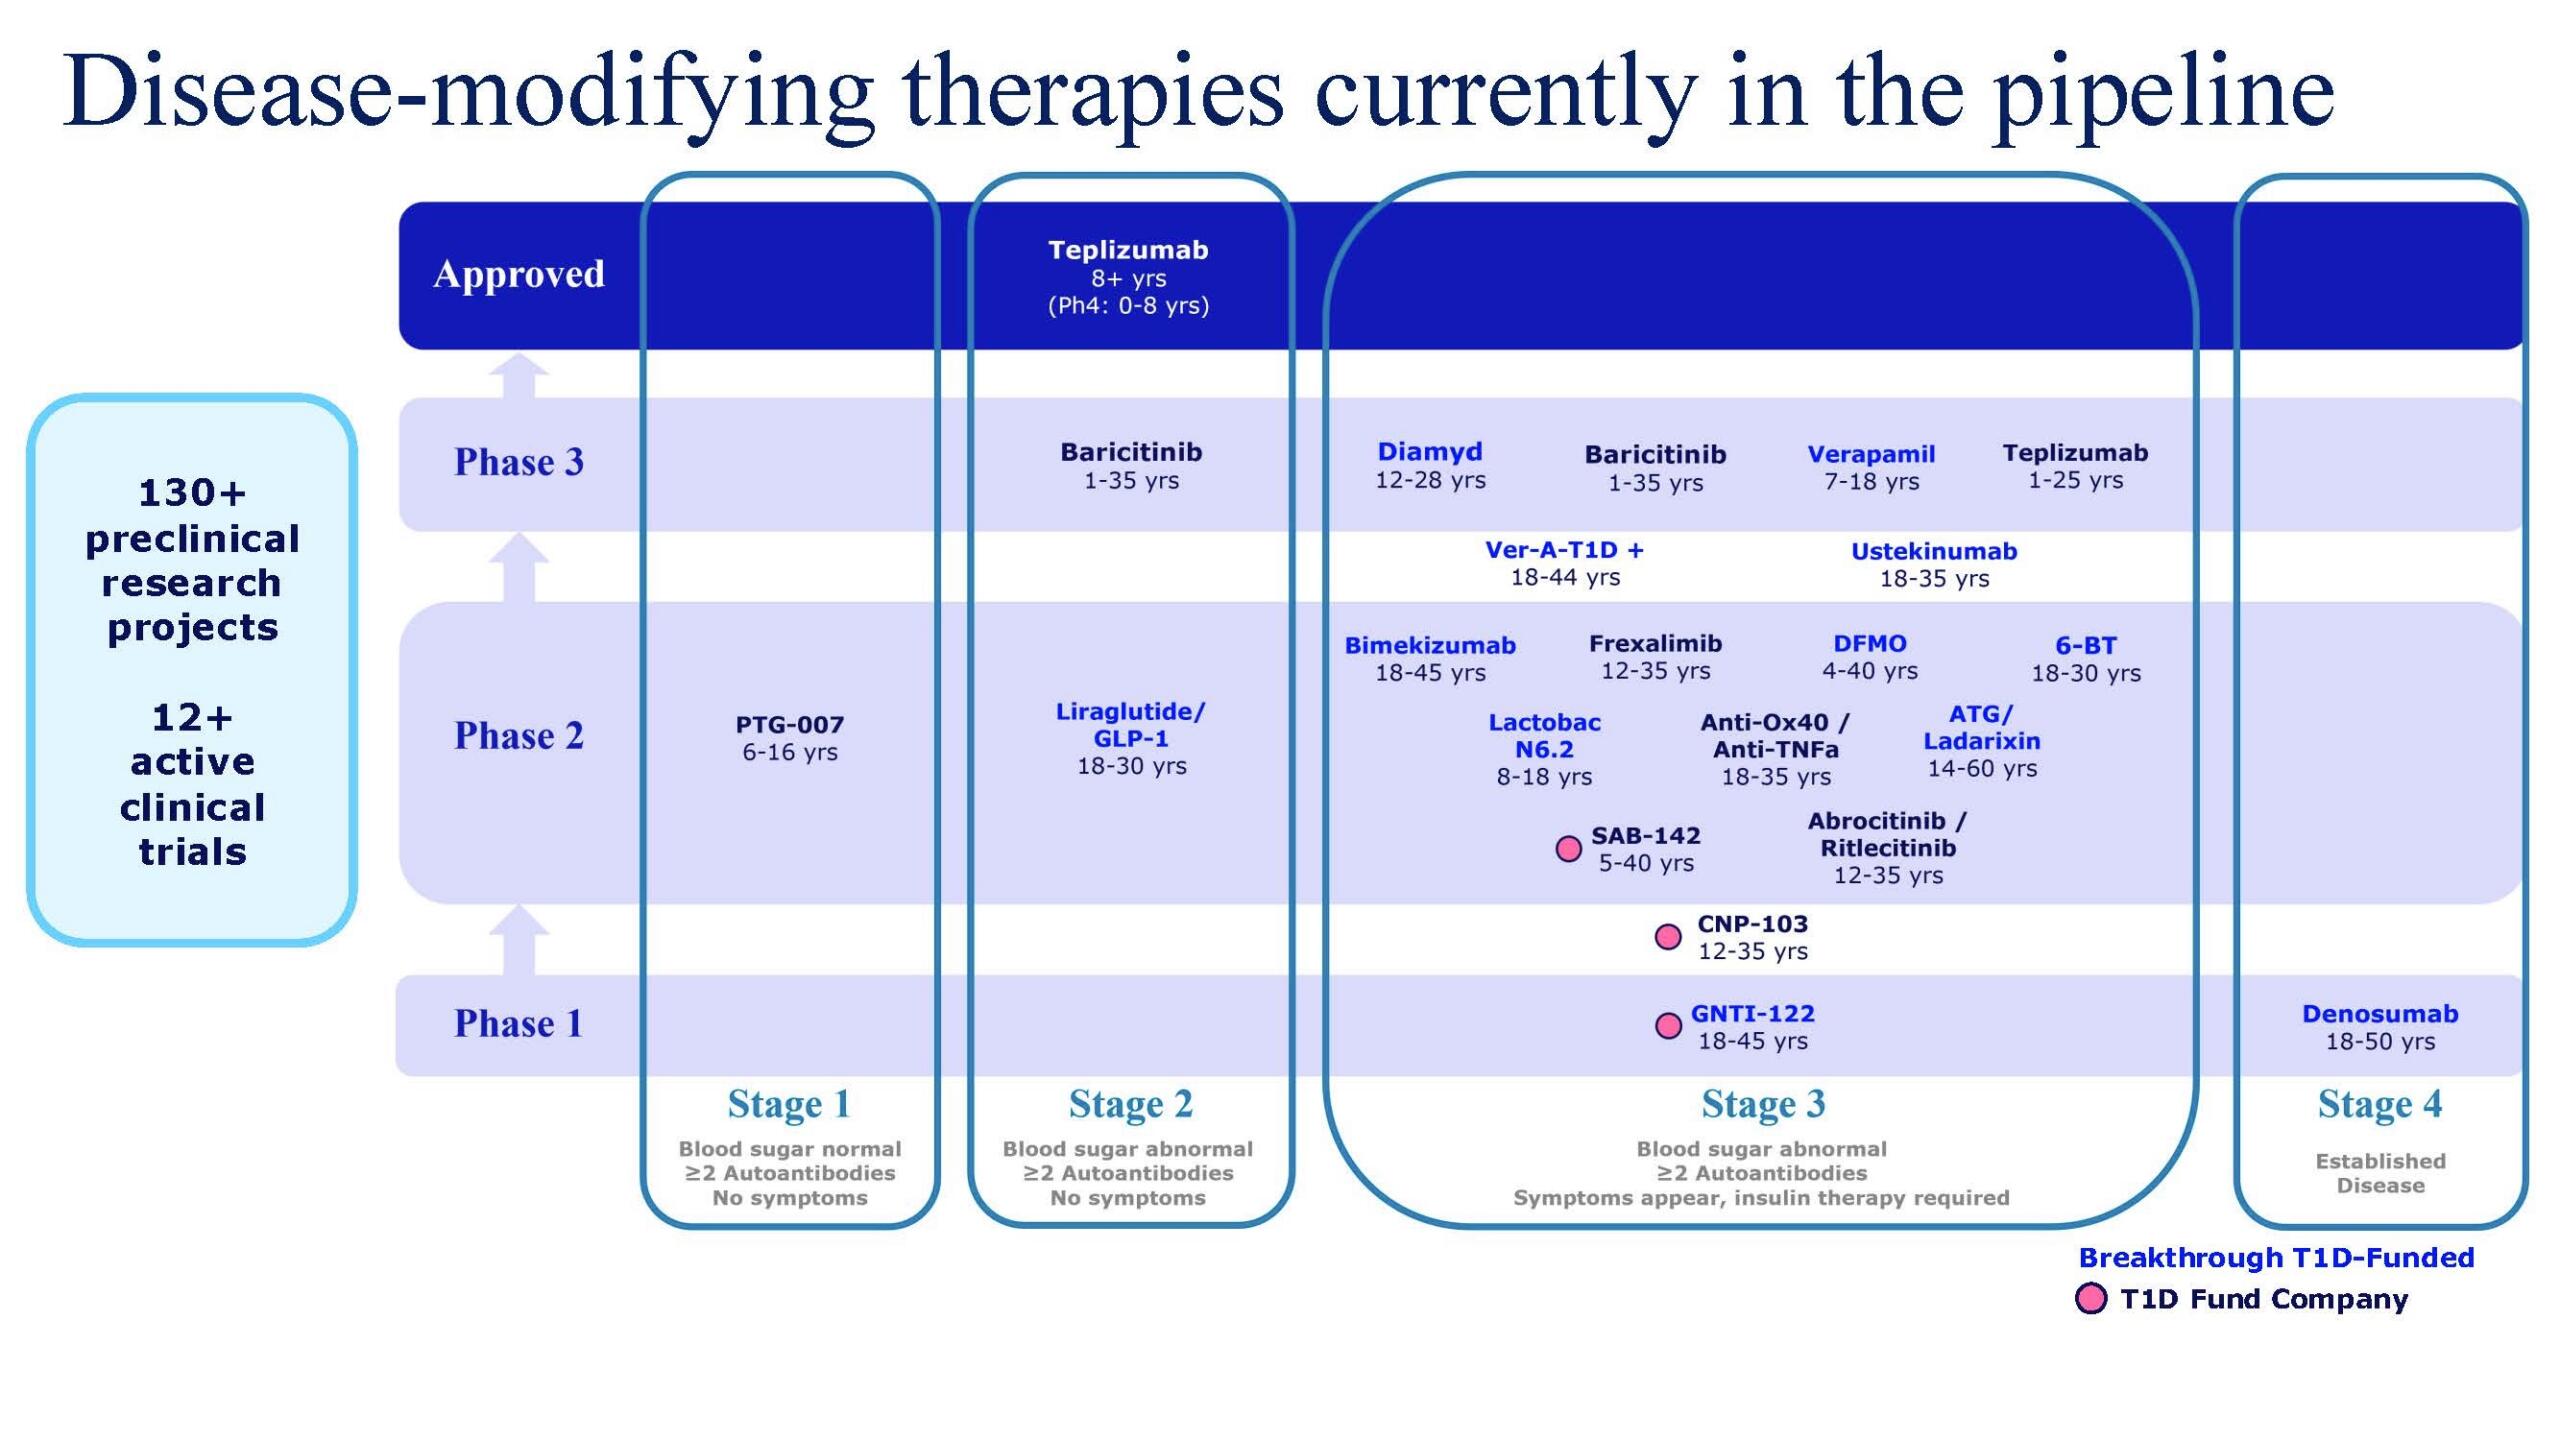
Breakthrough T1D is focused on developing drugs, or disease-modifying therapies (DMTs), that change the course of T1D for everyone affected by it—and those yet to be. That means slowing or halting the progression of the disease, preventing it from ever occurring, and reversing it entirely through immune therapies and beta cell therapies.
Note: To enlarge the image below, left click on it.
Update on Diamyd’s DIAGNODE-3 Clinical Trial
On March 27, Diamyd Medical announced results from an interim analysis of the Breakthrough T1D-funded Phase 3 DIAGNODE-3 trial, which assessed the ability of of Diamyd (retogatein or rhGAD65) to preserve insulin production (C-peptide) in the first 174 out of 321 participants in the trial.
Phase 3 Clinical Trials pave the way for discussions with regulatory agencies toward approval.
Surprisingly, and contradictory to positive data from prior phases of this clinical trial, the interim analysis showed that there was no observable preservation of insulin production (C-peptide). These results underscore the complexity of immune therapies in T1D and confirm Breakthrough T1D’s continued support of the clinical development of emerging disease-modifying therapies.
Breakthrough T1D’s Perspective on the DIAGNODE-3 Results
While this outcome was not expected, Phase 3 trials provide significant learnings for the development of future therapies and the field overall. Critical insight can be gained through the analysis of the data, even from clinical trials that do not meet their primary endpoint. These moments sharpen our understanding and accelerate better-designed approaches and more targeted application of therapies that are in development.
“Progress in type 1 diabetes research and treatment has always required persistence and learning from every study,” said Josh Vieth, Ph.D., Breakthrough T1D Senior Director of Research. “These results reinforce that immune interventions in type 1 diabetes are complex and highly context dependent. It’s imperative that we take these results seriously, understand what they mean, and use them to make strategic decisions about what’s next for retogatein and other disease-modifying therapies. There remains an unmet need for safe, effective therapies that rebalance the immune system in a targeted way, and Diamyd Medical is a pioneering approach to precision medicine for type 1 diabetes in clinical applications.”
What’s Next
Breakthrough T1D is in contact with the Diamyd team about next steps, which will include careful, collaborative analysis of the data from the trial to understand why these results differ from previous results. Diamyd plans to continue core operations, including manufacturing activities, during this period of analysis before determining the appropriate course of action. This includes the possibility of testing this therapy earlier in the progression of T1D (Stage 1 or 2), for which they have previously received “Fast Track” designation, an FDA program which would expedite this process.
Our Multi-part Strategy for Disease Modifying Therapy Development
Breakthrough T1D has been funding DMT research for decades. Following the 2022 approval of Tzield, the first DMT for T1D, we remain focused on our strategy for the development of disease-modifying therapies that can slow, halt, or reverse the course of T1D.
This strategy aims to both rebalance the immune attack as well as support a person’s own beta cells. Tolerization, or re-training the immune system to stop attacking beta cells without broad immunosuppression is an important part of that strategy. We are currently funding disease-modifying trials with companies like GentiBio to test their engineered Tregs, and trials aimed at repurposing existing drugs including DFMO, Bimekizumab, Denosumab, and ATG for use in T1D. To learn more, consult our previous article about this work.
November 2022 was a historic moment for the type 1 diabetes (T1D) community: Teplizumab (Tzield), the first disease-modifying therapy (DMT) for T1D, was approved by the FDA.
Tzield has been game-changing for T1D. It’s the first therapy for the disease that addresses the root cause of T1D, not the symptoms. It targets the T cells that are responsible for destroying insulin-producing beta cells, slowing down the autoimmune processes that cause T1D. Tzield has proven to delay progression to Stage 3 T1D—when insulin therapy is often required—for up to three years.
The approval of Tzield was a culmination of decades of passionate work by Breakthrough T1D, the only organization that supports T1D therapy development at every stage—from discovery research all the way through to people with type 1 diabetes receiving these therapies with healthcare coverage paying for them.
Pioneering Research and Strategic Investments
In the late 1980s, Kevan Herold, M.D., had just started his faculty-level career at The University of Chicago. He was diagnosed with T1D several years earlier, which heavily influenced his decision to focus on endocrinology. There, he met Jeff Bluestone, Ph.D., an immunologist concentrating on cancer research. After meeting many members of the T1D community through Dr. Herold, Dr. Bluestone switched a large portion of his research to new therapies for T1D.
One of their early studies showed that type 1 diabetes onset could be delayed with an anti-CD3 antibody, which later became teplizumab. Breakthrough T1D supported this novel research, which led to the first-ever clinical trial of a T1D disease-modifying therapy in humans in the early 2000s. The trial was a success and laid the groundwork for further studies and eventual support from the National Institutes of Health (NIH) through the Special Diabetes Program (SDP).
Over the next two decades, teplizumab was acquired by MacroGenics, a company formed to develop immune-based therapeutics for autoimmune diseases and cancer, then sold to Provention Bio, a T1D Fund-backed biopharmaceutical company focused on disease interception and prevention. The drug underwent several NIH and Breakthrough T1D-funded clinical trials; it was TrialNet’s TN-10 clinical trial that pushed it over the finish line to FDA approval in 2022, with the support of Provention Bio.
In 2023, Provention Bio was acquired by Sanofi. This brought the first T1D disease-modifying therapy into the portfolio of a leading global pharmaceutical company. It also represented a significant endorsement of the potential of DMTs to have an impact on people living with T1D.
People like Chris Dunn.
Breakthroughs in Action
Chris Dunn is a parent of four children, two of whom live with T1D. Knowing that immediate family connections are a risk factor for developing T1D, Chris and her children without T1D participated in screening.
Much to her surprise, Chris’ screening results revealed the presence of multiple T1D antibodies; further testing indicated she was in stage 2. Chris knew that Tzield could potentially delay her need for insulin therapy, so she made the informed decision to undergo treatment.
“I’ve had a front row seat to this disease for nearly 20 years,” Chris said. “Any day that you can save yourself from having to be on insulin therapy and all of the risks that come with that is worth it to me.”
Chris represents our research breakthroughs in action. She hopes that Tzield will delay the onset of Stage 3 T1D until cell therapies are available to cure the disease.
The Future of Tzield
As Tzield becomes more widely used in people over the age of 8 in Stage 2 type 1 diabetes, Breakthrough T1D’s Disease-Modifying Therapies Program is exploring how it may benefit other ages and stages.
“We continue to fund research to discover and develop new interventions and new ways of rebalancing the immune system, ultimately working toward our goal of a world without type 1 diabetes,” said Joshua Vieth, Ph.D., Senior Director of Research at Breakthrough T1D.
In October 2025, Tzield was accepted into the FDA Commissioner’s National Priority Voucher program for accelerated review. If approved, this could lead to expanded use of Tzield for people with newly diagnosed Stage 3 T1D (when insulin therapy is required). This is significant—it would be the first time people at this stage could have the option for a disease-modifying therapy.
Delaying the onset of T1D in young children would be transformative for families facing a diagnosis. Interim results from an ongoing clinical trial, PETITE-T1D, showed that Tzield is safe and well-tolerated in children under 8 with Stage 2 T1D. Final results of the study are expected sometime this year, and Tzield has been accepted for priority review by the FDA for this population.
While Tzield is the first approved disease-modifying therapy for T1D, Breakthrough T1D will make sure it’s not the last. Our goal is to not just delay T1D progression but stop it entirely, or even reverse its course. We will support the continuous development of these therapies to change the trajectory of type 1 diabetes for everyone affected by it—and those yet to be—to cure the disease.
Closing the gap between access to and adoption of type 1 diabetes (T1D) therapies is a mission priority for Breakthrough T1D.
Our newly created Medical Affairs unit provides education and resources for the entire T1D community, from clinicians to people living with the condition, so that everyone impacted by T1D is empowered to make informed decisions about healthcare and emerging therapies.
Chris Dunn represents our efforts in action.

Chris is a parent to four children, two of whom live with T1D. Knowing the increased risk of T1D in immediate family members, Chris and her children without T1D participated in screening. In what she could only describe as “surreal,” Chris’ screening results revealed the presence of multiple T1D antibodies; further testing indicated she was in stage 2.
For decades, Breakthrough T1D funded discovery research, supported clinical development, and worked with regulators to bring Tzield—the first disease-modifying therapy for type 1 diabetes—to market. Tzield is available to people in stage 2 type 1 diabetes—like Chris—and can delay progression to stage 3, or clinical onset of T1D, for up to three years. This means potentially years without blood-sugar monitoring, insulin administration, and the fear of short- and long-term complications.
Watch Chris’s story now:
Part 1: Screening and Early Detection
Part 2: Early Detection and Disease-Modifying Therapies
What’s happening?
Earlier today, Eli Lilly and Company announced that they are launching two new clinical trials for baricitinib in type 1 diabetes (T1D). These phase 3 trials will investigate whether the drug can delay T1D onset or progression and will open for recruitment soon. Read on to learn more about the trials, why this matters, and what led to this exciting news.
Baricitinib has shown promise for T1D
Baricitinib is a JAK inhibitor that interferes with signaling pathways critical to both immune cells and beta cells. This drug has the potential to extend the “honeymoon period” of T1D, meaning that it could preserve remaining insulin-producing beta cells earlier in disease progression. More beta cells mean better blood sugar management—and potentially reduced long-term complications.
JAK inhibitors
JAK inhibitors, including baricitinib, are already FDA-approved for other autoimmune diseases, such as rheumatoid arthritis, alopecia, and more. JAK signaling pathways are associated with overactive immune responses, so blocking this pathway may turn down the immune response.
The phase 2 Breakthrough T1D-funded BANDIT study was key in showing that this drug is safe and effective in T1D. This study was led by Professor Thomas Kay, MBBS, Ph.D., and his team at St. Vincent’s Institute of Medical Research in Australia. In this trial, more than 90 newly diagnosed individuals with stage 3 T1D between the ages of ten and 30 were treated with either baricitinib (as a single, daily oral tablet) or placebo for 48 weeks.
The results were positive: people treated with baricitinib had increased insulin production, spent more time-in-range, needed less external insulin, and experienced minimal side effects. These data were published in the prestigious New England Journal of Medicine and inspired the launch of another clinical trial (JAKPOT T1D) investigating different JAK inhibitors in preserving beta cells in T1D.
Thanks to the BANDIT study, which stemmed from years of work with Lilly to supply the drug for the trial, we got the convincing data needed to move baricitinib to phase 3—and one step closer to people with T1D.
The new studies
The new studies will be recruiting soon at medical centers around the globe. Participants in either trial will randomly receive either baricitinib or placebo. The studies are also double-blinded, meaning that neither the study team nor individuals will know whether they are administering or receiving baricitinib or a placebo. Importantly, baricitinib is a once-daily oral pill—meaning its use is simple and easy.
BARICADE-DELAY
- Purpose: To determine if baricitinib can delay the onset of clinical stage 3 T1D in people who are at high risk
- Eligibility: Must be between one and 36 years old and be in stage 2 T1D
- Time commitment: Up to approximately five years
- Primary outcome: Time to diagnosis of stage 3 T1D
BARICADE-PRESERVE
- Purpose: To determine if baricitinib can preserve beta cell function in people with newly diagnosed T1D
- Eligibility: Must be between one and 36 years old and diagnosed with stage 3 T1D within the last 100 days
- Time commitment: About 60 weeks
- Primary endpoint: C-peptide preservation (a measure of insulin production)
Breakthrough T1D is a supporter of baricitinib
Breakthrough T1D has been a tireless advocate for the use of JAK inhibitors in T1D. In conjunction with our Australia affiliate, we funded the BANDIT study, which generated the positive data that provided the basis for these new clinical trials.
Baricitinib is a cornerstone of our Disease-Modifying Therapies Program, which aims to find treatments that can delay, halt, reverse, or prevent T1D. The progression of baricitinib through the pipeline is a perfect example of what we do best: identify a promising therapy, collaborate with industry to support or fund initial clinical trials that establish a therapy’s effects in T1D, facilitate the path towards an industry-sponsored phase 3 trial, and help recruit trial participants to accelerate progress.
We will continue to follow these studies closely and look forward to seeing the results. We encourage our community and supporters to spread the word—if you or anyone you know may be eligible for these trials, share this information!
Finally, we thank Lilly for their shared commitment to our mission: a world without T1D. Industry investment in clinical trials for T1D helps us progress faster—and with partners like Lilly, we’ll get more therapeutic options to people with T1D sooner.

“Breakthrough T1D has been a tireless advocate for the use of JAK inhibitors and has seen the promise of baricitinib as a therapy for type 1 diabetes to preserve insulin production and delay disease progression,” said Breakthrough T1D Chief Scientific Officer Sanjoy Dutta, Ph.D. “We’re thrilled that Lilly is advancing clinical research with baricitinib and thank them for moving us one step closer to making it available for people with type 1 diabetes.”
“In the BANDIT trial we tested for the first time whether baricitinib could preserve insulin-producing cells under autoimmune attack in type 1 diabetes. Years of laboratory work indicated that this drug should be effective. Baricitinib given for 12 months maintained insulin production compared with its loss with placebo. We are grateful to Breakthrough T1D and Lilly for their support of the trial. This was a very exciting outcome from our bench to bedside research. Current insulin therapy is life-saving in diabetes but it is imperfect, and new treatments such as baricitinib show promise. Preservation of insulin production allows the body’s own amazing processes to control blood glucose and reduce the burden of type 1 diabetes. We hope that the BARICADE trials will confirm our findings and extend them to people with earlier diabetes, before insulin is required, and lead to the use of baricitinib in clinical practice for type 1 diabetes.” – Professor Tom Kay, Director, St Vincent’s Institute of Medical Research (SVI) in Melbourne, Australia

Get involved in clinical trials
Clinical trials are key to bringing new treatments, devices, and therapies from labs and into clinics. People who choose to participate in clinical trials help drive progress forward for the entire T1D community. If you or anyone you know is interested in participating in a clinical trial, use our Clinical Trials Matching Tool to find a trial that you may be eligible for. You can also reach out to a Clinical Trial Education Volunteer in your area to connect and answer any questions you may have. Information about the new baricitinib clinical trials will be available on our clinical trials web page when enrollment begins.
This past week, the FDA and Sanofi, the maker of Tzield, made an important announcement. Tzield, the first disease-modifying therapy approved for delaying onset of stage 3 type 1 diabetes (T1D) in people with stage 2 T1D, has been accepted into the FDA Commissioner’s National Priority Voucher (CNPV) program for people with stage 3 T1D.
Here’s what it means—and why.
The FDA Commissioner’s National Priority Voucher (CNPV) Pilot Program
The CNPV program aims to accelerate the drug review process for companies aligned with U.S. national priorities that address a large, unmet medical need while maintaining the FDA’s rigorous standards for safety, efficacy, and quality.
This program endeavors to reduce the review time for products from 10-12 months to 1-2 months. However, the program does not guarantee approval and the FDA reserves the right to determine the best course of action for the product’s being reviewed.
On Friday, October 17, the first 9 recipients of vouchers were announced, and Sanofi received one for Tzield in stage 3 individuals.
Why Tzield?
In short: the FDA recognizes there is a large unmet need in the T1D population, and Tzield has the potential to address these needs.
Sanofi’s Tzield is the first disease-modifying therapy approved to delay onset of stage 3 T1D in people with stage 2 T1D. (Stage 2 T1D is indicated by the presence of multiple autoantibodies and abnormal blood sugar levels, but individuals are not requiring insulin therapy yet). Tzield, which has been supported by Breakthrough T1D for decades, has been a gamechanger in T1D as it’s the first therapy for this disease that addresses the root cause of T1D, not the symptoms. It targets the T cells that are responsible for destroying insulin-producing beta cells, slowing down the autoimmune processes that cause T1D. In stage 2, this means a stage 3 diagnosis is delayed an average of 3 years.
The problem: it’s only approved for use in stage 2 T1D. The vast majority of people in stage 2 don’t even know they have early T1D because there are no external symptoms. The only way of knowing is to get screened for risk markers of T1D. While the number of individuals screened for T1D has dramatically risen in recent years, most people who may benefit from the drug progress to stage 3 before they have the chance to reap its benefits—and delay onset.
Additionally, Tzield already being reviewed under the FDA’s accelerated approval program. Sanofi is continuing to study Tzield in this patient population through the confirmatory BETA-PRESERVE phase 3 study, which will provide more information on the risks and benefits of the drug in the coming years.
Breakthrough T1D has supported the development of Tzield for decades—and supports its use in stage 3 T1D.
Preserving beta cell health is critical
T1D is caused by the destruction of the beta cells, which are the only cells in the body that make insulin. The fewer beta cells a person has, the less insulin they make.
Simply put, it’s better to have more beta cells, and longer we can keep those cells alive and making insulin, the better. There are many studies that support this, but one study in particular really demonstrated the benefits.
The PROTECT Study
In the PROTECT study, Tzield was administered to newly diagnosed children and adolescents in stage 3 T1D to see if it could slow the destruction of beta cells as measured by C-peptide. (C-peptide is a natural byproduct of insulin production and a key biomarker as we evaluate the efficacy of Cures therapies).
In this study, investigators looked at newly diagnosed individuals who were administered Tzield compared with placebo and measured their beta cell function (using C-peptide) over time. The results were clear: Tzield significantly slowed the decline of beta cell function. This has real impact on the lives of people with T1D, too. People who received Tzield and therefore had higher levels of endogenous insulin production required less insulin and spent more time in range.
In summary: more beta cells are better. Tzield has demonstrated that it can help achieve that.
What happens next?
Sanofi could hear from the FDA in the next 1-2 months that Tzield has been approved for use in stage 3 T1D. If that happens, it will mean that, for the first time, individuals diagnosed with T1D have a therapy option besides insulin. This would be a historic first, allowing people to benefit from the decline in the loss of beta cells and modify the course of T1D like the PROTECT study has demonstrated.
What we’re saying
“We know two things: there is a large, unmet need in the T1D community for more therapy options, and there is significant data demonstrating the benefits of preserving beta cell health,” said Campbell Hutton, Senior Vice President, Global Advocacy. “Breakthrough T1D applauds the FDA for accelerating the review process of a therapy that can have significant positive impact for the T1D community.”

