Bonjour from Montreal, Canada, where the latest and greatest in type 1 diabetes (T1D) research was presented at the International Society for Pediatric and Adolescent Diabetes (ISPAD) 51st Annual Conference. ISPAD is a yearly highlight of the T1D conference calendar, and this year was no exception. Scientists, clinicians, researchers, industry members, people with diabetes, and more were on hand to provide updates in cures, improving lives, access, and more—with much of it being supported by Breakthrough T1D.
Let’s take a look at the highlights.
About ISPAD
ISPAD is one of Breakthrough T1D’s peer organizations. They are dedicated to childhood and adolescent diabetes all over the world. In addition to collaborating in scientific advancements, Breakthrough T1D and ISPAD also fund several grants together—including providing support for clinical fellows from around the world to learn how to care for people with T1D from top-tier clinicians.
Tzield is being studied in kids under 8
Tzield has been in the news for a variety of reasons lately. Sanofi—the manufacturer of Tzield—recently received a voucher from the FDA for the use of Tzield in symptomatic, stage 3 T1D (for which it is not yet approved), potentially expediting the regulatory review process.
Tzield is currently approved for children and adults aged eight years and older in stage 2 T1D to delay the onset of stage 3 T1D. An ongoing study is investigating if Tzield can delay the progression of T1D from stage 2 to stage 3 in a new demographic: kids under eight.
At the ISPAD conference, researchers presented an interim analysis from the PETITE-T1D study, which is investigating if Tzield is as safe and tolerable in kids under eight in stage 2 T1D as it is in older individuals.
So far, 23 children have received a 14-day course of Tzield. To date, the safety and tolerability profile of Tzield is similar to that of older individuals who receive the drug. Two children in the study have progressed to stage 3 T1D.
This study is ongoing and we look forward to seeing more data.
Key takeaway
Tzield can delay T1D onset by an average of 3 years. This important study is determining if a new population—kids with T1D under eight years old—can benefit, and the data so far is encouraging.
Breakthrough T1D taking the stage
Breakthrough T1D leadership was on site to present and chair sessions.
Chief Scientific Officer Sanjoy Dutta, Ph.D., gave an overview of Breakthrough TD’s mission strategy and chaired a session jointly with ISPAD.
Chief Medical Officer, Global, Thomas Danne, M.D., was there to discuss Time in Normoglycemia, which is blood sugars between 70 and 140 mg/dl, and how technology can help kids achieve it.
Vice President of Medical Affairs, Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES, served as faculty for the 21st Annual ISPAD Science School for Health Professionals that took place immediately before the ISPAD Conference.
Community Engagement & Communications Director, Global Access & Global Responsibility, Renza Scibilia, hosted a symposium on advancing diabetes care in complex settings.
Technology improves outcomes
A motif that was repeated by many, many investigators: automated insulin delivery (AID) systems help people do better. This spans several different technologies and systems: Tandem Control IQ, Minimed 780G, Cam APS, and OmniPod. Here’s why:
The near-constant adjustments made by these systems are always working to meet glycemic targets.
They can help people get closer to their glycemic targets with less user input.
They lower the mental burden of T1D, helping people less engaged with managing their T1D do better.
Key takeaway
It is widely established that AID systems lead to better outcomes. It’s important to continue to ensure that everyone has access to these systems and that they work better with less user input. They must become the standard of care across the world for kids with T1D.
The importance of clinical trials for stage 3 T1D
Stage 3 is when people are typically diagnosed with T1D. At this stage, beta cell function has not been completely eliminated. Individuals are still making insulin—not enough, but some. Decades of research by Breakthrough T1D and others has demonstrated clear benefits to holding onto beta cell function for as long as possible.
Clinical trials for individuals in stage 3 are few and far between. While there are exceptions (like the recently announced BARICADE-PRESERVE), we need more trials because people in stage 3 T1D can benefit from therapies to keep these cells alive and producing insulin for longer.
Key takeaway
Prioritizing clinical trials for stage 3 T1D—and recruiting for them—can be a bridge between better glycemic control today and future cures.
Stay tuned for the 2025 Top Advances piece in the coming weeks to see everything we’ve accomplished this year as we look towards the next one.
To drive our mission forward, Breakthrough T1D financially supports type 1 diabetes (T1D) research through training awards and grants to academic scientists or clinicians, investments in promising companies, conference support, and more. Here, we take a deeper dive specifically into our training awards offered to early-stage researchers to understand the impact and outcomes that these awards have on individual careers and T1D research as a whole.
Key Takeaways
Breakthrough T1D conducted a survey of researchers and clinicians who received training awards from 2015 to 2024, totaling $62,513,719 in funding.
The purpose was to understand the impact of the training awards on career decisions and the research and clinical outcomes stemming from the awards.
Most Breakthrough T1D award recipients stayed in diabetes research or clinical practice after the award ended.
Training award recipients reported publications, patents, honors, clinical trials, collaborations, resources, and mentoring of new trainees arising from Breakthrough T1D training awards.
Recipients gave positive feedback on the awards, and many continue to be involved in Breakthrough T1D beyond applying for funding.
Why did we conduct this survey?
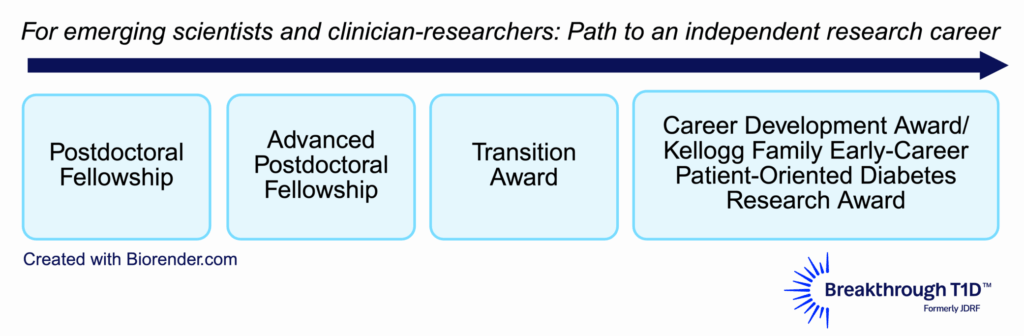
Training awards are a key part of Breakthrough T1D’s grants portfolio. These awards support early-career scientists and clinical researchers to explore promising ideas and encourage trainees to follow career paths that drive T1D research forward. Our approach is designed to provide opportunities to support trainees from an early postdoctoral stage (after receiving a higher degree) to transitioning to an independent lab and career as a T1D researcher.
Breakthrough T1D offers opportunities for funding at different stages of early career development on the path to independence.
Breakthrough T1D previously conducted surveys analyzing the impact and outcomes of training awards completed between 1974 to 2014, revealing that these awards encouraged long-term pursuit of a career in T1D. The current survey included an expanded analysis on training awards completed between 2015 to 2024. The results provide a broader understanding of how our financial support impacts research outcomes, career paths, and additional funding secured by awardees. This way, we can ensure that our funds for trainees are being used in the best way possible, supporting the best and brightest researchers and ideas that drive our mission forward now and in the future.
Survey methodology
From 2015 to 2024…
$62,513,719
Dollar amount of Breakthrough T1D funds invested in training awards
269
Number of training awards granted
230
Number of unique award recipients
Types of training awards surveyed
Training award
Number of awards granted between 2015-2024
Number of awards evaluated based on survey responses
Postdoctoral Fellowship
155
80
Advanced Postdoctoral Fellowship
48
35
Career Development Awards
36
26
Kellogg Family Early Career Patient-Oriented Diabetes Research Awards
8
4
Transition Awards
22
17
Total
269
162
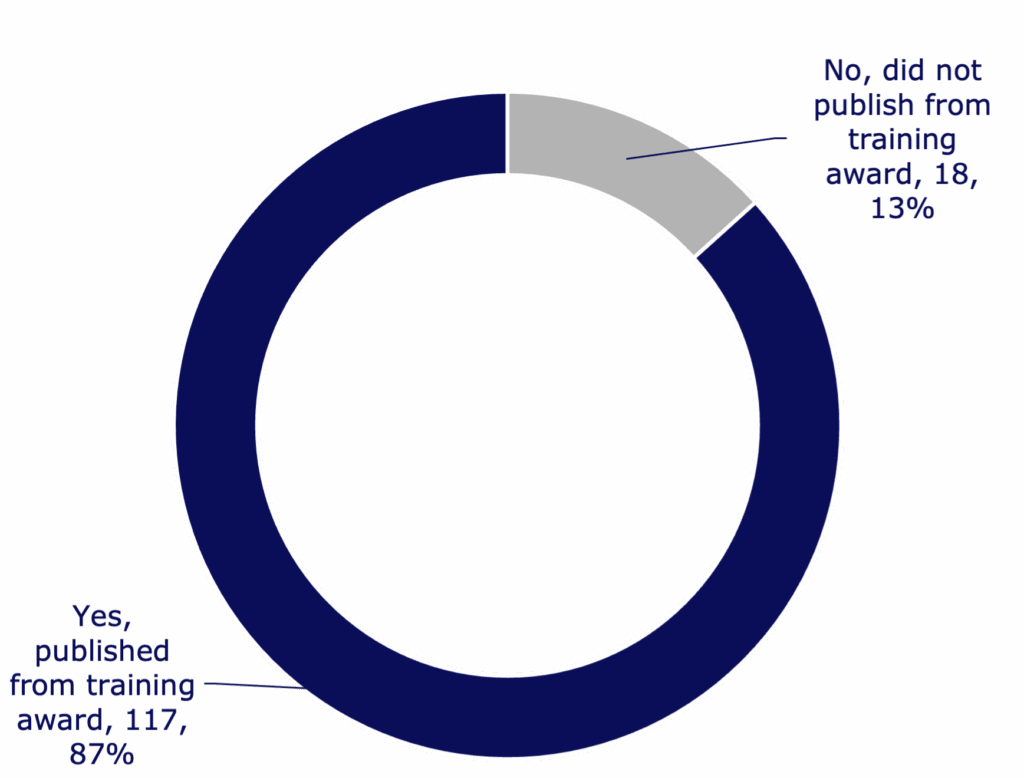
Of the total training awards funded between 2015 to 2024, this survey is a reflection of 135 respondents (60%) covering 162 awards. Respondent data was analyzed, mapped, and reported.
Percent of respondents who remained in academia after award completion
79%
Percent of respondents still working in diabetes (including T1D and type 2 diabetes) in both research and/or clinical practice
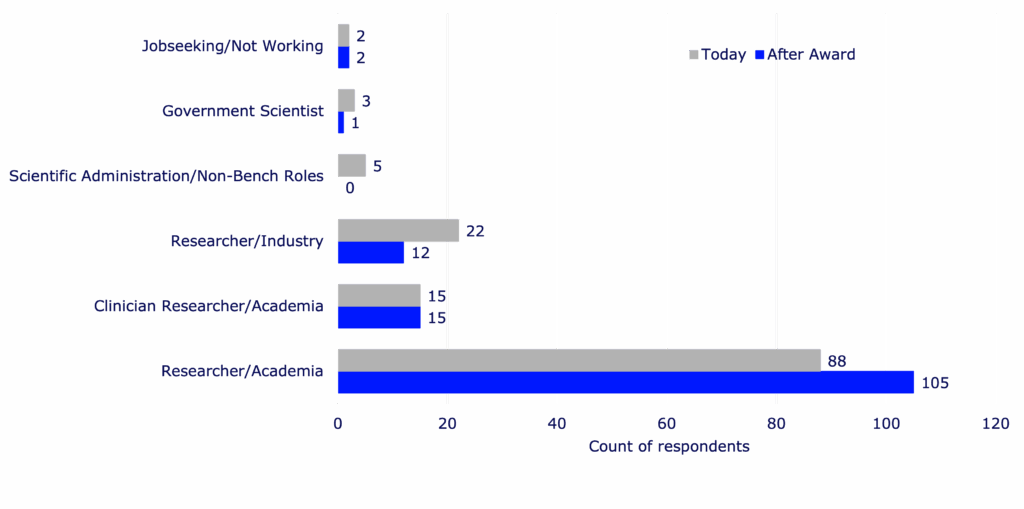
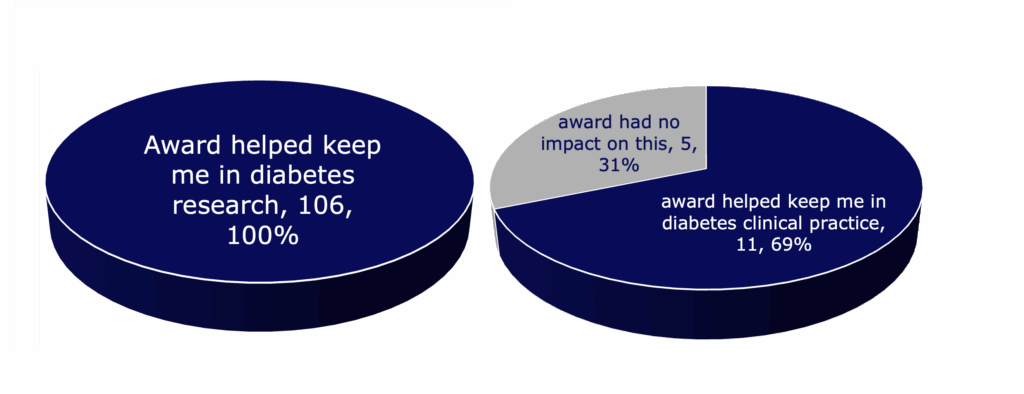
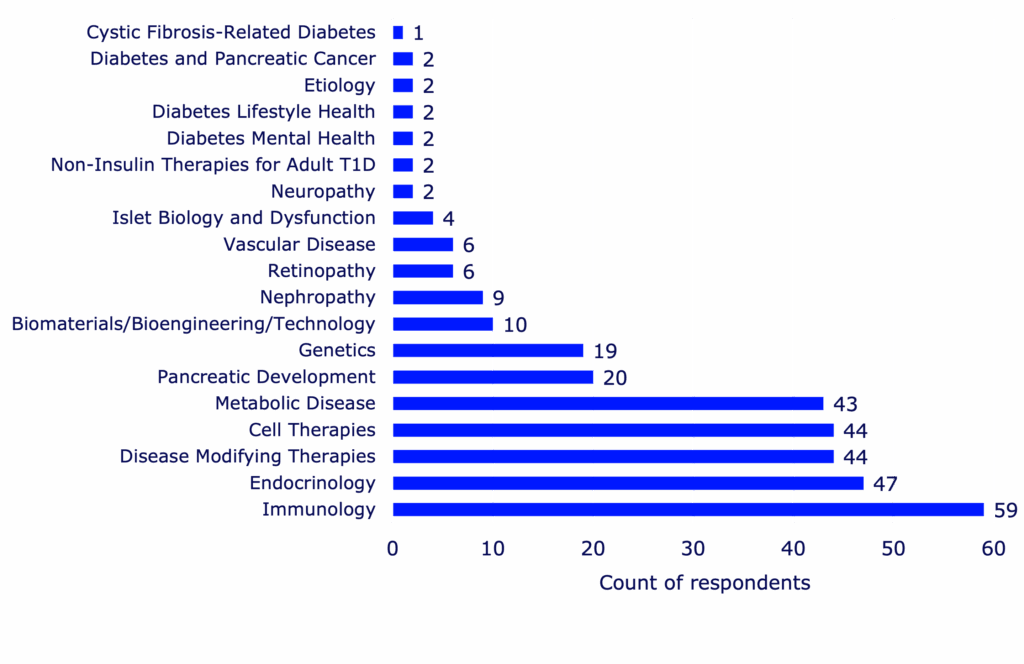
Number of respondents in the job they hold today (gray; “Today”) versus the job they took immediately after the training award ended (blue; “After award”).Number and percent of respondents who reported whether Breakthrough T1D training awards influenced their decision to stay in diabetes research or clinical practice.Areas of focus of respondents who stayed in diabetes research. Note that respondents could choose as many options as applicable.
Essential findings: Career trajectories for training award recipients
Researchers take on more senior positions post-Breakthrough T1D award, including tenure-track roles.
Every respondent working in diabetes research reported that the training award influenced their decision to continue to focus on diabetes.
Those who received more advanced training awards were more likely to stay in the diabetes field.
The main reasons researchers and clinicians stayed in diabetes are that the awards support training, networking, and publications.
If given the option, most respondents chose the Breakthrough T1D training award over other training award options, primarily due to prestige and better award terms.
Impacts on research outcomes
Research supported by training awards resulted in a variety of outcomes that could benefit the larger scientific community and drive T1D research forward. Readouts of successful research include peer-reviewed journal publications, clinical trials, patents, collaborations, resources, grant review requests, and research honors or recognitions.
Number and percent of respondents who published research stemming from the training award in peer-reviewed journals.
463
Number of published papers reported by respondents
176
Number of journals that respondents published in
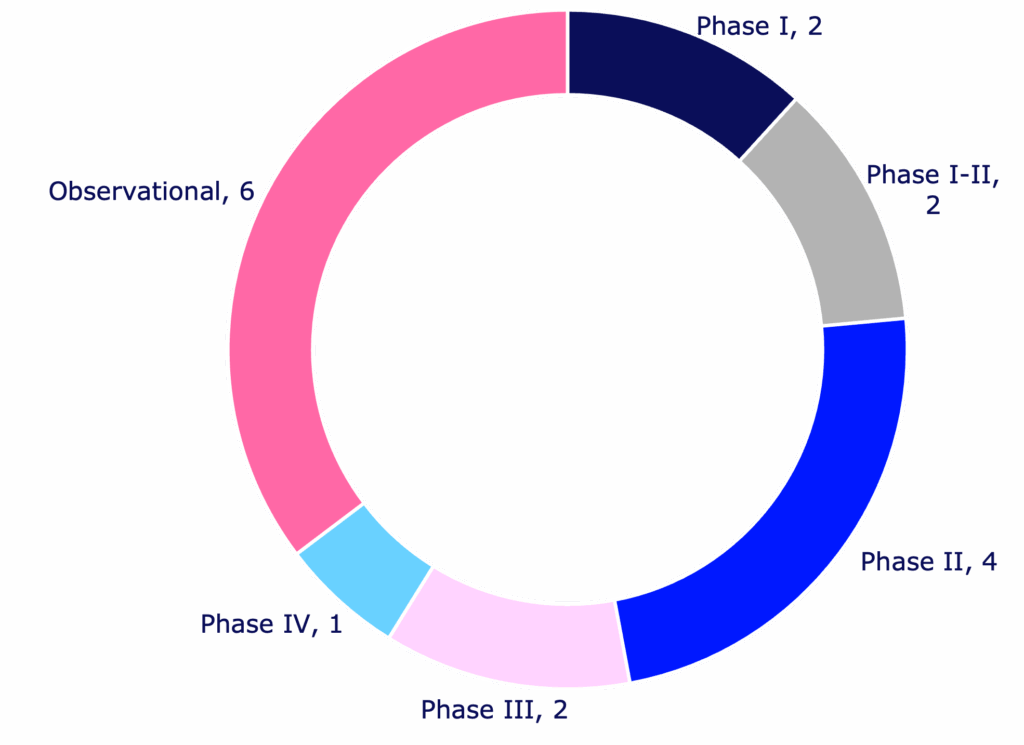
Number of clinical trials (17 total) initiated at different phases stemming from research completed with training award funds. These trials focused on new therapies, beta cell replacement, and improvements to closed-loop systems.
41
Number of patent-related activities reported from training awards
57%
Percent of respondents who formed at least one and often multiple collaborations throughout the training award
57
Number of different shareable resources developed by award recipients
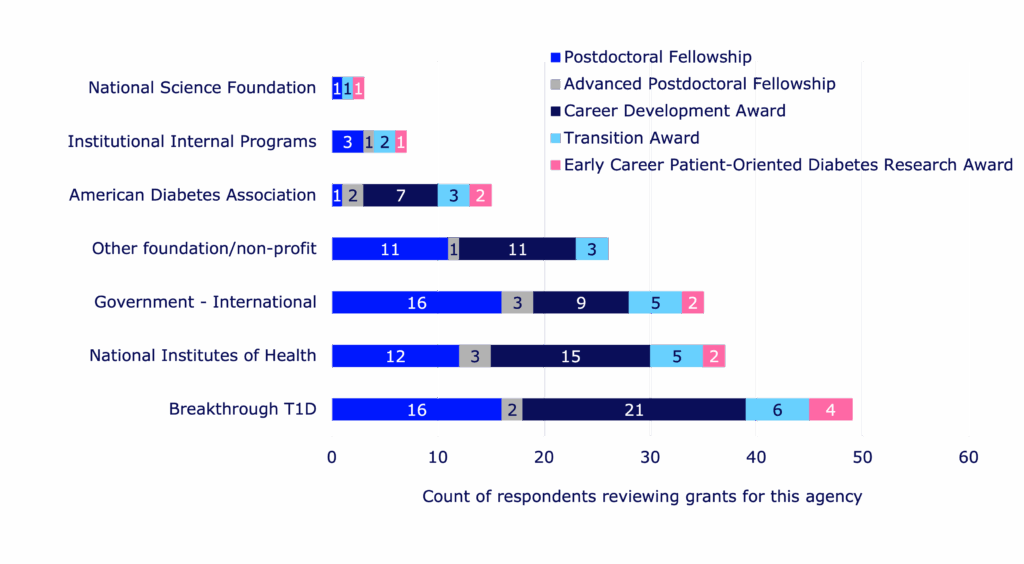
Number of respondents (60%) who serve as grant reviewers at indicated agencies, broken out by training award mechanism. Invitations to review grants is a sign of scientific expertise in a given field.
39%
Percent of respondents who serve as grant reviewers for Breakthrough T1D
31
Percent of respondents who reported receiving at least one research honor
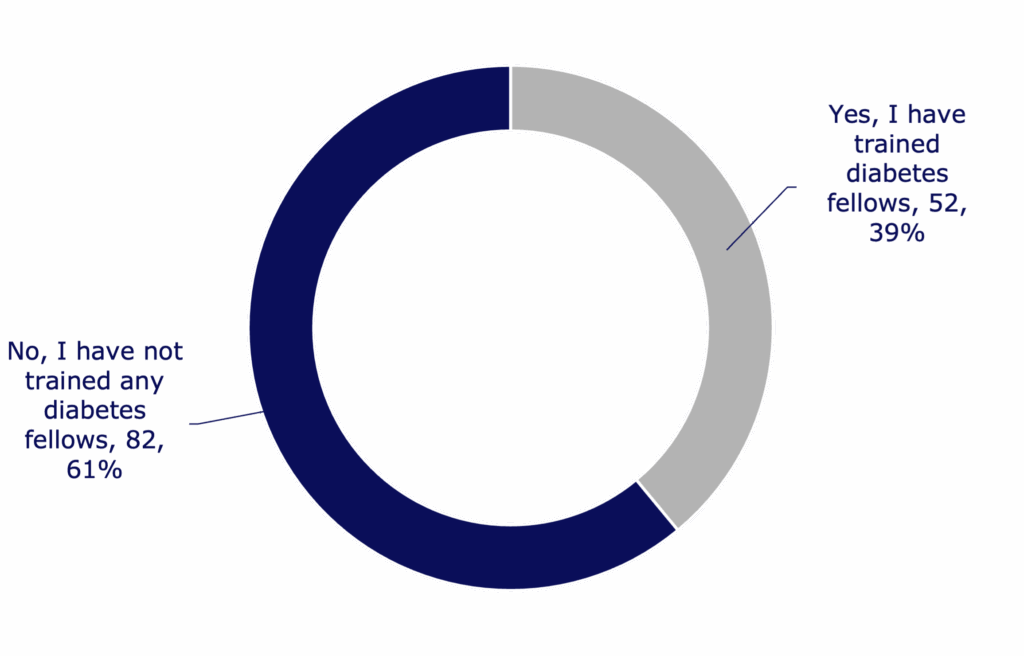
Percent and number of respondents who reported training their own diabetes research fellows.
91
Total number of research fellows trained by respondents
84%
Percent of next-generation trainees in academic research or clinical practice
Essential findings: Research outcomes stemming from awards
Respondents from every single type of training award report having trained a next-generation diabetes research fellow.
Recipients of Career Development Awards published the most papers and formed the most collaborations.
Recipients of Postdoctoral Fellowships were the least likely to form a collaboration, revealing a potential opportunity for Breakthrough T1D to help facilitate more collaborative connections amongst this awardee group.
Awardees reported holding various professional roles in the diabetes community, including consultants to nonprofits and industry, conference planners, program leaders, and manuscript reviewers.
The most prominent honor reported was a recognition or excellence award.
Impacts on securing additional funding
Breakthrough T1D training awards help early-career researchers continue an engaging and successful career in diabetes research. This is an important factor in securing further funding after the awards end, which helps researchers and clinicians maintain the ability to continue critical research that helps drive our mission forward.
78%
Percent of respondents who reported receiving additional research funding since the completion of the training award
$327,880,689
Dollar amount of additional research funding secured by respondents from various funding sources
Essential findings: Additional funds secured for research
For each training award, recipients secured at least five times the training award amount in additional funding post-award.
Postdoctoral fellows exhibited the greatest return on investment—meaning they secured the greatest amount of additional funding after the award ended.
Overall impacts on early career development
Top five areas of overall impact reported by respondents.
Essential findings: Impact on early career development as a whole
Early-stage trainees prioritize the ability to test a promising research idea that others would not support.
Later-stage trainees prioritize getting promotion or tenure and generating data to secure additional research funding.
Training awards are key to achieving our mission
Based on these data, it’s clear that Breakthrough T1D’s training awards impact early-career researchers and clinicians across the board: from career development, to training the next generation, to securing additional research funding, to publishing more papers.
This is exemplified by feedback from trainees. Some reported that Breakthrough T1D’s training awards are the best in their class and are critical for T1D research, including the ability to execute niche projects that other funding agencies would not support. Most respondents reported being immensely grateful for their training awards. See what some of the awardees have to say:
“Unequivocally, the award launched my career as a diabetes researcher.”
–Danielle Dean, Ph.D., Postdoctoral Fellowship Award recipient
“I am now fortunate to have mentees below me (one of whom received a Career Development Award). So not only did this award help me, but it helped establish an enduring source for new trainees interested in diabetes research.”
–Jeremy Pettus, M.D., Kellogg Family Early Career Patient-Oriented Diabetes Research Award recipient
“[I have made] International collaborations … research institutions and biotech companies to advance therapy development… partnerships across Europe, Asia, and the U.S.”
–Luis Arnes, Ph.D., Advanced Post Doctoral Fellowship and Transition Award recipient
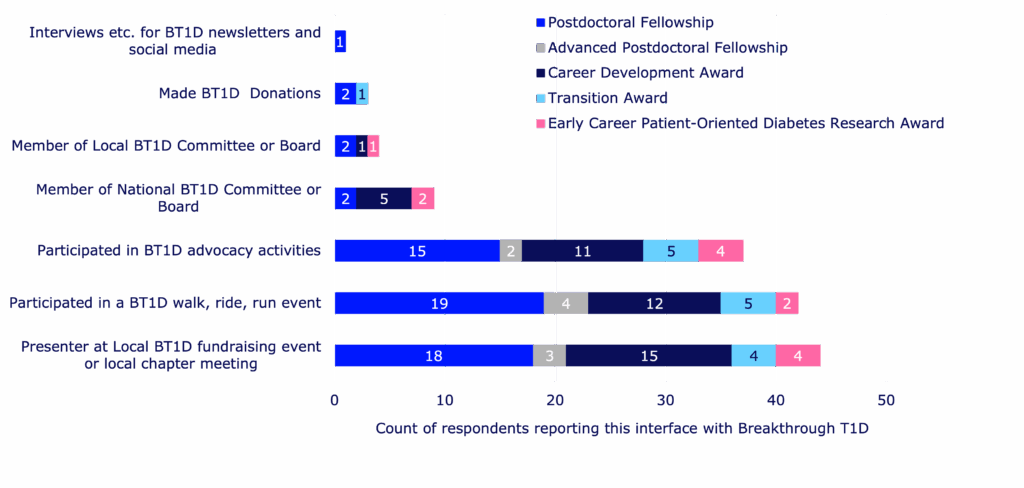
Ways in which respondents (50%) continued to engage with Breakthrough T1D after the award ended, parsed out by training award mechanism.
Not only do these awards help retain talent in diabetes research, but they also help awardees maintain connections with Breakthrough T1D as a whole—outside of seeking financial support. Training award recipients have presented research updates at local events, participated in Breakthrough T1D fundraising activities, and supported our advocacy efforts. We are helping to build the next generation of T1D researchers, advocates, T1D community supporters, and more—all working toward the same goal of a world without T1D.
This survey has put into context where our money is going—and it’s going to the right places. Helping to train the next generation of scientists and clinicians is key to the success of our mission. We’re seeing significant returns on our investments, embodied by trainees securing substantial funding for ongoing T1D research, the creation of shareable resources that will help drive research forward and increase collaboration, and the success of our awardees in securing desirable jobs and leadership positions.
We put our time and money into identifying the best-and-brightest scientists and ideas, encourage them to stay in the field, and guide them as they pass the torch to the upcoming talented pool of young T1D researchers. We support scientists so they can do the important work that will help people with T1D live better lives—and maybe one day live without T1D. And, most importantly, we wouldn’t be able to do this without YOU: our supporters, our donors, and the entire T1D community that allows us to do what we do every day—improve the lives of people with T1D as we drive towards a cure. Thank you.
The full-length report was put together with the assistance of Breakthrough T1D consultant Kim Hunter-Schaedle.
The short version
Breakthrough T1D’s newest publication outlines what the future of beta cell replacement therapies looks like—and how we can make these therapies a reality for everyone with type 1 diabetes (T1D) who wants them through innovative clinical trial design and expanding the pool of eligible trial participants.
Breakthrough T1D, in collaboration with other leading experts in the field, recently published an article titled “Future Directions and Clinical Trial Considerations for Novel Islet β-Cell Replacement Therapies for Type 1 Diabetes” in the journal Diabetes. Breakthrough T1D Research and Advocacy staff who contributed to the publication include Sanjoy Dutta, Ph.D., Chief Scientific Officer, Esther Latres, Ph.D., Vice President of Research, and Marjana Marinac, Pharm.D., Associate Vice President of Regulatory Affairs.
Beta cell replacement therapies have the potential to cure type 1 diabetes (T1D) by removing the need for external insulin. While donor islet transplantation can result in insulin independence and results from early trials with manufactured islets are encouraging, people with T1D need better tools and therapies. This publication serves as a roadmap for the entire field—including researchers, product developers, industry, regulators, clinicians, and people with T1D—to address these needs and ensure that beta cell replacement therapies can get to people with T1D as quickly and safely as possible.
Read on to learn more about what the future of beta cell replacement therapies looks like.
Key Takeaways
Currently available beta cell replacement therapies are limited to people with T1D with unstable blood sugar management, typically measured by HbA1c levels, in addition to dangerous lows (hypoglycemic events) that require immediate assistance. These therapies also require lifelong immunosuppression.
New and improved beta cell replacement therapies are on the way, and we need to make sure that they are available for people with T1D beyond those with unstable blood sugar management and severe hypoglycemic events.
Clinical trials for these therapies must be strategically designed to include more people with T1D given the potential for insulin independence.
Shared decision-making between people with T1D and their care team will be critical for evaluating the risks versus benefits of a beta cell replacement therapy, especially as more options become available.
People living with T1D depend on external insulin to manage their condition throughout their lives. Despite advancements in diabetes technology, such as continuous glucose monitors (CGMs) and automated insulin delivery (AID) systems, most people with T1D are unable to achieve blood sugar targets, rendering them at a higher risk for complications, reduced quality of life, and lower life expectancy.
One promising avenue to meet these needs is through cell replacement therapy. Lantidra®, the first FDA-approved donor-derived islet replacement therapy for T1D, has proven to be safe and effective in eliminating severe hypoglycemia, providing insulin independence, and improving quality of life. However, this therapy is limited to people with severe hypoglycemia and requires immunosuppression to prevent rejection of the transplanted cells, which can have side effects. Even more, these donor-derived islets are in limited supply.
Alternative beta cell replacement therapies are emerging—and we can no longer limit their development to people experiencing severe hypoglycemia.
As stated in the publication:
Given the proven benefits of islet transplantation extending far beyond the amelioration of severe hypoglycemia that has been documented and the understanding of the risk profile gained over the past 20 years, consideration must be given to broadening the application for islet beta cell replacement.
Developing cell therapy strategies to meet unmet needs of the T1D population
Breakthrough T1D’s vision for the T1D community includes beta cell replacement therapies with no immunosuppression that are available to everyone who wants them. We are committed to making this a reality through our Project ACT (Accelerate Cell Therapies) initiative, which will accelerate the development of these therapies to achieve our vision as quickly as possible.
Project ACT
Scientific progress takes time, resources, collaborations, and effort. To accelerate islet replacement therapies faster than ever, Breakthrough T1D launched Project ACT (Accelerate Cell Therapies) to simultaneously advance research, development, regulatory policies, access, and adoption of manufactured islet therapies that do not require broad immunosuppression.
We are entering an exciting era of beta cell replacement. Emerging therapies are addressing challenges such as cell source and scalability, resulting in the development of islets derived from sources other than donors, including manufactured islets and porcine islets. Up-and-coming therapies are also testing different transplantation sites, methods of delivery, and cell protection strategies to prevent immune rejection with the fewest side effects possible (and ideally no immunosuppression). Learn more about what scientists are doing to optimize beta cell replacement therapies.
Breakthrough T1D’s continuous support of many of these therapies, such as Vertex’s manufactured islet therapy zimislecel, has been critical to accelerating them through the clinical pipeline. Explore emerging beta cell replacement therapies in clinical trials now—and see how Breakthrough T1D’s commitment to these therapies helped make this possible.
When successful, the advent of new, safe, scalable, and effective beta cell replacement therapies will provide the T1D community with options. As these therapies are moving their way through the pipeline, we need to ensure they are being studied in a broader T1D population who stand to benefit.
So, how do we make this happen?
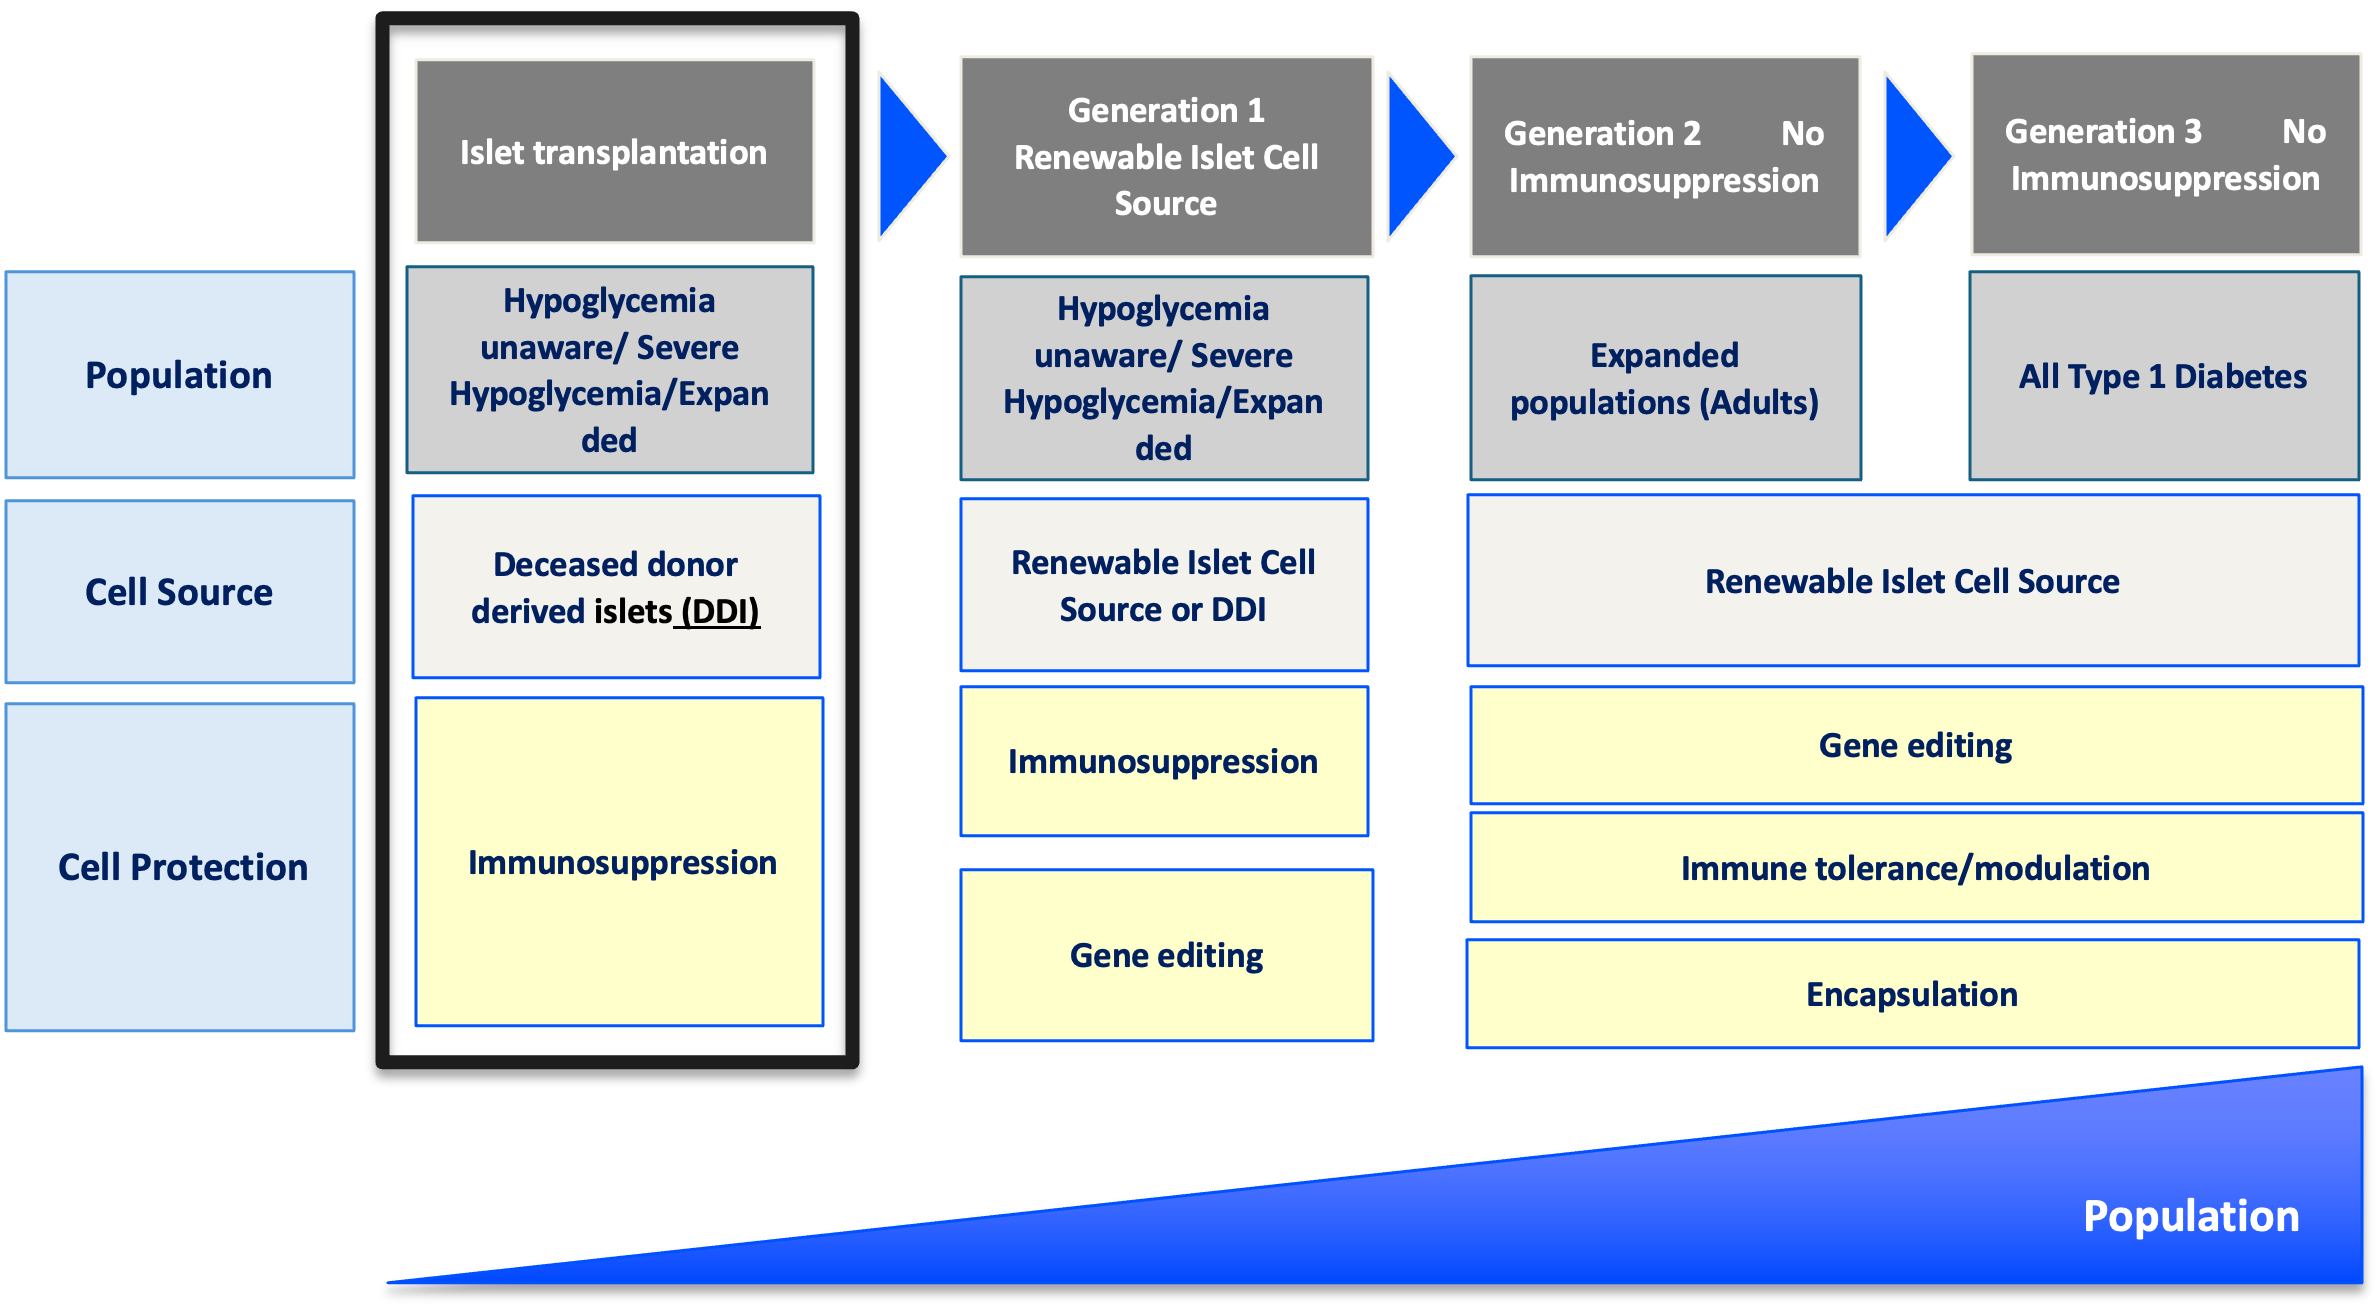
Breakthrough T1D’s roadmap for the future development of beta cell replacement therapies in T1D.
The roadmap for emerging beta cell replacement therapies
The goal
Accelerate availability of emerging next-generation beta cell replacement therapies for every person with T1D who wants them by designing clinical trials that speed their development, regulatory approval, access, and adoption.
Expanding the T1D population eligible for beta cell transplantation
Current trials testing beta cell therapies necessitating immunosuppression require participants to have elevated HbA1c levels and recurrent severe hypoglycemic events. This limits the pool of participants to people who meet the requirements and are most likely to benefit, given the side effects associated with chronic, broad immunosuppressants.
Clinical trials for emerging beta cell replacement therapies should broaden eligibility criteria so more people with T1D can participate—and experience the potential benefits. When designing new clinical trials, sponsors and regulators should consider including a broader range of HbA1c levels, clinically important or serious hypoglycemic events, and other complications.
Studies have found that the T1D community is generally open to beta cell replacement therapies as a potential solution to T1D, and people are willing to accept the associated risk versus benefit considerations for the possibility of becoming insulin independent. A Breakthrough T1D assessment also found that physicians are interested in recommending beta cell replacement therapies to people with T1D—especially if they don’t require immunosuppression.
“Clinical trials to support the development of islet cell replacement therapies need to evolve to include a broader representation of people living with T1D who could benefit from these novel therapies. This includes expanding the outcomes used to assess the benefits of cell replacement that reflect how people with T1D feel and function.”
Marjana Marinac, Pharm.D., Associate Vice President of Regulatory Affairs
Placing people with T1D at the center of clinical trial design
The outcomes used to assess the effectiveness of cell therapies currently in clinical trials, including those involving deceased donor islets, are acceptable for emerging beta cell replacement therapies. These include on-target HbA1c levels, absence of severe hypoglycemia, significant reduction or elimination of external insulin, and restoration of the body’s insulin production as measured by C-peptide.
Other endpoints that should be considered include CGM metric targets like time-in-range in addition to person-reported outcomes. Understanding how a beta cell therapy may affect a person’s health-related quality of life—such as diabetes distress, fear of hypoglycemia, or social and family dynamics—will be critically important for calculating the risk to benefit ratio of these therapies.
“There are still significant unmet needs in the T1D community. Breakthrough T1D’s roadmap is supported by the assessment of clinically meaningful outcomes and driving research toward solutions that address key factors such as cell sources and protections strategies that will broaden the people with T1D who could benefit from emerging cell replacement therapies.”
Esther Latres, Ph.D., Vice President of Research
Innovative trial designs to accelerate development of cell therapies
Clinical trials for beta cell replacement therapies are generally based on a single-arm, open-label design—meaning there is no placebo group and both participants and researchers know which therapy is being administered. While this design can work for emerging beta cell therapies, single trials with multiple arms testing alternative transplant sites, immune protection strategies, or other methods have the potential to speed up the pace of development.
Similarly, adaptive trial designs use mid-trial interim analyses of study data to inform the remainder of the trial. This helps researchers learn what’s working (or not working) and adjust the design accordingly, with guidance from regulatory agencies, so the rest of the trial is a focused and efficient use of time and resources. Potential interim changes to trial design include reducing the number of participants required, eliminating doses, recruiting people who are most likely to benefit, or stopping the trial outright due to clear success or failure.
By applying guidance in therapeutic development and innovative trial designs to emerging beta cell replacement therapies, we can move early-stage trials along faster, thereby allowing regulators to make decisions sooner. To support quicker trials and reduce the possibility for delays, researchers, developers, and regulators around the world need to work together to achieve convergence on trial populations, endpoints, and innovative designs that will meet regional requirements.
Learning from past successes
People with T1D continue to live with unmet needs with still significant risk for long-term complications, and they need more therapeutic options. Right now, most clinical trials for beta cell replacement therapies requiring immunosuppression are limited to a small portion of the T1D population. This needs to change—especially given the potential for insulin independence. The T1D community must be put first when making decisions about beta cell replacement therapies, and Breakthrough T1D is making sure that this happens.
Adjusting how we approach clinical trials for emerging beta cell replacement therapies will be critical for ensuring we accelerate the research, development, regulatory approval, access and adoption of these novel therapies. Breakthrough T1D successfully accomplished this for AID systems—and we are confident that following a similar roadmap for cell therapies will get us to the finish line, faster.
Curative therapies for T1D are in reach. This roadmap, in conjunction with our Project ACT initiative, is key to bringing beta cell replacement therapies to every person with T1D who wants them.
To make this a reality, everyone needs to work together. As stated in the publication, “This requires a comprehensive strategy and a coordinated collaboration across stakeholders in every field relevant to islet cell replacement.” This roadmap is a guide for moving toward our common goal of a cure for T1D as soon as possible.
Breakthrough T1D will continue to lead the way until the T1D community can choose the beta cell replacement therapy that works best for them, regardless of blood glucose management or hypoglycemia status. Everyone deserves the chance to benefit.
Key Takeaways
Breakthrough T1D helped organize a meeting in European Parliament to bring the unmet needs of the type 1 diabetes (T1D) community to the forefront and discuss how we can accelerate cures, especially cell therapies, in the EU.
This meeting was attended by several Breakthrough T1D leadership and staff.
Building long-term partnerships with the European Union (EU) Institutions will allow us to work together toward global T1D cures.
A meeting of the minds
This past week, Breakthrough T1D helped organize an event hosted by Member of European Parliament Tomislav Sokol, Ph.D., titled “Accelerating Breakthroughs to Address Unmet Needs in Type 1 Diabetes.” This meeting, a significant coming-together of Breakthrough T1D and European policymakers, focused on the role of the EU in addressing the needs of the T1D community and accelerating T1D breakthroughs.
The purpose of this meeting was to raise awareness of T1D and the urgent need for the accelerated development and approval of breakthrough therapies in the EU. Conversations between Breakthrough T1D and European policymakers homed in on barriers and opportunities to advancing cures—including cell therapies and disease-modifying therapies—in the EU to get them into the hands of people with T1D, faster. This was an important step in establishing an open dialogue between Breakthrough T1D and the EU Institutions about working together to address T1D globally.
“This event in the EU Parliament allows us to engage with important decision-makers to ensure that the research and policy environments are oriented in a way to accelerate development of T1D breakthrough therapies in the EU as we also do in other countries,” explained Campbell Hutton, Senior Vice President of Global Advocacy at Breakthrough T1D.
Attendees
Several Breakthrough T1D leadership and staff members attended the meeting, including Thomas Danne, M.D., Ph.D., Chief Medical Officer, Global; Sanjoy Dutta, Ph.D., Chief Scientific Officer; Lynn Starr, Chief Global Advocacy Officer, Carmen Hurtado del Pozo, Director, European Research; and Campbell Hutton, Senior Vice President of Global Advocacy.
Several Members of the European Parliament (MEP) in addition to host Tomislav Sokol, Ph.D., were in attendance. Other attendees included people with a lived experience of T1D, health staff from EU Member States, researchers in the EU, and other European diabetes organizations.
Dr. Dutta delivered a talk on the role of breakthrough therapies in transforming T1D. Dr. Danne moderated a panel to provide insight about unlocking the potential of cell therapies breakthroughs in the EU with T1D cell therapy researchers: Professor Lorenzo Piemonti, M.D., Director of the Diabetes Research Institute at Vita-Salute San Raffaele University and Associate Professor Francoise Carlotti, Ph.D., Head of the Islet Research Lab at Leiden University Medical Center. Finally, Lynn Starr closed with remarks about our shared global responsibility to work toward breakthrough T1D therapies.
Breakthrough T1D leadership and staff who attended the meeting.
When and where it took place
The event took place on June 5, 2025, in Brussels, Belgium, at the European Parliament.
Driving toward T1D cures in the EU and beyond
T1D is on the rise around the world, including in Europe. Recent publications by Breakthrough T1D staff and leadership brought attention to the rise in incidence and global T1D burden. We need to act now in conjunction with governments around the world—like the EU—to address the unmet needs of everyone around the world affected by T1D.
T1D cures, including cell therapies, are advancing through the clinical pipeline. Bringing awareness of T1D to the forefront—and educating key people on the progress we’re making toward cures—will be incredibly important for driving T1D research forward in the EU. This represents a critical opportunity for the EU to accelerate cell therapies faster than ever. As a global organization, Breakthrough T1D is collaborating with the EU government to help make this possible.
As the largest global funder of T1D research, Breakthrough T1D has provided funding to researchers across the world in addition to the EU. Right now, Breakthrough T1D is supporting €56 million in European initiatives, including 31 clinical trials—representing 19% of our funded research (including the U.K.). Breakthrough T1D has expert teams in research, medical, regulatory, and advocacy in Europe, meaning we are uniquely positioned to provide guidance on how the EU can strengthen its T1D efforts and collaborate on a global scale to drive T1D breakthroughs, especially in cell therapies.
Type 1 diabetes is a critical disease in Europe, and I was pleased to host an event for the T1D community and my colleagues in the European Parliament to learn about the unmet needs in T1D and how we can work together to accelerate breakthrough therapies in Europe to address those needs.”
Tomislav Sokol, Ph.D.Member of the European Parliament
What Breakthrough T1D leadership is saying
“This meeting is critically important to bringing the unmet needs of the T1D community into the spotlight in the EU. Global advocacy for curative T1D research is essential to achieving Breakthrough T1D’s mission, and continued collaboration with EU policymakers will get us there faster.”
Lynn Starr
Chief Global Advocacy Officer
“International efforts to accelerate global adoption of T1D cures will become increasingly important as newer, emerging cell therapies become available to people with T1D. Conversations like these with EU policymakers is bringing this urgent need to the forefront.”
Thomas Danne, M.D., Ph.D.
Chief Medical Officer, Global
“Cell therapies are accelerating through the clinical pipeline faster than ever. We need to act now on a global scale to ensure that people with T1D around the world can access these transformative therapies. This meeting is a significant step toward that goal.”
Sanjoy Dutta, Ph.D.
Chief Scientific Officer
Accelerating global action is paramount to our mission
Global problems require global solutions. This meeting served as a critical launching point for a continued partnership with the EU to fill gaps and address unmet needs for the T1D community. Building relationships and fostering long-term partnerships is critically important for reaching our common goal of bringing cures to people with T1D as soon as possible.
These important conversations between Breakthrough T1D and the EU government align with our Project ACT (Accelerate Cell Therapies) initiative to accelerate the development of cell therapies that do not require immunosuppression—for everyone with T1D in every country. In addition, through international Centers of Reference, Breakthrough T1D’s Medical Affairs team is developing expert clinical care centers that will be trained and ready to provide cell therapies to people with T1D once they become available. We are at the forefront of global action to prepare the world for curative cell therapies.
Project ACT
Scientific progress takes time, money, and effort. To accelerate islet replacement therapies faster than ever, Breakthrough T1D launched Project ACT (Accelerate Cell Therapies) to simultaneously advance research, development, regulatory policies, access, and adoption of manufactured islet therapies that do not require broad immunosuppression.
We are driving toward a future in which everyone with T1D—no matter where they are—has access to therapies, treatments, and care, bringing us closer to achieving our mission of a world without T1D. The more people we have working toward our mission, the faster we will get there.
Breakthrough T1D’s newest mission pillar, Medical Affairs, is bridging the gap between access to and adoption of T1D therapies. The establishment of this program is essential to Project ACT (Accelerate Cell Therapies): Breakthrough T1D’s initiative to accelerate the development of manufactured islet cell replacement therapies that do not require immunosuppression. The goal is to make sure that people with type 1 diabetes (T1D) can get these therapies as soon as they hit the market.
The field is moving quickly: people are becoming insulin-independent in cell therapy clinical trials. We are advancing towards the submission of the first-generation manufactured islet cell therapy that requires immunosuppression, Vertex’s zimislecel (VX-880). We are at a critical moment and need to act now to ensure that healthcare providers (HCPs) are ready to bring manufactured islet cell therapies into clinical settings.
Enter Medical Affairs
This is where Medical Affairs comes in. The team, led by Thomas Danne, M.D., Chief Medical Officer International, is working with the medical community to anticipate obstacles to getting manufactured islet therapies into clinics and find ways to overcome them now.
To accomplish this, Breakthrough T1D recently hosted two cell therapy workshops, convening multidisciplinary, international experts in islet cell transplantation to discuss a clinical roadmap for manufactured islet cell therapies—and how to ensure that clinical teams are in place and prepared to provide these therapies to people with T1D who qualify. By preparing now, we can get this first-generation therapy into the hands of people with T1D as soon as possible after regulatory approval.
The cell therapy workshops were hosted by Breakthrough T1D’s Thomas Danne, M.D., Chief Medical Officer International, and Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES, Vice President of Medical Affairs.
Read on to learn more about the cell therapy workshops, the attendees, and what each accomplished.
Workshop #1: Who may benefit most from manufactured cell replacement therapies
Key Takeaways
T1D leaders are working on a five-year roadmap for the clinical adoption of manufactured islet cell therapies.
It will include key criteria and evidence to help clinicians determine who is the best fit for manufactured islet cell therapies.
The guidelines are prioritizing shared decisions between people with T1D and their care team to optimize outcomes and maximize long-term health.
Attendees
The first of the cell therapy workshops, held in late April, convened transplant surgeons, T1D clinicians and researchers, a member of Vertex’s leadership team, a member of Breakthrough T1D’s Participant Advisory Council to represent people with a lived experience of T1D, and Breakthrough T1D Vice President of Research Esther Latres, Ph.D.
The purpose of this workshop was to start developing a five-year roadmap to help guide the T1D care community to support the adoption of manufactured islet cell therapies in clinical care. The evidence-based recommendations will be vetted by a larger group of clinical experts, diabetes organizations, and people with lived experience with T1D to ensure there is broad agreement. The consensus document will ultimately be published to expand its reach.
This process will summarize the essential evidence that will help HCPs decide who may benefit the most from manufactured islet cell replacement therapies. These decisions will take into account the perspective of people with T1D and differences in age, hypoglycemia unawareness, or kidney health, to name a few. This can help HCPs better understand the benefits versus risks for manufactured cell therapies on a person-by-person basis—making sure that each clinical decision is made jointly to prioritize long-term health.
Workshop #2: Pilot workshop to develop international Centers of Reference for T1D cell therapy
Key Takeaways
Centers of Reference are expert T1D care centers that are preparing to bring manufactured islet cell therapies to the T1D community.
This workshop was the first step to understanding what kind of education, training, and resources are needed for Centers of Reference to be effective.
Attendees discussed how to make sure people T1D who receive manufactured cell therapies at Centers of Reference will have the best clinical experience possible.
Attendees
The second cell therapy workshop, held in early May, convened clinicians from various global medical institutions, including University of Minnesota Medical Center, University of Wisconsin Health Transplant Center, the Penn Rodebaugh Diabetes Center, University of Chicago Medicine, IRCCS Ospedale San Raffaele (Italy), Institute of Transplantation, Newcastle upon Tyne (United Kingdom), and University of Alberta (Edmonton, Alberta, Canada).
Additional attendees from Breakthrough T1D included CEO Aaron Kowalski, Ph.D., Vice President of Research Esther Latres, Ph.D., the Medical Affairs team, a volunteer, and a member of the Participant Advisory Council, who is a person living with T1D.
The objective of this workshop was to take the first step toward creating Centers of Reference for T1D manufactured cell therapies. “The initial purpose is to accelerate readiness of healthcare professionals to deliver manufactured islet cell therapies once they become available,” explained Dr. Danne. “…making such a treatment a success needs teamwork. Accredited Centers of Reference will not only deliver advanced T1D treatments but also serve as a training hub for professionals aspiring to become experts.”
This workshop focused on better understanding what potential Centers of Reference need to be successful. The attendees covered a range of topics: what an ideal T1D care team might look like, the education and training required for experts in T1D manufactured islet cell therapy, and career development for early-stage T1D professionals.
The goal is to prepare expert clinicians—who are already doing islet cell transplants—to bring manufactured islet cell therapies into clinical practice at their institutions and others, once they have regulatory approval. These centers will serve as a benchmark for best practices in T1D manufactured cell therapy, establishing a network of expert teams to make sure that everyone who can benefit from manufactured cell replacement therapy is given the opportunity to consider it.
What the experts are saying
“We need to build consensus and teamwork. When manufactured cell therapies exist, it’s going to take significant coordination between endocrinologists, transplant surgeons, and people with T1D to ensure as many people as possible are benefiting from these therapies.”
“We’re trying to solve access and awareness. There’s a definite gap between primary care endocrine diabetes specialists and transplant specialists…there’s so much more that we have to fill in for [people with T1D].”
Helen Nelson, BSN, RN, CCTC, CPTC
Program Manager, Organ Allocation/Clinical Triage and Pancreas Transplant Program at University of Wisconsin Health Transplant Center
“It’s going to be a significant problem if we have a cure but no one has access to it because no one can deliver it. We must work together—transplant surgeons, endocrinologists, researchers, everyone. It’s like building Cape Canaveral in anticipation of sending rockets into space.”
Peter Senior, MBBS, Ph.D.
Islet Transplant Endocrinologist, Professor in the Department of Medicine, and Director of the Alberta Diabetes Research Institute at the University of Alberta, Canada
“There is amazing excitement around creating cell therapies. People are excited about it. We must ensure that organizations like Breakthrough T1D bridge the gap between research and the T1D population so that there is no difference between an individual’s reality and what therapies are available.”
James Shaw, M.D., Ph.D.
Transplant Endocrinologist and Professor of Regenerative Medicine for Diabetes at the Institute of Transplantation, Newcastle upon Tyne, United Kingdom
This is just the beginning
Manufactured islet cell therapies are coming. We need teamwork to get these therapies into clinics so people with T1D don’t have to wait years to get them. This is why Breakthrough T1D is acting now: when the first manufactured islet cell therapy hits the market, multidisciplinary care teams around the world will be ready. These workshops—the first of many—will help accelerate the safe and effective integration of manufactured islet cell therapies into clinics.
“This way we will ensure that the medical community is ready to deliver manufactured cell therapies once they become more widely available.,” Dr. Danne said. Thanks to the hard work of the Medical Affairs team at Breakthrough T1D, this goal is in sight.
Breakthrough T1D strives to accelerate life-changing breakthroughs to cure, prevent, and better treat type 1 diabetes (T1D) and its complications. To accomplish these goals, we use a multi-pronged strategic approach, including conducting scientific studies and educating our community. In line with these goals, Breakthrough T1D recently published two peer-reviewed journal articles. One detailed burdensome unmet needs in the T1D community and identified key steps we can take to meet these needs. The other used real-world data to better understand American T1D demographics and predict changes in the next decade.
Let’s take a deeper dive into each.
Unmet needs of the T1D community: More work is needed
Despite major progress in T1D management, T1D still results in premature death, complications, and very significant daily burden.
Daily insulin use is a persistent challenge that comes with physical, emotional, social, and economic burdens.
New therapies and cures that can reduce or eliminate the challenges of living with T1D are closer than ever.
The entire T1D community (researchers, sponsors, clinicians, advocates, people with T1D, regulators) needs to work together to overcome scientific, drug development, and regulatory challenges to make cures for T1D a reality.
This commentary reviews previously existing data across the T1D care spectrum to help demonstrate the magnitude and significance of the unmet needs faced by people living with T1D. This information is used to emphasize the urgency researchers, sponsors, and regulators must place on developing cures for T1D. The authors provide recommendations and actionable steps to overcome scientific, clinical, and regulatory challenges that will help meet these needs.
Daily life with T1D is still a challenge
To say that the daily routine of people living with T1D is hard would be an understatement.
Insulin injections and dosage calculations. Wearable tech maintenance. Carbohydrate counting. Mealtime and exercise tracking. Doctor’s appointments. Hypoglycemia, hyperglycemia, and diabetic ketoacidosis (DKA) avoidance. It requires constant attention: 24 hours a day, 7 days a week.
The truth of the matter is that T1D management is a burdensome, demanding, and highly intensive task. There are no breaks, vacations, or time off—even overnight, it requires management. These challenges remain, even with today’s advancements in technology and the emergence of novel therapies for T1D. Simply put, we need to do more for the T1D community, and we cannot settle for the status quo.
The bigger picture
The global burden of T1D
11
The average number of years of life lost for people with T1D globally.
21%
The percent decrease in mortality rate for people with T1D in the last 30 years globally, which is not distributed equally among everyone with T1D.
The challenge of day-to-day T1D management compounds into long-term negative outcomes for the T1D population. Despite improvements in mortality rate, the life expectancy of people with T1D is still shorter than those without T1D.
Keeping blood glucose in a normal range is extremely difficult, and people with T1D need to be acutely aware of their insulin doses to prevent highs (hyperglycemia) and lows (hypoglycemia). Prolonged hyperglycemia leads to heart, kidney, and eye damage. Hypoglycemia can be very dangerous and a source of distress and anxiety, especially if it occurs often and eventually without symptoms (termed “hypoglycemia unawareness”).
The impact of hypoglycemia
25-40%
Percent of people with T1D who experience hypoglycemia unawareness.
30%
Percent of adults with T1D who have a fear of hypoglycemia.
Current technologies cannot solve the problem of hypoglycemia or make people with T1D have perfect blood sugar levels. As a whole, these challenges represent a profound emotional and mental burden for people with T1D, often leading to diabetes distress and burnout—which itself can lead to worse glycemic control. People with T1D have a tougher time managing the ins and outs of daily life because of the extreme mental and physical load of having T1D.
A longer life on its own is not the goal: it’s longer lives without ever having to think about T1D.
Breakthrough T1D’s vision for the future…
Breakthrough T1D envisions a world where the burden of T1D no longer exists. A world where people don’t have to manage their diabetes—they don’t take insulin, don’t have blood sugar highs and lows, and don’t develop complications. Curing T1D is our north star.
…and how to make it a reality
To achieve these goals, we need widespread screening, innovative research and therapies, patient-centered clinical approaches, and evolved regulatory pathways. We need to adjust the T1D paradigm and move clinical testing along at a quicker pace.
The regulatory route for new therapies determines whether companies, which have the greatest ability perform research in a quick and efficient manner, will invest their time and money into innovative T1D therapies. They are more encouraged to do so if they see defined and reasonable pathways for new therapies to reach the market—especially if healthcare systems are in place that will allow these therapies to be adopted by healthcare professionals and used by the people who need them most.
It starts with the decision-makers, who weigh the benefits versus risks of a new therapy. These decisions need to have more input from people who have a lived experience with T1D and can better decide if the benefits outweigh the risks, especially given the tremendous daily burden of living it. Clinical testing should broaden to include more populations of people with T1D—not just those who have severe disease—because nearly everyone has the chance to benefit. As the authors state in the commentary:
The magnitude of benefits required to outweigh a product’s risks should be determined by people living with T1D and no one else.
To further optimize T1D clinical trials, Breakthrough T1D and other experts have pushed for the validation of C-peptide, a biomarker for the body’s insulin production, as a clinical trial endpoint. Compared to the currently used endpoints, C-peptide would provide easier assessments and shorter clinical timeframes, thereby making the process of T1D therapy development more streamlined—and bringing these data to decision-makers sooner.
Once better clinical endpoints are validated, more personal experiences are incorporated into clinical trials, and the regulatory path to market is clear, companies will be encouraged to invest in T1D research programs, thereby speeding up research, innovation, and progress along the clinical pipeline—getting life-changing therapies into the hands people with T1D faster than ever.
What comes next?
This publication will be shared broadly with regulators, legislators, payers, and the T1D research community to encourage research, innovation, and funding and advocate for quicker, more efficient clinical testing and regulatory pathways to approval.
I think the misperception that the therapies available today are good enough is one of the most insidious challenges to ushering in the era of T1D cures…Today’s therapies do not offer the freedom from diabetes that people living with the disease want…I believe when we fully appreciate the daily experiences of people living with T1D, and when we use these experiences to guide our research development and regulatory decisions, we will also then have clear pathways for new therapies that meet these needs.”
Stephen Karpen, PharmDSenior Director of Regulatory Affairs at Breakthrough T1D
This is a call to action for everyone working in the T1D space. The overarching purpose is to foster awareness of these unmet needs and the urgency with which we must act as a community to address them—by working together and collaborating across the pipeline of T1D management.
Read on to learn more about the population of people living with T1D with these unmet needs.
Nearly 47% of Americans with T1D are enrolled in commercial health insurance followed by nearly 30% in Medicare, and 15% in Medicaid.
People with T1D who use diabetes devices have lower mortality rates than those who do not.
Most Americans living with T1D today are Non-Hispanic White people.
In the next 10 years, the Hispanic and African American populations with T1D are expected to grow the most, and the average age will increase from 47 to 49 years old.
The purpose of this study was to identify key T1D demographics in the United States and predict how these demographics will change over the next decade. Using healthcare insurance claim datasets, population growth projections, and existing literature, the authors modeled T1D demographic changes between 2024 and 2033.
This study was funded by Breakthrough T1D in collaboration with the T1D Index team so that these data can be incorporated into the Index. (Disclaimer: the T1D index uses multiple datasets and publications to predict the number of people living with T1D, which may explain discrepancies in Index estimates and predictions from this study).
Incidence
The number of new T1D diagnoses in a given time period.
Prevalence
The total number of people with T1D (new and existing diagnoses) in a given time period.
T1D stats: Now
2.07 million
Number of people in the U.S. living with T1D.
47
Average age of people living with T1D.
67%
Percent of people with T1D who are 20–64 years old.
19%
Percent of people with T1D who are over 65 years old.
47%
Percent of people with T1D who have commercial health insurance plans. Other coverage includes Medicare (30%) and Medicaid (15%).
T1D stats: 10 years from now
2.29 million
Number of people in the U.S. living with T1D (due to increase in T1D incidence and improved survival from devices).
49
Average age of people living with T1D.
33%
Percent increase in T1D population that aged 65 and older (mostly due to aging of the current T1D population).
38%
Percent increase in T1D population that is aged 10 and younger.
44%
Percent of people with T1D who have private/commercial health insurance plans. Other coverage includes Medicare (30%) and Medicaid (17.4%).
30%
Percent increase in T1D population who will use Medicaid.
What comes next?
Despite significant advances in T1D technology, therapies, and care management, the T1D population still faces a greater risk of complications and a higher mortality rate. Breakthrough T1D leadership will use key information from this study to inform future strategic research and advocacy efforts.
This data gives us an opportunity to quantify key information about our community to inform decision-makers…With better data specific to those with T1D, we can ensure that we’re advocating for solutions that not only expand access but also promote a better health care system for those with T1D.”
Lynn StarrChief Global Advocacy Officer at Breakthrough T1D
These data will help inform elected officials and payers about how healthcare policies may ultimately affect the T1D community—ensuring that the policies in place are having the greatest impact they can. The next phase of the project will analyze key demographic information in the context of access to cell therapies.
The ultimate goal is to ensure that everyone with T1D has access to the therapies, technology, and care that works best for them. By understanding T1D population demographics, Breakthrough T1D can make the most informed decisions possible as we move toward our goal of a world without T1D. We call on regulators, legislators, payers, and T1D researchers to take urgent action to meet the unmet needs of the T1D community now and in the future.
This May, Matt Varey, a key volunteer with Breakthrough T1D since 2001, will embark on an ambitious two-month-long, 7,500-kilometer cycling journey across Canada.
As Matt rides Coast-to-Coast for Cures in support of Breakthrough T1D, his goal is that his passion and drive will inspire people to give generously to make each day better for those living with type 1 diabetes (T1D) while driving toward cures.
Matt sat down with Breakthrough T1D Canada to share more about his motivations behind taking on such an ambitious fundraiser and why supporting the T1D community is so important to him.
You’ve been involved with Breakthrough T1D as a volunteer and board member for over 20 years. How did you first get connected with the organization?
Matt Varey: My relationship with Breakthrough T1D (then JDRF) started in 2001. My job at the Royal Bank of Canada (RBC) transferred me to Toronto. At that time, we were asked to build a new Canadian business within the bank, and it entailed me and other leaders going across Canada and speaking to employees very passionately and credibly about what they were going to help build.
Banking is a human business based on trust. I had to get out of my introverted shell and talk to employees, so I would ask them, “Who are you as a person? I want to get to know you as a human beyond just work.” I had no idea what Breakthrough T1D (then JDRF) was at the time. And you’d hear from people about their kids or sports, but one or two people would get teary or speak with a crack in their voice. So, naturally, I would probe a bit and ask more, and they would tell me about their family member and their journey with T1D.
So, when I got back from this Canada-wide work trip, I learned about the Breakthrough T1D “battle of the banks” Ride and thought to myself, “Wow, I have to do this.” That spring, I was part of the RBC Ride team. I saw all these people raising money for T1D research, and I made this connection to the people I met along that work trip affected by T1D, and I got the bug. My mother always said, “What’s given is yours forever,” and I knew I had a new purposeful journey with Breakthrough T1D.
It all flowed from there. I became the chair of the RBC Ride Cabinet and then the National Cabinet Chair. I saw the power of progress; I saw the dedication and the passion of people. I said, “I can’t stop at the Ride.” And then I met a fabulous mentor, one of the most important people in my life, Peter Oliver.
Peter was one of the founding fundraisers of what was then JDRF Canada because of his daughter Vanessa, who lives with T1D. He was such a giving person, and he taught me things I will never forget about giving back. He told me, “Always think big, never take no for an answer.”
Peter was the definition of a mentor, about what Breakthrough T1D stood for and the people who worked there. And he knew that he had this young guy named Matt who would follow anything he asked. I’ve been a Board Member, Vice Chair, and Chair of Breakthrough T1D Canada, and I’ve never felt a culture of giving, togetherness, and dedication like I do from the people at this organization. This led me to being a board member of Breakthrough T1D International (headquartered in the United States), and now I am currently the Vice-Chair of Breakthrough T1D International.
This journey can be credited in so many ways to Peter, who was, is, and always will be my north star.
I’ve never felt a culture of giving, togetherness, and dedication like I do from the people at this organization.”
How did you devise the idea for Coast to Coast for Cures?
Matt Varey: As I retired in the summer of 2024, I thought about something my mum always taught me: “Never stop moving and never let the old man in.” So, with mentors like my mum telling me to “keep moving” and Peter Oliver saying, “Make sure it’s big, make sure it stands out, and make sure it challenges you,” I came up with the idea for the event.
Riding across Canada for 57 days and 7,500 km coast to coast for a cause is doing something different, and honestly, it scares me, which is good. I also love Canada so much, so that’s part of my journey, too. And I knew RBC would always have my back. As a mission, values-based organization, they told me in my retirement that if I ever did anything for Breakthrough T1D, they would be involved and support me 100%.
I want to challenge myself and hold true to my mum and Peter. My wife said she would take two months off work, bring the dog, and drive behind me. My wife is my everything, and I could never do this without her.
And one evening I made a public proclamation that I was going to do this, and then there was no turning back.
The world is changed by your actions, not by your words.”
What are you most excited about for the ride, both personally and for raising awareness of Breakthrough T1D and type 1 diabetes?
Matt Varey: The world is changed by your actions, not by your words. Human beings, deep inside, want to see people accomplish something that is hard but shows dedication. I think that it attracts human beings to be generous. If we’re going to be asking people to help us raise half a million dollars, they want to see your skin in the game.
I’m excited about seeing the generosity of people. I’m an optimist; I always believe tomorrow is going to be better than today. I’m excited to see Canada for two months with my wife and see my former RBC colleagues, whom I miss dearly.
Do you have a message for the Breakthrough T1D community?
Matt Varey: We will never ever stop moving forward for cures. Ever. And I am just one of thousands and thousands of incredibly dedicated volunteers who also wake up every day and say the same thing, with even more credibility than myself.
As Mary Tyler Moore, who lived with T1D herself, would say, “You can’t be brave if you’ve only had easy things happen to you.” And people who live with T1D are brave every day. So please know that my commitment to you is also to be brave. And we will never ever stop until we get to a world free from type 1 diabetes.
Visiting our site from Canada? Please click here to support Matt.
Editor’s note: This interview is an abbreviated version of one previously published by Breakthrough T1D Canada. Read the full interview here.
After months of unexplainable symptoms, Katie Howell was diagnosed with type 1 diabetes (T1D) last year at age 25. Read on to learn more about how she confronted her new reality and became the first participant in New York City to enroll in the DIAGNODE-3 clinical trial.
The unexpected diagnosis
Katie hangin’ out in NYC.
Katie Howell, a Mississippian-turned-New Yorker, has a wide array of hobbies: crafting pottery at her local ceramics studio, enjoying old movies in the theater, cozying up with a book in Prospect Park, and taking in the sun at Rockaway Beach. Katie moved to Brooklyn after completing a Master of Public Administration degree at the University of Tennessee, Chattanooga, and she’s thoroughly enjoying getting to know her new neighborhood.
Suddenly, things took a turn. Last year, Katie started experiencing symptoms of something unknown—for three months, she had no idea what was going on with her body. Then, in a moment of complete shock, 25-year-old Katie was diagnosed with type 1 diabetes (T1D). “Without a family history of T1D and without any health issues of my own, being diagnosed with a sudden, serious chronic illness could not have been more unexpected,” Katie explained.
At the time of her diagnosis, Katie was confronted with a flood of emotions. There was not a single person in her life that had T1D or could understand her experience. “…one of the most challenging parts of being diagnosed with a chronic illness is accepting it […]. This comes with a lot of hopeless feelings, and it is tough to surrender control to an incurable, pervasive, and expensive health condition,” Katie lamented.
Feeling alone and lost, she had no choice but to accept that she was dealing with a major life change—whatever that meant for the future.
Influenced
It wasn’t long before Katie took to social media to learn more about her diagnosis and connect with the T1D community. On Instagram, she stumbled upon Lauren Bongiorno, a T1D influencer. Ms. Bongiorno posted a video promoting DIAGNODE-3, a phase 3 clinical trial for the disease-modifying therapy Diamyd® for early-stage T1D.
Check out Lauren on Instagram: @lauren_bongiorno
Katie found that DIAGNODE-3 was enrolling at The Pediatric Diabetes Center at Hassenfeld Children’s Hospital at NYU Langone. After reaching out to the team at NYU, she realized that the stars had aligned: they had just opened enrollment, and after completing the necessary screening, Katie would be Participant Number One.
“It gets easier every visit!”
Katie received her first study injection in January and will get her third and final injection this month, followed by routine check-ins. This includes blood work, physical exams, and mixed-meal tolerance tests to measure her body’s ability to produce insulin.
As per the study protocol, Katie doesn’t know if she’s receiving the placebo or the study drug, Diamyd®. Still, she likes being in the study: she’s made meaningful connections with the trial team, has learned a lot about T1D, and feels that she’s making a difference—not just for herself, but also for biomedical research.
Katie’s biggest hurdles? Bloodwork and hospitals. “One challenge of this study is the routine blood work and being treated at the hospital. However, it does feel like exposure therapy. It gets easier every visit!” she exclaimed.
Finding her community
Since her diagnosis, Katie has made lasting relationships with others in the T1D community. She connected with the Greater New York Metro Chapter of Breakthrough T1D after volunteering at a Walk in NYC last fall. They introduced her to a group chat with other newly diagnosed young women, where they can ask questions, network, and learn from each other as they navigate their new realities.
“My advice to someone considering [the DIAGNODE-3] trial would be that, though the study is a commitment and an undertaking, they are taking part in discovering medical breakthroughs and T1D treatment research.”
Katie Howell
Participate in clinical trials
Clinical trials are key to bringing medical advancements from the lab to the clinic. This wouldn’t be possible without brave people with T1D, like Katie, who volunteer to participate. These studies offer the potential for life-changing treatment and move the ball forward for the T1D community.
From March 19-22, the world’s leading type 1 diabetes (T1D) researchers—including Breakthrough T1D staff, funded researchers, and partners—gathered in Amsterdam, the Netherlands, for the 2025 Advanced Technologies and Treatments in Diabetes (ATTD) conference. There were dozens of presentations, symposiums, panels and more over the course of the conference, providing a snapshot of the current state of T1D research, management, treatment, and, most importantly, progress towards cures.
Here are a few of the highlights.
Cell therapies
Cell therapies, which place insulin-producing cells into people living with T1D, are a priority of Breakthrough T1D for a simple reason: they have the potential to cure T1D. ATTD covered where cell therapies are on their path toward becoming a reality.
Breakthrough T1D Vice President of Research, Esther Latres, Ph.D., chaired a session on beta cell therapies for T1D. In this session, several researchers funded by Breakthrough T1D, including Andrew Stewart, M.D. (Mount Sinai Icahn School of Medicine), Cristina Nostro, Ph.D. (University of Toronto), Matthias Hebrok, Ph.D. (Helmholtz Munich), and Anath Shalev, M.D. (University of Alabama at Birmingham), discussed their work and the different tactics each are taking.
For example, Dr. Stewart and Dr. Shalev are working on cell survival and regeneration towards identifying ways to protect and prevent the loss of the body’s own beta cells —whereas Dr. Hebrok and Dr. Nostro are working on adapting the immune system to accept and not reject manufactured islet cells after transplantation. Dr. Hebrok is using an elegant approach based on generating chimeric antigen receptor (CAR) T cells to create a localized immune-suppressive environment.
This session highlighted the multiple-shots-on-goal approach required to address the challenge of protecting beta cells from immune-mediated destruction, whether the islet cells are the body’s own that remain at early stages of the disease or are the manufactured islet cells transplanted at later stages.
The speakers at Vertex’s industry symposium emphasized the same key point: the burden of T1D is too high, even with current therapies. Cell therapies can transform how this disease is managed—but they need to be minimally invasive and scalable. (If that sounds familiar, it’s because that’s what Breakthrough T1D is working to create through Project ACT.)
Key Takeaways
The data we have from clinical trials in cell therapies are the case in point for why Breakthrough T1D is prioritizing their development. However, there is still a long way to go before there is a renewable source of manufactured islets. The good news is that there is a lot of momentum around cell therapies, thanks to companies like Vertex, Breakthrough T1D’s Project ACT, and numerous scientists and researchers pushing us closer to our goal.
Using personal experiences to measure the benefits of cell therapies
It is important to understand how a medication, device, or therapeutic procedure (i.e., islet cell transplant) affects the lived experiences of a person. To do this, medical professionals use Person-Reported Outcome and Experience Measures (PROMs and PREMs) to understand how a new therapy influences a person’s day-to-day experience. These assessments generally inquire about how a person with T1D receiving a new therapy feels (stress, anxiety, overall mood), their diabetes management (time spent thinking about or making decisions about the disease), their use of the treatment or device (convenience, effectiveness, intrusiveness), and their overall quality of life (sleep, family life, work, finances, etc.).
Led by Breakthrough T1D Vice President of Research, Esther Latres, Ph.D., and co-organizers from the Breakthrough T1D Advocacy and Medical Affairs teams, Breakthrough T1D organized a PROMs workshop in Cell Therapy to capture meaningful data on a person’s subjective outcomes and experiences. The participants had a diverse range of expertise across the spectrum of T1D management, including people with lived T1D experience and professional and clinical research backgrounds. The one-day workshop focused on identifying what matter most to people living with T1D to inform PROMs assessments. The goal is to ensure that emerging cell therapy treatments and technologies are valued for both improving glycemic outcomes and improving lives.
Key Takeaways
Understanding the lived experience of people with T1D who receive novel cell therapies will be critical to assess what kind of impact they are having on a personal level. People living with T1D and T1D professionals gathered to discuss which factors matter most to people with T1D so the medical community can ask the right questions to those who receive new therapies.
Improving lives
Until we have cures, we need better tools for the millions around the globe living with T1D to lead healthier, fuller lives. That’s the focus of Breakthrough T1D’s Improving Lives portfolio.
Breakthrough T1D Chief Scientific Officer, Sanjoy Dutta, Ph.D., chaired a session on fully closing the loop with automated insulin delivery (AID) systems. (This means systems that require no input from the user.) There are a number of strategies to work towards this, including dual-hormone pumps, DIY systems, and systems that use insulin alone.
Breakthrough T1D Research Director, Jonathan Rosen, Ph.D., moderated a session titled Futuristic Technologies to Improve Outcomes and Quality of Life in Type 1 Diabetes. This session featured some innovative device and drug-device combinations under development for T1D. This includes a miniaturized insulin pump, a CGM combined with a pump into one wearable device, infusion sets made with new materials to promote extended wear, and non-insulin glucose control therapies paired with AID systems to improve outcomes.
Breakthrough T1D Chief Medical Officer International, Thomas Danne, M.D., chaired a panel titled Time in Tight Range: A Crucial Goal or Unnecessary Burden?
Time in Tight Range, which is now referred to as Time in Normal Glycemia (TING), is defined as time spent in a narrower blood glucose range (70-140 mg/dl). To lower the risk of complications as much as possible, we need to help people with T1D get as close as they can to replicating the glycemic range of a person without T1D.
That’s a lofty goal—especially considering that today, with the tools we have, the majority are not spending enough time in a wider range (70-180 mg/dl). This shift towards TING will give people with T1D a better target to aim for and reinforce the notion that we need better tools.
Key Takeaways
AID systems are helping people with T1D achieve better outcomes, but we need more advanced tools to help people achieve tighter glycemic control. We are making progress towards fully closing the loop and utilizing new strategies, like additional drugs, to help people do better until there are cures.
Building consensus for continuous ketone monitoring
Developing continuous ketone monitoring (CKM) systems is one of the current priorities of Breakthrough T1D’s Improving Lives work. It’s important because diabetic ketoacidosis (DKA) remains a significant and dangerous risk for people with T1D. CKMs have the potential to prevent DKA by informing people when ketones are rising so they can take steps to mitigate it before it becomes a crisis.
Additionally, they have the potential to enable safe use of SGLT inhibitors, a class of drugs that has benefits for heart and kidney complications but comes with an increased risk of DKA.
Led by the Medical Affairs team and Chief Medical Officer International, Thomas Danne, M.D., Breakthrough T1D is spearheading the development of an international consensus guidance document around CKM.
These devices are coming, and the medical community needs to be prepared. They will be a first, and there are many things to work out before they’re ready. For example, when should CKMs alert the users? What actions should the users take when the alarms go off? How do we balance real-world use with clinical utility?
These guidelines—and the experts from around the world who attended the meeting—will cover that. Together, they’re working on a manuscript they expect to publish later in 2025.
Key Takeaways
CKMs have the potential to prevent DKA and may allow for the safe use of SGLT inhibitors. To enable safe and effective usage and adoption of CKMs, medical professionals are working together to publish consensus guidelines.
Earlydetection
In addition to chairing a panel titled Early Detection of Diabetes and Intervention Strategies to Prevent Complications, Breakthrough T1D Associate Vice President of Community Screening and Clinical Trial Education, Anastasia Albanese-O’Neill, Ph.D., also led a symposium that laid out Breakthrough T1D’ s vision for screening and early detection. This session outlined the many components that must be achieved to fully realize our vision of a world without T1D. For early detection of diabetes, that means that research must first provide evidence of the importance and benefits of screening—a task that has been achieved by all the Breakthrough T1D worldwide screening programs—and work closely with regulatory affairs, health policy, and medical affairs to move towards general population screening.
Key Takeaways
We know the benefits of screening and why it’s important to achieve cures. The next step is to increase awareness of these benefits so that more people get screened.
Up next: ADA
The next big meeting is the year’s largest: The American Diabetes Association Annual Scientific Sessions. This meeting will take place from June 20-23 in Chicago, Illinois—and we’ll be there to cover the latest and greatest.
Did you know that women make up only 28% of the science, engineering, technology, and mathematics (STEM) workforce?
While we have made some progress closing the gender gap in STEM professions in past decades, there is still more work to be done. To support this effort, it’s critically important that we take time to recognize the incredible contributions that women in science are making every day—and all the hard work they’ve done to get there.
This Women’s History Month, Breakthrough T1D is highlighting the accomplishments of Kelsey Voss, Ph.D., a recently appointed Assistant Professor at the University of Virginia (UVA) School of Medicine and a recipient of Breakthrough T1D’s Advanced Postdoctoral Fellowship Award.
Flipping the script
Kelsey and her pup, Chai.
Kelsey’s story begins the same way many other young women’s stories have: she was encouraged to pursue a subject other than science. Maybe something less “hard.”
After a less-than-perfect score on a math exam in high school, Kelsey was pushed toward Liberal Arts and away from courses like Chemistry. Her response? Push back even harder. “…I went all-in on biomedical research after that because that’s what I thought was the most interesting,” she recalled.
From then on, her path became clear. Kelsey majored in Biology at the University of Mary Washington and had her first encounter with the world of biomedical research. The next stop was George Mason University, where Kelsey volunteered in a lab studying host-pathogen interactions. She gained valuable experience in experimental techniques and journal publications, eventually transitioning to and completing a master’s degree there—each day becoming a better scientist.
From trainee to Principal Investigator
All the while, Kelsey knew she wanted to be a Principal Investigator (PI) one day, calling the shots in her own lab. She continued her training and pursued a Ph.D. at the Uniformed Services University, working under Andrew Snow, Ph.D., studying T cells. The lab environment was engaging, fun, and productive. But, research is hard—the graduate program was notoriously difficult, and Kelsey faced unexpected results in her studies. Despite these challenges, Kelsey thrived. “The challenge is to not let failure become tied to your self-worth,” she explained. This is a tough lesson that all scientists eventually come to bear.
She found a mentor in Dr. Snow.
“I saw how it could be possible to have this crazy hard career and still be in love with the science and enjoy it,” Kelsey said. He was a major influence in her decision to continue pursuing her dream of becoming a PI. “I knew from this experience that I wanted to have a lab like [his] one day and be the person who lifts others to their next phase of study, life, and career.”
To finish her training, Kelsey picked up and moved to Nashville, TN, for a postdoctoral fellowship at Vanderbilt University Medical Center. Working under Jeff Rathmell, Ph.D., she studied how targeting iron metabolism in T cells can change their behavior in autoimmune diseases like lupus. Kelsey herself struggles with autoimmune disease as well as some of her friends, so the work had personal meaning.
Calling the shots
During her fellowship, Kelsey applied for Breakthrough T1D’s Advanced Postdoctoral Fellowship Award—and got it—to translate her research in lupus to type 1 diabetes (T1D).
“This is what I really appreciate about [Breakthrough T1D]…new people and new ideas may be riskier but also have the power to make a big impact,” she fondly recalls of Breakthrough T1D’s willingness to take a gamble on her career. And it certainly paid off: Kelsey went on to start her own lab at UVA.
In her new position, Kelsey is building on her postdoctoral work and using both mouse models and human samples to better understand how T cell metabolism is dysregulated in autoimmunity—“a puzzle that never ends.”
Kelsey finds her work rewarding in many ways: she loves being creative and solving problems. “…one of the best feelings in the world is being the first person to see an experimental result in real time. For those moments, you are the only person alive who knows that information,” she explained.
Kelsey’s dream job includes leading the next generation of scientists—including the young women who were told that they should pursue something else but followed their hearts instead.
“Let them know their voices are valued.”
As much of life goes, Kelsey’s personal experiences as a woman in science “had its ups and downs.” A major motivator was seeing other strong women in science flourishing. One such scientist, Polly Matzinger, Ph.D., unapologetically offered a new paradigm of immunology (the “danger theory”) that was in direct contrast to the currently accepted view. To Kelsey, she is an inspiration—someone who can stand up for what she believes in and fight for it.
For women, this is easier said than done. Even in friendly and casual environments, it can be difficult for women in STEM and other fields to speak up and offer their points of view.
“What stands out to me…as a woman in science is how a lot of young women need time to develop the confidence to voice their opinions. They tend to withhold their questions or comments at conferences, journal clubs, or class discussions more often compared to men,” Kelsey explained. “I would encourage the community to allow space for girls to speak up in group settings and let them know their voices are valued.”
“I think we should change the way we think about research, specifically, as more of a creative pursuit that fits well with imaginative personalities. The next step would be to normalize and destigmatize the idea of ‘failure’ when young women start to experiment in these fields.”
Kelsey Voss, Ph.D.
Your privacy
We value your privacy. When you visit BreakthroughT1D.org (and our family of websites), we use cookies to process your personal data in order to customize content and improve your site experience, provide social media features, analyze our traffic, and personalize advertising. By choosing “I Agree”, you understand and agree to Breakthrough T1D's Privacy Policy