
Heart and kidney complications remain a major concern for people living with type 1 diabetes (T1D). While there are some therapies available to reduce the risk of these complications, the T1D community urgently needs more options. SGLT inhibitors (SGLTi), which have proven effective in people with type 2 diabetes (T2D) and people without diabetes, are a potential solution, but there have been several roadblocks in their development. To overcome these challenges and accelerate SGLTi for people with T1D, Breakthrough T1D spearheaded a publication laying out the path forward.
The Publication: A Roadmap for SGLTi
The publication, titled “SGLT Inhibitors for Heart and Kidney Disease in Type 1 Diabetes,” was published in Diabetes Care in September 2026. Jonathan Rosen, Ph.D., Senior Director of Research and lead of our Improving Lives program, led the charge with several Breakthrough T1D collaborators including experts in endocrinology, nephrology, and cardiology. The goal of this work is to give researchers a roadmap for advancing safe and effective use of SGLTi in the T1D population, including expected benefits and risks based on the data we have available, clinical trial design considerations, and diabetic ketoacidosis (DKA) risk mitigation strategies.
Key Takeaways
- People with T1D urgently need more heart and kidney therapies.
- SGLTi works in people with T2D and people without diabetes, and we expect people with T1D to experience similar heart and kidney benefits; however, these benefits have not been demonstrated yet.
- DKA is a real risk of SGLTi, but strategies to reduce this risk—including continuous ketone monitoring—have the potential to enable safer use of these therapies in the T1D population.
- Smart design of pivotal clinical trials for SGLTi will make them smaller, less expensive, and quicker without cutting corners on safety.
Heart and Kidney Complications: An Unsolved Problem in T1D
People living with T1D are at a heightened risk of developing both heart and kidney disease in their lifetimes. Chronic kidney disease (CKD) can progress to kidney failure, in which a transplant or dialysis is needed to survive. Kidney disease also amplifies the risk of heart disease, which includes heart failure, atherosclerotic cardiovascular disease, and more.
~30%
Estimated lifetime risk of developing CKD in people with T1D
18%
Prevalence of heart failure in people with T1D and CKD
1.5%
Prevalence of heart failure in people with T1D and no kidney disease
3-5x
Increased incidence rate of hospitalization and mortality from heart failure in people living with T1D compared to those without diabetes
While some therapies exist to help slow the progression of heart and kidney disease, there are simply not enough available—and no treatments exist to prevent them altogether.
What are SGLT Inhibitors?
SGLTi, or sodium-glucose cotransporter inhibitors, are a class of medications that block glucose transport in the kidneys. This allows for excretion of excess sugar through the urine, which ultimately lowers pressure inside the kidney’s filtration system. These drugs also ease strain on the heart.
SGLTi were originally developed for blood-sugar management in people with T1D, but they were not approved due to an increased risk for DKA (more on that later). Yet, SGLTi have shown tremendous benefits for heart and kidney protection in people with T2D and without diabetes, independent of their effects on lowering blood sugar. People with T1D were not included in these clinical trials, even though we expect similar benefits. That’s why Breakthrough T1D is taking the lead to advance SGLTi to treat heart and kidney disease in the T1D community.
What We Know about SGLTi from Clinical Trials
We have extensive data on the benefits of SGLTi in people with T2D and people without diabetes. In fact, these medications are the frontline therapy for treating heart failure and kidney disease. Based on an analysis of several clinical trials in these populations treated with SGLTi:
40%
Reduced risk of CKD onset or progression
~30%
Reduced risk of heart failure hospitalization or urgent visits
People with T1D have historically been excluded from larger SGLTi clinical trials studying heart and kidney benefits, which explains why we don’t have as much information on its effectiveness in T1D. Yet, we can extrapolate some of the expected benefits based on available data from smaller trials.
20-50%
Reduction in a marker of kidney damage (pooled data from several trials)
5-15%
Projected reductions in 5-year kidney failure risk and 10-year heart disease risk
Based on the proven heart and kidney benefits of SGLTi, researchers think that SGLTi will work in T1D, too. But we haven’t proven that yet. The bottom line is that we need more data around use of SGLTi in T1D—and thoughtfully designed clinical trials will help us achieve that sooner.
The Path to Approval: Surrogate Endpoints
For clinical trials looking at heart and kidney outcomes, traditional endpoints are often progression to kidney failure or death from heart or kidney complications. These endpoints are difficult to study, especially in T1D, because these trials require lots of participants and may take a very long time.
One solution: surrogate endpoints. These are biomarkers, or biological markers, that serve as a proxy for how an individual feels, functions, or survives and can be used in place of traditional endpoints in a clinical trial if they are recognized by regulatory agencies as clinically meaningful. One example is HbA1c, which can assess the risk of complications, or C-peptide, which is often used to assess whether disease-modifying therapies can preserve insulin-producing beta cells. There are also bridging biomarkers, which are endpoints that can be used to extrapolate the effectiveness of a treatment from one indication or population to another, like from T2D to T1D. Clinical trials in T1D that use these kinds of endpoints can often be smaller, less expensive, and quicker, while still providing critical information on safety.
Bridging Biomarker Example: Finerenone
Finerenone (brand name Kerendia) was recently approved for CKD in people with T1D. The endpoint of this clinical trial was urinary albumin-to-creatinine ratio (UACR), a measure of kidney damage that can be detected much sooner than traditional endpoints that clinical trials in CKD have relied upon. In studies testing finerenone in T2D, the improvements in UACR correlated with long-term kidney benefits. Based on this and the fact that finerenone was ultimately approved for people with T2D and CKD, the U.S. Food and Drug Administration (FDA) authorized use of UACR as a bridging biomarker to accelerate finerenone for T1D.
Because the benefits of SGLTi are already so well understood in other populations, large scale clinical trials with traditional endpoints may not be needed to establish their benefit in T1D, especially for kidney disease. In cases like this, bridging biomarkers can be a more strategic approach to clinical trial design that can accelerate SGLTi therapies for the T1D community.
Enabling Safe SGLTi Use with DKA Risk Mitigation
The major drawback of SGLTi use in T1D is that there is about a 3-fold increase in DKA risk. DKA is a life-threatening complication that occurs when the body doesn’t have enough insulin, leading to the breakdown of fat for energy instead of sugar and eventually ketone buildup in the blood. In people with T1D, SGLTi increases DKA risk partly because it reduces blood-sugar levels, which may lower insulin doses.
Ongoing SGLTi trials in T1D have protocols in place to monitor ketones and empower participants to act when levels start rising. Recently, the first continuous ketone monitor (CKM) for T1D was approved, and CKM has tremendous promise to be another tool that can help people with T1D safely achieve the benefits of SGLTi. Breakthrough T1D is funding several studies to uncover how CKM can most effectively reduce DKA risk, so we’ll continue amassing important safety data as SGLTi move through the clinical pipeline.
SGLTi Clinical Trials in T1D
| Clinical Trial | Identifier | Drug(s) | Population | Primary Endpoint |
|---|---|---|---|---|
| SUGARNSALT | NCT06217302 | Sotagliflozin | T1D and CKD | eGFR |
| SOPHIST | NCT06435156 | Sotagliflozin | T1D and heart failure | Heart failure symptoms |
| Steno 1 | NCT06082063 | Sotagliflozin, semaglutide, finerenone | T1D and high risk of heart disease | Incidence of cardiovascular events |
| PLUTO | NCT06147232 | Sotagliflozin | T1D and CKD | Kidney oxygenation |
The Future of SGLTi in T1D
Technically speaking, there have been no SGLTi approved specifically for use in T1D in the U.S. Yet, multiple SGLTi are approved for adults with heart failure or CKD with or without diabetes, and this does not exclude people with T1D—but clinical use remains low. More trials and more data are needed to aid in the clinical adoption of SGLTi in T1D, and decisions around SGLTi use ultimately lie with individuals and their care teams.
The phase 3 SUGARNSALT trial (which includes DKA risk mitigation) will provide critical evidence around the SGLTi sotagliflozin in people with T1D and CKD and, if favorable, could lead to consideration for regulatory approval. Going forward, thoughtfully designed clinical trials will help get the data needed for future regulatory decisions and clinical adoption of SGLTi. Along with current strategies to prevent DKA, continuous advancements in CKM promise to improve the benefit-to-risk ratio of SGLTi for people with T1D.
In collaboration with researchers, clinicians, regulators, and companies around the world, Breakthrough T1D will keep advancing safe, effective use of SGLTi so that people with T1D will have another tool for healthier hearts and kidneys—and longer, healthier lives.
Islet cell therapies for type 1 diabetes (T1D) are in the works. In clinical trials, people are coming off external insulin—and experiencing healthy blood sugar levels. Researchers and clinicians are working hard behind the scenes to advance next-generation manufactured islet cell therapies as scalable cures. The momentum is real—and it’s more important than ever to double down, bring all the key players together, and make them a reality.
First- Versus Next-Generation Islet Cell Therapies
First-generation islet cell therapies, including those in clinical trials today, are limited to people with severe hypoglycemic events and hypoglycemia unawareness. Next-generation islet cell therapies, including manufactured versions that can be made at large scale, will, ideally, be open to expanded populations. The future we’re working toward is one where everyone with T1D who wants an islet cell therapy can get one.
The Workshop: Bringing Together Key Voices
To keep the momentum going, Breakthrough T1D co-hosted a public workshop with the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) titled “Accelerating the Translation of Cell Therapy for Type 1 Diabetes.” This workshop convened researchers, clinicians, industry leaders, representatives from the U.S. Food and Drug Administration (FDA), individuals with T1D, and more to discuss best practices and recommendations for accelerating islet cell therapies for the T1D community as newer generations become available.
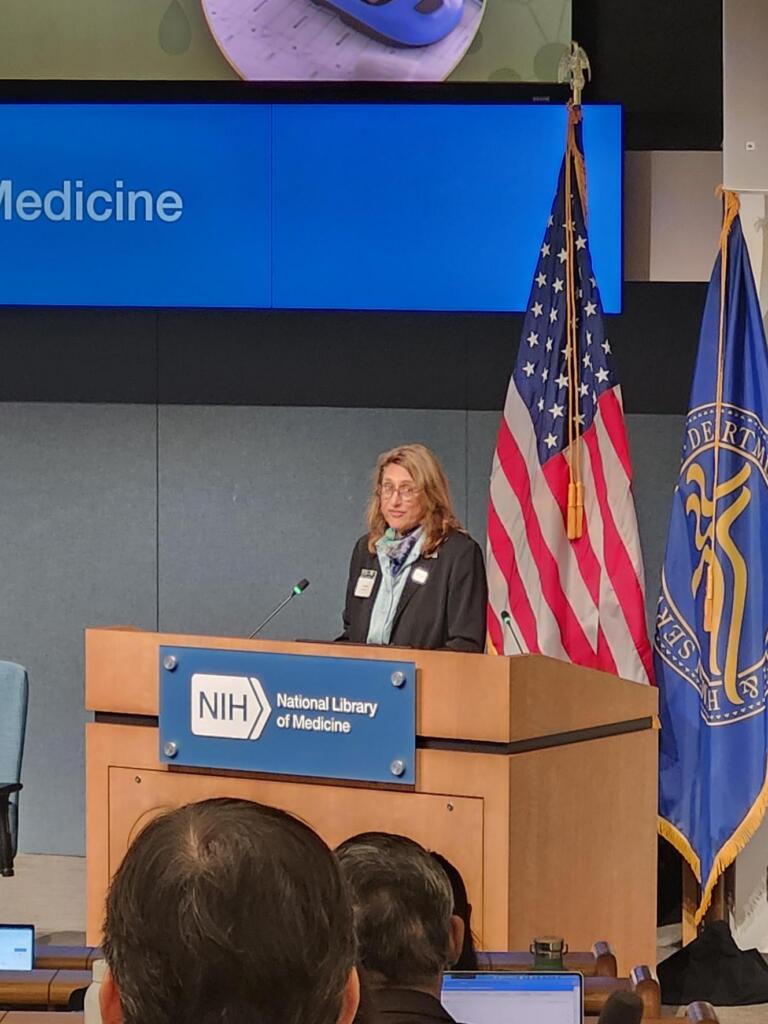

The planning committee included several Breakthrough T1D staff:
- Esther Latres, Ph.D. (Senior Vice President, Research)
- Nicholas Mamrak, Ph.D. (Senior Scientist, Research)
- Marjana Marinac, Pharm.D. (Associate Vice President, Regulatory Affairs)
- Chanel Press, Ph.D. (Director, Regulatory Affairs)
- Brianna Greeno (Senior Manager, Regulatory Affairs)
Key Takeaways
- Preclinical studies must be thoughtfully designed to ensure these novel islet cell therapies can be tested in human clinical trials.
- From the very beginning of their experiments, researchers must consider manufacturing requirements for nonclinical and clinical studies to effectively translate islet cell therapies to large scale.
- Real-life T1D experiences must be integrated into study designs and decision-making around next-generation islet cell therapies to ensure they create meaningful improvements to life with T1D and that the community is educated on them and is interested.
- Artificial intelligence (AI) is safely being applied to several different aspects of the islet cell therapy workflow, from forecasting responses to transplants, to optimizing manufacturing, to engineering cells.
The Conversation: Advancing Islet Cell Therapies from the Lab to Humans
The workshop broadly focused on considerations for advancing manufactured islet cell therapies, including lab-based work, large-scale manufacturing, and clinical trial design. Read on to learn more about the discussion around each topic.
Nonclinical studies gather evidence showing that new therapies are likely to work and be safe in people before moving to clinical trials. Choosing the best experimental design is key for accurate, reliable, and reproducible data, which includes identifying the right T1D model and data collection method to answer the question at hand. Presenters also shared data around islet cell source, survival, and immune protection from ongoing preclinical projects.
Large-scale manufacturing is critical to make sure there are enough islets for everyone with T1D who wants them. There are several FDA manufacturing requirements that need to be met for scalable islet cell therapies to move from preclinical studies to first-in-human studies, and these requirements change as the studies get bigger. Presenters dove into considerations for islet manufacturing in academic versus industry settings and how each is helping us learn about the optimal ways to produce lots of consistent and reliable islets at once—which is really hard to do!
We know from previous and ongoing studies that islet cell therapies work—people are reducing or eliminating their need for injected insulin. We also know that for many people with T1D, the benefits of getting an islet cell transplant outweigh the risks associated with long-term immunosuppression. Presenters considered what future clinical trials should look like: how to expand inclusion criteria, define meaningful endpoints, and educate the T1D and healthcare community to drive referrals and participation. Researchers must carefully consider manufacturing, safety, and efficacy considerations to ensure that trial designs meet requirements defined by regulators to clear a path for approval of next-generation therapies.
Researchers are taking advantage of AI and applying it to different aspects of the islet cell therapy workflow, including individually forecasting blood sugar responses one-year post-transplant to help guide informed decision-making. Researchers are also using AI to optimize islet manufacturing, from predicting how islet cells will fare under certain conditions to analyzing data and modifying processes. AI can help design novel therapies on a cellular level, meaning “smart” islet cells that could sense immune attack and deploy immune-protective measures in a targeted way.
Several members of the T1D community shared powerful stories around their lived experiences with the condition. Some panelists have lived with T1D for decades and are seeing their children go through the same thing, while others have received successful (or unsuccessful) islet cell transplants. The group covered a range of topics: day-to-day burdens, technology, experiences with immunosuppression, and how islet transplants changed their lives (with one person noting that still needing one insulin injection per day post-transplant is a dramatically positive outcome). Ensuring the voices of the T1D community are heard by people in the field driving islet cell therapies forward is key to thoughtful person-centered research and design.
Learn more about how our Participant Advisory Council uses their voices to guide clinical trials.


Why this Matters
Islet cell therapy science is advancing on three fronts at once: nonclinical research in the lab, clinical trials in humans, and large-scale manufacturing. While researchers, scientists, and clinicians are working hard pushing these efforts forward, Breakthrough T1D is helping to keep the conversation open around what’s working, how to overcome challenges, how to engage with regulators, and new partnerships and collaborations. Even more, keeping the voices of people with T1D in the mix is key to advancing islet cell therapies in a way that’s meaningful for our community. Breakthrough T1D thanks the NIDDK for co-hosting a successful event and all presenters, panelists, and attendees for contributing to critical conversations that will ultimately help accelerate next-generation islet cell therapies for type 1 diabetes.
Finerenone is the First Therapy Approved in 30 Years for Kidney Disease and T1D
Today, the U.S. Food and Drug Administration (FDA) approved finerenone (brand name Kerendia) to reduce urinary albumin-to-creatinine ratio (UACR) in adults with chronic kidney disease (CKD) associated with type 1 diabetes (T1D). UACR is a measure of kidney damage, and reducing it is expected to slow kidney disease progression in adults with CKD and T1D. This is a major win for the T1D community—finerenone is the first therapeutic advance in 30 years for people living with the burden of T1D and kidney disease.
Finerenone
Finerenone is a once-daily pill that has been approved since 2021 for the treatment of CKD in type 2 diabetes and, since July 2025, for certain adults with heart failure. In CKD, the hormone aldolsterone is overactive, leading to kidney damage. Finerenone blocks this hormone’s activity to protect the kidneys from further damage.
Data from the FINE-ONE Study that Led to this Approval
Bayer’s global, phase 3 FINE-ONE clinical trial investigated the use of finerenone in people with CKD associated with T1D. This trial achieved its primary outcome: finerenone significantly reduced UACR—a measure of kidney damage—compared to placebo.
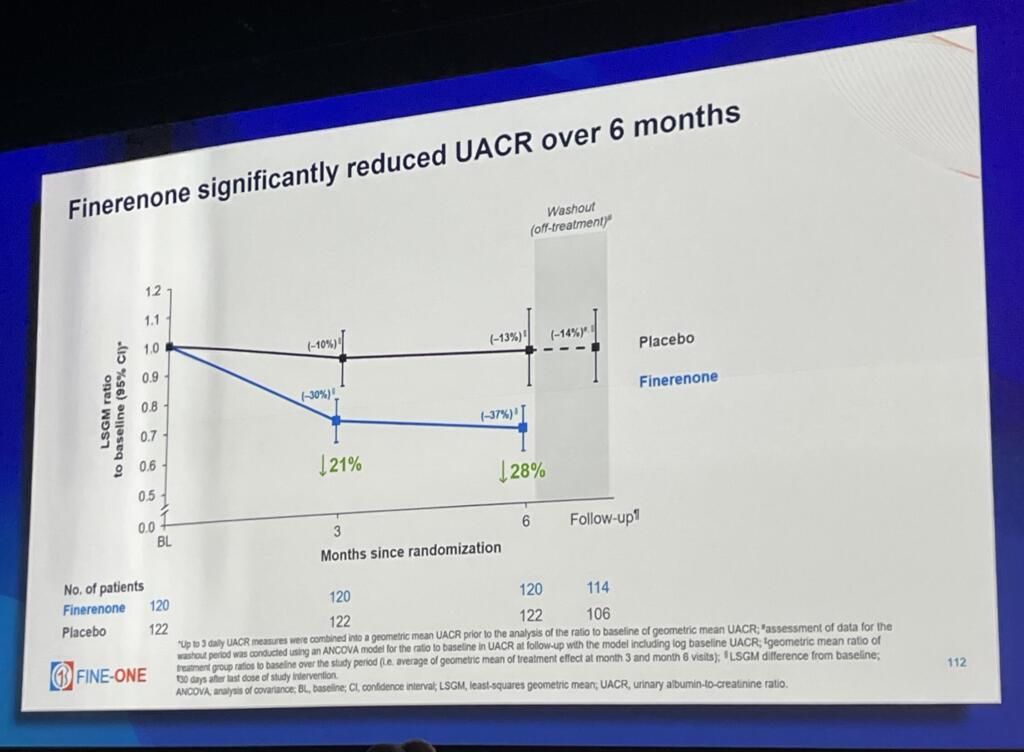
So, what does this mean? Previous clinical trials with people who have type 2 diabetes and CKD have shown that reductions in UACR from finerenone are associated with positive long-term health outcomes. In people with T1D, reductions in UACR caused by finerenone are likely indicative of lower risk of kidney disease progression, kidney failure, and cardiovascular events. These data were published in The New England Journal of Medicine.
Finerenone was well-tolerated, with no new safety issues reported and few serious adverse events. Based on these results, Bayer submitted the data for regulatory review, with the goal of expanding finerenone’s indication to include treatment of CKD in people living with T1D. Finerenone’s approval represents an incredible step forward for people living with the burden of both kidney disease and T1D.
A Win for T1D and Kidney Disease
CKD is one of the most common complications of T1D. Nearly a third of people living with T1D will develop CKD, increasing the risk of both kidney failure and cardiovascular disease. Right now, the treatment options for people with T1D and CKD are limited—and there is a major need for therapies that can address this.
Finerenone is the first therapy in three decades to achieve positive outcomes for CKD in people with T1D. This is a huge step forward in the right direction, and this exciting data has the potential to transform the lives of people living with T1D with CKD now that finerenone is approved for this population.
The Bigger Picture
Breakthrough T1D strategically collaborated with Bayer to support the FINE-ONE clinical trial, and we are committed to further collaboration with Bayer to advance therapies for people with T1D. Working together with Bayer and other companies will allow us to deliver more treatments to people with T1D to address complications like kidney disease.

“Today, there are few treatments available for chronic kidney disease, a common complication of type 1 diabetes. The approval of finerenone (brand name Kerendia) is a huge win for the T1D community. Breakthrough T1D thanks the FDA for its review and approval and Bayer for their commitment to giving people with T1D a new therapeutic option for chronic kidney disease.”
Jonathan Rosen, Ph.D., Research Director at Breakthrough T1D
As a part of our Improving Lives portfolio, we aim to identify and support treatments and therapies that can address complications that arise from T1D, like CKD. The approval of finerenone opens the door for more treatments to come that could transform the landscape of available therapies for people with T1D, and industry investment in this space helps drive progress forward faster than ever. The T1D community needs more options, and our strategic industry partnerships will help make this possible.
Breakthrough T1D thanks the FDA for approving finerenone and Bayer for their commitment to improving the lives of people living with CKD associated with T1D.
What’s Happening?
A new publication in The New England Journal of Medicine provides more detail about the first person with type 1 diabetes (T1D) treated with Sana Biotechnology’s gene-edited islets. This person is still making insulin 14+ months after their islet transplant—without immunosuppressants!
What to Know About Sana’s Gene-Edited Islets
Sana’s novel cell therapy approach is designed to help transplanted islet cells evade immune attack while continuing to produce insulin. The strategy uses gene editing to create hypoimmune islet cells, which are cells engineered to avoid detection by the immune system while maintaining their insulin-producing function. This approach is one of several next-generation cell therapy strategies being prioritized by Breakthrough T1D to help overcome one of the biggest barriers to cell replacement therapies: immune rejection.
In this first-in-human study, deceased-donor islets were genetically modified to become immune-evasive and then transplanted into the forearm. Because this is a phase 1 trial, the primary goal is to assess safety, while also monitoring islet function through C-peptide, a marker of the body’s own insulin production.
Importantly, the transplant included only about 5% of the number of cells typically needed to fully restore insulin production, reflecting the exploratory nature of the study.
The Results So Far
The results so far are encouraging. After 60 weeks, there have been no severe adverse events, meeting the trial’s primary safety endpoint. At 14 months after transplantation, the participant continued to produce detectable C-peptide, indicating that the transplanted cells remained alive and functional. The islet cells were also visible in the participant through PET and MRI imaging.
Researchers also observed that C-peptide levels temporarily declined after about one year, likely due to beta cell exhaustion, but subsequently recovered. This is an encouraging signal that the transplanted cells may be capable of regaining function.
Importantly, the participant had no detectable immune response to the transplanted islet cells. While the levels of T1D autoantibodies remained unchanged, this had no impact on the survival and function of the gene-edited islets.
What’s Coming Next
While still very early, these findings provide important proof of concept that gene-edited, immune-evasive islet cells can survive and function in a person with T1D. If confirmed in larger studies, this approach could help move the field closer to cell therapies that work without long-term immune suppression—a major goal for the future of T1D cures.
Excitingly, Sana plans to translate their hypoimmune gene-editing technology to manufactured islets in a new clinical trial, meaning that they are combining their unique immune protection strategy with a scalable approach. This is in line with our Project ACT initiative, which aims to dramatically speed development, access, and adoption of islet cell therapies for everyone with T1D who wants them.
Project ACT
Scientific progress takes time, resources, collaborations, and effort. To get islet cell therapies to people with T1D faster than ever, Breakthrough T1D launched Project ACT (Accelerate Cell Therapies) to simultaneously advance research, development, regulatory policies, access, and adoption of islet cell therapies that do not require broad immunosuppression.
Driving Research into T1D Cell Therapies
Sana is a portfolio company of the T1D Fund: A Breakthrough T1D Venture. Through equity investments, we have helped Sana grow their T1D pipeline, leading to their gene-edited islet cell therapy being investigated in human clinical trials. Even more, the T1D Fund recently invested in Century Therapeutics, another company developing manufactured islet cell therapies with immune-evasive capabilities. We will continue to work closely with Sana and other promising companies to support their product development and accelerate scalable islet cell therapy approaches that do not require immunosuppression.
This article was written by Sandy Vogt, Ph.D., and Brian Herrick.
Spotlight on Jessie Stover

Jessie Stover is the Development Manager at Breakthrough T1D’s Indiana Chapter. Stover was born and raised in Evansville, Indiana, and she now lives in Indianapolis with her two cats, Milo and Zuko. She enjoys reading, crafting, concerts, and “baking gluten-free desserts so good that no one can tell they’re gluten-free.”
Here, Stover tells her story: from type 1 diabetes (T1D) diagnosis as a toddler, to an insulin pump clinical trial, to learning how to manage her T1D as a teenager, to a new outlook on living with the condition as an adult. Breakthrough T1D thanks Stover for her bravery in sharing her story and her commitment to the T1D community.
Gummy Bears and Insulin Shots

Stover was diagnosed with type 1 diabetes when she was just 2 years old. While her family has a history of autoimmune disorders, “there is no one else in my family with T1D, so it was a big shock to my parents, and we all had so much to learn,” explains Stover.
The learning process started in the kitchen, with a container forever-full of gummy bears to treat lows, a new kitchen scale to measure and track carbs, and sugar-free versions of things Stover had always enjoyed, like Kool-Aid. Between her parents, grandparents, and school secretary, she had “quite the village.”
But, like any kid, Stover didn’t like shots, and she remembers running away from her parents when it was time for an insulin dose.
A Kiddo in a Clinical Trial
During one of Stover’s appointments with her endocrinologist in Indianapolis, she was referred to a clinical trial exploring whether young children could benefit from an insulin pump. “My mom is a very practical person, so it was almost a no-brainer for her since it meant the possibility of no more insulin shots, and it could help manage my blood sugars more smoothly,” explains Stover. No shots sounded pretty good.
By the age of 4, she was enrolled in the trial and using her first insulin pump. Stover noticed a difference immediately; the pump site insertion didn’t hurt at all because they had the option to use a numbing cream. The relief was tangible not just for Stover, but also for her primary caregiver: her mom. Using an insulin pump meant automatically calculated insulin doses, remote control of insulin dosing, and, most importantly, no more shots. Stover has been using an insulin pump ever since.
Learn More about Clinical Trials
Visit Breakthrough T1D’s clinical trials web page to learn more about how you can get involved in clinical trials. Use our clinical trial matching tool to find recruiting trials near you that you may be eligible for. Connect with a Clinical Trial Education Volunteer in your area to better understand the process and get your questions answered.
Being a Teenager is Hard Enough

As Stover grew into a teenager, she also grew into managing T1D on her own. This was when she first truly understood what her diagnosis meant. “It wasn’t new, but it was as if something finally clicked in my brain that it wasn’t going to go away, and now it was my turn to do all the work,” she explains. Coupled with stressful conversations around needing to “do better” to avoid future complications, it was a tough transition, and Stover struggled to find the resources to help her get through it. “Just because the textbook makes it look easy, and my mom made it look easy, it felt like I was expected to immediately do the same,” Stover recalls.
It all changed when someone on Stover’s diabetes care team said: “Being a teenager is hard enough. Adding T1D into the mix is like trying to stop a volcano from erupting!” For the first time, Stover felt that everything she was feeling about being a teen and managing T1D had been put perfectly into words. “I realized I was allowed to be angry, upset, and unhappy, and I didn’t have to just accept T1D and move on. Stepping back and allowing space to understand and grieve my diagnosis helped me,” she said.
This realization opened the door to more candid conversations and a stronger relationship with her parents. Stover was able to openly discuss her mental health needs and set boundaries around what she felt comfortable sharing with her parents about her T1D. “I let myself have space to have bad days and started celebrating the good. I started celebrating my diaversary and stopped trying to make other people comfortable with what I was going through, because I was the one going through it and I needed to do what I needed to do,” Stover explains.
Mental Health Guide
Check out Breakthrough T1D’s Mental Health Guide, which has everything you need to help you navigate the day-to-day of living with T1D.
A Fresh Outlook on Living With T1D

While Stover’s mindset around T1D evolved over the years, she also feels that mental health resources have improved dramatically since she was a teen. Now, she advocates for people living with T1D to take advantage of therapy or connect with others on social media who are experiencing the same thing. “There’s an entire community of people who decided diabetes wasn’t going to be invisible, and in doing so, more honest conversations can happen,” Stover explains. “We know more about chronic illness fatigue, medical trauma, and the effect of societal pressure to be ‘normal.’ If you go looking, you can find someone talking about it. Validation is a very powerful thing.”
Stover’s fortitude shined through when she was diagnosed with Celiac disease right after she graduated college. This time, things went a little differently; Stover had learned to give herself grace, and she found that figuring out how to manage a second autoimmune disease was a bit easier this time around.
In the years since Stover first started using an insulin pump, diabetes technology rapidly advanced with the evolution of pumps and continuous glucose monitors (CGMs), which, when used together, are called an automated insulin delivery (AID) system. As she grew up, Stover was hesitant to put her trust in new systems. “There are so many nuances to T1D care, and it’s been hard to wrap my head around how technology could know me better than I know myself,” Stover explains.
Yet, she eventually decided to add a CGM to her T1D management toolkit. “It is nice to be able to see how your glucose levels are trending,” Stover said. Despite living with anxiety around technology failures and hypoglycemia, Stover found a way to make CGMs work for her. She has her low alarm set when her glucose levels reach 100 mg/dL—well before the typical threshold of 70 mg/dL—so she can execute a plan of action before her blood sugars drop further. “It’s a little extra peace of mind to know that I can catch a low before it becomes a big problem.”
From kid to adult and all the ups and downs in between, Stover found how to manage her T1D in the way that works best for her.
Breakthrough T1D was (and Still is) Along for the Ride

Stover and her family were connected with other T1D families and Breakthrough T1D from the very start. There was a “tiny but mighty” team of parents who started a Breakthrough T1D Walk in Southern Indiana during Stover’s childhood, which, over time, often included many of her friends and classmates. Over two decades later, the Holiday World Walk in Indiana is still alive and well (and organized by Stover herself!).
In addition to Walk, Stover was a Youth Ambassador. “Breakthrough T1D has been a part of my life almost as much as T1D has. And now, getting to be a part of sharing the Walk with other families is truly a gift,” she says.
Word to the Wise
A word of advice from Stover: T1D is only invisible if you let it be. She encourages people living with the condition to take up space.
“Celebrate your diaversary, bedazzle your Omnipod, rock your fun patterned tapes, celebrate with diabesties. Find little ways to bring joy into it, but also take the time to feel the bad days. Take the time to learn how to let the good and bad coexist.”
Talk about T1D. Take advantage of resources. Connect with others online and in person. Give yourself grace. We can all learn a thing or two from Stover!

“We were never meant to do the job of the pancreas. Everyone carries the weight of T1D differently; everyone processes and grieves differently. There are going to be bad days, and the bad days should NEVER be punished. Grace, compassion, and a safe space to authentically be a person living with T1D will have a much better outcome. The only party at fault is the immune system that attacked the wrong thing.”
-Jessie Stover
They’re all over the news: Ozempic ®. Trulicity ®. Jardiance ®. Mounjaro ™. And more.
These drugs are all approved for glucose control in type 2 diabetes (T2D). Some of them also have additional indications reflecting their demonstrated benefits for cardiovascular disease, kidney health, and obesity.
None of these drugs are currently approved for glucose control in people with type 1 diabetes (T1D). However, a recent consensus report addressed the growing interest in GLP-1 receptor agonists as an adjunctive therapy for T1D and their “potential to improve glycemic and metabolic outcomes without increasing the risk of severe hypoglycemia or diabetic ketoacidosis.”
Let’s examine GLP-1 therapies and SGLT inhibitors and consider how drugs like Ozempic may one day help people with type 1 diabetes.
GLP-1 therapies
GLP-1 (glucagon-like peptide-1) receptor agonists work in multiple ways to control blood glucose and obesity. They block the release of glucagon, stimulate insulin production, slow the rate at which your stomach empties, and increase the sensation of feeling full. They are usually injected, but oral versions are available.
In people with T2D, this class of drugs lowers blood sugar levels and, for most people, causes weight loss. GLP-1 therapies have also been shown to reduce the risk of long-term cardiovascular complications often experienced by people with T2D, such as heart attack and stroke.
GLP-1 drugs include Ozempic/Rybelsus/Wegovy (semaglutide), Trulicity (dulaglutide), Victoza (liraglutide), and Mounjaro (tirzepatide), among others.
When GLP-1 treatments hit the market in the early 2000s, Breakthrough T1D and others funded several clinical trials to test whether GLP-1 receptor agonists, in addition to insulin, improved outcomes for people with type 1 diabetes. While some of these studies showed that the addition of GLP-1 therapies to insulin led to improvements in HbA1c, total insulin dose, and weight, the benefits were relatively modest and accompanied by some side effects like hypoglycemia (low blood sugar). As a result, these studies did not lead to GLP-1 receptor agonists being highly adopted for use by people with T1D.
However, these trials were done with older GLP-1 drugs. We are investigating whether the newest, most advanced GLP-1 therapies (like Ozempic) will improve the health of people living with type 1 diabetes. (See below!)
Consensus report on safe use of GLP-1 medications in T1D
Despite the fact that GLP-1 receptor agonists (and dual GLP-1/GIP receptor agonists) are not FDA-approved for use in T1D for any indication, people with T1D are still able to access these drugs since they are approved to treat obesity and overweight. Until now, HCPs have not had clear guidance around safe use for this class of drugs in people living with T1D.
Thanks to the diaTribe Foundation, including co-authorship by Brynn Marks, M.D. (Senior Director of Medical Affairs), we now have a consensus report featuring recommended expert guidelines for how HCPs and people with T1D can safely use GLP-1 medications alongside insulin therapy. This includes considerations around insulin dosing and continuous glucose monitor (CGM) adjustments, ketone management, monitoring and mitigating side effects (especially gastrointestinal) and complications like eye disease, and more. The idea is to support safe, individualized care for people living with T1D who may benefit from these medications.
This report also provides an overview of evidence around benefits of GLP-1 medications in T1D populations based on real-world and clinical trial data. Ongoing and future large-scale clinical trials are needed to provide additional data supporting the use of these drugs in people with T1D. Until then, both HCPs and T1D community members have a tangible resource for important considerations around using GLP-1 drugs safely. Consensus reports are a key step in driving clinical adoption of these therapies if they become FDA-approved for T1D in the future, and Breakthrough T1D endorses this report alongside five international diabetes organizations.
If you are living with T1D, consider talking to your healthcare team about the potential benefits of GLP-1 medications and see if they could be a fit for you.
SGLT inhibitors
SGLT (sodium-glucose co-transporter) inhibitors are oral medications for people with T2D that lower blood sugar by preventing the kidneys from reabsorbing glucose, leading to the excretion of sugar through the urine.
In addition to improving blood sugar for people with and without T2D, these drugs also provide benefits such as weight loss, blood pressure reduction, and transformative benefits to the heart and kidneys.
SGLT drugs include Jardiance (empagliflozin), Farxiga (dapagliflozin), and Invokana (canagliflozin), among others. The SGLT inhibitors empagliflozin and dapagliflozin are approved to treat chronic kidney disease and heart failure, regardless of diabetes status.
Yet, increased risk of diabetic ketoacidosis (DKA) in people with T1D limits the use of these therapies to improve blood sugar management or reduce the risk of complications. A key Breakthrough T1D priority is to find ways to mitigate this risk so people with T1D can also take advantage of the benefits of SGLT inhibitors.
Breakthrough T1D-funded research in GLP-1 and SGLT therapies
Breakthrough T1D has a long history with GLP-1 medications like Ozempic. In the 1980s, Breakthrough T1D-funded researcher Pauline Kay Lund, Ph.D., was the first to clone the hormone glucagon and discover two new hormones, one of which was GLP-1.
Today, there is real-world evidence of GLP-1 receptor agonists improving the lives of people with type 1 diabetes.
Real-world evidence
Observational studies using historical patient data from electronic health records (not randomized clinical trials) that can give an idea if a drug might be beneficial or not for a certain indication.
Evidence demonstrates that semaglutide (Ozempic) or tirzepatide (Mounjaro) have the potential to lower A1c, increase time-in-range, and reduce the amount of daily insulin needed in people with T1D. More research is needed in this area. That’s where Breakthrough T1D comes in!
Most recently, the Breakthrough T1D-funded ADJUST-T1D clinical trial showed that, in people with T1D and obesity or overweight using an automated insulin delivery system, Ozempic can help manage both weight and blood sugar.
Additional Breakthrough T1D-funded research on GLP-1 and SGLT therapies is investigating the benefits of these drugs for people with T1D, including reducing the risk of common complications of type 1 diabetes like cardiovascular disease and kidney disease.
Snapshot of active clinical trials in GLP-1 and SGLT therapies
Here are a few examples of Breakthrough T1D-funded clinical trials in GLP-1 and SGLT therapies that are currently underway:
| Clinical Trial Name | Study Details |
|---|---|
| REMODEL T1D | Determine whether semaglutide (Ozempic) protects the kidneys in those living with T1D. |
| Triple Therapy in T1DM | Assess whether the addition of dapagliflozin (Farxiga) to semaglutide (Ozempic) and insulin improves glycemic control in those living with T1D. |
| SUGARNSALT | Determine the effectiveness and safety of sotagliflozin (Inpefa) in slowing kidney function decline in those living with T1D and moderate to severe diabetic kidney disease. |
| Dapagliflozin + Pioglitazone in T1D | Examine how adding dapagliflozin (Farxiga) and pioglitazone (Actos) to insulin therapy affects glucose control and ketone concentration in people living with T1D. |
Our commitment to improving lives
Breakthrough T1D strives to improve health outcomes in people living with type 1 diabetes. Insulin therapy alone is often not enough for people with T1D to achieve glucose and metabolic control. The use of adjunctive drugs that complement insulin therapy can help. Since the FDA has already approved these medications for treating other conditions, positive results from these clinical trials could speed up the adaptation of these therapies for people living with T1D.
Learn more about clinical trials and how they are advancing breakthroughs for the T1D community.
What’s Happening?
In an exciting update for the type 1 diabetes (T1D) community, Tzield—the first disease-modifying therapy approved by the FDA to delay progression of stage 2 T1D—has now been approved by the FDA for use in stage 3 T1D. People aged 8-17 with stage 3 T1D will soon be able to get Tzield in clinics (with a prescription) if they have been diagnosed within the last 8 weeks. This makes it the first disease-modifying therapy approved for individuals in stage 3 T1D.
Breakthrough T1D thanks the FDA for recognizing the urgent need for disease-modifying therapies in T1D and for advancing access to Tzield for individuals with stage 3 T1D through a complete and rigorous review of the data and Sanofi for their commitment to the T1D community.
How Did This Happen?
Regulators at the FDA thoroughly reviewed data from the PROTECT clinical trial to support Tzield’s approval. The PROTECT study demonstrated that Tzield could safely and effectively preserve insulin-producing beta cells in newly diagnosed children and adolescents with stage 3 T1D. Clinical data shows that individuals with more beta cell function also have better diabetes-related outcomes, like improved HbA1c, more time in range, less hypoglycemia, and less insulin use.
Tzield was approved through FDA’s accelerated approval pathway, demonstrating FDA’s recognition of the urgent needs faced by those living with T1D. This means that based on the available data, the FDA has determined the drug is safe and reasonably likely to provide a clinical benefit and can be available while an additional clinical study happens. Based on the experience with Tzield in stage 2 and the robust evidence in stage 3, input from an external advisory committee was not needed.
Tzield is the first drug approved for stage 3 T1D—a major milestone for the field. Many disease-modifying therapies for stage 3 T1D are currently in clinical trials and at various stages of the drug development pipeline. This also marks the first time a disease-modifying therapy has been granted approval based on C-peptide, a marker of beta cell function. Breakthrough T1D has supported efforts to advance C-peptide as a clinical trial endpoint for nearly 10 years.

The Importance of Beta Cells
Beta cells are the cells in the pancreas that make insulin. In people with T1D, these vital cells are destroyed by the immune system. Thanks to years of research, including many studies funded by Breakthrough T1D, there is a significant amount of evidence showing that there are meaningful benefits to preserving beta cell function in people with T1D who are already using insulin. These include reduced hypoglycemic events, less insulin, reduced burden of care, and improved HbA1c. Learn more about C-peptide and the benefits of preserving beta cell function.
Tzield is Addressing an Unmet Need
Tzield was granted accelerated approval because FDA recognizes there is a large unmet need in the T1D population—and the potential for Tzield to help meet these needs.
In 2022, Sanofi’s Tzield also became the first disease-modifying therapy approved to delay the onset of stage 3 T1D in people with stage 2 T1D. Tzield, which has been supported by Breakthrough T1D for decades, has been a game changer in T1D as it’s the first therapy for this disease that addresses the root cause of T1D, not the symptoms. It targets the T cells that are responsible for destroying insulin-producing beta cells, slowing down the autoimmune processes that cause T1D. In people with stage 2 who receive Tzield, a stage 3 diagnosis is delayed by an average of 2 years. In April 2026, FDA expanded Tzield’s indication in stage 2 to include children as young as 1 year of age and older.
The vast majority of people in stage 2 don’t even know they have early T1D because there are no external symptoms. The only way to know is to get screened for risk markers of T1D. While the number of individuals screened for T1D has dramatically risen in recent years, most people progress to stage 3 before they have the chance to reap the benefit of Tzield delaying onset. Now that Tzield is approved for stage 3 T1D, people will have more opportunities to preserve insulin-producing beta cells, even if they didn’t identify their T1D early.

“The approval of Tzield for individuals ages 8-17 with stage 3 type 1 diabetes is an exciting milestone that reinforces the importance of beta cell preservation and provides an opportunity to change the course of the disease for those living with T1D,” said Aaron J. Kowalski, Ph.D., Breakthrough T1D CEO. “For the first time, individuals diagnosed with type 1 diabetes in stage 3 will have the option to treat the disease rather than just the symptoms. Breakthrough T1D thanks the FDA for recognizing the urgent unmet need in T1D and granting Tzield accelerated approval in the U.S. We are also grateful for Sanofi’s continued study of Tzield, and we look forward to the results of the confirmatory clinical research.”
What Happens Next?
Sanofi is conducting a new clinical trial, called BETA PRESERVE, to support full approval of Tzield for stage 3 T1D. This study will provide additional safety and efficacy data from children and adults with T1D up to 25 years old with stage 3 T1D treated with Tzield or placebo.
There are two primary endpoints: HbA1c levels and days without mealtime insulin. If you or anyone you know may be interested in participating, contact a study site near you to learn more and see if you are eligible.
The Bottom Line
For the first time, individuals diagnosed with T1D have a therapy option besides insulin that addresses the root cause of the disease. This is a historic first, modifying the course of T1D and allowing people to benefit from preserved beta cell function, as the PROTECT study has demonstrated.
This is incredibly exciting, but we are not done. We will continue to work to ensure individuals in stage 3 T1D all over the world, not just the U.S., have access to more therapies to help them do better.
Breakthrough T1D has been supporting the evolution of Tzield for decades, and we support its use in stage 3 T1D. We thank the FDA for recognizing the urgent unmet needs in T1D, and we are grateful to Sanofi for their continued research. Read more about the journey of Tzield from the lab and into clinics (written by Breakthrough T1D supporter Doug Lowenstein).
The recent news about successful clinical trials in islet cell therapies for type 1 diabetes cures is very exciting. But the science behind it can be confusing. Breakthrough T1D is here to answer all of your questions about islet cells, from the research lab to real-world treatments.
What are islet cells?
Islet cells are a group of cells in the pancreas that release hormones to regulate blood sugar. Beta cells are a type of islet cell that make insulin. In people with type 1 diabetes (T1D), the autoimmune system destroys the beta cells in the pancreas, which produce insulin.
What is islet cell therapy?
Islet cell therapies replace destroyed islet cells with external insulin-producing cells and protect them so that they can function for a very long time.
Is islet cell therapy a cure for type 1 diabetes?
The answer is: It could be.
Adults around the world who have received islet cell transplants are coming off external insulin, lasting from months to years. But for newer, more advanced islet cell therapies, we are still doing clinical trials and don’t yet know how these cells will work long-term.
Right now, islet cell therapies as potential cures for type 1 diabetes are limited to adults with severe T1D who have a lot of trouble managing their condition. Even more, adults who are eligible to receive islet cell therapies need to take lifelong immunosuppressants, which, depending on other health considerations, may not be the right decision for everyone.
To make islet cell therapies available to everyone with T1D who may want them, Breakthrough T1D’s end goal is to manufacture islet cells on a large scale and safely put them inside the body of every person with T1D to replace the cells that were lost without the use of immunosuppressants. This would effectively cure type 1 diabetes.
Are there any islet cell therapies available right now?
In Europe and Canada, islet cell therapies using islet cells from deceased donors have been successfully used to treat people with T1D for years.
In the United States, there is currently one islet cell therapy approved for T1D as of 2023 called Lantidra®, which is also derived from deceased donors. Lantidra and other islet cell therapies used around the world are intended for adults with T1D who experience:
- Severe hypoglycemia (dangerous low blood sugar)
- Hypoglycemia unawareness (the inability to sense when blood sugar is dropping)
These individuals often cannot safely manage their blood glucose levels with the standard therapies used to manage T1D.
Other islet cell therapies are still in clinical trials. Adults with T1D who are interested in participating in these clinical trials generally must meet the same eligibility requirements: severe hypoglycemia and hypoglycemia unawareness.
What are deceased donor islet cells?
Deceased donor islet cells come from the pancreases of deceased donors. It can take up to three pancreases to get enough islet cells for one transplant. Deceased donor islet cells are in limited supply, and there aren’t enough for everyone with T1D who may want them. This is similar to a kidney or liver transplant—there aren’t enough organs for everyone who needs them.
What are manufactured islet cells?
Thanks to years of support from Breakthrough T1D and others, scientists can manufacture islet cells in a laboratory by using specific protocols to turn precursor cells into insulin-producing cells. Manufactured islet cells can be made in large quantities and are the only solution to making sure there are enough islet cells for everyone with T1D who may want them.
How are islet cells transplanted?
Islet cell transplantation is a procedure in which insulin-producing islet cells (from either deceased donors or a manufactured source) are transplanted into a person living with T1D. Once transplanted, these cells can begin producing insulin in response to blood glucose levels.
Lantidra, the only approved donor-derived islet cell therapy for T1D in the U.S., is transplanted as a single infusion into a vein in the liver. Other islet cell therapies in clinical trials are testing different transplantation sites around the body, such as in the forearm muscles, in a small device underneath the skin, or within the abdominal wall. The goal is to figure out which transplant sites allow the cells to have the greatest chance of survival.
Recipients of Lantidra—and most other donor-derived and manufactured islet cell therapies in clinical trials—must take immunosuppressives to prevent the body from rejecting the transplanted cells. However, researchers are testing new ways to protect islet cells without immunosuppressants.
What is immunosuppression?
Immunosuppression uses drugs to reduce the effectiveness of your immune system. It is required to prevent your body from rejecting a transplant.
A person who receives a transplant of any kind will almost always need to take immunosuppressants for the rest of their lives. Immunosuppressants help keep transplanted organs, tissues, and cells alive. However, they can come with side effects and may make individuals more susceptible to infections and cancers. For those who are eligible to receive an islet cell transplant, it is up to individuals and their care teams to determine if the benefits of receiving a transplant outweigh the risks of lifelong immunosuppression.
Why do current cell therapies require immunosuppression?
Most islet cell therapies—including Lantidra and those in clinical trials—require immunosuppression. This is because the source of the islet cells comes from somewhere other than your own body. Your body views the transplanted cells as “foreign,” meaning the immune system will activate and reject the transplant, and the islet cells will die. To prevent this from happening, immunosuppressants can dampen your immune system so that it doesn’t attack the transplanted cells.
Researchers are finding new ways to make immunosuppression milder or remove the need for immunosuppression altogether. Some of these approaches are already in clinical trials.

Why is there so much talk about clinical trials and T1D?
Without clinical trials, we would never know if new therapies developed by scientists in the lab could make a difference in people’s lives. This is where the T1D community comes in! By volunteering to participate in clinical trials, you become uniquely positioned to help drive biomedical research forward. Moreover, by participating, you help not only yourself, but everyone with T1D.
Why are there such specific eligibility requirements for cell therapy clinical trials?
Clinical trials can come with both risks and benefits. The potential benefit would be the islet cell therapy working, meaning the transplanted islets survive and make insulin. The potential risks include side effects from the transplant procedure, chronic immunosuppression, and more.
Right now, these trials are limited to adults with the most difficultly managing their T1D because the potential benefits outweigh the risks. The adults eligible to participate in these trials will help researchers gather more evidence about the safety and efficacy of islet cell replacement therapies.
Until researchers have more data on the safety and efficacy of islet cell therapies, children are not yet eligible for these trials to protect them from the potential risks. Future clinical trials may be available to children and other populations of adults with T1D, but we are not there yet.
Where can I find cell therapy clinical trials I’m eligible for?
Breakthrough T1D has an easy-to-use tool called the Clinical Trials Connection, which asks users simple questions—about where they live, the distance they can travel, and other characteristics—to match them with trials for which they are eligible.
Here are some currently recruiting trials in cell therapies in the U.S.:
| Clinical Trial Name | Immunosuppression Required? | Participation Criteria |
|---|---|---|
| A Safety, Tolerability, and Efficacy Study of VX-880 in Participants With Type 1 Diabetes | Yes | Ages: 18 to 65 Years Living with Insulin-Dependent T1D: More than 5 Other Criteria: At least two episodes of documented severe hypoglycemia in the 12 months prior to enrollment Consistent use of a CGM for at least 3 months before screening |
| An Efficacy, Safety, and Tolerability Study of VX-880 in Participants With Type 1 Diabetes With a Kidney Transplant | Yes | Ages: 18 to 65 Years Living with Insulin-Dependent T1D: More than 5 Other Criteria: Taking a stable immunosuppression regimen of tacrolimus and mycophenolate mofetil, mycophenolate sodium, or sirolimus for at least 4 weeks Consistent use of CGM for at least 4 weeks before screening and willingness to use CGM for the duration of the study |
| Safety, Tolerability, and Efficacy of Immunomodulation With A Monoclonal Antibody Against CD40L in Combination With Transplanted Islet Cells in Adults With Brittle Type 1 Diabetes Mellitus (T1D) (Tegoprubart) | Yes | Ages: 18 to 65 Years Living with Insulin-Dependent T1D: More than 5 HbA1c Level: 6.5% to 9.5% Other Criteria: At least 3 unexplained severe hypoglycemic episodes not secondary to a missed meal or dosing error, in the 12 months prior Impaired awareness of hypoglycemia |
| Breakthrough – T1DM and Chronic Kidney Disease | Yes | Ages: 18 to 70 Years Living with Insulin-Dependent T1D: More than 5 HbA1c Level: 6.5% to 9.5% Other Criteria: Chronic kidney disease stage 1, 2 or 3a |
| A Study to Investigate Safety and Effectiveness of Porcine Pancreatic Cells (OPF-310) in Patients With Type 1 Diabetes Mellitus | No | Ages: 35 to 65 Years Living with Insulin-Dependent T1D: More than 5 HbA1c Level: Over 9.0% Other Criteria: Unable to achieve adequate control of T1D using a closed-loop systems for at least 6 months prior to enrollment At least one episode of severe hypoglycemia in the 12 months prior to study consent |
| Improving Islet Transplantation Outcomes With Gastrin for Type 1 Diabetes | Yes | Ages: 18 to 68 Years Living with Insulin-Dependent T1D: More than 5 Other Criteria: Unstable blood glucose characterized by frequent hypoglycemia and/or hypoglycemic unawareness and/or one or more hospital visits for DKA in the 12 months preceding enrollment |
| Islet Transplantation in Type 1 Diabetic Kidney Allograft | Yes | Ages: 18 to 68 Years Living with Insulin-Dependent T1D: More than 5 Other Criteria: Kidney transplant 3 or more months ago and taking appropriate calcineurin inhibitor (CNI)-based maintenance immunosuppression |
| Pancreatic Islet Transplantation Into the Anterior Chamber of the Eye | Yes (localized eye drops) | Ages: 18 to 75 Other Criteria: At least one eye with extensive loss of vision from hand motion to no light perception Phakic or pseudophakic with a stable intraocular lens in the blind eye Normal cornea with good visualization of the anterior segment Normal anterior segment anatomy including the iris bed |
| Islet Transplantation With Recipient T-Reg Cells or Deceased Donor Vertebral Bone Marrow Therapy | Yes | Ages: 18 to 75 Years Living with Insulin-Dependent T1D: More than 5 Other Criteria: Involvement in intensive diabetes management defined as self-monitoring of glucose values no less than a mean of three times each day averaged over each week and by the administration of three or more insulin injections each day or insulin pump therapy. At least two episodes of severe hypoglycemia in the 12 months prior to study enrollment Reduced awareness of hypoglycemia |
Everyone says a cure is 5-10 years away. Why does progress seem to be so slow for T1D advancements?
First, clinical trials can take quite a long time. It can be difficult to find people with T1D who are eligible and willing to participate. Also, people who are receiving a new therapy or treatment often need to be monitored for years to understand long-term safety and efficacy.
Second, science is often complex and unpredictable. Research and clinical trials don’t always turn out the way we hope they will. And we can’t always predict how long research will take. But, all data is good data! Researchers learn from clinical trials to help think about the best way to approach future studies.
Does fundraising for Breakthrough T1D helping fund research in cell therapies?
As the leading global T1D research and advocacy organization, Breakthrough T1D is currently funding over $450 million in research in 24 countries. Everything we do is focused on making cures happen for everyone facing T1D, sooner.
Without continuous support from the T1D community, we would never have gotten this far.
Breakthrough T1D looks forward to a future where manufactured islet therapies are a reality for everyone with T1D, and we will not stop until we get there.
Will cell therapies ever become available for everyone living with T1D?
In the coming years, it’s likely that first-generation manufactured islet therapies will be available to people with T1D with severe hypoglycemia unawareness and will require broad immunosuppression. Later, advancements in cell survival and immune protection—combined with the discovery of more tolerable immune suppression approaches—will open the doors for more people with T1D to access these life-changing therapies.
Project ACT
Scientific progress takes time, money, and effort. To accelerate islet replacement therapies faster than ever, Breakthrough T1D launched Project ACT (Accelerate Cell Therapies) to simultaneously advance research, development, regulatory policies, access, and adoption of manufactured islet therapies that do not require broad immunosuppression.
By Sandy Vogt, Ph.D. and Kara Sweet
ADA’s 86th Scientific Sessions
This event is one of the largest diabetes conferences in the world, bringing together over 11,000 attendees to share and learn about cutting-edge research and advancements toward cures. Each year, Breakthrough T1D-funded researchers highlight their work, demonstrating the progress we’re making toward achieving our mission. Leading experts will present over 100 studies spanning cell therapies, disease-modifying therapies (DMTs), diabetes technology, treatments, and more!
ADA 2026 has officially come to a close! We’re excited to report on the final two days of the conference, with even more updates spanning Cures and Improving Lives. Read on to learn about Breakthrough T1D-funded research making an impact and highlights from our on-site staff, especially in cell therapies.
Check out the updates from days 3 and 4 across Cures and Improving Lives:
Quick Primer on T1D Immunology Terms
- Antigen: part of a beta cell that the immune system mistakenly recognizes as “non-self” and mounts an immune response against.
- Antigen-presenting cell (APC): Immune cell that “presents” beta cell antigens on their surface to T cells, which then learn to attack the beta cells.
- T cells: The destructive immune cells that directly attack beta cells.
- Regulatory T cells (Tregs): help control and resolve immune responses but are less functional and effective in T1D.
Cell Therapies
Cell Therapies Highlight: Breakthrough T1D-Funded Clinical Trial for Tegoprubart Continues to Hit Milestones
Piotr Witkowski, M.D. (University of Chicago) gave an update on the Breakthrough T1D-funded clinical trial for Eledon’s tegoprubart, an immune therapy being tested with donor-derived islet cell transplants. All 12 participants are off external insulin. They are not experiencing severe hypoglycemic events or unexpected adverse events, there are no signs of the body rejecting the transplanted cells, and there are no signs of kidney toxicity.
Islet Size Matters
- Presenter: Julia Panzer, Ph.D. (City of Hope)
- In humans, islets have a range of sizes.
- Older adults with T1D tend to have smaller islets, but we don’t know if islets are shrinking or if more small islets are being generated.
- Based on islets isolated from donor pancreases and sorted by size, smaller islets are less responsive to changes in glucose, and they are preferentially targeted by T cells (the immune cells that attack insulin-producing beta cells).
- This work provides insight into how T1D may progress differently with age based on changes in islet size.
Cell Therapies Highlight: Research Funded by Breakthrough T1D or the T1D Fund
Jessica Weaver, Ph.D. (Arizona State University) presented about how we can learn lessons from placental immunology to train the immune system to ignore beta cells in T1D. During pregnancy, specialized cells in the placenta (called trophoblasts) teach the mother’s immune system to ignore the developing baby. Dr. Weaver is testing if trophoblasts can be successfully transplanted in mice in an encapsulation device her team optimized through computational modeling to improve cell survival. The goal is to eventually see if trophoblasts can be co-implanted with islet cells so that they send signals to the immune system to ignore them.
Leonardo Ferreira, Ph.D. (Medical University of South Carolina) presented on a dual cell engineering strategy for T1D. In this approach, manufactured beta cells are engineered to display a unique protein fragment on their surface. Tregs are then engineered to recognize that same unique fragment. When implanted together, the Tregs can turn down the activity of any destructive immune cells that become activated against the protein fragment. In mouse models, this method has proven to be successful, and Dr. Ferreira is finding even more ways to modify these cell types to enhance their functions. The idea is to translate this into a new manufactured islet cell therapy approach that would also modify a person’s immune cells so that immunosuppression is not required.
Julie Sneddon, Ph.D. (University of California, San Francisco) studies how precursor cells turn into beta cells during development. Her work provides insights into how we can harness this knowledge to optimize beta cell manufacturing in the lab for large-scale islet cell therapies.
Quinn Peterson, Ph.D. (Mayo Clinic) focuses on manufacturing all the different cells of the islet, in addition to beta cells, for islet cell therapies. His work in T1D mouse models showed that implanting beta cells with alpha cells (which secrete glucagon) allows them to function better with fewer cells. This could have implications for how we optimize islet cell replacement therapies.
Peng Wang, Ph.D. (Mount Sinai Icahn School of Medicine) presented his work on a small molecule called harmine, which can promote the function and expansion of beta cells in T1D mouse models. The goal is to use harmine in the context of manufactured islet cell transplants to improve their maturation and function to make these therapies more effective.
Leonardo Velazco-Cruz, Ph.D. (Century Therapeutics, a T1D Fund portfolio company) presented on the company’s manufactured islet cell therapy product, CNTY-183, which is engineered with Allo-evasion 5.0 technology so that immunosuppression is not needed. Dr. Velazco-Cruz reported that Century Therapeutics has developed a scalable, bioreactor-enabled differentiation process that can produce consistent, functional manufactured islets. In mouse models, engineered islets were protected from the immune system and maintained insulin production as measured by C-peptide. The company will continue to develop its product for eventual translation into humans.

Advocacy Staff Making an Impact
Clem Cypra, Director of Health Policy, presented a poster from our Advocacy team on how well insurance claims capture hypoglycemia in people with T1D. This is especially important because an eligibility requirement for islet cell therapy clinical trials is severe hypoglycemia, and payers often use claims data to understand who may qualify for new therapies. The team found that claims capture significantly lower rates of hypoglycemia in people with T1D compared to rates reported in clinical studies and published reports. Therefore, relying on claims alone may result in coverage decisions that are not in line with real-world care for people with T1D, and additional research is needed to fully uncover the impact of hypoglycemia on the T1D community.

Key Takeaways
- Breakthrough T1D-funded cell therapy research is advancing on two fronts: helping transplanted islet cells survive and function without lifelong immunosuppression, and manufacturing better islet cells at scale.
- The clinical trial studying tegoprubart at the University of Chicago continues to impress, with all 12 participants off external insulin and no signs of rejection or kidney toxicity.
- Across the funded portfolio, researchers are engineering the immune system to tolerate beta cells while others refine how islet cells are created in a lab.
- Together, this work is moving the field toward manufactured islet cell therapies that could one day restore insulin production without immunosuppression.
Disease-Modifying Therapies
Cell engineering approaches to turn down autoimmunity
- Presenter: Justin Spanier, Ph.D. (University of Minnesota)
- The interaction between APCs and T cells is critical to the autoimmune process.
- Dr. Spanier presented on two different cell engineering strategies to disrupt this interaction.
- The first approach involves developing an antibody that binds to beta cell antigens on the surface of APCs, which physically blocks T cells from interacting with it.
- The second approach involves engineering Tregs to interact with beta cell antigens on the surface of APCs so that, again, T cells cannot interact.
- Dr. Spanier is further refining these approaches with the ultimate goal of finding new ways to suppress autoimmunity in T1D.
Disease-Modifying Therapies Highlight: Breakthrough T1D-Funded Research
Jacqueline Burke, Ph.D. (Northwestern University) spoke about the development of a “tolerozome,” a nanoparticle loaded with an immune-modulating agent (rapamycin) that can train the immune system to ignore beta cells. Her approach is unique in that tolerozomes are delivered specifically to immune cells, meaning that other surrounding cells are unchanged. Even more, this approach can be applied to islet cell transplants (to prevent attack on transplanted cells) or early-stage T1D (to preserve the body’s beta cells). Data from animal models of T1D support the potential for these approaches with limited toxicity, and ongoing studies will assess long-term tolerozome dosing and combination with manufactured islets.
Spotlight on Breakthrough T1D-Funded Research: Uncovering Biological Mechanisms in T1D
T1D Pancreases have Tissue-Wide Biological Alterations
- Presenter: Dirk Homman, M.D., Ph.D. (University of Miami)
- Dr. Homman presented his work on full-scale assessment of the entire pancreases of people with T1D (obtained through the Breakthrough T1D-sponsored nPOD program).
- Using histology and single-cell computational methods, he found that T1D pancreases have tissue-wide alterations that are not limited to islets.
- These findings will provide a better basis for our understanding of T1D pathology and help researchers adapt mouse models of T1D to better mimic biological changes that occur in humans.
Beta Cells are Stressed
- Presenter: Farooq Syed, Ph.D. (Arthur-Riggs Diabetes and Metabolism Research Institute)
- Beta cells have increased signaling through specific stress-response pathways, which may contribute to their ability to provoke an autoimmune response.
- Dr. Syed explored how stress pathways can influence large-scale changes in beta cell genes, further uncovering how molecular alterations in the beta cells themselves may contribute to autoimmunity.
Key Takeaways
- Disease-modifying therapy research is focused on retraining the immune system in a targeted way to ignore the beta cells so they can continue to produce insulin.
- These strategies include engineering various agents, including antibodies, modified Tregs, nanoparticles, and more that may protect transplanted islets or preserve beta cells in early-stage T1D.
- Foundational research is also deepening our understanding of the disease itself: T1D pancreases show tissue-wide alterations beyond the islets, and beta cells under stress may help provoke the autoimmune response.
- Together, we are going down the path to new ways to slow or stop the autoimmune attack at the heart of T1D.
Early Detection
Global Pediatric Screening Inequities
- Presenter: Jean Claude Katte, M.D., Ph.D. (University of Exeter)
- The Young Onset Diabetes in Sub-Saharan Africa study found that most people diagnosed with T1D in this geography did not have any autoantibodies detected.
- T1D screening tools based on autoantibody detection were developed using white populations with a European ancestry.
- This suggests that our current screening model and staging framework may not be suitable for people from all geographies since there appears to be biological variability.
- Dr. Katte also highlighted significant inequities in access to care in Africa and other geographies.
- Breakthrough T1D is committed to helping close these gaps through our Advocacy work around the globe, including our ALIGN-T1D initiative.
Monitoring Youth with One Persistent Autoantibody
- Presenter: Nicole Sheanon, M.D., M.S. (Cincinnati Children’s Hospital Medical Center). Dr. Sheanon is also a part of our Mission Impact Volunteer program.
- Around 15% of youth with a single autoantibody detected and no symptoms will go on to develop T1D.
- The first three years after autoantibody detection are the most critical monitoring window.
- Healthcare professionals (HCPs) should look out for any changes in health that may signal progression of T1D, including changes in HbA1c levels or the development of an additional autoantibody.
- Education is critically important so that families know to remain aware of the potential risk of T1D development, even if it’s low.
- For more, take a look at published consensus guidance for monitoring of early-stage T1D, which was published a few years ago and spearheaded by Vice President of Medical Affairs Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES.

Early Detection Highlight: Breakthrough T1D-Funded Researchers and Staff
Holly O’Donnell, Ph.D. (Barbara Davis Center) presented on the psychosocial impact of T1D diagnoses (early-stage and clinical) on families. Dr. O’Donnell found that communicating with families about the risk of T1D progression can be a challenge, and education efforts need to be individualized and repeated to be effective. Families with a greater understanding of T1D risk also tend to have more anxiety, especially for those who have a family history of the disease. Dr. O’Donnell is currently working on a Breakthrough T1D-funded study to adapt a cognitive behavioral therapy to reduce anxiety around risk of progression for families with children in early-stage T1D. For more, see Dr. O’Donnell’s o-demand seminar for HCPs.
Dr. Albanese-O’Neill spoke about recommendations for T1D screening and monitoring. She covered a range of topics, including the global T1D screening landscape, ICD-10 diagnosis codes for early-stage T1D, and the potential benefits and of screening, early detection, and follow-up monitoring. Dr. Albanese-O’Neill also discussed the importance of clinical trials, especially for DMTs targeted toward early-stage or newly diagnosed individuals, and she urged the HCPs in the audience to encourage research participation in their clinics. She closed with information about our early detection pilot clinics and international consensus guidelines for general population T1D screening, developed by Dr. Albanese-O’Neill with expert collaborators.

Key Takeaways
- Current screening methods may miss people elsewhere, so we must adapt our screening and staging frameworks need to ensure it works across the globe.
- Breakthrough T1D is working to close these gaps through Advocacy efforts around the world, including the ALIGN-T1D initiative.
- The first three years after detection are the most important monitoring window for youth who have a single autoantibody.
- Although it does have marked benefits, learning about T1D risk early can be emotionally difficult for families. Breakthrough T1D-funded research is developing tailored support to help them cope.
Improving Lives
The State of T1D in Adults
- Presenter: Marissa Hitchcock, BSN, RN, CDCES (Children with Diabetes)
- The global prevalence of T1D is increasing by 2-3% each year.
- 21% of adults with T1D are meeting HbA1c targets of less than 7%, and 64% are using diabetes technology.
- Cardiovascular events occur 10 to 15 years earlier in T1D adults, and 30-40% of adults develop kidney disease within 25 years of diagnosis.
- There are not enough options for adults with T1D to reduce their risk for heart and kidney disease; while GLP-1 receptor agonists and SGLT inhibitors are showing promise in clinical trials, they are still not approved and widely accessible.
- Major gaps in care for this population include healthcare access and affordability, psychosocial support, socioeconomic disparities, and representation in clinical trials.
- We need to do more for adults with T1D, and a major priority of Breakthrough T1D is funding research into devices and therapies that can improve blood sugar and weight management and reduce complications so T1D adults can do and feel better.
Improving Lives Highlight: Breakthrough T1D-Funded Researchers and Staff Making an Impact
Courtney Ackeifi, Ph.D., Senior Scientist, hosted a networking event for building partnerships with scientists and clinicians working on cardiometabolic therapies for T1D. In a short presentation, she highlighted the urgent need for cardiometabolic therapies for the T1D community and opportunities to partner with Breakthrough T1D to accelerate progress in this area. Anyone who is interested can check out our funding opportunities.
Key Takeaways
- It is critical that we continue to invest in complications research, especially as adults with T1D are encountering earlier and higher rates of heart disease and kidney disease. We need more options.
- There are still significant gaps that are preventing everyone from having access to the therapies that work best for them- Major gaps remain in access, affordability, mental health support, and clinical trial representation for adults with T1D.
- Breakthrough T1D is working to close these gaps so there are more options for people with T1D and they are accessible.
Advocating for Children with T1D
Lauren Figg (Stanford University) presented on how the medical community can advocate for children with T1D to get adequate access to care. Social needs, including basics like food, clothing, and shelter in addition to whether they can afford insulin or other supplies, should be document in electronic health records so HCPs can provide the appropriate support. Figg also suggested that HCPs be aware of local community resources, deliver information through multiple ways (verbal, printed, etc.), and follow up with families to ensure they are getting the T1D care they need.

That’s a wrap on ADA 2026! For more, tune in on Wednesday, June 10, at 6 PM Eastern Time on our social channels for a live Mid-Year Mission Update from our leadership—including highlights from ADA, recent advances, and what we can look forward to for the rest of 2026.
Coming soon: A full ADA 2026 recap with everything you need to know about the conference. Keep an eye on our News & Updates webpage!
ADA’s 86th Scientific Sessions
This event is one of the largest diabetes conferences in the world, bringing together over 11,000 attendees to share and learn about cutting-edge research and advancements toward cures. Each year, Breakthrough T1D-funded researchers highlight their work, demonstrating the progress we’re making toward achieving our mission. Leading experts will present over 100 studies spanning cell therapies, disease-modifying therapies (DMTs), diabetes technology, treatments, and more!
Reporting live from New Orleans, LA! Breakthrough T1D is on site at ADA 2026 with leading scientists, clinicians, healthcare professionals, industry partners, and more to hear about exciting updates in type 1 diabetes (T1D) research—including work supported by Breakthrough T1D.
Read on for everything you need to know from the first two days ADA 2026, including key takeaways from panels and sessions featuring Breakthrough T1D staff and noteworthy highlights from Breakthrough T1D-funded researchers—both past and present—whose work was front-and-center.
Check out the updates from days 1 and 2 across Cures and Improving Lives!
Cell Therapies: Breakthrough T1D Staff at the Forefront
Sanjoy Dutta. Ph.D., Chief Scientific Officer, participated in a panel discussion about advancing manufactured islet cell therapies for widespread clinical use. A major theme was that eligibility requirements for clinical trials are too narrow—which means that less people have the chance to benefit and trials don’t progress as quickly. Patient-reported outcomes will be important to demonstrate to regulators that many people with T1D can and want to benefit from islet cell replacement therapy, and we need established, systemic methods in place to take the T1D community’s opinions into account.
The panelists also discussed the current challenges surrounding immunosuppression, which is one of the barriers to clinical trial participation, and ongoing efforts to develop novel cell protection strategies. Immunotherapies in development for early-stage T1D may be applicable in islet cell transplant settings, including approaches that retrain the immune system to ignore beta cells—an area that Breakthrough T1D is invested in.
To accelerate progress in manufactured islet cell therapies, the panelists agreed that the top priorities are:
- More companies exploring novel approaches
- Expanding eligibility criteria for trials—and incoporating the perspectives of the T1D community into regulatory decisions—so we can build more evidence around the safety and efficacy of manufactured islet cell therapies
- Additional frameworks to help guide the field, like our cell therapies roadmap and upcoming publications from Breakthrough T1D staff around manufacturing and preclinical considerations
- Optimizing manufacturing processes to reduce costs and ensure access for people who want these therapies
- Optimizing cell therapy products by reducing or eliminating the need for immunosuppression and finding the best transplant site for survival

Brynn Marks, M.D., Senior Director of Medical Affairs, chaired a session about the promise and perspective of islet cell replacement therapies for kids with T1D. Notably, Melena Bellin, M.D. (University of Minnesota) spoke about insights from children with pancreatitis who require full pancreas removal and receive transplants of their own healthy islet cells into their livers. In comparison to adults, children who receive this type of dual transplant have higher rates of islet survival and function and are more likely to stop needing external insulin. Laura Jacobsen, M.D. (University of Florida) spoke about practical clinical expectations for cell therapies and DMTs based on the data we have in adults and what this might mean for kids. Finally, Jane Speight, Ph.D. (The Australian Center of Behavioral Research in Diabetes) closed out with a talk about psychosocial considerations for pediatric islet cell transplantation.

Key Takeaways
The data surrounding islet cell therapies is very exciting, but we have more work to do until manufactured products are accessible to everyone with T1D who may want them. We are at the very beginning of considering what these therapies might look like in the pediatric T1D population.
Disease-Modifying Therapies
C-peptide
C-peptide is a biomarker of the body’s insulin production, which can be measured easily by a blood test. It’s formed when pro-insulin is cleaved into active insulin and C-peptide.
The Potential for a New and Improved C-Peptide
- Presenter: Samuel Sangqu Wu, Ph.D. (University of South Florida)
- C-peptide has the potential to be a validated endpoint for DMT clinical trials, and researchers like Dr. Wu are looking into new ways to help make this possible.
- Time to minimal residual C-peptide (TMRCP) is defined by how much longer people will have measurable C-peptide—meaning how long they will continue to make insulin.
- Dr. Wu applied this metric to six TrialNet studies and found that extrapolating TMRCP identified the same treatments as effective as each original analysis.
- TMRCP may be another metric to define the clinical meaningfulness of C-peptide, meaning it could be an alternative endpoint to consider for future DMT trials.
- Breakthrough T1D supported these efforts.
TEPLI-REAL: Evaluating Real-World Outcomes of People Treated with Tzield
- Presenter: Stephen Gitelman, M.D. (University of California, San Francisco)
- The purpose of this study was to understand populations who pursue treatment with Tzield and post-treatment outcomes through review of electronic health records.
- Diagnosis of T1D is heterogeneous, with people having either autoantibodies or dysglycemia (abnormal blood sugar) detected first, or others having both detected at the same time.
- These diagnostic pathways influence Tzield initiation. Those who had dysglycemia and autoantibodies detected at the same time had the shortest median time to start treatment.
- Most people who initiated Tzield were adolescents, and 94% of people who started treatment completed the full 14-day course.
- This study offers important considerations for healthcare professionals (HCPs) regarding how T1D diagnosis influences Tzield treatment in routine practice.
Decoding Immune Mechanisms and Engineering the Immune System in T1D
- Todd Brusko, Ph.D. (University of Florida) presented on spatial locations of different immune cells that contribute to the autoimmune process in T1D pancreases—and the underlying mechanisms that influence this.
- Kyle Gaulton, Ph.D. (University of California, San Diego) uncovered single-cell changes in pancreatic cells from T1D pancreases using advanced genomic methods.
- Mohammad Haj Dezfulian, Ph.D. (University of Pennsylvania) mapped T1D antigens contributing to autoimmunity by taking a closer look at T cells, which play a role in destroying insulin-producing beta cells.
- Remi Creusot, Ph.D. (Columbia University) presented on a different approach to retraining the immune system to ignore beta cells, starting with precursors to immune cells.
- Together, these studies are deepening our understanding of how and where the immune system attacks insulin-producing beta cells in T1D—and uncovering new ways to retrain it.
Disease-Modifying Therapies Highlight: Research Supported by Breakthrough T1D or the T1D Fund
Kenneth Brayman, M.D., Ph.D., FACS (University of Virginia) presented work on two Breakthrough T1D-funded projects. The first centered around the preclinical optimization of a potential immune therapy for T1D called IgM. Dr. Brayman and his team found that this therapy can retrain the immune system to ignore insulin-producing beta cells in mouse models of T1D, and he expanded on the mechanisms by which this happens. In humans, this could be another way to promote beta cell survival.
The second study that Dr. Brayman presented, which is funded by Breakthrough T1D in conjunction with his collaborator Gordon Laurie, Ph.D. (University of Virginia), focused on a new potential drug called N-104, which mimics a compound that was found to be decreased in people with T1D. The data presented show that, in mouse models, N-104 may suppress autoimmunity while simultaneously promoting beta cell regeneration—marking a new potential DMT worth exploring further.
Christoph Bausch, Ph.D. (SAB Biotherapeutics, a T1D Fund portfolio company) presented data from the phase 1 study of SAB-142, a humanized ATG. This potential DMT preserved C-peptide, improved time in range, and reduced insulin therapy use. Even more, it can be safely re-dosed with mild side effects related to the infusion procedure. Next up is the phase 2b SAFEGUARD study, which is currently enrolling and will further explore the safety and efficacy of SAB-142. The ultimate goal is to delay or halt T1D progression.
Alok Joglekar, Ph.D. (University of Pittsburgh) presented on a novel DMT approach that involves engineering different types of T cells in the body to suppress self-reactive T cells that are causing destruction of insulin-producing beta cells. His approach is designed to be antigen-specific, meaning selectively shutting down only the beta-cell-destroying T cells while leaving the rest of the immune system intact.

Key Takeaways
Understanding the key immune mechanisms underlying T1D pathogenesis is a major focus of T1D researchers, and they are turning this knowledge into novel strategies for potential DMTs. To expedite DMT clinical trials, time to minimal residual C-peptide may be a clinically meaningful measure of beta cell preservation. Real-world data about who is initiating Tzield treatment—and when—is providing HCPs with important information about the pathway to Tzield initiation in routine clinical practice.
Early Detection
Clinical Implementation of Pediatric T1D Screening and Monitoring
- Presenter: Sarah Lydia Holly, BSN, RN (Children’s National Hospital)
- Six pediatric endocrinology centers worked together to increase T1D screening and monitoring rates in kids through quality improvement and operational strategies.
- Between June 2024 to February 2026, the teams implemented patient and HCP education strategies, integration of screening and monitoring in clinical workflows, defined pathways for follow-up, and multidisciplinary coordination.
- The teams exceeded their goal and screened 1700+ people. No cases of diabetic ketoacidosis (DKA) reported, 85% engaged in long-term monitoring, and 73% were offered Tzield.
- This study demonstrates the feasibility of screening and monitoring in routine pediatric care, and this can facilitate early intervention and DKA prevention.
Early Detection Highlight: Breakthrough T1D Staff
Raquel Lopez Diez, Ph.D., Senior Scientist, hosted a Breakthrough T1D Reception for the T1D Genetic Risk Score (GRS) Consortium. The session brought together investigators and collaborators to discuss upcoming projects and future directions related to the T1D GRS Consortium, with dedicated conversations around genetics in non-European ancestry populations and adult-onset disease. The attendees exchanged ideas, identified areas for collaboration, and shaped priorities for the Consortium moving forward.
Key Takeaways
Screening and Early Detection has proven benefits, and the more people screened, the more people can avoid DKA at diagnosis, take advantage of a therapy to delay onset, and more. This is a major priority for Breakthrough T1D, and we support general population screening efforts.
Improving Lives
Discontinuation of Roche’s Dual GLP-1/GIP Receptor Agonist for T1D
- Presenter: Jeremy Pettus, M.D. (University of California, San Diego)
- Roche conducted a phase 2 clinical trial to evaluate changes in glycemic control in overweight or obese adults with T1D treated with their drug acmopatide (CT-868).
- People treated with acmopatide demonstrated reduced HbA1c levels, weight, insulin dose, and blood pressure compared to placebo.
- Despite these improvements, Roche decided to discontinue research into acmopatide and abandon plans for a phase 3 clinical trial.
- However, there are other companies studying GLP-1s in people with T1D. For example, Lilly has an ongoing clinical trial that is fully enrolled. Learn more below.
GLP-1/GIP Receptor Agonists: The Good News
Eli Lilly’s phase 3 trials for tirzepatide for glycemic control in adults with T1D and obesity or overweight (SURPASS-1-T1D and SURPASS-2-T1D) are fully enrolled, with results expected in the coming months. The Breakthrough T1D-funded ADJUST-T1D trial demonstrated glycemic and metabolic benefits for people with T1D and obesity or overweight using an AID system treated with semaglutide. A few days ago, top experts in the field published a consensus on safe use of this class of drugs in the T1D population—including authorship by Brynn Marks, M.D., Senior Director of Medical Affairs—which means that we are providing healthcare professionals (HCPs) with the education needed to bring these therapies safely to the T1D community (more to come on this later). We and others will continue to push for additional research solidifying the safety and efficacy of GLP-1/GIP receptor agonists and advocate for approval for the T1D community.
GLP-1 Receptor Agonists for Kids
- Presenter: Michelle Van Name, M.D. (Yale University)
- There is clear evidence in adults with T1D that GLP-1 receptor agonists can improve weight and glycemic control and reduce the risk of heart and kidney complications, and more clinical evidence is needed for the adolescent population.
- Adolescents with T1D could benefit from this class of drugs because they tend to have insulin resistance and live with overweight or obesity, and those who develop T1D earlier in life have a greater lifetime risk of long-term complications.
- Currently enrolling clinical trials (T1-DISCO and Obesity Complicating T1D: GLP-1 Analogue Anti-Obesity Treatment) in young adults living with T1D and obesity are investigating the impacts of GLP-1s on cardiovascular outcomes.
- Dr. Van Name’s mentor was Bill Tamborlane, M.D., a long-time champion for the T1D community and Breakthrough T1D supporter who recently passed away.

Improving Lives Highlight: Breakthrough T1D-Funded Researchers and Breakthrough T1D Staff
Richard Pratley, M.D. (Advent Health) presented on the unique needs of the heterogenous population of older people living with T1D. It can be especially challenging for HCPs to set glycemic targets because of variable life expectancies, lifestyle differences, presence of other health issues, and a lack of evidence surrounding blood glucose management for this population. Dr. Pratley recommends that goals for glycemic targets in older adults with T1D should be individualized, and T1D technology can significantly reduce hypoglycemic events. And he emphasized an important point—there aren’t enough therapies to reduce the risk of heart and kidney complications, which older adults are especially vulnerable for. Dr. Pratley is executing a Breakthrough T1D-funded clinical trial to repurpose cardiorenal drugs that work in T2D for T1D.
Viral Shah, M.D., a Breakthrough T1D-funded researcher, presented an evidence synthesis on ketone monitoring and treatment, which was co-authored by experts in the field including our Vice President of Medical Affairs, Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES. The team collected real-world or hypothetical clinical situations related to DKA to create a framework that HCPs can follow to determine the best course of action. This includes considering who is the intended population for ketone monitoring, when and how to check ketones, defining clinical parameters for elevated ketones, and follow-up steps for management. This effort is critically important because rates of DKA are increasing around the globe, as detailed in the preceding presentation by Guillermo Umpierrez, M.D. Ketone management is a Breakthrough T1D priority, and our Medical Affairs team previously spearheaded a publication outlining international expert recommendations on continuous ketone monitoring in T1D.
Dr. Albanese-O’Neill and Jonathan Rosen, Ph.D., Director of Research, were co-authors on two posters reporting on a multinational survey of adults using T1D technology with severe hypoglycemia exploring how they are doing in their daily lives. The participants reported sub-optimal health and significant impairments in productivity, highlighting the remaining unmet needs for the T1D community despite recent advances—showcasing why the work we do to improve the lives of those living with T1D is so critically important.

Key Takeaways
GLP-1s are top of mind for researchers—they have proven benefits for adults with T1D, and ongoing clinical trials will provide more evidence for their use in younger populations. We need to do more for older adults with T1D, from individualized approaches to glycemic targets to developing more therapies to prevent heart and kidney complications. Last but not least, DKA rates are increasing around the world, and Breakthrough T1D is actively involved in efforts to guide HCPs on ketone management—which is especially important with continuous ketone monitoring on the horizon.

Look out for another article soon wrapping up days 3 and 4 of ADA 2026!

