
People living with type 1 diabetes (T1D) need to check their blood sugar levels on a regular basis. Without regular checks during both the day and night, blood sugars may get too high (hyperglycemia) or too low (hypoglycemia). While some people opt to monitor their blood sugar (glucose) levels through finger pricks, others choose to use technology like continuous glucose monitors (CGMs).
CGMs are wearable devices that measure glucose levels every one to five minutes and help people with T1D determine if they need to take immediate action to manage their diabetes. CGMs can also help to identify long-term patterns in glucose levels that can be used to adjust diabetes management plans. Through connected apps, CGMs can often generate a full picture of a person’s glucose trends, from current and average levels to increasingly important metrics like time in range. Read on to learn about the power of time in range—what it is, why it matters, and future applications.
What is Time in Range?
Time in Range
Time in range is the percentage of time per day spent within the range of 70 and 180 milligrams of glucose per deciliter of blood (mg/dL).
Time in range is used by people with T1D and their care teams to see how often glucose levels are within the recommended range. Current standards of care recommend that most people with T1D aim for the following targets:
| Glucose levels (mg/dL) | Percent of time per day spent | |
|---|---|---|
| Time Above Range | Greater than 180 | Less than 25% |
| Time in Range | 70-180 | 70% |
| Time Below Range | Less than 70 | 4% or less |
| Less than 54 | 1% or less |
While each person has different glucose targets, most people living with T1D should aim to have their glucose levels in the recommended range, which is considered safe and healthy for most. People with T1D should work closely with their healthcare teams to review CGM data and create personalized high and low alerts, which often change based on time since T1D diagnosis, age, complications, hypoglycemia unawareness, pregnancy, and more.
CGMs also produce 24-hour graphs (as shown in the figure below), which show whether glucose levels are in, above, or below range at different time points throughout the day. Since glucose levels can change day to day, healthcare teams generally review patterns over a 14-day period. Percentage of time spent in, above, or below range coupled with the 24-hour graph are especially helpful in identifying glucose patterns according to time of day.

Time in Range Versus HbA1c
Time in range and 24-hour CGM graphs paint a picture of a person’s glucose patterns throughout the day. People can choose how many days of CGM data they want to review, and reviewing a specific period of time may help individuals better understand how diet, exercise, and illness affect glucose levels. On the other hand, HbA1c is measured through a blood test that reports average blood sugar levels over the previous 2-3 months. Healthcare professionals (HCPs) often use both time in range and HbA1c measurements to get a comprehensive picture of a person’s glucose levels and make the most informed care decisions possible.
Why Time in Range is Important?
The most important feature of time in range (and CGM data) is that it can provide people living with T1D with an extensive overview of how and when their glucose levels change throughout the day. Blood sugars can change based on exercise, meals, stress, hormones, and more—and time in range can help people understand how lifestyle factors come into play for their personal blood sugar management.
“Time in range helps people with T1D better understand glucose patterns that are not captured by HbA1c,” explains Brynn E. Marks, M.D., MSHPEd, Senior Director of Medical Affairs at Breakthrough T1D. “Additionally, CGM can help people to review their glucose patterns in between visits with their diabetes team and allow for more frequent adjustments to their insulin doses. Reviewing and acting on time in range data and glucose patterns identified by CGM can empower people to manage their T1D and to avoid the roller coasters of managing high and low blood glucose that negatively impact quality of life.”
Spending more time in range is becoming increasingly associated with a lower risk of developing complications, although further research is needed to better understand this connection. Time in range is also often used as an outcome measurement in clinical trials to help researchers understand if a new therapy or treatment is improving blood sugar management. So, the benefits of time in range go beyond personal blood sugar trends, and as we continue to improve our understanding of this metric, its applicability in research and beyond will continue to broaden.
What’s Next for Time in Range
Time in Tight Range
Time in tight range, which is also sometimes referred to as time in normal glycemia, is defined as the percentage of time spent with glucose levels between 70 to 140 mg/dL. People without diabetes have a time in tight range of about 96%. As diabetes therapies and technologies continue to advance, we are just beginning to understand the potential clinical benefits of aiming for a narrower glucose range in people with T1D. Researchers suspect that fluctuations outside in time in tight range may be a better predictor of complications risk. Yet, before we integrate time in tight range into clinical decisions, more research is needed to uncover the benefits of this metric and advance therapies and technologies that will allow people to achieve this narrower target without creating additional undo burden.
Automated Insulin Delivery Systems in Clinical Trials
Diabetes technology has advanced tremendously in the past few decades, largely driven by Breakthrough T1D. Right now, we have automated insulin delivery (AID) systems that can automatically increase or decrease insulin delivery based on CGM readings. These AID systems help to improve time in range and time in tight range while decreasing high and low blood sugar levels, but meal announcements are still required. Fully closed loop systems in the pipeline will not require mealtime announcements. This next-generation technology has the potential to help people achieve time in range targets while using less effort to manage T1D. Breakthrough T1D is funding studies to drive innovation in fully closed-loop systems and bring newer generations to the T1D community quickly and safely.
Non-Insulin Therapies
Therapies used alongside insulin and AID systems have the potential to improve both blood sugar levels and metabolic health. Breakthrough T1D is funding studies investigating treatments that can address insulin resistance, weight management, hypoglycemia, and long-term complications. The goal is to customize treatment approaches and ensure that the T1D community can choose from multiple drugs that may best manage blood sugars and overall health.
GLP-1 in Clinical Trials
The Breakthrough T1D-funded ADJUST-T1D clinical trial showed that the GLP-1 receptor agonist semaglutide (Ozempic) can improve blood sugar and weight outcomes in adults living with T1D and overweight or obesity. After 26 weeks, people treated with semaglutide showed greater improvements in both time in range and time in tight range compared to those who received the placebo. This study has provided evidence for the potential of this class of drugs to benefit the T1D community, and Breakthrough T1D is continuing to drive research into this area.
While exciting advancements in treatments and devices are coming down the pike, many people living with T1D are still unable to reach time in range goals with the tools currently available. Access to improved technologies and non-insulin therapies that can help people with T1D achieve optimal glucose targets will make it possible to use time in tight range goals as the standard of care. Because glucose targets are personalized, time in tight range may not be the right metric for everyone, and more research is needed to see which populations may benefit the most. In the meantime, Breakthrough T1D is working tirelessly to improve the lives of the T1D community, help people achieve the best blood sugar management possible with the options available now, and accelerate the next breakthroughs through the pipeline.

“In the future, I think we will see greater use of time in range in T1D management by people with T1D and care providers as adoption of CGM continues to increase. A growing body of evidence suggests that greater time in range, like low HbA1c, is associated with a lower risk of developing long-term complications. These data might not only support CGM use and attention to time in range in clinical decision-making, but may also impact the way new therapies are evaluated. Today, time in range is widely accepted as a means to evaluate AID systems, but we are not there yet when it comes to evaluating new drugs. Finally, there is a lot of ongoing research to understand time in tight range and how this will help us with clinical guidance and therapy development in the future.”
-Jonathan Rosen, Ph.D., Director of Research at Breakthrough T1D
Improving the Lives of the T1D Community
The goal of Breakthrough T1D’s Improving Lives Program is to ensure that people with T1D have the highest quality of life possible while cures are on the way. We are actively supporting research to drive innovation in technology and devices and understand how new and repurposed medications can improve blood sugar levels, reduce the risk of long-term complications, and benefit overall health. We are clearing approval and coverage pathways for these advancements through our advocacy work and enhancing clinical adoption of devices to improve blood sugar management in more people than ever. Until cures are widely available, Breakthrough T1D will continue to improve the lives of those living with T1D now.
They’re all over the news: Ozempic ®. Trulicity ®. Jardiance ®. Mounjaro ™. And more.
These drugs are all approved for glucose control in type 2 diabetes (T2D). Some of them also have additional indications reflecting their demonstrated benefits for cardiovascular disease, kidney health, and obesity.
None of these drugs are currently approved for glucose control in people with type 1 diabetes (T1D). However, a recent consensus report addressed the growing interest in GLP-1 receptor agonists as an adjunctive therapy for T1D and their “potential to improve glycemic and metabolic outcomes without increasing the risk of severe hypoglycemia or diabetic ketoacidosis.”
Let’s examine GLP-1 therapies and SGLT inhibitors and consider how drugs like Ozempic may one day help people with type 1 diabetes.
GLP-1 therapies
GLP-1 (glucagon-like peptide-1) receptor agonists work in multiple ways to control blood glucose and obesity. They block the release of glucagon, stimulate insulin production, slow the rate at which your stomach empties, and increase the sensation of feeling full. They are usually injected, but oral versions are available.
In people with T2D, this class of drugs lowers blood sugar levels and, for most people, causes weight loss. GLP-1 therapies have also been shown to reduce the risk of long-term cardiovascular complications often experienced by people with T2D, such as heart attack and stroke.
GLP-1 drugs include Ozempic/Rybelsus/Wegovy (semaglutide), Trulicity (dulaglutide), Victoza (liraglutide), and Mounjaro (tirzepatide), among others.
When GLP-1 treatments hit the market in the early 2000s, Breakthrough T1D and others funded several clinical trials to test whether GLP-1 receptor agonists, in addition to insulin, improved outcomes for people with type 1 diabetes. While some of these studies showed that the addition of GLP-1 therapies to insulin led to improvements in HbA1c, total insulin dose, and weight, the benefits were relatively modest and accompanied by some side effects like hypoglycemia (low blood sugar). As a result, these studies did not lead to GLP-1 receptor agonists being highly adopted for use by people with T1D.
However, these trials were done with older GLP-1 drugs. We are investigating whether the newest, most advanced GLP-1 therapies (like Ozempic) will improve the health of people living with type 1 diabetes. (See below!)
Consensus report on safe use of GLP-1 medications in T1D
Despite the fact that GLP-1 receptor agonists (and dual GLP-1/GIP receptor agonists) are not FDA-approved for use in T1D for any indication, people with T1D are still able to access these drugs since they are approved to treat obesity and overweight. Until now, HCPs have not had clear guidance around safe use for this class of drugs in people living with T1D.
Thanks to the diaTribe Foundation, including co-authorship by Brynn Marks, M.D. (Senior Director of Medical Affairs), we now have a consensus report featuring recommended expert guidelines for how HCPs and people with T1D can safely use GLP-1 medications alongside insulin therapy. This includes considerations around insulin dosing and continuous glucose monitor (CGM) adjustments, ketone management, monitoring and mitigating side effects (especially gastrointestinal) and complications like eye disease, and more. The idea is to support safe, individualized care for people living with T1D who may benefit from these medications.
This report also provides an overview of evidence around benefits of GLP-1 medications in T1D populations based on real-world and clinical trial data. Ongoing and future large-scale clinical trials are needed to provide additional data supporting the use of these drugs in people with T1D. Until then, both HCPs and T1D community members have a tangible resource for important considerations around using GLP-1 drugs safely. Consensus reports are a key step in driving clinical adoption of these therapies if they become FDA-approved for T1D in the future, and Breakthrough T1D endorses this report alongside five international diabetes organizations.
If you are living with T1D, consider talking to your healthcare team about the potential benefits of GLP-1 medications and see if they could be a fit for you.
SGLT inhibitors
SGLT (sodium-glucose co-transporter) inhibitors are oral medications for people with T2D that lower blood sugar by preventing the kidneys from reabsorbing glucose, leading to the excretion of sugar through the urine.
In addition to improving blood sugar for people with and without T2D, these drugs also provide benefits such as weight loss, blood pressure reduction, and transformative benefits to the heart and kidneys.
SGLT drugs include Jardiance (empagliflozin), Farxiga (dapagliflozin), and Invokana (canagliflozin), among others. The SGLT inhibitors empagliflozin and dapagliflozin are approved to treat chronic kidney disease and heart failure, regardless of diabetes status.
Yet, increased risk of diabetic ketoacidosis (DKA) in people with T1D limits the use of these therapies to improve blood sugar management or reduce the risk of complications. A key Breakthrough T1D priority is to find ways to mitigate this risk so people with T1D can also take advantage of the benefits of SGLT inhibitors.
Breakthrough T1D-funded research in GLP-1 and SGLT therapies
Breakthrough T1D has a long history with GLP-1 medications like Ozempic. In the 1980s, Breakthrough T1D-funded researcher Pauline Kay Lund, Ph.D., was the first to clone the hormone glucagon and discover two new hormones, one of which was GLP-1.
Today, there is real-world evidence of GLP-1 receptor agonists improving the lives of people with type 1 diabetes.
Real-world evidence
Observational studies using historical patient data from electronic health records (not randomized clinical trials) that can give an idea if a drug might be beneficial or not for a certain indication.
Evidence demonstrates that semaglutide (Ozempic) or tirzepatide (Mounjaro) have the potential to lower A1c, increase time-in-range, and reduce the amount of daily insulin needed in people with T1D. More research is needed in this area. That’s where Breakthrough T1D comes in!
Most recently, the Breakthrough T1D-funded ADJUST-T1D clinical trial showed that, in people with T1D and obesity or overweight using an automated insulin delivery system, Ozempic can help manage both weight and blood sugar.
Additional Breakthrough T1D-funded research on GLP-1 and SGLT therapies is investigating the benefits of these drugs for people with T1D, including reducing the risk of common complications of type 1 diabetes like cardiovascular disease and kidney disease.
Snapshot of active clinical trials in GLP-1 and SGLT therapies
Here are a few examples of Breakthrough T1D-funded clinical trials in GLP-1 and SGLT therapies that are currently underway:
| Clinical Trial Name | Study Details |
|---|---|
| REMODEL T1D | Determine whether semaglutide (Ozempic) protects the kidneys in those living with T1D. |
| Triple Therapy in T1DM | Assess whether the addition of dapagliflozin (Farxiga) to semaglutide (Ozempic) and insulin improves glycemic control in those living with T1D. |
| SUGARNSALT | Determine the effectiveness and safety of sotagliflozin (Inpefa) in slowing kidney function decline in those living with T1D and moderate to severe diabetic kidney disease. |
| Dapagliflozin + Pioglitazone in T1D | Examine how adding dapagliflozin (Farxiga) and pioglitazone (Actos) to insulin therapy affects glucose control and ketone concentration in people living with T1D. |
Our commitment to improving lives
Breakthrough T1D strives to improve health outcomes in people living with type 1 diabetes. Insulin therapy alone is often not enough for people with T1D to achieve glucose and metabolic control. The use of adjunctive drugs that complement insulin therapy can help. Since the FDA has already approved these medications for treating other conditions, positive results from these clinical trials could speed up the adaptation of these therapies for people living with T1D.
Learn more about clinical trials and how they are advancing breakthroughs for the T1D community.
ADA’s 86th Scientific Sessions
This event is one of the largest diabetes conferences in the world, bringing together over 11,000 attendees to share and learn about cutting-edge research and advancements toward cures. Each year, Breakthrough T1D-funded researchers highlight their work, demonstrating the progress we’re making toward achieving our mission. Leading experts will present over 100 studies spanning cell therapies, disease-modifying therapies (DMTs), diabetes technology, treatments, and more!
Reporting live from New Orleans, LA! Breakthrough T1D is on site at ADA 2026 with leading scientists, clinicians, healthcare professionals, industry partners, and more to hear about exciting updates in type 1 diabetes (T1D) research—including work supported by Breakthrough T1D.
Read on for everything you need to know from the first two days ADA 2026, including key takeaways from panels and sessions featuring Breakthrough T1D staff and noteworthy highlights from Breakthrough T1D-funded researchers—both past and present—whose work was front-and-center.
Check out the updates from days 1 and 2 across Cures and Improving Lives!
Cell Therapies: Breakthrough T1D Staff at the Forefront
Sanjoy Dutta. Ph.D., Chief Scientific Officer, participated in a panel discussion about advancing manufactured islet cell therapies for widespread clinical use. A major theme was that eligibility requirements for clinical trials are too narrow—which means that less people have the chance to benefit and trials don’t progress as quickly. Patient-reported outcomes will be important to demonstrate to regulators that many people with T1D can and want to benefit from islet cell replacement therapy, and we need established, systemic methods in place to take the T1D community’s opinions into account.
The panelists also discussed the current challenges surrounding immunosuppression, which is one of the barriers to clinical trial participation, and ongoing efforts to develop novel cell protection strategies. Immunotherapies in development for early-stage T1D may be applicable in islet cell transplant settings, including approaches that retrain the immune system to ignore beta cells—an area that Breakthrough T1D is invested in.
To accelerate progress in manufactured islet cell therapies, the panelists agreed that the top priorities are:
- More companies exploring novel approaches
- Expanding eligibility criteria for trials—and incoporating the perspectives of the T1D community into regulatory decisions—so we can build more evidence around the safety and efficacy of manufactured islet cell therapies
- Additional frameworks to help guide the field, like our cell therapies roadmap and upcoming publications from Breakthrough T1D staff around manufacturing and preclinical considerations
- Optimizing manufacturing processes to reduce costs and ensure access for people who want these therapies
- Optimizing cell therapy products by reducing or eliminating the need for immunosuppression and finding the best transplant site for survival

Brynn Marks, M.D., Senior Director of Medical Affairs, chaired a session about the promise and perspective of islet cell replacement therapies for kids with T1D. Notably, Melena Bellin, M.D. (University of Minnesota) spoke about insights from children with pancreatitis who require full pancreas removal and receive transplants of their own healthy islet cells into their livers. In comparison to adults, children who receive this type of dual transplant have higher rates of islet survival and function and are more likely to stop needing external insulin. Laura Jacobsen, M.D. (University of Florida) spoke about practical clinical expectations for cell therapies and DMTs based on the data we have in adults and what this might mean for kids. Finally, Jane Speight, Ph.D. (The Australian Center of Behavioral Research in Diabetes) closed out with a talk about psychosocial considerations for pediatric islet cell transplantation.

Key Takeaways
The data surrounding islet cell therapies is very exciting, but we have more work to do until manufactured products are accessible to everyone with T1D who may want them. We are at the very beginning of considering what these therapies might look like in the pediatric T1D population.
Disease-Modifying Therapies
C-peptide
C-peptide is a biomarker of the body’s insulin production, which can be measured easily by a blood test. It’s formed when pro-insulin is cleaved into active insulin and C-peptide.
The Potential for a New and Improved C-Peptide
- Presenter: Samuel Sangqu Wu, Ph.D. (University of South Florida)
- C-peptide has the potential to be a validated endpoint for DMT clinical trials, and researchers like Dr. Wu are looking into new ways to help make this possible.
- Time to minimal residual C-peptide (TMRCP) is defined by how much longer people will have measurable C-peptide—meaning how long they will continue to make insulin.
- Dr. Wu applied this metric to six TrialNet studies and found that extrapolating TMRCP identified the same treatments as effective as each original analysis.
- TMRCP may be another metric to define the clinical meaningfulness of C-peptide, meaning it could be an alternative endpoint to consider for future DMT trials.
- Breakthrough T1D supported these efforts.
TEPLI-REAL: Evaluating Real-World Outcomes of People Treated with Tzield
- Presenter: Stephen Gitelman, M.D. (University of California, San Francisco)
- The purpose of this study was to understand populations who pursue treatment with Tzield and post-treatment outcomes through review of electronic health records.
- Diagnosis of T1D is heterogeneous, with people having either autoantibodies or dysglycemia (abnormal blood sugar) detected first, or others having both detected at the same time.
- These diagnostic pathways influence Tzield initiation. Those who had dysglycemia and autoantibodies detected at the same time had the shortest median time to start treatment.
- Most people who initiated Tzield were adolescents, and 94% of people who started treatment completed the full 14-day course.
- This study offers important considerations for healthcare professionals (HCPs) regarding how T1D diagnosis influences Tzield treatment in routine practice.
Decoding Immune Mechanisms and Engineering the Immune System in T1D
- Todd Brusko, Ph.D. (University of Florida) presented on spatial locations of different immune cells that contribute to the autoimmune process in T1D pancreases—and the underlying mechanisms that influence this.
- Kyle Gaulton, Ph.D. (University of California, San Diego) uncovered single-cell changes in pancreatic cells from T1D pancreases using advanced genomic methods.
- Mohammad Haj Dezfulian, Ph.D. (University of Pennsylvania) mapped T1D antigens contributing to autoimmunity by taking a closer look at T cells, which play a role in destroying insulin-producing beta cells.
- Remi Creusot, Ph.D. (Columbia University) presented on a different approach to retraining the immune system to ignore beta cells, starting with precursors to immune cells.
- Together, these studies are deepening our understanding of how and where the immune system attacks insulin-producing beta cells in T1D—and uncovering new ways to retrain it.
Disease-Modifying Therapies Highlight: Research Supported by Breakthrough T1D or the T1D Fund
Kenneth Brayman, M.D., Ph.D., FACS (University of Virginia) presented work on two Breakthrough T1D-funded projects. The first centered around the preclinical optimization of a potential immune therapy for T1D called IgM. Dr. Brayman and his team found that this therapy can retrain the immune system to ignore insulin-producing beta cells in mouse models of T1D, and he expanded on the mechanisms by which this happens. In humans, this could be another way to promote beta cell survival.
The second study that Dr. Brayman presented, which is funded by Breakthrough T1D in conjunction with his collaborator Gordon Laurie, Ph.D. (University of Virginia), focused on a new potential drug called N-104, which mimics a compound that was found to be decreased in people with T1D. The data presented show that, in mouse models, N-104 may suppress autoimmunity while simultaneously promoting beta cell regeneration—marking a new potential DMT worth exploring further.
Christoph Bausch, Ph.D. (SAB Biotherapeutics, a T1D Fund portfolio company) presented data from the phase 1 study of SAB-142, a humanized ATG. This potential DMT preserved C-peptide, improved time in range, and reduced insulin therapy use. Even more, it can be safely re-dosed with mild side effects related to the infusion procedure. Next up is the phase 2b SAFEGUARD study, which is currently enrolling and will further explore the safety and efficacy of SAB-142. The ultimate goal is to delay or halt T1D progression.
Alok Joglekar, Ph.D. (University of Pittsburgh) presented on a novel DMT approach that involves engineering different types of T cells in the body to suppress self-reactive T cells that are causing destruction of insulin-producing beta cells. His approach is designed to be antigen-specific, meaning selectively shutting down only the beta-cell-destroying T cells while leaving the rest of the immune system intact.

Key Takeaways
Understanding the key immune mechanisms underlying T1D pathogenesis is a major focus of T1D researchers, and they are turning this knowledge into novel strategies for potential DMTs. To expedite DMT clinical trials, time to minimal residual C-peptide may be a clinically meaningful measure of beta cell preservation. Real-world data about who is initiating Tzield treatment—and when—is providing HCPs with important information about the pathway to Tzield initiation in routine clinical practice.
Early Detection
Clinical Implementation of Pediatric T1D Screening and Monitoring
- Presenter: Sarah Lydia Holly, BSN, RN (Children’s National Hospital)
- Six pediatric endocrinology centers worked together to increase T1D screening and monitoring rates in kids through quality improvement and operational strategies.
- Between June 2024 to February 2026, the teams implemented patient and HCP education strategies, integration of screening and monitoring in clinical workflows, defined pathways for follow-up, and multidisciplinary coordination.
- The teams exceeded their goal and screened 1700+ people. No cases of diabetic ketoacidosis (DKA) reported, 85% engaged in long-term monitoring, and 73% were offered Tzield.
- This study demonstrates the feasibility of screening and monitoring in routine pediatric care, and this can facilitate early intervention and DKA prevention.
Early Detection Highlight: Breakthrough T1D Staff
Raquel Lopez Diez, Ph.D., Senior Scientist, hosted a Breakthrough T1D Reception for the T1D Genetic Risk Score (GRS) Consortium. The session brought together investigators and collaborators to discuss upcoming projects and future directions related to the T1D GRS Consortium, with dedicated conversations around genetics in non-European ancestry populations and adult-onset disease. The attendees exchanged ideas, identified areas for collaboration, and shaped priorities for the Consortium moving forward.
Key Takeaways
Screening and Early Detection has proven benefits, and the more people screened, the more people can avoid DKA at diagnosis, take advantage of a therapy to delay onset, and more. This is a major priority for Breakthrough T1D, and we support general population screening efforts.
Improving Lives
Discontinuation of Roche’s Dual GLP-1/GIP Receptor Agonist for T1D
- Presenter: Jeremy Pettus, M.D. (University of California, San Diego)
- Roche conducted a phase 2 clinical trial to evaluate changes in glycemic control in overweight or obese adults with T1D treated with their drug acmopatide (CT-868).
- People treated with acmopatide demonstrated reduced HbA1c levels, weight, insulin dose, and blood pressure compared to placebo.
- Despite these improvements, Roche decided to discontinue research into acmopatide and abandon plans for a phase 3 clinical trial.
- However, there are other companies studying GLP-1s in people with T1D. For example, Lilly has an ongoing clinical trial that is fully enrolled. Learn more below.
GLP-1/GIP Receptor Agonists: The Good News
Eli Lilly’s phase 3 trials for tirzepatide for glycemic control in adults with T1D and obesity or overweight (SURPASS-1-T1D and SURPASS-2-T1D) are fully enrolled, with results expected in the coming months. The Breakthrough T1D-funded ADJUST-T1D trial demonstrated glycemic and metabolic benefits for people with T1D and obesity or overweight using an AID system treated with semaglutide. A few days ago, top experts in the field published a consensus on safe use of this class of drugs in the T1D population—including authorship by Brynn Marks, M.D., Senior Director of Medical Affairs—which means that we are providing healthcare professionals (HCPs) with the education needed to bring these therapies safely to the T1D community (more to come on this later). We and others will continue to push for additional research solidifying the safety and efficacy of GLP-1/GIP receptor agonists and advocate for approval for the T1D community.
GLP-1 Receptor Agonists for Kids
- Presenter: Michelle Van Name, M.D. (Yale University)
- There is clear evidence in adults with T1D that GLP-1 receptor agonists can improve weight and glycemic control and reduce the risk of heart and kidney complications, and more clinical evidence is needed for the adolescent population.
- Adolescents with T1D could benefit from this class of drugs because they tend to have insulin resistance and live with overweight or obesity, and those who develop T1D earlier in life have a greater lifetime risk of long-term complications.
- Currently enrolling clinical trials (T1-DISCO and Obesity Complicating T1D: GLP-1 Analogue Anti-Obesity Treatment) in young adults living with T1D and obesity are investigating the impacts of GLP-1s on cardiovascular outcomes.
- Dr. Van Name’s mentor was Bill Tamborlane, M.D., a long-time champion for the T1D community and Breakthrough T1D supporter who recently passed away.

Improving Lives Highlight: Breakthrough T1D-Funded Researchers and Breakthrough T1D Staff
Richard Pratley, M.D. (Advent Health) presented on the unique needs of the heterogenous population of older people living with T1D. It can be especially challenging for HCPs to set glycemic targets because of variable life expectancies, lifestyle differences, presence of other health issues, and a lack of evidence surrounding blood glucose management for this population. Dr. Pratley recommends that goals for glycemic targets in older adults with T1D should be individualized, and T1D technology can significantly reduce hypoglycemic events. And he emphasized an important point—there aren’t enough therapies to reduce the risk of heart and kidney complications, which older adults are especially vulnerable for. Dr. Pratley is executing a Breakthrough T1D-funded clinical trial to repurpose cardiorenal drugs that work in T2D for T1D.
Viral Shah, M.D., a Breakthrough T1D-funded researcher, presented an evidence synthesis on ketone monitoring and treatment, which was co-authored by experts in the field including our Vice President of Medical Affairs, Anastasia Albanese-O’Neill, Ph.D., APRN, CDCES. The team collected real-world or hypothetical clinical situations related to DKA to create a framework that HCPs can follow to determine the best course of action. This includes considering who is the intended population for ketone monitoring, when and how to check ketones, defining clinical parameters for elevated ketones, and follow-up steps for management. This effort is critically important because rates of DKA are increasing around the globe, as detailed in the preceding presentation by Guillermo Umpierrez, M.D. Ketone management is a Breakthrough T1D priority, and our Medical Affairs team previously spearheaded a publication outlining international expert recommendations on continuous ketone monitoring in T1D.
Dr. Albanese-O’Neill and Jonathan Rosen, Ph.D., Director of Research, were co-authors on two posters reporting on a multinational survey of adults using T1D technology with severe hypoglycemia exploring how they are doing in their daily lives. The participants reported sub-optimal health and significant impairments in productivity, highlighting the remaining unmet needs for the T1D community despite recent advances—showcasing why the work we do to improve the lives of those living with T1D is so critically important.

Key Takeaways
GLP-1s are top of mind for researchers—they have proven benefits for adults with T1D, and ongoing clinical trials will provide more evidence for their use in younger populations. We need to do more for older adults with T1D, from individualized approaches to glycemic targets to developing more therapies to prevent heart and kidney complications. Last but not least, DKA rates are increasing around the world, and Breakthrough T1D is actively involved in efforts to guide HCPs on ketone management—which is especially important with continuous ketone monitoring on the horizon.

Look out for another article soon wrapping up days 3 and 4 of ADA 2026!
The FDA has approved Tandem’s Control-IQ+ technology for use in pregnancy with type 1 diabetes (T1D). This is the first-ever automated insulin delivery (AID) technology cleared in the U.S. for pregnancy with T1D—a major milestone for the T1D community!
What is an Automated Insulin Delivery (AID) System?
An AID system has three main components: an insulin pump, a continuous glucose monitor (CGM), and an algorithm that lets these components communicate with each other to determine the best insulin dose to help keep blood sugar in range.
Automated insulin delivery systems:
- Are used in place of multiple daily injections (MDI) of insulin
- Continuously measure blood-glucose levels and adjust insulin delivery automatically
- Give less insulin when blood sugar is low and more insulin when blood sugar is high
- Still require user input for meals and snacks and troubleshooting (called hybrid closed-loop)
- Have been shown to improve time-in-range
Tandem’s Control-IQ+ algorithm can be paired with the Tandem Mobi System or t:slim X2 insulin pump and is compatible with Dexcom’s G6/G7 and Abbott’s Freestyle Libre 3 Plus CGMs. Consider speaking with your healthcare provider if you are pregnant or planning to become pregnant to see if these options may be a fit for you.
Using Technology to Manage Type 1 Diabetes During Pregnancy
As your body changes during pregnancy, so does your T1D management. Technologies like automated insulin delivery systems can give you more real-time information about your blood-glucose levels and patterns, help keep you in a tighter range, and reduce the risk of hyperglycemia, hypoglycemia, and long-term complications.
The FDA’s decision to approve Control-IQ+ for pregnancy was based on the results from the CIRCUIT clinical trial. Pregnant women with type 1 diabetes who used Tandem’s Control-IQ+ technology spent around 3 more hours per day in the recommended blood sugar range for pregnancy (63-140 mg/dL) compared to those using a CGM and their usual method of insulin delivery (MDI or insulin pump). Even more, participants using Control-IQ+ had fewer low blood sugar events and less glycemic variability, and they reported better sleep quality.
Right now, less than half of pregnant individuals with T1D achieve 70% or more time in the pregnancy-specific blood sugar range. The approval of Control-IQ+ technology has the potential to change this—meaning healthier pregnancies for both babies and soon-to-be moms.

“During pregnancy, Control-IQ+ was a game-changer.
It helped me achieve more time in range, more predictable outcomes, and experience fewer highs and lows. It also reduced much of the mental burden and T1D-related anxiety that comes with having to constantly monitor and make adjustments, which allowed me to focus more on my overall health and my baby’s well-being. I’m grateful for Control-IQ+ helping me feel more confident and in control during my pregnancy and the healthy, safe delivery of my baby boy.”
Liz Walsh, Living with T1D for 35 years
Other Tips for a Healthy Pregnancy with T1D
Maintaining a healthy lifestyle can benefit both you and your baby throughout your pregnancy. There are extra considerations for pregnant individuals with T1D because changing hormone levels and insulin sensitivity throughout different stages of pregnancy can have significant impacts on blood sugar. Your insulin dose will likely increase during pregnancy, and using an AID system can help make this transition easier.
Work together with your healthcare team to track and manage your blood sugar levels and make the necessary lifestyle adjustments to have the safest and healthiest pregnancy possible—both before and during your pregnancy. This includes eating right, staying active, getting good sleep, monitoring for complications, and maintaining good mental health.

T1D Pregnancy Guide
Get guidance and support on all stages of pregnancy, from pre-pregnancy planning to juggling T1D as a new mom.
Accelerating T1D Research for Pregnancy and Beyond
Breakthrough T1D research grants supported the development of the Control-IQ+ algorithm, and our advocacy supported the Special Diabetes Program, which funded its clinical testing.
We continue to support research into fully closed-loop AID systems to remove the need for user input around meals and troubleshooting so blood sugar management can one day be easier than ever. The work doesn’t stop until pregnant individuals with T1D have more options and can choose the best AID system that works for them.
Right now, we’re funding a clinical trial that will adapt and evaluate the Loop algorithm (as part of the twiist AID system) for pregnant women with T1D. Another Breakthrough-T1D funded study is collecting data from pregnant women with T1D to better understand changes in insulin sensitivity throughout pregnancy. This will then be used to help develop AID systems capable of adapting to pregnancy-specific changes in insulin requirements.
By Sandy Vogt, Ph.D., and Kara Sweet
Partners in clinical trials
Clinical trials are key to bringing new treatments, therapies, and devices for type 1 diabetes (T1D) from the lab to the clinic. Pharmaceutical and biotech companies, which conduct research and help develop and manufacture new therapies, are a critical player in accelerating this process. Companies often partner with clinical researchers at medical centers and hospitals to test their new therapies through clinical trials. These collaborative partnerships are essential for new drugs to move through the pipeline and get to people with T1D.
Clinical trials terms you need to know
Sponsor
The trial sponsor is the person, organization or company that initiates, manages, and oversees a clinical trial, ensuring it is conducted ethically and safely.
Trial site
A trial site is the medical center, hospital, or clinic where clinical trial participants receive the study drug, treatment, or intervention and receive care throughout the duration of the trial.
Principal investigator
Within a particular trial site, the Principal Investigator (PI) is the lead researcher that oversees the trial and the research team. The PI ensures participant safety, supervises data collection and analysis, and maintains scientific and ethical integrity during the research process.
Spotlight on the CATT1 clinical trial
The CATT1 clinical trial is investigating whether cadisegliatin (TTP399), a glucokinase activator, can reduce hypoglycemic events (low blood sugars) in people with T1D when used alongside insulin therapy. Read on to learn more about the people making the CATT1 clinical trial happen, the science behind cadisegliatin, and how you can get involved.
The CATT1 clinical trial
Sponsor
vTv Therapeutics (a company with support from the T1D Fund: A Breakthrough T1D Venture)
Trial site spotlight
The University of North Carolina (UNC) Medical Center located in Chapel Hill, N.C.
Principal investigator spotlight
Klara Klein, M.D., Ph.D., Assistant Professor of Medicine and Director of the Endocrinology, Diabetes, and Obesity (EnDO) Clinical Research Unit (CRU) at the UNC School of Medicine, Division of Endocrinology and Metabolism
Clinical research team member spotlight
Alex Kass, MSN, MBA, RN, CDCES, Research Program Director for the EnDO CRU
Breakthrough T1D x vTv Therapeutics
Breakthrough T1D has a long-standing relationship with vTv Therapeutics. After partnering with Breakthrough T1D in 2017, vTv pivoted from type 2 diabetes to T1D. With Breakthrough T1D’s support, vTv launched a phase 2 clinical trial (SimpliciT1) investigating cadisegliatin as an adjunctive therapy for T1D, showing that it improved blood glucose control. Eager to keep the momentum going, the T1D Fund has supported vTv from early 2024 onwards, most recently participating in the company’s latest round of financing to continue to support the ongoing phase 3 trial for cadisegliatin in T1D.

“Breakthrough T1D has long been a supporter of adjunctive therapies, meaning medicines that can be taken alongside insulin to improve glucose control and other outcomes. Previous clinical trials have demonstrated the potential for cadisegliatin to reduce hypoglycemia and improve HbA1C in people with T1D, and we are excited to support the phase 3 program to advance this therapy toward the clinic where it can be used to address major unmet clinical needs in our community.”
Jonathan Rosen, Ph.D., Director of Research at Breakthrough T1D
Meet the team at UNC
Within the UNC Medical Center, the EnDO CRU is a hub for endocrinologists, clinical researchers, and other experts who work together to lead clinical studies at cutting edge facilities that help bring new transformative therapies to the people who need them most. Within the EnDO CRU, Dr. Klara Klein and Alex Kass are taking the lead on T1D clinical trials—a passion they both share for different reasons.
T1D has been on Dr. Klein’s mind since she was a little girl. “I grew up hearing about diabetes—my mom is an endocrinologist, and it was a frequent topic at the dinner table,” she said. After following in her mother’s footsteps and becoming an endocrinologist herself, Dr. Klein is shocked that insulin—which was discovered over 100 years ago—is still the gold standard for T1D management. In this sense, not much has changed since she was sitting at the dinner table with her parents.
This sentiment inspires her work. “I’ve always been struck by the daily challenges people with T1D face. Even with incredible advances in technology, managing T1D is a constant effort—every meal, every workout, every illness,” she explained. Her true passion is bringing new therapies to fruition that can ease the daily burden of living with T1D until everyone has access to cures. “Being part of research that could improve the lives of people living with diabetes in meaningful ways is both exciting and deeply rewarding.”
Dr. Klein is supported by a passionate and experienced team composed of five endocrinologist sub-investigators, a nurse coordinator, and a research assistant. She also works closely with Kass, who leads the operational side of many different trials within the EnDO CRU.
Kass is one of a few other staff on the team who is also living with T1D, giving him an inside perspective and inspiring his career to help people with diabetes live better lives. “Having type 1 diabetes myself has fueled my passion for both patient care and finding better treatment options,” he explained. “Together, our team’s mission is simple: to run high-quality studies that give people with diabetes access to promising therapies and make their day-to-day lives easier. This shared passion in our group inspires me!”
The team is working hard behind-the-scenes to recruit and care for participants of the CATT1 clinical trial, which is just one of the many studies they are running to help people with T1D.
Everything you need to know about the CATT1 clinical trial
The phase 3 CATT1 clinical trial is investigating whether cadisegliatin can reduce moderate to severe low blood sugar (hypoglycemic) events when used alongside insulin therapy over a period of six months. Hypoglycemia is the most common short-term complication of T1D, and we need to do more to help people with T1D manage their blood sugar to reduce dangerous lows. This clinical trial is trying to do just that.
Based on observations from previous clinical studies, cadisegliatin may be able to lower the risk of hypoglycemia. Participants in the phase 2 SimpliciT1 study showed clinically meaningful improvements in blood sugar control in addition to a 40% reduction in hypoglycemic events compared to the placebo. Nearly 600 participants have received cadisegliatin so far—it’s been well-tolerated and hasn’t increased the risk of diabetic ketoacidosis (DKA).
Unexpected clinical trial results
Sometimes, clinical trials have unexpected results. In this case, researchers may pivot to change the design of future trials to ensure they’re looking for the right thing. For cadisegliatin, earlier trials primarily looked at improvements in control of high blood sugar, but researchers noticed significant reductions in hypoglycemic events, too. Now, this is the primary outcome for the CATT1 trial—while this wasn’t the original intention, it’s the most clinically meaningful assessment for people with T1D.
Dr. Klein, Kass, and their team are actively recruiting for the CATT1 trial over the next three or so months.
Some key eligibility criteria are:
- Minimum of five years since T1D diagnosis
- At least one moderate to severe hypoglycemic event (Level 2 or 3) in the last two months prior to screening
- 18 years of age or older
- HbA1c levels < 9.5%
- Use of a continuous glucose monitor (CGM) for at least three months prior to screening (excluding closed-loop systems)
Clinical classification of hypoglycemic events
| Level | Severity | Blood glucose range and characteristics |
|---|---|---|
| 1 | Mild | 54 to 70 mg/dL |
| 2 | Serious/moderate or clinically significant | < 54 mg/dL |
| 3 | Severe | An altered mental and/or physical state requiring immediate assistance to prevent progression to loss of consciousness, seizure, coma, or death. |
Participants, investigators, and care providers will all be unaware of whether the participants are receiving cadisegliatin or the placebo, which will both be given orally. Participants can expect a combination of in-person and virtual visits over a 26-week period. During these visits, the clinical research team will check blood sugar levels, perform other lab tests to assess safety, and provide top-tier T1D care.
At UNC, for the entire length of the trial, participants will have access to a dedicated study team including a nurse coordinator, research assistant, and diabetes specialists. The clinical research team will guide participants through every step of the process—answering questions, reviewing results, providing support—so that people with T1D and their families can feel confident that they are in good hands.
Interested in participating?
Complete a pre-screener questionnaire to see if you qualify!
The science behind cadisegliatin
We know that cadisegliatin has been shown to reduce the risk of hypoglycemia in people with T1D (SimpliciT1 study). The next question is: how?
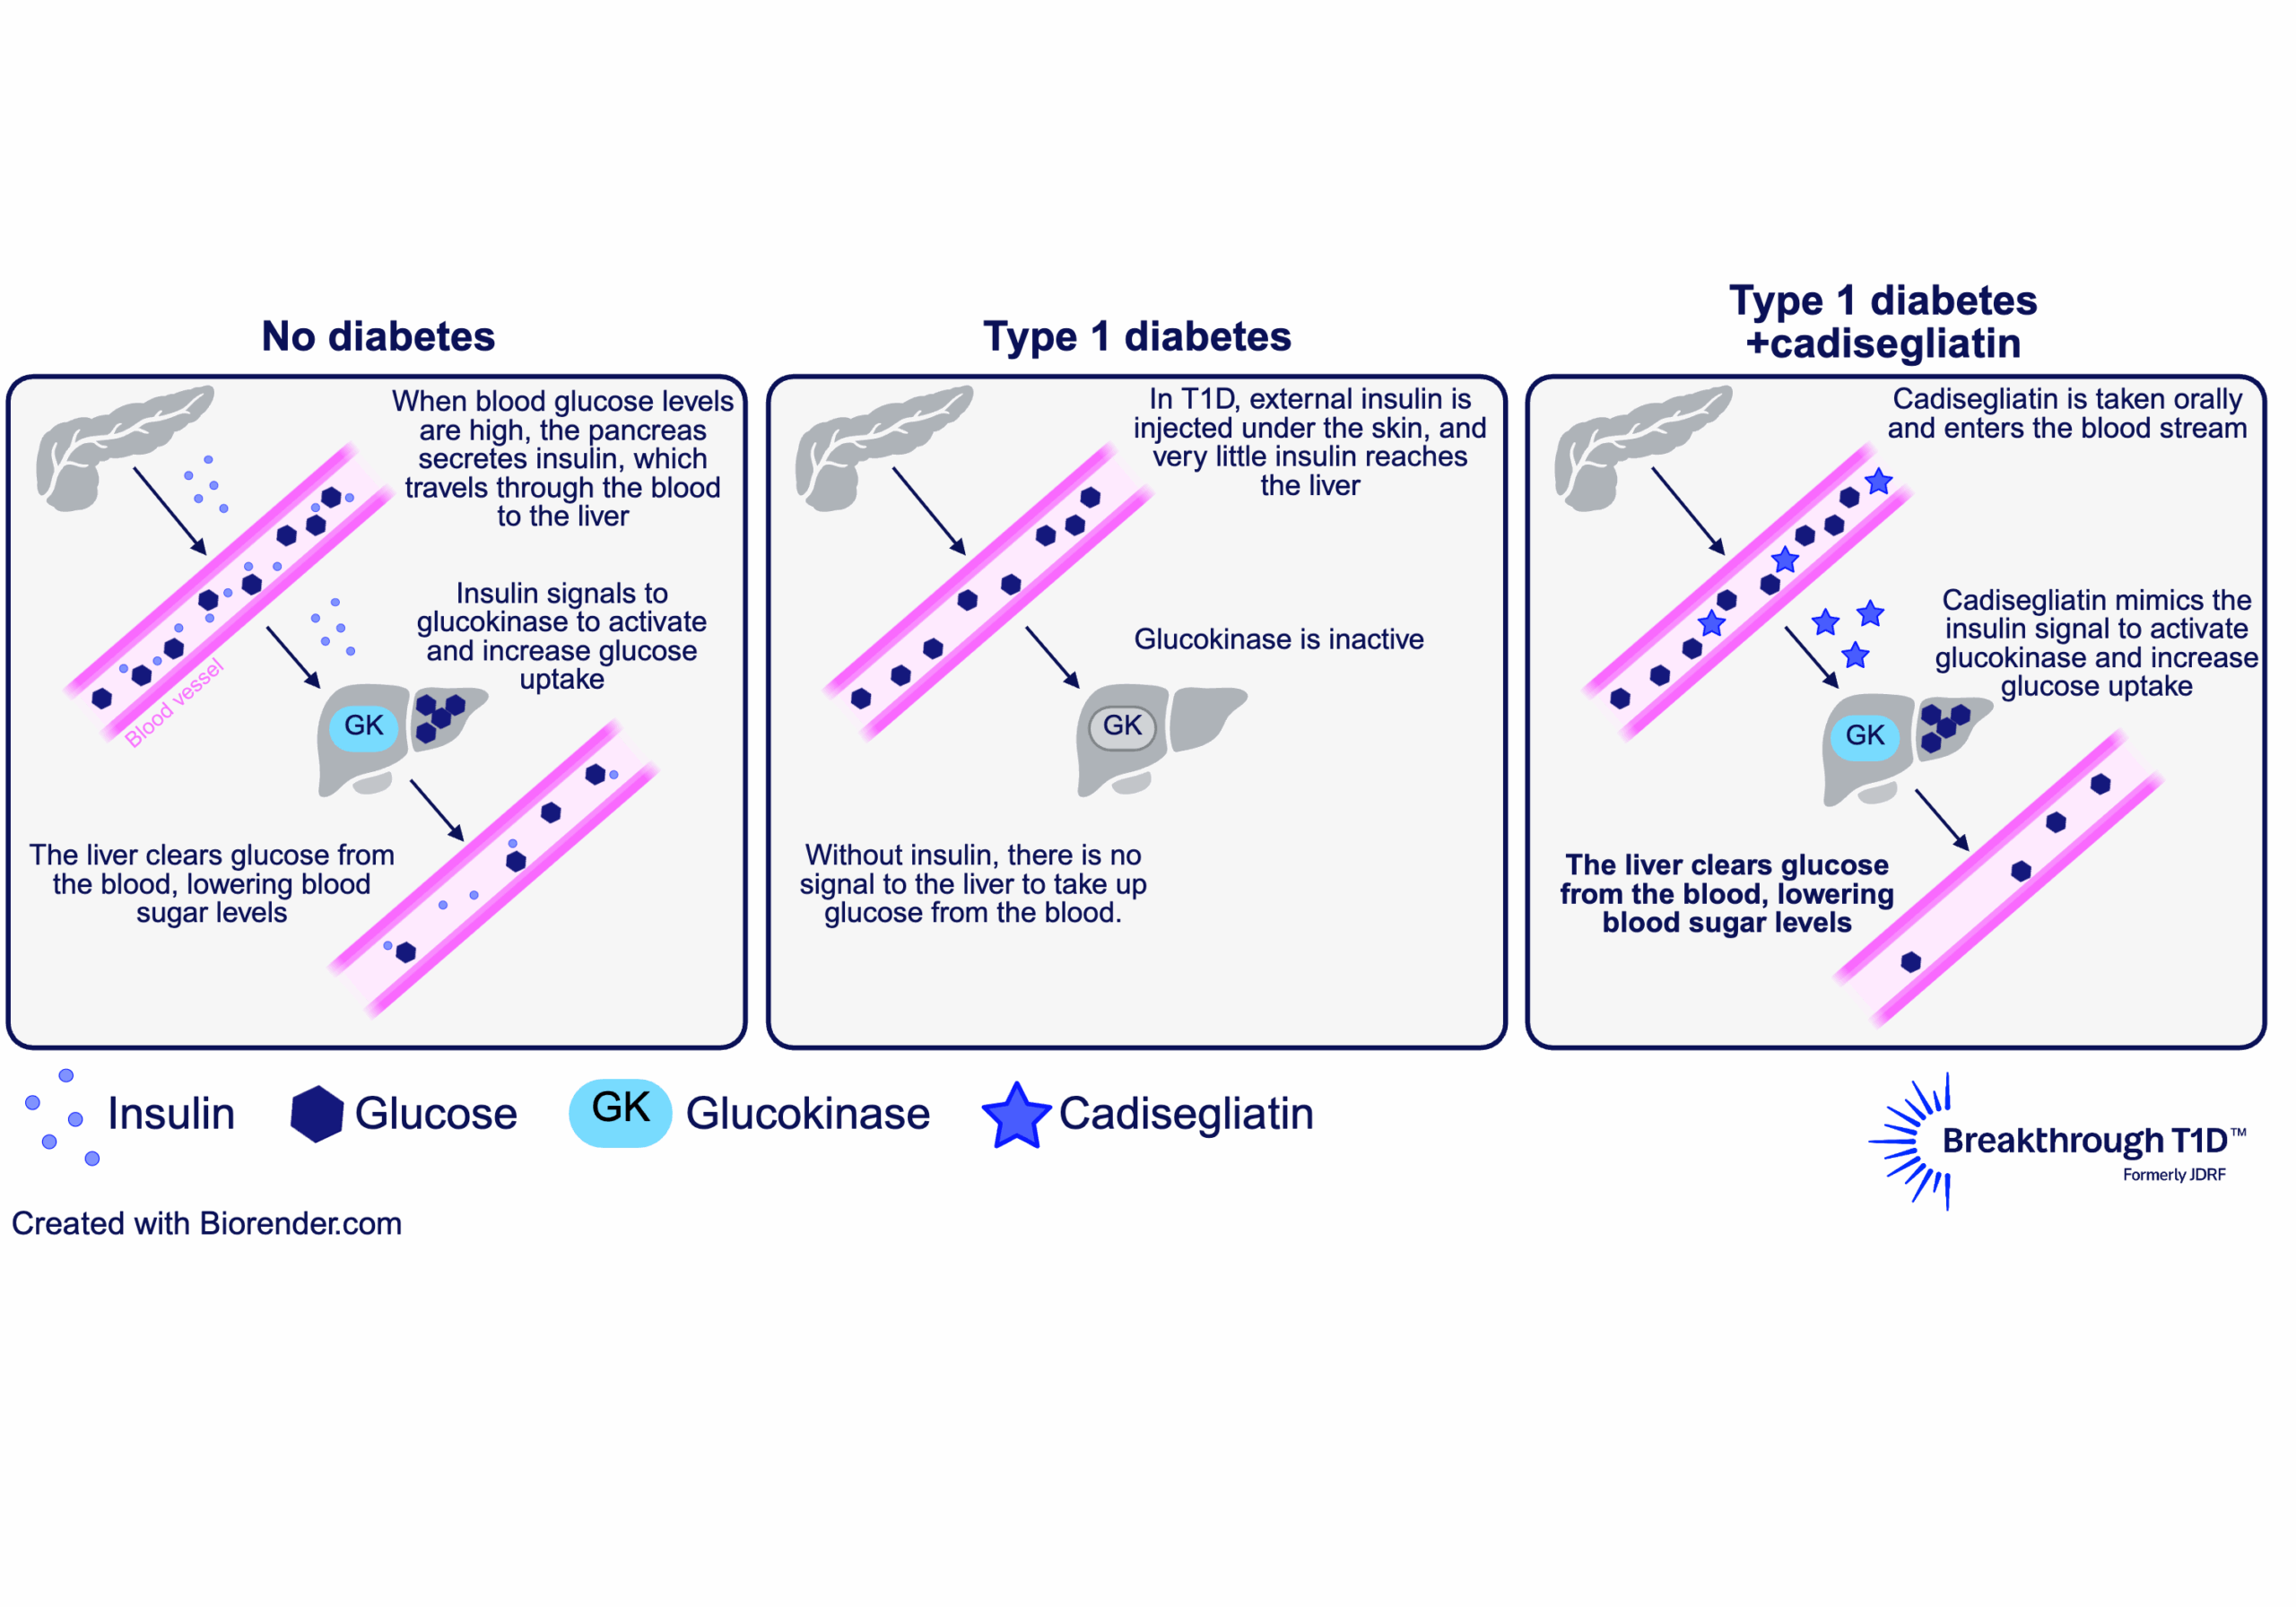
The answer to this question lies in the liver. The liver plays a major role in blood glucose control by taking up excess sugar from the blood and storing it until it’s needed again. To facilitate this, an enzyme called glucokinase in liver cells is activated in response to higher levels of insulin (indicating high blood sugar). This allows liver cells to remove glucose from the blood, bringing blood sugars down to a normal range.
Some of the glucose in the liver is also converted into glycogen, a storage form for glucose. This way, the liver can help increase blood sugar levels when needed, such as in between meals, overnight, or during exercise, to avoid low blood sugar. In this way, glucokinase helps reduce both hyperglycemia and hypoglycemia.
In people with T1D, the pancreas produces little to no insulin, and injected insulin doesn’t reach the liver the same way insulin from the pancreas does. So, glucokinase doesn’t get the signal that allows liver cells to respond to high blood sugar—making hyperglycemia and hypoglycemia worse.
This is where a glucokinase activator like cadisegliatin comes in. It keeps glucokinase in an active state, which restores the ability of liver cells to respond to (and reduce) high blood sugar. Then, in response to low blood sugar, the liver can release some of the sugar it has stored as glycogen into the blood stream. This is why cadisegliatin is being studied in people with T1D— it has the potential to improve blood glucose control in the liver and reduce the risk of highs and dangerous lows, with the goal of easing the daily burden of living with the disease.
Make a difference for yourself and others by participating in clinical trials
How to get involved
If you’re interested in getting involved at UNC, visit their Research for Me website to learn more about the CATT1 clinical trial at this location and other diabetes trials that may be the right fit for you. Reach out to the study team directly, and they will follow up with you to answer your questions and see if you qualify.
You can also register to be contacted by clinical researchers at UNC about participating in future studies for T1D. A research team member will reach out if a study becomes available that matches your profile criteria.
The CATT1 trial is also enrolling at other locations in the U.S. Find the trial site closest to you.
The clinical research team at UNC encourages trial participation as an opportunity to contribute to the body of research that may improve T1D care not only for yourself, but for the T1D community. Participants receive continued support at every step of the way—and safety is the highest priority.
By choosing to participate in a trial, people with T1D may gain access to research treatments, drugs, or devices that may make daily life with T1D easier, while receiving top quality diabetes care delivered by renowned medical centers. The data generated from these trials—thanks to the courageous and brave T1D community members who choose to participate—will shape the treatment landscape for future generations of people with T1D. Dr. Klein is one of many investigators who finds the dedication of the T1D community inspiring. “…I am consistently amazed and moved by the generosity of our participants who dedicate their time and energy to help move science forward,” she explains.

“The T1D community is incredibly generous with their time and motivated to help advance care—not just for themselves, but for the type 1 diabetes community and future generations of people who will live with type 1 diabetes. It’s really an honor to be able to work with them.”
-Klara Klein, M.D., Ph.D.
For Kass, it’s personal. By having T1D himself, he can form deeper connections with trial participants and their families. This allows him to keep conversations honest, participate in shared problem-solving, and understand the same day-to-day challenges of living with T1D—all a part of why he’s excited to be a member of the team providing top-tier diabetes care.
“Some of my favorite moments are when a participant or parent says, ‘You get it,’ and we can talk not just about the study, but about what it means to live well with diabetes. Whether it’s troubleshooting a CGM issue, celebrating a small win in blood sugar control, or simply being a dependable point of contact, I value the trust our participants place in us. That trust is what keeps me passionate about this work.”
-Alex Kass, MSN, MBA, RN, CDCES

Learn more about clinical trials
Visit Breakthrough T1D’s clinical trials web page to learn more about how you can get involved in clinical trials. Use our clinical trial matching tool to find recruiting trials near you that you may be eligible for. Connect with a Clinical Trial Education Volunteer in your area to better understand the process and get your questions answered.
Without clinical trials, progress wouldn’t be possible. All new therapies, devices, and treatments need to be tested to get from labs and into clinics as quickly and safely as possible. Thank you to every trial participant—in the past, present, and future—for helping us get closer to a world without T1D.
Analysis compiled by Avalere Health and supported by Breakthrough T1D (formerly JDRF) finds that research funded by the Special Diabetes Program (SDP) has yielded more than $50 billion in federal healthcare savings.
Created by Congress in 1997 and administered by the National Institutes of Health (NIH), the SDP provides federal funding to support research to prevent, treat, and ultimately cure type 1 diabetes (T1D).
The Special Diabetes Program (SDP) is set to expire soon! Ask your Members of Congress to renew the SDP!
Working closely with the SDP’s champions in Congress—Senators Susan Collins (R-ME) and Jeanne Shaheen (D-NH) and Diana DeGette (D-CO) and Gus Bilirakis (R-FL)—Breakthrough T1D leads advocacy efforts supporting continued funding for the SDP.
The SDP has directly supported many of the most important innovations that have changed how T1D is managed—including continuous glucose monitors (CGMs) and automated insulin delivery (AID) systems.
Today, these technologies are the standard of care and are used more broadly, including by people with type 2 diabetes (T2D) contributing to improved health outcomes for people with T1D and T2D.
Understanding the SDP’s Economic Impact
To better understand the program’s economic impact, Avalere Health conducted an analysis of estimated federal cost savings associated with SDP-supported technologies.
The analysis focused on direct medical expenditures and modeled the savings resulting from the use of CGM and AID systems including savings to the tax-payer supported public insurance programs like including Medicare, Medicaid, and the Department of Veteran’s Affairs.
Avalere Health’s findings indicate that CGMs and AID systems alone have generated at least $50 billion in federal healthcare savings through improved glucose management and reduced diabetes-related complications.
The actual federal savings and total economic impact of these technologies is likely higher as the analysis does not account for indirect cost savings—such as improved productivity (such as, not having to take time off work to treat a low, etc.), reduced disability, or long-term prevention of complications.
CGM and AID 2024 utilization and savings, total federal savings from start of SDP
| Technology | Population Using Technology (2024) | Annual Savings Per Patient (2024) | Federal Savings By Diabetes Type (1998-2024) | Total Federal Savings (1998-2024) |
|---|---|---|---|---|
| Continuous Glucose Monitors (CGMs) Without AID | T1D: 749,700 T2D: 1,738,600 | $5,502 | T1D: $10.9 Billion T2D: $21.2 Billion | $32.1 Billion |
| Automated Insulin Delivery System (AID) | T1D: 780,300 T2D: 1,856,400 | $5,306 | T1D: $5.4 Billion T2D: $12.9 Billion | $18.3 Billion |
T1D therapies on that are on the market or currently in development have benefited from SDP-supported research in numerous ways, including:
- Clinical trials and technology validation for CGMs and AID systems
- Development of disease-modifying therapies, including Tzield, the first therapy approved by the FDA to delay the onset of insulin therapy dependence in T1D
- Development of advanced therapies for diabetic eye disease
- Early-stage beta-cell replacement research, including Lantidra, the first therapy approved by the FDA to place insulin-producing cells back in the body and ultimately reduce or eliminate the need for insulin therapy
The SDP’s Future
This study and existing literature confirm that the SDP has demonstrated a strong return on investment—both clinically and economically. The SDP has also made life with T1D more manageable. AID systems are now standard of care and they are leading to better outcomes with less disease burden.
Ongoing support for diabetes research and treatments will be essential to realizing the full potential of emerging innovations for individuals with diabetes
Disruptions in SDP funding may hinder clinical research infrastructure, delay scientific advancement, and slow patient access to therapies that reduce complications and lower overall costs.
As policymakers evaluate the future of the SDP in the debate over government funding stakeholders should consider how funding decisions will maintain or interrupt momentum in diabetes research, bringing advanced therapies to market, and how that will impact continued cost savings from improved health outcomes for people with diabetes.
Read the Insights & Analysis report and the full white paper on the Avalere Health website.
Editor’s note: Content for this story drawn from Avalere Health’s Insights & Analysis report.
Continuous glucose monitors, or CGMs, have become increasingly popular with people who do not live with type 1 diabetes (T1D) as a way to observe the impact of activity and food on their blood-glucose levels.
While increased visibility of T1D technology can help normalize an advanced way to manage what is often an invisible condition, can wearing a CGM benefit people without T1D? Breakthrough T1D takes a look.
What are continuous glucose monitors?
Continuous glucose monitors are small, wearable devices that continuously measure a person’s blood-glucose levels. They are primarily used in place of glucose meters and finger pokes. A sensor just under the skin measures the glucose levels in real time. The levels are then relayed to a receiver, smartphone, watch, or insulin pump, which displays the readings.
How do CGMs benefit people living with T1D?
Continuous glucose monitors have been transformative for daily type 1 diabetes management. They have proven to:
- Lower HbA1c levels
- Reduce episodes of hypoglycemia (low blood sugar)
- Reduce the risk of complications associated with chronic hyperglycemia (high blood sugar)
- Increase time-in-range
Breakthrough T1D has played a pivotal role in the development and accessibility of CGMs for improved health outcomes in people living with type 1 diabetes.
In 2008, a Breakthrough T1D-funded clinical trial demonstrated the efficacy of CGMs in helping to manage blood sugar, with lower HbA1c levels and reduced rates of severe hypoglycemia in people living with T1D. This led to broader health insurance coverage and, ultimately, broader use of CGMs in the T1D community. The expansion of Medicare coverage of CGMs in 2022 also helped increase their use.
CGMs also have remarkable benefits during pregnancy with T1D. A 2017 study co-funded by Breakthrough T1D and the Canadian Institutes of Health Research showed that CGM use before and during pregnancy improves the health outcomes for both mothers and babies while reducing costs for neonatal hospitalization.
Today, eight CGMs are available in the U.S., and several are used in automated insulin delivery systems.
Unlocking access
Though T1D therapies like continuous glucose monitors are approved for use in the U.S., that isn’t enough. Breakthrough T1D tirelessly advocates for insurance coverage and the adoption of these therapies so that the entire T1D community can benefit from them.
Are there benefits to using a CGM if you don’t have type 1 diabetes?
For people without diabetes, CGM use is still considered investigational. “Early studies suggest CGMs may help detect abnormal blood sugar patterns in those with elevated risk—such as individuals who are overweight, have a strong family history of diabetes, or show borderline lab values—sometimes revealing glucose variability that standard tests might miss,” said Amin Ghavami Nejad, Senior Research Scientist at Breakthrough T1D.
There is also interest in using CGMs among athletes to monitor for exercise-related hypoglycemia and in exploring how blood sugar fluctuations may relate to cardiovascular risk. However, CGMs are not FDA-approved for individuals without diabetes, and there is no established clinical framework for interpreting the data in this population. More research is needed before CGM use in people without diabetes can be broadly recommended.
The role of continuous glucose monitoring in type 2 diabetes (T2D), however, continues to grow. The American Diabetes Association (ADA) 2025 Standards of Care recommended CGM use for adults with T2D who use insulin based on evidence that they improve glucose control, reduce hypoglycemia, and help patients make more informed daily decisions. The recent launch of Dexcom’s over-the-counter CGM, Stelo, also reflects rising interest in expanding access for people with T2D not using insulin and those with prediabetes, though this remains an evolving space and is not yet fully supported by clinical guidelines.
Breakthrough T1D will continue to support research in this area to accelerate therapies and access that can benefit those living with T1D and beyond.
ADA Recap Series
This article is the first of our three-part ADA Recap Series. Breakthrough T1D was on site in Chicago, IL from June 20-23 for the American Diabetes Association’s (ADA) 85th Scientific Sessions. We’re here to report on the latest-and-greatest type 1 diabetes (T1D) advancements—including many driven by Breakthrough T1D funding. Look out for tomorrow’s article for updates on Cures.
Improving Lives
Breakthrough T1D’s Improving Lives program focuses on devices, insulins, adjunctive therapies, treatments for complications, and psychosocial interventions to improve the health and quality of life of people living with T1D.
Adjunctive therapies and complications
There was significant focus on GLP-1 receptor agonists (GLP-1RAs) and SGLT inhibitors (SGLTi) in reducing long-term complications and improving glycemic control in people with T1D.
GLP-1 receptor agonists
Glucagon-like peptide 1 receptor agonists mimic the hormone GLP-1, which elevates insulin and regulates appetite. Examples include Ozempic® (semaglutide) and Mounjaro® (tirzepatide), which acts on both GLP-1 and a similar target, GIP.
SGLT inhibitors
Sodium-glucose cotransporter inhibitors target kidney cells to prevent them from reabsorbing glucose into the blood so it gets excreted as waste. Examples include Farxiga® and Zynquista®.
While SGLTi and GLP1-1RAs have proven effective for heart and kidney disease in type 2 diabetes (T2D) and in people without diabetes, people with T1D have often been excluded from critical trials. Thanks to years of advocacy and support from Breakthrough T1D, T1D trials are ongoing—and real-world evidence suggests that GLP-1RAs and SGLTi could be impactful in the T1D community as well.
Real-world evidence for GLP-1RA use in T1D
- Presenter: Ildiko Lingvay, M.D.; University of Texas Southwestern
- People with T1D have self-reported that they decided to try GLP-1RAs for weight loss and improved glycemic control.
- Real-world evidence suggests that GLP-1RAs have a clinically meaningful impact on weight and reduced insulin dose.
- While GLP-1RAs are generally safe, some people have stopped use because of gastrointestinal side effects. These side effects are also seen in people with T2D and people without diabetes.
A review of SGLTi and GLP-1RAs in reducing chronic kidney disease (CKD) in T1D
- Presenter: David Cherney, Ph.D.; University of Toronto
- In the EMPA-KIDNEY trial that included non-diabetes participants and people with T1D or T2D, empagliflozin (SGLTi) improved kidney health in people with T1D.
- In the ATTEMPT trial, dapagliflozin (SGLTi) improved time in range (TIR), reduced HbA1c levels, and had positive effects on kidneys in youth with T1D.
- The Breakthrough T1D-funded enrolling phase 3 SUGARNSALT trial is testing whether sotagliflozin (SGLTi) can prevent progression of moderate to severe kidney disease in people with T1D, and it includes careful diabetic ketoacidosis (DKA) risk mitigation strategies.
- The SEMA-AP trial found that semaglutide (GLP-1RA) increases TIR in people with T1D when used alongside an AID system.
- The Breakthrough T1D-funded recruiting phase 2 REMODEL-T1D trial is testing if semaglutide (GLP-1RA) can improve kidney health in people with T1D.
Glucokinase
Glucokinase (GK) is an enzyme in liver cells that works in an insulin-dependent manner to regulate blood sugar. In people with T1D who have little insulin reaching the liver, GK can’t work as normal, contributing to higher blood sugar.
Use of a glucokinase activator for glycemic control
- Presenter: Klara Klein, M.D., Ph.D.; University of North Carolina
- In the phase 1/2 SimpliciT1 study, people with T1D who received the GK activator TTP399 showed improvements in blood glucose with fewer hypoglycemic events.
- A different study found that TTP399 does not increase the risk for DKA.
- These studies were done in collaboration with vTv Therapeutics, a company with funding and support from Breakthrough T1D and the T1D Fund: A Breakthrough T1D Venture. The phase 3 CATT1 study for TTP399 is testing whether it can reduce moderate to severe hypoglycemic events in people with T1D.
Adjunctive therapies and complications highlight: Breakthrough T1D-funded research
Halis Kaan Akturk, M.D. (University of Colorado), Janet Snell-Bergeon, Ph.D., MPH (University of Colorado), and Viral Shah, M.D. (Indiana University) presented findings from the Breakthrough T1D-funded ADJUST-T1D clinical trial, which was recently published in the New England Journal of Medicine Evidence. The trial tested whether semaglutide (GLP-1RA) can improve glycemic and weight outcomes in adults with T1D and obesity who are using an AID system. 36% of people treated with semaglutide met the primary endpoints of TIR greater than 70%, time below range less than 4%, and weight loss of 5% or more compared to the placebo, and the drug was well-tolerated and safe. This trial represents critical evidence for use of a GLP-1RA as a potential way to manage both glycemic control and weight in people with T1D.
Ye Je Choi, MPH (University of Washington) reported on the CROCODILE study, which examined metabolic alterations in kidneys of people with T1D. She observed early structural and metabolic changes in kidneys that occurred before the onset of clinical kidney disease and associated structural damage. Her work could contribute to the development of biomarkers that can help predict the onset of kidney disease in people with T1D before it occurs.
Jeremy Pettus, M.D. (University of California at San Diego) conducted a phase 2 clinical trial to address insulin resistance in people with T1D. External insulin therapy can increase levels of insulin in the blood relative to glucose, which reduces sensitivity and may contribute to cardiovascular disease (CVD). Treatment with the glucagon receptor antagonist volagidemab, which prevents the liver from releasing glucose into the blood, reduces insulin requirements by 15%, resulting in improved glycemic control and insulin sensitivity without changes in bodyweight.
Schafer Boeder, M.D. (University of California at San Diego) worked with Dr. Pettus on a phase 1/2 clinical trial that tested whether the addition of SGLTi to the glucagon receptor antagonist volagidemab can further improve glycemic control in people with T1D. The combination of therapies increased TIR up to 86% from 70% and reduced daily insulin use by 27%. Further research is needed to better understand the safety profile of this regimen.
Justin Gregory, M.D. (Vanderbilt University) worked with Dr. Pettus and Dr. Boeder on the above study. He also presented on the use of GLP-1RAs and dual GLP-1/GIP receptor agonists for reducing complications in T1D.
Key takeaways
Clinical trials with GLP-1RAs and SGLTi are providing encouraging evidence about these therapies’ potential to improve long-term health in people with T1D. Breakthrough T1D is working toward a future where these drugs are an option for people with T1D to better manage their blood sugar and reduce complications.
Devices
Real-world insights from Automated Insulin Delivery (AID) systems
- Presenter: David Maahs, M.D., Ph.D.; Stanford University
- Based on published real-world evidence for AID systems in people with T1D, TIR is increased by an average of eight to 15% from baseline in a range of studies across various systems.
- Youth with T1D have better glycemic control and reduced rates of DKA with AID systems. Those with lower TIR at the start of AID system use see the greatest improvements.
Real-world evidence: iLet Bionic Pancreas AID system
- Presenter: Steven Russell, M.D., Ph.D.; Beta Bionics
- The iLet Bionic Pancreas contains a continuously adapting algorithm that automatically determines insulin doses. No carbohydrate counting is required, and meals are only announced as breakfast, lunch, and dinner.
- Data was collected from 16,000 users over two years.
- Users achieved an average HbA1c level of 7.3%, down from 8.9%. This is accompanied by low rates of hypoglycemia and significantly improved self-reported quality of life.
Continuous ketone monitoring: Innovations and clinical applications
- Presenters: Ketan Dhatariya, MBBS, M.D., Ph.D. (Norfolk and Norwich University Hospitals), Lori Laffel, M.D., MPH (Harvard University), Jennifer Sherr, M.D., Ph.D. (Yale University), and Richard Bergenstal, M.D. (HealthPartners Institute).
- DKA rates are increasing in the U.S., but mortality rates from DKA are decreasing.
- The history of continuous glucose monitoring (CGM) offers a roadmap for continuous ketone monitoring (CKM) development, showing how early skepticism gave way to broad clinical impact.
- CKM could allow for earlier detection of rising ketones to prevent DKA. CKM also has the potential to identity infusion set failures, be a valuable addition to AID systems, help monitor early-stage T1D, and more.
- Five new studies funded by the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) will develop CKM for safe and effective use of SGLTi in T1D.
- Tandem, Beta Bionics, Sequel MedTech, and Ypsomed announced plans to integrate Abbott’s dual glucose ketone sensor into their AID systems.
Making the case for time in tight range
- Presenter: Gregory Forlenza, M.D.; University of Colorado
- Dr. Forlenza presented on the benefits and challenges of time in tight range (TITR), also known as time in normal glycemia (TING), defined as blood glucose levels between 70-140 mg/dL.
- TITR will likely be more clinically beneficial than TIR as fluctuations outside of TITR may be better predictors of complications and offer a better therapeutic window for intervention.
- More research is needed to advance therapeutics that will allow people with T1D to achieve TITR before it can be integrated into clinical decisions.
Devices highlight: Breakthrough T1D-funded research
Erin Cobry, M.D. (University of Colorado) presented the results of a Breakthrough T1D-funded clinical trial evaluating an artificial intelligence-powered AID algorithm designed to not require meal announcements. She showed that this algorithm (used without meal announcements) improved overnight TIR, and provided equivalent daytime TIR, compared to participants’ usual care. A major goal for Breakthrough T1D is to advance AID systems that do not require meal announcements to improve both glucose outcomes and quality of life for people with T1D.
Key takeaways
Devices have transformed how this disease is managed. Systems are becoming easier to use with less user input—and, critically, people with T1D are doing better. This is the dream Breakthrough T1D had when we launched the Artificial Pancreas project 20 years ago. We will continue to drive toward our goal of developing systems that provide superior health outcomes with minimal user burden.
Insulins
Inhaled insulin treatment for youth with T1D
- Presenter: Michael Haller, M.D.; University of Florida
- Afrezza® is an inhaled, fast-acting insulin that has proven to be effective in adults.
- The phase 3 INHALE-1 study examined Afrezza® in youth with T1D. Users report greater treatment satisfaction and no increase in weight compared to injected rapid-acting insulin analogs.
- Afrezza® is safe for youth with T1D. The most common adverse events were pulmonary-related, such as coughing.

Breakthrough T1D’s Improving Lives team making an impact
Courtney Ackeifi, Ph.D., Senior Scientist, hosted an Improving Lives Happy Hour with Breakthrough T1D-funded researcher Jeremy Pettus, M.D. The discussion included research priorities for adjunctive (non-insulin) therapies for people with T1D and their healthcare providers. They also discussed the importance of industry partnerships and the role of Breakthrough T1D in driving these relationships, which can accelerate new T1D therapies toward the clinic.
Dr. Ackeifi also spoke at the ADJUST-T1D trial update, contextualizing the use of adjunctive therapies like GLP-1RAs for superior glucometabolic control in people with T1D.
Look out for tomorrow’s article for an update on Cures research presented at ADA 2025!
Menstrual cycles and type 1 diabetes (T1D) have a lot in common: they can be unpredictable, inconsistent from person to person, and physically challenging. Let’s take a closer look at how periods and menopause may influence blood sugar.
What happens during the menstrual cycle?
Most girls get their first period around age 12. Then, each month, the ovary releases an egg; if it doesn’t get fertilized, it’s reabsorbed, and the lining of the uterus is shed as a period. This cycle continues unless the egg is fertilized, after which it implants into the uterine lining (and periods stop). At the end of a woman’s reproductive window between ages 45 and 55, known as menopause, periods stop permanently, and pregnancy is no longer possible.
These complex processes are driven by a conversation between a woman’s brain, ovaries, and uterus, which is controlled by different hormones released at different times. These hormones—such as progesterone and estrogen—may significantly impact blood sugar.
Life with T1D and periods
Women with T1D are more likely to experience longer and irregular periods. More than one-third of teenage girls with T1D—especially those diagnosed before their first period—may have abnormal menstrual cycles. Because 50-60% of people are diagnosed before the age of 15, many women and girls will experience this.
The hormonal culprits responsible for these irregularities affect blood sugar differently depending on the menstrual cycle stage. Progesterone, which is elevated leading to the next period, may increase insulin resistance and the risk of hyperglycemia, especially compared to after the period ends.
The role of estrogen is less clear: it may increase insulin sensitivity—especially when levels are rising post-period—or have no effect at all.
Pregnancy Guide
Get guidance and support on all stages of pregnancy, from pre-pregnancy
planning to juggling T1D as a new mom.
What about menopause?
On average, women diagnosed with T1D before their first period may have a three-year reduction in reproductive lifespan compared to women without T1D—meaning earlier menopause.
As if the barrage of symptoms—including mood swings, brain fog, and sleep issues—weren’t enough, women with T1D might encounter unpredictable blood sugar because of decreasing estrogen and progesterone. Even more, menopause and hypoglycemia can have overlapping symptoms, so special attention is needed to prevent dangerous lows.
Putting it all together
While further scientific studies are required to better understand how hormonal changes affect T1D, there are things you can do to manage your blood sugar more easily.
First, work together with your healthcare team to track blood sugar levels during different menstrual cycle phases or menopause to identify patterns and know what to expect. Women with T1D who take hormonal birth control may have different considerations.
Next, the usual: exercise, eat healthy, and get good sleep. Carefully consider your diet right before your period; while you may crave sugar and carbs, you may also be more susceptible to hyperglycemia, so proceed with caution.
Finally, be kind to yourself. Life with T1D can be hard. Periods and menopause can be hard. Just remember—you’re not alone!
While we look back on 2024, we can reflect upon the incredible progress we’ve made in advancing breakthroughs toward cures and improving everyday life with T1D.
This wouldn’t have been possible without each and every one of you and your continued support of our mission as we drive toward cures for T1D.
Here are the top 11 advances that together, we made happen in 2024:
Breakthrough T1D announced the launch of Project ACT, an initiative aimed at accelerating breakthroughs in T1D cell replacement therapies that do not require broad immunosuppression. Recent advances, such as Vertex’s stem cell-derived islets, have been made possible by Breakthrough T1D’s Cell Therapies program as part of our drive toward cures. The goal of Project ACT is to push research, development, regulatory policies, access, and adoption to increase the rate at which cell therapies without the need for broad immunosuppressants will become available to people with T1D.
Why this matters: Immunosuppressive drugs are a barrier to access to cell replacement therapies because of their toxic side effects, which is why islet transplants are currently only available to people with severe low blood sugar (hypoglycemic) unawareness and episodes. By striving toward a future where we realize the benefits of cell replacement therapies without the downsides of the current regimen of immunosuppressants, we will make islet replacement therapies broadly accessible to the T1D community.
Vertex’s clinical trial of VX-880, a first-generation stem cell-derived islet replacement therapy for people with severe hypoglycemia (requiring the use of immunosuppressants), has transitioned into a phase 1/2/3, or pivotal, trial. This news comes after Vertex shared incredibly promising data in the earlier phases of the trial, including 11 of 12 participants reducing or eliminating the need for external insulin.
The upcoming trial will expand to 50 people who will get a single, target dose of VX-880. The primary endpoint will be insulin therapy independence without severe hypoglycemic events after one year. This is the final clinical testing stage before Vertex can seek FDA approval.
Breakthrough T1D has a decades-long relationship with Vertex and the leading scientists behind stem cell-derived islet therapies, an advancement that would not have been possible without Breakthrough T1D funding and support. The T1D Fund had invested in Semma Therapeutics, which was acquired by Vertex Pharmaceuticals in 2019, eventually leading to the active clinical development of VX-880 in T1D.
Why this matters: This is the first time a scalable cure for T1D is entering phase 3 clinical trials—a significant win and a huge step toward accelerating the delivery of cell therapies to members of the T1D community!
Tegoprubart: Transplant Survival Without Standard Immunosuppressive Drugs
Tegoprubart, an anti-CD40L immunotherapy that limits the immune response, is being tested in a Breakthrough T1D-funded study in people with T1D and severe hypoglycemia who have received deceased donor islets. Eledon Pharmaceuticals announced promising initial results in which two of three people achieved insulin therapy independence. According to the study, tegoprubart is safer for both people and transplanted cells in comparison to broad immunosuppressants, with milder side effects and greater islet survival. To further support this effort, the T1D Fund: A Breakthrough T1D Venture invested in Eledon.
Cell Pouch: A Home for Transplanted Islets
Breakthrough T1D has been supporting the development of Cell Pouch, an implantable device from Sernova that provides a safe, immune-protected environment for transplanted islet cells. In phase 1/2 clinical trials, all six people who received donor islets within the Cell Pouch achieved sustained insulin therapy independence with immunosuppressants, including long-term islet survival and function over five years without harmful side effects.
Why this matters: Standard of care immunosuppressive drugs that help avoid transplant rejection come with unwelcome side effects, such as increased risk of infection and malignancy and toxicity to kidneys, nerves, and islet cells themselves. Breakthrough T1D is focused on finding alternative ways to keep transplanted islet cells alive and healthy so that cell replacement therapies can become more tolerable and accessible.
In a major effort spearheaded by Breakthrough T1D, the first internationally recognized clinical guidelines for those who test positive for T1D autoantibodies have been published. These include guidance on monitoring frequency, education, and psychosocial support in addition to recommended actions for healthcare professionals (HCPs) when the risk of T1D progression is high. The guidelines were cooperatively developed with over 60 international experts spanning ten countries.
Why this matters: Previously, there had been no consensus on monitoring guidelines for people who test positive for T1D autoantibodies. Standardization of clinical recommendations means that individuals, families, and HCPs have tangible next steps to monitor early T1D progression and catch life-threatening complications sooner.
- Breakthrough T1D is leading a campaign to secure a recommendation for T1D screening from the U.S. Preventative Services Task Force (USPSTF), the main authority for preventative care. Approval would require T1D screening to be covered by insurance—an important step forward in expanding access.
- Driven by Breakthrough T1D’s advocacy efforts, The Centers for Medicare and Medicaid Services (CMS) established a unique ICD-10 code for stage 2 T1D. ICD-10 codes are used by HCPs to classify and document diagnoses, symptoms, and procedures. These codes provide a unified way for doctors and providers to indicate what diseases or conditions a person has in their electronic health record (EHR), empowering HCPs to document accurate diagnoses and provide the best possible care.
Why this matters: T1D early detection is critically important to prevent life-threatening complications at diagnosis and to give people necessary resources to make informed decisions about their health. Integrating T1D screening into the U.S. healthcare system will increase access to care.
The past year has seen some important advances in glucose management therapies and devices:
- Cadisegliatin, an activator of a blood sugar regulator in the liver, is being investigated in a phase 3 clinical trial (TTP399) as an adjunct therapy to insulin for people with T1D, although it is currently placed on clinical hold. vTv Therapeutics, the trial sponsor, is also a T1D portfolio company.
- The Omnipod 5 app is now available for the iPhone, making it easier to control the Omnipod without the need to carry a controller. It can also integrate with the Dexcom G6 continuous glucose monitor (CGM).
- Eversense 365 is the first FDA-approved year-round sensor that can easily integrate with automated insulin delivery (AID) systems. Other sensors require replacement after 10-14 days.
Why this matters: While advancements in glucose management have been pivotal in improving health outcomes for people with T1D, access remains a challenge. AID systems are globally underutilized, and not everyone has the necessary technology to connect devices. Breakthrough T1D is working to not only support advances in glucose management but also increase access.
Related content: While Breakthrough T1D consistently strives to improve the lives of those living with T1D, as an organization we have made incredible progress in the development of AID systems, also called the artificial pancreas systems. Read a historical perspective written by Breakthrough T1D volunteer Doug Lowenstein that covers conception to FDA approval of the first artificial pancreas systems, which changed the lives of people with T1D.
An inquiry spearheaded by the Breakthrough T1D affiliates in the U.K. uncovered risks of developing T1D eating disorders (T1DE), including bulimia, anorexia, or insulin restriction to lose weight. There is a significant gap in education and clinical guidelines for HCPs, a lack of internationally recognized criteria for T1DE diagnosis, and insufficient care integration, leading to preventable complications and healthy years of life lost. Breakthrough T1D recognizes the importance of spreading awareness and support for T1DE, and much work is needed to improve the lives of those living with T1DE.
Why this matters: There is an urgent need to change the way T1DE is approached, including integrated physical care with mental health services to get people with T1DE the access to care that they need.
In a study that included people with T1D, finerenone (Kerendia®) has been shown to improve cardiovascular outcomes in adults with heart failure. The drug is already approved in the U.S. to treat kidney and cardiovascular disease in people with T2D. Based on these results, Breakthrough T1D is supporting a clinical trial (FINE-ONE) in conjunction with Bayer to investigate the use of finerenone for T1D with the hopes of reducing kidney complications.
Why this matters: Kidney and cardiovascular disease remain significant challenges for those with T1D, especially given the FDA’s recent rejection of an SGLT inhibitor to lower blood glucose in people with T1D and chronic kidney disease. Yet, a new clinical trial (SUGARNSALT) will better assess the benefits versus risks.
Breakthrough T1D is advocating for the regulatory approval of C-peptide, a biomarker for insulin production by beta cells, to be used as an endpoint in clinical trials. An endpoint can accurately predict a meaningful benefit in clinical trials for disease-modifying therapies (DMTs; treatments that can slow, halt, or reverse T1D). To support this endeavor, Breakthrough T1D scientists and an expert consensus panel published research with evidence supporting C-peptide as an endpoint. Breakthrough T1D is continuing to engage with regulators, coordinate with industry, and assess more clinical trial data to drive this effort forward.
Why this matters: Current clinical trial endpoints (HbA1c, hypoglycemia, and complications) are not the best way to gauge the clinical benefits of T1D therapies. If C-peptide gets regulatory approval to be used as an endpoint, clinical trials could be smaller and shorter while still accurately assessing the advantages of a DMT. This means that drug development can move more quickly, and people with T1D will be able to access therapies sooner.
Related content: Two years ago, the T1D community received the incredible news that Tzield® had become the first FDA-approved disease-modifying therapy that can significantly delay T1D onset. Breakthrough T1D volunteer Doug Lowenstein recounts the life-changing drug’s journey nearly 100 years after the discovery of insulin.
The T1D Index is a data simulation tool that measures the global health impact of T1D, bridging gaps in our knowledge of public health statistics. T1D Index 2.0 has new and improved functionality, including advanced simulation capabilities, validation of data, and enhanced user experience. Breakthrough T1D contributed to both the development and improvement of the T1D Index.
Why this matters: The T1D index is critical in defining the intercontinental scope of T1D, driving us toward country-specific solutions and improved global health outcomes.
Earlier this year, JDRF rebranded to Breakthrough T1D. While our mission remains the same, our name needs to better reflect who we are and where we’re going. Our new brand aligns with our mission to accelerate life-changing breakthroughs for those of every age living with T1D as we work toward a world without it.
Why this matters: The proof is in the name—each day we strive to increase and accelerate breakthroughs in T1D, and it’s critical for our brand to accurately reflect our mission.
It’s certainly been an exciting year! While we still have more work to do, it’s crucial to celebrate our wins, both big and small, to see how far we’ve come in our push to make T1D a thing of the past.
Together, we’re accelerating breakthroughs for people with T1D, and the support of the T1D community drives our mission forward every single day, leading the way to lifechanging therapies and cures. Let’s see what 2025 has in store!

