
Spotlight on Jessie Stover

Jessie Stover is the Development Manager at Breakthrough T1D’s Indiana Chapter. Stover was born and raised in Evansville, Indiana, and she now lives in Indianapolis with her two cats, Milo and Zuko. She enjoys reading, crafting, concerts, and “baking gluten-free desserts so good that no one can tell they’re gluten-free.”
Here, Stover tells her story: from type 1 diabetes (T1D) diagnosis as a toddler, to an insulin pump clinical trial, to learning how to manage her T1D as a teenager, to a new outlook on living with the condition as an adult. Breakthrough T1D thanks Stover for her bravery in sharing her story and her commitment to the T1D community.
Gummy Bears and Insulin Shots

Stover was diagnosed with type 1 diabetes when she was just 2 years old. While her family has a history of autoimmune disorders, “there is no one else in my family with T1D, so it was a big shock to my parents, and we all had so much to learn,” explains Stover.
The learning process started in the kitchen, with a container forever-full of gummy bears to treat lows, a new kitchen scale to measure and track carbs, and sugar-free versions of things Stover had always enjoyed, like Kool-Aid. Between her parents, grandparents, and school secretary, she had “quite the village.”
But, like any kid, Stover didn’t like shots, and she remembers running away from her parents when it was time for an insulin dose.
A Kiddo in a Clinical Trial
During one of Stover’s appointments with her endocrinologist in Indianapolis, she was referred to a clinical trial exploring whether young children could benefit from an insulin pump. “My mom is a very practical person, so it was almost a no-brainer for her since it meant the possibility of no more insulin shots, and it could help manage my blood sugars more smoothly,” explains Stover. No shots sounded pretty good.
By the age of 4, she was enrolled in the trial and using her first insulin pump. Stover noticed a difference immediately; the pump site insertion didn’t hurt at all because they had the option to use a numbing cream. The relief was tangible not just for Stover, but also for her primary caregiver: her mom. Using an insulin pump meant automatically calculated insulin doses, remote control of insulin dosing, and, most importantly, no more shots. Stover has been using an insulin pump ever since.
Learn More about Clinical Trials
Visit Breakthrough T1D’s clinical trials web page to learn more about how you can get involved in clinical trials. Use our clinical trial matching tool to find recruiting trials near you that you may be eligible for. Connect with a Clinical Trial Education Volunteer in your area to better understand the process and get your questions answered.
Being a Teenager is Hard Enough

As Stover grew into a teenager, she also grew into managing T1D on her own. This was when she first truly understood what her diagnosis meant. “It wasn’t new, but it was as if something finally clicked in my brain that it wasn’t going to go away, and now it was my turn to do all the work,” she explains. Coupled with stressful conversations around needing to “do better” to avoid future complications, it was a tough transition, and Stover struggled to find the resources to help her get through it. “Just because the textbook makes it look easy, and my mom made it look easy, it felt like I was expected to immediately do the same,” Stover recalls.
It all changed when someone on Stover’s diabetes care team said: “Being a teenager is hard enough. Adding T1D into the mix is like trying to stop a volcano from erupting!” For the first time, Stover felt that everything she was feeling about being a teen and managing T1D had been put perfectly into words. “I realized I was allowed to be angry, upset, and unhappy, and I didn’t have to just accept T1D and move on. Stepping back and allowing space to understand and grieve my diagnosis helped me,” she said.
This realization opened the door to more candid conversations and a stronger relationship with her parents. Stover was able to openly discuss her mental health needs and set boundaries around what she felt comfortable sharing with her parents about her T1D. “I let myself have space to have bad days and started celebrating the good. I started celebrating my diaversary and stopped trying to make other people comfortable with what I was going through, because I was the one going through it and I needed to do what I needed to do,” Stover explains.
Mental Health Guide
Check out Breakthrough T1D’s Mental Health Guide, which has everything you need to help you navigate the day-to-day of living with T1D.
A Fresh Outlook on Living With T1D

While Stover’s mindset around T1D evolved over the years, she also feels that mental health resources have improved dramatically since she was a teen. Now, she advocates for people living with T1D to take advantage of therapy or connect with others on social media who are experiencing the same thing. “There’s an entire community of people who decided diabetes wasn’t going to be invisible, and in doing so, more honest conversations can happen,” Stover explains. “We know more about chronic illness fatigue, medical trauma, and the effect of societal pressure to be ‘normal.’ If you go looking, you can find someone talking about it. Validation is a very powerful thing.”
Stover’s fortitude shined through when she was diagnosed with Celiac disease right after she graduated college. This time, things went a little differently; Stover had learned to give herself grace, and she found that figuring out how to manage a second autoimmune disease was a bit easier this time around.
In the years since Stover first started using an insulin pump, diabetes technology rapidly advanced with the evolution of pumps and continuous glucose monitors (CGMs), which, when used together, are called an automated insulin delivery (AID) system. As she grew up, Stover was hesitant to put her trust in new systems. “There are so many nuances to T1D care, and it’s been hard to wrap my head around how technology could know me better than I know myself,” Stover explains.
Yet, she eventually decided to add a CGM to her T1D management toolkit. “It is nice to be able to see how your glucose levels are trending,” Stover said. Despite living with anxiety around technology failures and hypoglycemia, Stover found a way to make CGMs work for her. She has her low alarm set when her glucose levels reach 100 mg/dL—well before the typical threshold of 70 mg/dL—so she can execute a plan of action before her blood sugars drop further. “It’s a little extra peace of mind to know that I can catch a low before it becomes a big problem.”
From kid to adult and all the ups and downs in between, Stover found how to manage her T1D in the way that works best for her.
Breakthrough T1D was (and Still is) Along for the Ride

Stover and her family were connected with other T1D families and Breakthrough T1D from the very start. There was a “tiny but mighty” team of parents who started a Breakthrough T1D Walk in Southern Indiana during Stover’s childhood, which, over time, often included many of her friends and classmates. Over two decades later, the Holiday World Walk in Indiana is still alive and well (and organized by Stover herself!).
In addition to Walk, Stover was a Youth Ambassador. “Breakthrough T1D has been a part of my life almost as much as T1D has. And now, getting to be a part of sharing the Walk with other families is truly a gift,” she says.
Word to the Wise
A word of advice from Stover: T1D is only invisible if you let it be. She encourages people living with the condition to take up space.
“Celebrate your diaversary, bedazzle your Omnipod, rock your fun patterned tapes, celebrate with diabesties. Find little ways to bring joy into it, but also take the time to feel the bad days. Take the time to learn how to let the good and bad coexist.”
Talk about T1D. Take advantage of resources. Connect with others online and in person. Give yourself grace. We can all learn a thing or two from Stover!

“We were never meant to do the job of the pancreas. Everyone carries the weight of T1D differently; everyone processes and grieves differently. There are going to be bad days, and the bad days should NEVER be punished. Grace, compassion, and a safe space to authentically be a person living with T1D will have a much better outcome. The only party at fault is the immune system that attacked the wrong thing.”
-Jessie Stover
People living with type 1 diabetes (T1D) need to check their blood sugar levels on a regular basis. Without regular checks during both the day and night, blood sugars may get too high (hyperglycemia) or too low (hypoglycemia). While some people opt to monitor their blood sugar (glucose) levels through finger pricks, others choose to use technology like continuous glucose monitors (CGMs).
CGMs are wearable devices that measure glucose levels every one to five minutes and help people with T1D determine if they need to take immediate action to manage their diabetes. CGMs can also help to identify long-term patterns in glucose levels that can be used to adjust diabetes management plans. Through connected apps, CGMs can often generate a full picture of a person’s glucose trends, from current and average levels to increasingly important metrics like time in range. Read on to learn about the power of time in range—what it is, why it matters, and future applications.
What is Time in Range?
Time in Range
Time in range is the percentage of time per day spent within the range of 70 and 180 milligrams of glucose per deciliter of blood (mg/dL).
Time in range is used by people with T1D and their care teams to see how often glucose levels are within the recommended range. Current standards of care recommend that most people with T1D aim for the following targets:
| Glucose levels (mg/dL) | Percent of time per day spent | |
|---|---|---|
| Time Above Range | Greater than 180 | Less than 25% |
| Time in Range | 70-180 | 70% |
| Time Below Range | Less than 70 | 4% or less |
| Less than 54 | 1% or less |
While each person has different glucose targets, most people living with T1D should aim to have their glucose levels in the recommended range, which is considered safe and healthy for most. People with T1D should work closely with their healthcare teams to review CGM data and create personalized high and low alerts, which often change based on time since T1D diagnosis, age, complications, hypoglycemia unawareness, pregnancy, and more.
CGMs also produce 24-hour graphs (as shown in the figure below), which show whether glucose levels are in, above, or below range at different time points throughout the day. Since glucose levels can change day to day, healthcare teams generally review patterns over a 14-day period. Percentage of time spent in, above, or below range coupled with the 24-hour graph are especially helpful in identifying glucose patterns according to time of day.

Time in Range Versus HbA1c
Time in range and 24-hour CGM graphs paint a picture of a person’s glucose patterns throughout the day. People can choose how many days of CGM data they want to review, and reviewing a specific period of time may help individuals better understand how diet, exercise, and illness affect glucose levels. On the other hand, HbA1c is measured through a blood test that reports average blood sugar levels over the previous 2-3 months. Healthcare professionals (HCPs) often use both time in range and HbA1c measurements to get a comprehensive picture of a person’s glucose levels and make the most informed care decisions possible.
Why Time in Range is Important?
The most important feature of time in range (and CGM data) is that it can provide people living with T1D with an extensive overview of how and when their glucose levels change throughout the day. Blood sugars can change based on exercise, meals, stress, hormones, and more—and time in range can help people understand how lifestyle factors come into play for their personal blood sugar management.
“Time in range helps people with T1D better understand glucose patterns that are not captured by HbA1c,” explains Brynn E. Marks, M.D., MSHPEd, Senior Director of Medical Affairs at Breakthrough T1D. “Additionally, CGM can help people to review their glucose patterns in between visits with their diabetes team and allow for more frequent adjustments to their insulin doses. Reviewing and acting on time in range data and glucose patterns identified by CGM can empower people to manage their T1D and to avoid the roller coasters of managing high and low blood glucose that negatively impact quality of life.”
Spending more time in range is becoming increasingly associated with a lower risk of developing complications, although further research is needed to better understand this connection. Time in range is also often used as an outcome measurement in clinical trials to help researchers understand if a new therapy or treatment is improving blood sugar management. So, the benefits of time in range go beyond personal blood sugar trends, and as we continue to improve our understanding of this metric, its applicability in research and beyond will continue to broaden.
What’s Next for Time in Range
Time in Tight Range
Time in tight range, which is also sometimes referred to as time in normal glycemia, is defined as the percentage of time spent with glucose levels between 70 to 140 mg/dL. People without diabetes have a time in tight range of about 96%. As diabetes therapies and technologies continue to advance, we are just beginning to understand the potential clinical benefits of aiming for a narrower glucose range in people with T1D. Researchers suspect that fluctuations outside in time in tight range may be a better predictor of complications risk. Yet, before we integrate time in tight range into clinical decisions, more research is needed to uncover the benefits of this metric and advance therapies and technologies that will allow people to achieve this narrower target without creating additional undo burden.
Automated Insulin Delivery Systems in Clinical Trials
Diabetes technology has advanced tremendously in the past few decades, largely driven by Breakthrough T1D. Right now, we have automated insulin delivery (AID) systems that can automatically increase or decrease insulin delivery based on CGM readings. These AID systems help to improve time in range and time in tight range while decreasing high and low blood sugar levels, but meal announcements are still required. Fully closed loop systems in the pipeline will not require mealtime announcements. This next-generation technology has the potential to help people achieve time in range targets while using less effort to manage T1D. Breakthrough T1D is funding studies to drive innovation in fully closed-loop systems and bring newer generations to the T1D community quickly and safely.
Non-Insulin Therapies
Therapies used alongside insulin and AID systems have the potential to improve both blood sugar levels and metabolic health. Breakthrough T1D is funding studies investigating treatments that can address insulin resistance, weight management, hypoglycemia, and long-term complications. The goal is to customize treatment approaches and ensure that the T1D community can choose from multiple drugs that may best manage blood sugars and overall health.
GLP-1 in Clinical Trials
The Breakthrough T1D-funded ADJUST-T1D clinical trial showed that the GLP-1 receptor agonist semaglutide (Ozempic) can improve blood sugar and weight outcomes in adults living with T1D and overweight or obesity. After 26 weeks, people treated with semaglutide showed greater improvements in both time in range and time in tight range compared to those who received the placebo. This study has provided evidence for the potential of this class of drugs to benefit the T1D community, and Breakthrough T1D is continuing to drive research into this area.
While exciting advancements in treatments and devices are coming down the pike, many people living with T1D are still unable to reach time in range goals with the tools currently available. Access to improved technologies and non-insulin therapies that can help people with T1D achieve optimal glucose targets will make it possible to use time in tight range goals as the standard of care. Because glucose targets are personalized, time in tight range may not be the right metric for everyone, and more research is needed to see which populations may benefit the most. In the meantime, Breakthrough T1D is working tirelessly to improve the lives of the T1D community, help people achieve the best blood sugar management possible with the options available now, and accelerate the next breakthroughs through the pipeline.

“In the future, I think we will see greater use of time in range in T1D management by people with T1D and care providers as adoption of CGM continues to increase. A growing body of evidence suggests that greater time in range, like low HbA1c, is associated with a lower risk of developing long-term complications. These data might not only support CGM use and attention to time in range in clinical decision-making, but may also impact the way new therapies are evaluated. Today, time in range is widely accepted as a means to evaluate AID systems, but we are not there yet when it comes to evaluating new drugs. Finally, there is a lot of ongoing research to understand time in tight range and how this will help us with clinical guidance and therapy development in the future.”
-Jonathan Rosen, Ph.D., Director of Research at Breakthrough T1D
Improving the Lives of the T1D Community
The goal of Breakthrough T1D’s Improving Lives Program is to ensure that people with T1D have the highest quality of life possible while cures are on the way. We are actively supporting research to drive innovation in technology and devices and understand how new and repurposed medications can improve blood sugar levels, reduce the risk of long-term complications, and benefit overall health. We are clearing approval and coverage pathways for these advancements through our advocacy work and enhancing clinical adoption of devices to improve blood sugar management in more people than ever. Until cures are widely available, Breakthrough T1D will continue to improve the lives of those living with T1D now.
Breakthrough T1D is deeply saddened at the passing of William V. Tamborlane, M.D. Dr. Tamborlane was a tireless champion for the type 1 diabetes (T1D) community, a pioneering clinical scientist, dedicated physician, and longtime Breakthrough T1D partner, grantee, reviewer, advisor, and friend.
“Bill Tamborlane was a giant in our field, and he will be terribly missed,” said Breakthrough T1D CEO Aaron Kowalski, Ph.D. “For more than four decades, Bill pushed the boundaries of what was possible in T1D care—from the earliest insulin pumps to the artificial pancreas systems that have transformed the lives of so many people with T1D, including myself and my brother.”
Dr. Tamborlane was a pioneer in the development of automated insulin delivery. In 1979, with his Yale mentor Robert Sherwin, M.D., he co-authored the landmark study showing that a portable insulin pump could normalize blood glucose in people with type 1 diabetes—the foundation for modern pump therapy. Over the next four decades, he led pioneering work in continuous glucose monitoring, sensor-augmented pumps, closed-loop control algorithms, and the artificial pancreas.
His voice and expertise were pivotal to the Breakthrough T1D Artificial Pancreas Project, and his Yale team conducted some of the earliest closed-loop trials in children and adolescents—populations long underserved by diabetes technology research. He chaired the NICHD-sponsored Diabetes Research in Children Network (DirecNet) and co-chaired the JDRF CGM Study Group, work that established the clinical evidence base for CGM in young people with T1D. He authored more than 1,000 peer-reviewed publications across his career.
“He had a remarkable gift for translating laboratory science into therapies that work for real children and real families,” said Breakthrough T1D Chief Scientific Officer Sanjoy Dutta, Ph.D. “His refusal to accept that kids should have to wait accelerated the field by years.”
Dr. Tamborlane received many of the highest honors in diabetes research, including the JDRF Mary Tyler Moore and S. Robert Levine Excellence in Clinical Research Award, the Diabetes Technology Society Leadership Award, and the American Diabetes Association Award for Achievements in Clinical Diabetes Research. At Yale, he served as Chief of Pediatric Endocrinology for more than three decades, training generations of pediatric endocrinologists who carry his work forward today.
Everyone at Breakthrough T1D will be thinking of Dr. Tamborlane’s family and will always remember the work he did to make life with T1D better for everyone affected by it.
The FDA has approved Tandem’s Control-IQ+ technology for use in pregnancy with type 1 diabetes (T1D). This is the first-ever automated insulin delivery (AID) technology cleared in the U.S. for pregnancy with T1D—a major milestone for the T1D community!
What is an Automated Insulin Delivery (AID) System?
An AID system has three main components: an insulin pump, a continuous glucose monitor (CGM), and an algorithm that lets these components communicate with each other to determine the best insulin dose to help keep blood sugar in range.
Automated insulin delivery systems:
- Are used in place of multiple daily injections (MDI) of insulin
- Continuously measure blood-glucose levels and adjust insulin delivery automatically
- Give less insulin when blood sugar is low and more insulin when blood sugar is high
- Still require user input for meals and snacks and troubleshooting (called hybrid closed-loop)
- Have been shown to improve time-in-range
Tandem’s Control-IQ+ algorithm can be paired with the Tandem Mobi System or t:slim X2 insulin pump and is compatible with Dexcom’s G6/G7 and Abbott’s Freestyle Libre 3 Plus CGMs. Consider speaking with your healthcare provider if you are pregnant or planning to become pregnant to see if these options may be a fit for you.
Using Technology to Manage Type 1 Diabetes During Pregnancy
As your body changes during pregnancy, so does your T1D management. Technologies like automated insulin delivery systems can give you more real-time information about your blood-glucose levels and patterns, help keep you in a tighter range, and reduce the risk of hyperglycemia, hypoglycemia, and long-term complications.
The FDA’s decision to approve Control-IQ+ for pregnancy was based on the results from the CIRCUIT clinical trial. Pregnant women with type 1 diabetes who used Tandem’s Control-IQ+ technology spent around 3 more hours per day in the recommended blood sugar range for pregnancy (63-140 mg/dL) compared to those using a CGM and their usual method of insulin delivery (MDI or insulin pump). Even more, participants using Control-IQ+ had fewer low blood sugar events and less glycemic variability, and they reported better sleep quality.
Right now, less than half of pregnant individuals with T1D achieve 70% or more time in the pregnancy-specific blood sugar range. The approval of Control-IQ+ technology has the potential to change this—meaning healthier pregnancies for both babies and soon-to-be moms.

“During pregnancy, Control-IQ+ was a game-changer.
It helped me achieve more time in range, more predictable outcomes, and experience fewer highs and lows. It also reduced much of the mental burden and T1D-related anxiety that comes with having to constantly monitor and make adjustments, which allowed me to focus more on my overall health and my baby’s well-being. I’m grateful for Control-IQ+ helping me feel more confident and in control during my pregnancy and the healthy, safe delivery of my baby boy.”
Liz Walsh, Living with T1D for 35 years
Other Tips for a Healthy Pregnancy with T1D
Maintaining a healthy lifestyle can benefit both you and your baby throughout your pregnancy. There are extra considerations for pregnant individuals with T1D because changing hormone levels and insulin sensitivity throughout different stages of pregnancy can have significant impacts on blood sugar. Your insulin dose will likely increase during pregnancy, and using an AID system can help make this transition easier.
Work together with your healthcare team to track and manage your blood sugar levels and make the necessary lifestyle adjustments to have the safest and healthiest pregnancy possible—both before and during your pregnancy. This includes eating right, staying active, getting good sleep, monitoring for complications, and maintaining good mental health.

T1D Pregnancy Guide
Get guidance and support on all stages of pregnancy, from pre-pregnancy planning to juggling T1D as a new mom.
Accelerating T1D Research for Pregnancy and Beyond
Breakthrough T1D research grants supported the development of the Control-IQ+ algorithm, and our advocacy supported the Special Diabetes Program, which funded its clinical testing.
We continue to support research into fully closed-loop AID systems to remove the need for user input around meals and troubleshooting so blood sugar management can one day be easier than ever. The work doesn’t stop until pregnant individuals with T1D have more options and can choose the best AID system that works for them.
Right now, we’re funding a clinical trial that will adapt and evaluate the Loop algorithm (as part of the twiist AID system) for pregnant women with T1D. Another Breakthrough-T1D funded study is collecting data from pregnant women with T1D to better understand changes in insulin sensitivity throughout pregnancy. This will then be used to help develop AID systems capable of adapting to pregnancy-specific changes in insulin requirements.
By Sandy Vogt, Ph.D., and Kara Sweet
What is the pipeline?
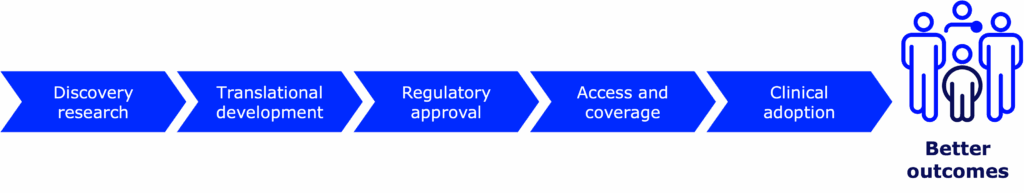
Every new medical device, therapy, treatment, and drug—including those for type 1 diabetes (T1D)—goes through the drug development pipeline. Getting a new therapy or device from the earliest stages of research eventually into the hands of people with T1D is a complicated process. Science takes time (from years to decades!), money (from hundreds of millions to billions!), and brainpower (lots and lots of brilliant scientists, doctors, researchers, and more)—and lots of it.

That’s what drives us and our work in the pipeline: people with T1D doing better.
This process is complex, to say the least. There are safety checks at every step of the way. Data are scrutinized, and preclinical and clinical testing must meet ethical standards. In fact, many new drugs and devices don’t make it very far in the pipeline—and those that do take a long time to get there.
Breakthrough T1D is unique in that we work across the entire pipeline—from start to finish—for every promising therapy or device that we invest in. Between Research, Advocacy, and Medical Affairs, we work at every single step to accelerate progress and get new treatments to people with T1D faster than ever.
That’s our value proposition. That’s what makes supporting us different than supporting an individual researcher, or a university, or a company.
Let’s dive a little deeper into the pipeline—and how we’re turbocharging it.
Time and money
Total money spent in the diabetes space in FY24:
$146 million
By Breakthrough T1D
$521 million
Total T1D research support, including by Breakthrough T1D
$160 million
By the Special Diabetes Program
$412.9 billion
In healthcare
Total investments in new drugs and devices:
12 to 15 years
Estimated time it takes a new drug to get to the clinic
$1 billion
Estimated total cost to bring a new drug from discovery research to the clinic
3 to 7 years
Estimated time it takes a new medical device to get to the clinic
$522 million
Estimated total cost to bring a new medical device from discovery research to the clinic
The pipeline in action: Automated insulin delivery systems
Automated insulin delivery systems vs. artificial pancreas systems
At the very beginning, these devices were called artificial pancreas (AP) systems. Today, they are called automated insulin delivery (AID) systems. We’ll be referring to them as AID systems going forward.
The process at a glance:
$171 million
The amount of money Breakthrough T1D spent on AID system-related research from 2005 to 2024
12 years
The amount of time it took for next-generation AID systems to go from discovery research to clinical adoption after Breakthrough T1D became involved
Hundreds of millions of dollars
Total investment in AID systems from all stakeholders
60+ years
The amount of time it took for AID systems to become a reality, starting with the first experimental AP system in 1964
A deeper dive into the process:
Breakthrough T1D x AID systems
Breakthrough T1D has played a significant role in the evolution of AID systems. Doug Lowenstein, a long-time Breakthrough T1D volunteer and supporter, detailed the history of AID systems from the very beginning, and how we accelerated progress at every step of the way.
Discovery research
It’s the early 2000s. I’m a new AID system, but I don’t exist yet—I’m just an idea. I live in the minds of some scientists and researchers who think that I have the potential to one day become a reality. But, turning an idea into reality can be hard. It’ll take a lot of people, time, and effort for me to exist—but it’s not impossible. The question is: how? Answer: it starts with funding.
2005: Breakthrough T1D launches the Artificial Pancreas Project
Breakthrough T1D dedicates funds to scientists and researchers who have compelling ideas to turn AID systems into a reality, marking the start of the decades-long Artificial Pancreas Project (APP). These investments were key in jump-starting research into all the components needed to make an AID system work.
“[The goal was] to keep people alive and healthy until we find a cure. We were losing people…overnight of low blood sugars. If we could automatically dose insulin and have everybody go to sleep and all wake up, that was an incredible victory.” -John Brady, member of Breakthrough T1D Executive Committee in the early 2000s, former Chair of Breakthrough T1D’s International Board of Directors, and father of a son with T1D
Translational research
It’s 2008. Scientists are making progress on the three key parts that need to work in harmony for me to become a reality: a continuous glucose monitor (CGM), an insulin pump, and an algorithm that lets them talk to each other. But, like most new ideas, before I’m allowed to be tested on humans, I need to be tested in animal models first. Lucky for me, I skipped this step because someone made a tool that could simulate how I would act if I was attached to a human being.
2008: Breakthrough T1D-funded scientists create simulator tool to bypass animal studies
The simulator tool, developed from the initial Breakthrough T1D grants, allowed scientists to model how an AID system would respond to real-life scenarios, like eating a certain amount of carbs or exercising, and how this would translate to blood sugar outcomes like time in range or hypoglycemic events. The FDA accepting the use of this tool was a major win—without animal studies, AID system development was accelerated by years.
“The simulator saved at least five years of animal studies because we didn’t require an algorithm to be tested in an animal model to be deemed safe and effective before going into human studies. That entire chunk was eliminated.” -Sanjoy Dutta, Ph.D., Breakthrough T1D Chief Scientific Officer
Clinical trials
It’s 2012. Scientists have come up with different versions of my components that are ready to be tested in humans. For the next four years, I’ll be attached to people with T1D around the world who courageously volunteered themselves to test if I actually work. Turns out, I do a pretty good job at managing blood sugar—and I’m safe!
2012 to 2016: AID systems make headway in clinical trials
While clinical trials for AID systems started in earnest in 2008, they kicked into high gear in 2012, when investigators started conducting trials using different AID components and algorithms in real-life settings. Progress moved quickly, and results from numerous studies supported the idea that AID systems are both safe and effective. Breakthrough T1D funding—along with the Special Diabetes Program—helped move these trials forward.
“Getting involved in AID system trials to me was my chance to pay it forward for somebody else. I have lived 45 years with T1D…I think there’s something comforting in knowing that my body was used for something that not only had the potential to make me healthier, but really was for other people. I do think there’s something to be said for doing good, feeling good, and this is what it felt like being part of trials.” – Alecia Wesner
Regulatory approval
Flashback to 2009. While scientists are busy figuring me out, people at Breakthrough T1D are already thinking about and planning for my future—and how to work with the decision-makers at the FDA who will ultimately decide my fate. The FDA has also given their two cents about the best ways researchers can test me in clinical trials to get the data needed for me to get approved. Fast forward to 2016, it finally happens: I get FDA approval!
2009 to 2016: From APP roadmap to FDA approval
In 2009, Breakthrough T1D published the AP Roadmap, detailing what the future of AID systems will look like—and how we plan to get there. Two years later, we worked with the FDA on clinical trial design for AID systems so that there was a clear path to approval. After human clinical trials, the FDA approved Medtronic’s hybrid closed-loop MiniMed 670G—officially marking the first AID system to be available in the U.S.
“I do give [Breakthrough T1D] credit for pushing, for saying there’s a real need for this.” -Jeff Shuren, M.D., Head of the Center for Devices and Radiological Health at the FDA at the time
Access
Flashback to 2008. At this time, people were still unsure if one of my main components—a CGM—was a reliable way to measure blood sugar. This all changed when a first-of-its-kind clinical trial showed that CGMs are better than finger pricks and glucose meters, and they were covered by insurance shortly after. This decision paved the way for my future: after my approval in 2016, insurers began offering to cover me.
2008 to 2017: Insurance coverage evolves
The landmark Breakthrough T1D-funded clinical trial in 2008 provided the data to convince private insurers to cover CGMs. Nearly a decade later, Breakthrough T1D launched its “Coverage2Control” campaign to advocate for insurance coverage of T1D treatments, therapies, and devices—including AID systems—ultimately resulting in all major private insurers offering coverage of AID systems by the end of 2017, followed by Medicare shortly after.
“Seeing the artificial pancreas go from concept to reality…is what makes Breakthrough T1D and all of the advocacy volunteers—who sent an email, made a call, signed an action alert, or met with their Member of Congress—very proud of this historic achievement and the impact that these will have on the individual lives of those with type 1 diabetes.” -Cynthia Rice, former Chief Mission Strategy Officer at Breakthrough T1D
Adoption
It’s present day. There are tons of iterations of me, and even more coming. People get to choose which version of me they like best. I’m covered by most health insurance. I’ve come a long way since I was just another thought in the minds of a few scientists who had a vision… and now I’ve come to life! Even so, not everyone has chosen to use me yet—and I will continue to evolve and grow until I can make the lives easier of as many people with T1D as possible.
2017 and on: More and more AID systems come to life
After the first hybrid closed-loop AID system was approved, the flood gates were opened. More and more systems are coming to market each year, and they keep getting better. They’re smaller, easier to use, and better at managing blood sugar. They’re covered by both government and private insurance plans. They’re an integral part of routine discussions between people with T1D and their healthcare providers, and people have options to choose which system is best for them. This is a future that was difficult to imagine two decades ago—and now it’s a reality. Even so, the work continues until AID systems are a reality for more and more people with T1D.
“What we brought to bear is resulting in a safer and easier life for hundreds of thousands, and soon millions, of people with T1D, including my son, that is going to keep them safe until something like a cure comes along,” -Jeffrey Brewer, one of the APP founders
The final stage: Cures and improved lives
It took tons of time, money, people, and effort to get us where we are today, but we’re not at the finish line yet. “The end game for AID systems,” says Breakthrough T1D CEO Aaron Kowalski, Ph.D., “is to have multiple compatible pumps, glucose sensors, and algorithms, so that patients can mix and match what they prefer.”
The end game for T1D as a whole, however, is cures. AID systems have greatly improved the lives of those with T1D—and will continue to do so now and in the future—while we continuously work toward cures that are one day available to everyone with the condition.
The path followed for AID systems is a roadmap for other therapies coming down the pipeline. Breakthrough T1D’s Project ACT is taking a page from the AP roadmap and applying it to cell therapies, so that functional cures can get to people with T1D who want them as quickly and safely as possible.

“While I’m proud of my work as a scientist at Breakthrough T1D on AID systems (and my brother and I currently wear AID systems that are derived from Breakthrough T1D-supported work), more than anything else I want to take off my diabetes devices and achieve what our founders set out to do—find cures for T1D.”
Breakthrough T1D successfully took an idea and turned it into a reality—and we’ll do it again and again until T1D is a thing of the past.
Analysis compiled by Avalere Health and supported by Breakthrough T1D (formerly JDRF) finds that research funded by the Special Diabetes Program (SDP) has yielded more than $50 billion in federal healthcare savings.
Created by Congress in 1997 and administered by the National Institutes of Health (NIH), the SDP provides federal funding to support research to prevent, treat, and ultimately cure type 1 diabetes (T1D).
The Special Diabetes Program (SDP) is set to expire soon! Ask your Members of Congress to renew the SDP!
Working closely with the SDP’s champions in Congress—Senators Susan Collins (R-ME) and Jeanne Shaheen (D-NH) and Diana DeGette (D-CO) and Gus Bilirakis (R-FL)—Breakthrough T1D leads advocacy efforts supporting continued funding for the SDP.
The SDP has directly supported many of the most important innovations that have changed how T1D is managed—including continuous glucose monitors (CGMs) and automated insulin delivery (AID) systems.
Today, these technologies are the standard of care and are used more broadly, including by people with type 2 diabetes (T2D) contributing to improved health outcomes for people with T1D and T2D.
Understanding the SDP’s Economic Impact
To better understand the program’s economic impact, Avalere Health conducted an analysis of estimated federal cost savings associated with SDP-supported technologies.
The analysis focused on direct medical expenditures and modeled the savings resulting from the use of CGM and AID systems including savings to the tax-payer supported public insurance programs like including Medicare, Medicaid, and the Department of Veteran’s Affairs.
Avalere Health’s findings indicate that CGMs and AID systems alone have generated at least $50 billion in federal healthcare savings through improved glucose management and reduced diabetes-related complications.
The actual federal savings and total economic impact of these technologies is likely higher as the analysis does not account for indirect cost savings—such as improved productivity (such as, not having to take time off work to treat a low, etc.), reduced disability, or long-term prevention of complications.
CGM and AID 2024 utilization and savings, total federal savings from start of SDP
| Technology | Population Using Technology (2024) | Annual Savings Per Patient (2024) | Federal Savings By Diabetes Type (1998-2024) | Total Federal Savings (1998-2024) |
|---|---|---|---|---|
| Continuous Glucose Monitors (CGMs) Without AID | T1D: 749,700 T2D: 1,738,600 | $5,502 | T1D: $10.9 Billion T2D: $21.2 Billion | $32.1 Billion |
| Automated Insulin Delivery System (AID) | T1D: 780,300 T2D: 1,856,400 | $5,306 | T1D: $5.4 Billion T2D: $12.9 Billion | $18.3 Billion |
T1D therapies on that are on the market or currently in development have benefited from SDP-supported research in numerous ways, including:
- Clinical trials and technology validation for CGMs and AID systems
- Development of disease-modifying therapies, including Tzield, the first therapy approved by the FDA to delay the onset of insulin therapy dependence in T1D
- Development of advanced therapies for diabetic eye disease
- Early-stage beta-cell replacement research, including Lantidra, the first therapy approved by the FDA to place insulin-producing cells back in the body and ultimately reduce or eliminate the need for insulin therapy
The SDP’s Future
This study and existing literature confirm that the SDP has demonstrated a strong return on investment—both clinically and economically. The SDP has also made life with T1D more manageable. AID systems are now standard of care and they are leading to better outcomes with less disease burden.
Ongoing support for diabetes research and treatments will be essential to realizing the full potential of emerging innovations for individuals with diabetes
Disruptions in SDP funding may hinder clinical research infrastructure, delay scientific advancement, and slow patient access to therapies that reduce complications and lower overall costs.
As policymakers evaluate the future of the SDP in the debate over government funding stakeholders should consider how funding decisions will maintain or interrupt momentum in diabetes research, bringing advanced therapies to market, and how that will impact continued cost savings from improved health outcomes for people with diabetes.
Read the Insights & Analysis report and the full white paper on the Avalere Health website.
Editor’s note: Content for this story drawn from Avalere Health’s Insights & Analysis report.
Written by author and dedicated Breakthrough T1D supporter, advocate, and volunteer Moira McCarthy, pictured above with her daughter, Lauren
It’s now part of my morning routine, but not in the way most type 1 diabetes (T1D) parents would expect.
I grab my phone, open the continuous glucose monitor (CGM) app, and squeal with delight while wiping a strange salty substance from my eyes.
Because, just about every morning, I see something I thought would never be possible in my daughter’s 28 years of living with T1D: a perfectly straight line, totally in range.
It feels—and I not only don’t use this word lightly, but I’ve also never actually used it for a diabetes breakthrough before—transformational.
Starting a new T1D tool

My daughter, Lauren, diagnosed with T1D at age 6 and now almost 34, was late to the game when it came to automated insulin delivery (AID) system adoption. But, about three months ago, she–as her amazing adult endocrinologist kept telling me she someday would when she was ready–decided to give it a try. She chose one of the new, snappy automated insulin delivery systems as her newest tool after a seven-year pump break using pens and a CGM.
She was nervous. She’d experienced some tough years of burnout in the past and had long connected that with using a pump. She was hopeful, but skeptical.
It took her about 24 hours to realize this was truly worth it. And it took me about as much time to feel saved. Saved!
And here’s the cool thing: As long-time JDF, then JDRF, and now Breakthrough T1D volunteers, we absolutely saved ourselves.
That’s because, raising our hands from nearly the start (we attended our first Walk a year after her diagnosis), we were able to not only dream of what could be, but also make it happen.
There’s power and beauty in that, at a level I didn’t anticipate. And that’s the story I want to share. How we, just an average American family impacted by T1D, were able to lead, push, advocate, and win our way to access to smart devices like automated insulin delivery systems. We helped create a solution.
I should preface this with a fact: I’ve never been one to worry about my daughter. I attribute that to having raised her before technology and before the internet. We learned to trust and know that sometimes things go awry, but we can fix them.
But all T1D parents worry. Me? I worried about way, way down the road. Would she be okay in her midlife and later? I wasn’t sure.
Fueling breakthroughs from the ground up

Nearly 20 years ago, I was at an International Board of Directors meeting when then member Jeffrey Brewer had what I call his “pound the shoe on the table” moment. He offered $1 million with the stipulation that we, as an organization and as people passionate about a cure, also focus on creating technology to help people live better with T1D.
I was all in.
As National Advocacy Chair at the time, I helped our organization find funding and people for the original CGM trials. (Did you know no one else would do it, so we just did it ourselves with such great success that industry jumped on board?) We also fought for coverage—we literally found a person in every major insurance plan and filled out paperwork to get the first person covered in each, setting the precedent and swinging the doors open for all (well, almost all; insurance is a work in progress).
We did the Walks—our team, “Got Islets,” was one of the most successful in the nation. Then my daughter and I did the Rides, with our many friends continuing to donate after decades of us asking. Being directly involved gave me a voice in where funding went and how we focused our efforts. To me, tools that lessen the daily, hour-by-hour burden just made sense.
But, until a few months ago, it lived only in my imagination. While we’d always been early adopters (Lauren was the first young child in our state to go on a pump and one of the first in America to go on a CGM), as I said, it took time for her to be ready for this.
Little victories add up to big outcomes

Friends, it’s not a fever dream. This is real, and it’s spectacular. My daughter’s A1c fell quickly to nearly non-diabetic range. Her other labs are, as her endocrinologist said, “those of a person without diabetes.”
But more than that: She feels great! “Mom,” she told me the other day, “this sleeping all night thing? It’s pretty great!”
She feels more focused and refreshed—and since she works in advocacy fighting for coverage and treatments for Duchenne Muscular Dystrophy, that matters.
A Soul Cycle and Pilates enthusiast, she’s finally solved her workout dilemma. Before the automated insulin delivery system, her pattern was this: work out hard, crash low, eat all the carbs on the planet, marinate in remorse. Now? Activity mode works like a charm for her. No more blood sugar crashes, and way more workout satisfaction. Post-workout, she marinates in the feeling of success. The little things are the big things.
Finding our voice for powerful change
When we talk about my daughter’s improvements (and they’re such a big deal, we talk about them a lot!), we always go back to how we helped make this happen.
Like any long, long-term relationship, the organization and I have had our ups and downs. But I realize this: Had I not stumbled upon that Walk in 1998 (thank you, Marshall’s employee, for asking me if I wanted to give a dollar to help cure diabetes. Look what you did!), we may not have found our power, our voices, and our ability to bring positive change. And that feeling of having been a part of bettering her life firsthand? It’s incredible. We found power in what felt like a powerless future.
By the way, that “we” is more than my family. Every time I bump into friends who are long-time donors to this cause, I click on my phone, show them her in-range chart, and cry as I tell them, “YOU did this for us. YOU made this happen. I promised you every time you donated, I’d never just let your money go into a black hole. Here’s the proof. You did this for my kid.”
And me? An average suburban mom, given what seemed on day 1 to be an unbearable burden? Rather than give in to that, Breakthrough T1D helped me rise from it.
If you see me around, ask me to show you the graph I looked at that morning. When that salty substance leaks down my cheeks, know those are tears of joy.
And of thanks. We did what every parent dreams of: me, my friends, and Breakthrough T1D changed my child’s life for the better. This mom is over the moon. I cannot wait to see what the next generation of T1D parents and people living with T1D make happen. Because it’s truly in our hands.
We are our own solution. And from this view, that feels pretty darn great.
Your story matters
Living with T1D looks different for everyone. We want to hear your story: the highs, the lows, the challenges you’ve overcome, and the people who have supported you on your journey.
Continuous glucose monitors, or CGMs, have become increasingly popular with people who do not live with type 1 diabetes (T1D) as a way to observe the impact of activity and food on their blood-glucose levels.
While increased visibility of T1D technology can help normalize an advanced way to manage what is often an invisible condition, can wearing a CGM benefit people without T1D? Breakthrough T1D takes a look.
What are continuous glucose monitors?
Continuous glucose monitors are small, wearable devices that continuously measure a person’s blood-glucose levels. They are primarily used in place of glucose meters and finger pokes. A sensor just under the skin measures the glucose levels in real time. The levels are then relayed to a receiver, smartphone, watch, or insulin pump, which displays the readings.
How do CGMs benefit people living with T1D?
Continuous glucose monitors have been transformative for daily type 1 diabetes management. They have proven to:
- Lower HbA1c levels
- Reduce episodes of hypoglycemia (low blood sugar)
- Reduce the risk of complications associated with chronic hyperglycemia (high blood sugar)
- Increase time-in-range
Breakthrough T1D has played a pivotal role in the development and accessibility of CGMs for improved health outcomes in people living with type 1 diabetes.
In 2008, a Breakthrough T1D-funded clinical trial demonstrated the efficacy of CGMs in helping to manage blood sugar, with lower HbA1c levels and reduced rates of severe hypoglycemia in people living with T1D. This led to broader health insurance coverage and, ultimately, broader use of CGMs in the T1D community. The expansion of Medicare coverage of CGMs in 2022 also helped increase their use.
CGMs also have remarkable benefits during pregnancy with T1D. A 2017 study co-funded by Breakthrough T1D and the Canadian Institutes of Health Research showed that CGM use before and during pregnancy improves the health outcomes for both mothers and babies while reducing costs for neonatal hospitalization.
Today, eight CGMs are available in the U.S., and several are used in automated insulin delivery systems.
Unlocking access
Though T1D therapies like continuous glucose monitors are approved for use in the U.S., that isn’t enough. Breakthrough T1D tirelessly advocates for insurance coverage and the adoption of these therapies so that the entire T1D community can benefit from them.
Are there benefits to using a CGM if you don’t have type 1 diabetes?
For people without diabetes, CGM use is still considered investigational. “Early studies suggest CGMs may help detect abnormal blood sugar patterns in those with elevated risk—such as individuals who are overweight, have a strong family history of diabetes, or show borderline lab values—sometimes revealing glucose variability that standard tests might miss,” said Amin Ghavami Nejad, Senior Research Scientist at Breakthrough T1D.
There is also interest in using CGMs among athletes to monitor for exercise-related hypoglycemia and in exploring how blood sugar fluctuations may relate to cardiovascular risk. However, CGMs are not FDA-approved for individuals without diabetes, and there is no established clinical framework for interpreting the data in this population. More research is needed before CGM use in people without diabetes can be broadly recommended.
The role of continuous glucose monitoring in type 2 diabetes (T2D), however, continues to grow. The American Diabetes Association (ADA) 2025 Standards of Care recommended CGM use for adults with T2D who use insulin based on evidence that they improve glucose control, reduce hypoglycemia, and help patients make more informed daily decisions. The recent launch of Dexcom’s over-the-counter CGM, Stelo, also reflects rising interest in expanding access for people with T2D not using insulin and those with prediabetes, though this remains an evolving space and is not yet fully supported by clinical guidelines.
Breakthrough T1D will continue to support research in this area to accelerate therapies and access that can benefit those living with T1D and beyond.
ADA Recap Series
This article is the first of our three-part ADA Recap Series. Breakthrough T1D was on site in Chicago, IL from June 20-23 for the American Diabetes Association’s (ADA) 85th Scientific Sessions. We’re here to report on the latest-and-greatest type 1 diabetes (T1D) advancements—including many driven by Breakthrough T1D funding. Look out for tomorrow’s article for updates on Cures.
Improving Lives
Breakthrough T1D’s Improving Lives program focuses on devices, insulins, adjunctive therapies, treatments for complications, and psychosocial interventions to improve the health and quality of life of people living with T1D.
Adjunctive therapies and complications
There was significant focus on GLP-1 receptor agonists (GLP-1RAs) and SGLT inhibitors (SGLTi) in reducing long-term complications and improving glycemic control in people with T1D.
GLP-1 receptor agonists
Glucagon-like peptide 1 receptor agonists mimic the hormone GLP-1, which elevates insulin and regulates appetite. Examples include Ozempic® (semaglutide) and Mounjaro® (tirzepatide), which acts on both GLP-1 and a similar target, GIP.
SGLT inhibitors
Sodium-glucose cotransporter inhibitors target kidney cells to prevent them from reabsorbing glucose into the blood so it gets excreted as waste. Examples include Farxiga® and Zynquista®.
While SGLTi and GLP1-1RAs have proven effective for heart and kidney disease in type 2 diabetes (T2D) and in people without diabetes, people with T1D have often been excluded from critical trials. Thanks to years of advocacy and support from Breakthrough T1D, T1D trials are ongoing—and real-world evidence suggests that GLP-1RAs and SGLTi could be impactful in the T1D community as well.
Real-world evidence for GLP-1RA use in T1D
- Presenter: Ildiko Lingvay, M.D.; University of Texas Southwestern
- People with T1D have self-reported that they decided to try GLP-1RAs for weight loss and improved glycemic control.
- Real-world evidence suggests that GLP-1RAs have a clinically meaningful impact on weight and reduced insulin dose.
- While GLP-1RAs are generally safe, some people have stopped use because of gastrointestinal side effects. These side effects are also seen in people with T2D and people without diabetes.
A review of SGLTi and GLP-1RAs in reducing chronic kidney disease (CKD) in T1D
- Presenter: David Cherney, Ph.D.; University of Toronto
- In the EMPA-KIDNEY trial that included non-diabetes participants and people with T1D or T2D, empagliflozin (SGLTi) improved kidney health in people with T1D.
- In the ATTEMPT trial, dapagliflozin (SGLTi) improved time in range (TIR), reduced HbA1c levels, and had positive effects on kidneys in youth with T1D.
- The Breakthrough T1D-funded enrolling phase 3 SUGARNSALT trial is testing whether sotagliflozin (SGLTi) can prevent progression of moderate to severe kidney disease in people with T1D, and it includes careful diabetic ketoacidosis (DKA) risk mitigation strategies.
- The SEMA-AP trial found that semaglutide (GLP-1RA) increases TIR in people with T1D when used alongside an AID system.
- The Breakthrough T1D-funded recruiting phase 2 REMODEL-T1D trial is testing if semaglutide (GLP-1RA) can improve kidney health in people with T1D.
Glucokinase
Glucokinase (GK) is an enzyme in liver cells that works in an insulin-dependent manner to regulate blood sugar. In people with T1D who have little insulin reaching the liver, GK can’t work as normal, contributing to higher blood sugar.
Use of a glucokinase activator for glycemic control
- Presenter: Klara Klein, M.D., Ph.D.; University of North Carolina
- In the phase 1/2 SimpliciT1 study, people with T1D who received the GK activator TTP399 showed improvements in blood glucose with fewer hypoglycemic events.
- A different study found that TTP399 does not increase the risk for DKA.
- These studies were done in collaboration with vTv Therapeutics, a company with funding and support from Breakthrough T1D and the T1D Fund: A Breakthrough T1D Venture. The phase 3 CATT1 study for TTP399 is testing whether it can reduce moderate to severe hypoglycemic events in people with T1D.
Adjunctive therapies and complications highlight: Breakthrough T1D-funded research
Halis Kaan Akturk, M.D. (University of Colorado), Janet Snell-Bergeon, Ph.D., MPH (University of Colorado), and Viral Shah, M.D. (Indiana University) presented findings from the Breakthrough T1D-funded ADJUST-T1D clinical trial, which was recently published in the New England Journal of Medicine Evidence. The trial tested whether semaglutide (GLP-1RA) can improve glycemic and weight outcomes in adults with T1D and obesity who are using an AID system. 36% of people treated with semaglutide met the primary endpoints of TIR greater than 70%, time below range less than 4%, and weight loss of 5% or more compared to the placebo, and the drug was well-tolerated and safe. This trial represents critical evidence for use of a GLP-1RA as a potential way to manage both glycemic control and weight in people with T1D.
Ye Je Choi, MPH (University of Washington) reported on the CROCODILE study, which examined metabolic alterations in kidneys of people with T1D. She observed early structural and metabolic changes in kidneys that occurred before the onset of clinical kidney disease and associated structural damage. Her work could contribute to the development of biomarkers that can help predict the onset of kidney disease in people with T1D before it occurs.
Jeremy Pettus, M.D. (University of California at San Diego) conducted a phase 2 clinical trial to address insulin resistance in people with T1D. External insulin therapy can increase levels of insulin in the blood relative to glucose, which reduces sensitivity and may contribute to cardiovascular disease (CVD). Treatment with the glucagon receptor antagonist volagidemab, which prevents the liver from releasing glucose into the blood, reduces insulin requirements by 15%, resulting in improved glycemic control and insulin sensitivity without changes in bodyweight.
Schafer Boeder, M.D. (University of California at San Diego) worked with Dr. Pettus on a phase 1/2 clinical trial that tested whether the addition of SGLTi to the glucagon receptor antagonist volagidemab can further improve glycemic control in people with T1D. The combination of therapies increased TIR up to 86% from 70% and reduced daily insulin use by 27%. Further research is needed to better understand the safety profile of this regimen.
Justin Gregory, M.D. (Vanderbilt University) worked with Dr. Pettus and Dr. Boeder on the above study. He also presented on the use of GLP-1RAs and dual GLP-1/GIP receptor agonists for reducing complications in T1D.
Key takeaways
Clinical trials with GLP-1RAs and SGLTi are providing encouraging evidence about these therapies’ potential to improve long-term health in people with T1D. Breakthrough T1D is working toward a future where these drugs are an option for people with T1D to better manage their blood sugar and reduce complications.
Devices
Real-world insights from Automated Insulin Delivery (AID) systems
- Presenter: David Maahs, M.D., Ph.D.; Stanford University
- Based on published real-world evidence for AID systems in people with T1D, TIR is increased by an average of eight to 15% from baseline in a range of studies across various systems.
- Youth with T1D have better glycemic control and reduced rates of DKA with AID systems. Those with lower TIR at the start of AID system use see the greatest improvements.
Real-world evidence: iLet Bionic Pancreas AID system
- Presenter: Steven Russell, M.D., Ph.D.; Beta Bionics
- The iLet Bionic Pancreas contains a continuously adapting algorithm that automatically determines insulin doses. No carbohydrate counting is required, and meals are only announced as breakfast, lunch, and dinner.
- Data was collected from 16,000 users over two years.
- Users achieved an average HbA1c level of 7.3%, down from 8.9%. This is accompanied by low rates of hypoglycemia and significantly improved self-reported quality of life.
Continuous ketone monitoring: Innovations and clinical applications
- Presenters: Ketan Dhatariya, MBBS, M.D., Ph.D. (Norfolk and Norwich University Hospitals), Lori Laffel, M.D., MPH (Harvard University), Jennifer Sherr, M.D., Ph.D. (Yale University), and Richard Bergenstal, M.D. (HealthPartners Institute).
- DKA rates are increasing in the U.S., but mortality rates from DKA are decreasing.
- The history of continuous glucose monitoring (CGM) offers a roadmap for continuous ketone monitoring (CKM) development, showing how early skepticism gave way to broad clinical impact.
- CKM could allow for earlier detection of rising ketones to prevent DKA. CKM also has the potential to identity infusion set failures, be a valuable addition to AID systems, help monitor early-stage T1D, and more.
- Five new studies funded by the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) will develop CKM for safe and effective use of SGLTi in T1D.
- Tandem, Beta Bionics, Sequel MedTech, and Ypsomed announced plans to integrate Abbott’s dual glucose ketone sensor into their AID systems.
Making the case for time in tight range
- Presenter: Gregory Forlenza, M.D.; University of Colorado
- Dr. Forlenza presented on the benefits and challenges of time in tight range (TITR), also known as time in normal glycemia (TING), defined as blood glucose levels between 70-140 mg/dL.
- TITR will likely be more clinically beneficial than TIR as fluctuations outside of TITR may be better predictors of complications and offer a better therapeutic window for intervention.
- More research is needed to advance therapeutics that will allow people with T1D to achieve TITR before it can be integrated into clinical decisions.
Devices highlight: Breakthrough T1D-funded research
Erin Cobry, M.D. (University of Colorado) presented the results of a Breakthrough T1D-funded clinical trial evaluating an artificial intelligence-powered AID algorithm designed to not require meal announcements. She showed that this algorithm (used without meal announcements) improved overnight TIR, and provided equivalent daytime TIR, compared to participants’ usual care. A major goal for Breakthrough T1D is to advance AID systems that do not require meal announcements to improve both glucose outcomes and quality of life for people with T1D.
Key takeaways
Devices have transformed how this disease is managed. Systems are becoming easier to use with less user input—and, critically, people with T1D are doing better. This is the dream Breakthrough T1D had when we launched the Artificial Pancreas project 20 years ago. We will continue to drive toward our goal of developing systems that provide superior health outcomes with minimal user burden.
Insulins
Inhaled insulin treatment for youth with T1D
- Presenter: Michael Haller, M.D.; University of Florida
- Afrezza® is an inhaled, fast-acting insulin that has proven to be effective in adults.
- The phase 3 INHALE-1 study examined Afrezza® in youth with T1D. Users report greater treatment satisfaction and no increase in weight compared to injected rapid-acting insulin analogs.
- Afrezza® is safe for youth with T1D. The most common adverse events were pulmonary-related, such as coughing.

Breakthrough T1D’s Improving Lives team making an impact
Courtney Ackeifi, Ph.D., Senior Scientist, hosted an Improving Lives Happy Hour with Breakthrough T1D-funded researcher Jeremy Pettus, M.D. The discussion included research priorities for adjunctive (non-insulin) therapies for people with T1D and their healthcare providers. They also discussed the importance of industry partnerships and the role of Breakthrough T1D in driving these relationships, which can accelerate new T1D therapies toward the clinic.
Dr. Ackeifi also spoke at the ADJUST-T1D trial update, contextualizing the use of adjunctive therapies like GLP-1RAs for superior glucometabolic control in people with T1D.
Look out for tomorrow’s article for an update on Cures research presented at ADA 2025!
While we look back on 2024, we can reflect upon the incredible progress we’ve made in advancing breakthroughs toward cures and improving everyday life with T1D.
This wouldn’t have been possible without each and every one of you and your continued support of our mission as we drive toward cures for T1D.
Here are the top 11 advances that together, we made happen in 2024:
Breakthrough T1D announced the launch of Project ACT, an initiative aimed at accelerating breakthroughs in T1D cell replacement therapies that do not require broad immunosuppression. Recent advances, such as Vertex’s stem cell-derived islets, have been made possible by Breakthrough T1D’s Cell Therapies program as part of our drive toward cures. The goal of Project ACT is to push research, development, regulatory policies, access, and adoption to increase the rate at which cell therapies without the need for broad immunosuppressants will become available to people with T1D.
Why this matters: Immunosuppressive drugs are a barrier to access to cell replacement therapies because of their toxic side effects, which is why islet transplants are currently only available to people with severe low blood sugar (hypoglycemic) unawareness and episodes. By striving toward a future where we realize the benefits of cell replacement therapies without the downsides of the current regimen of immunosuppressants, we will make islet replacement therapies broadly accessible to the T1D community.
Vertex’s clinical trial of VX-880, a first-generation stem cell-derived islet replacement therapy for people with severe hypoglycemia (requiring the use of immunosuppressants), has transitioned into a phase 1/2/3, or pivotal, trial. This news comes after Vertex shared incredibly promising data in the earlier phases of the trial, including 11 of 12 participants reducing or eliminating the need for external insulin.
The upcoming trial will expand to 50 people who will get a single, target dose of VX-880. The primary endpoint will be insulin therapy independence without severe hypoglycemic events after one year. This is the final clinical testing stage before Vertex can seek FDA approval.
Breakthrough T1D has a decades-long relationship with Vertex and the leading scientists behind stem cell-derived islet therapies, an advancement that would not have been possible without Breakthrough T1D funding and support. The T1D Fund had invested in Semma Therapeutics, which was acquired by Vertex Pharmaceuticals in 2019, eventually leading to the active clinical development of VX-880 in T1D.
Why this matters: This is the first time a scalable cure for T1D is entering phase 3 clinical trials—a significant win and a huge step toward accelerating the delivery of cell therapies to members of the T1D community!
Tegoprubart: Transplant Survival Without Standard Immunosuppressive Drugs
Tegoprubart, an anti-CD40L immunotherapy that limits the immune response, is being tested in a Breakthrough T1D-funded study in people with T1D and severe hypoglycemia who have received deceased donor islets. Eledon Pharmaceuticals announced promising initial results in which two of three people achieved insulin therapy independence. According to the study, tegoprubart is safer for both people and transplanted cells in comparison to broad immunosuppressants, with milder side effects and greater islet survival. To further support this effort, the T1D Fund: A Breakthrough T1D Venture invested in Eledon.
Cell Pouch: A Home for Transplanted Islets
Breakthrough T1D has been supporting the development of Cell Pouch, an implantable device from Sernova that provides a safe, immune-protected environment for transplanted islet cells. In phase 1/2 clinical trials, all six people who received donor islets within the Cell Pouch achieved sustained insulin therapy independence with immunosuppressants, including long-term islet survival and function over five years without harmful side effects.
Why this matters: Standard of care immunosuppressive drugs that help avoid transplant rejection come with unwelcome side effects, such as increased risk of infection and malignancy and toxicity to kidneys, nerves, and islet cells themselves. Breakthrough T1D is focused on finding alternative ways to keep transplanted islet cells alive and healthy so that cell replacement therapies can become more tolerable and accessible.
In a major effort spearheaded by Breakthrough T1D, the first internationally recognized clinical guidelines for those who test positive for T1D autoantibodies have been published. These include guidance on monitoring frequency, education, and psychosocial support in addition to recommended actions for healthcare professionals (HCPs) when the risk of T1D progression is high. The guidelines were cooperatively developed with over 60 international experts spanning ten countries.
Why this matters: Previously, there had been no consensus on monitoring guidelines for people who test positive for T1D autoantibodies. Standardization of clinical recommendations means that individuals, families, and HCPs have tangible next steps to monitor early T1D progression and catch life-threatening complications sooner.
- Breakthrough T1D is leading a campaign to secure a recommendation for T1D screening from the U.S. Preventative Services Task Force (USPSTF), the main authority for preventative care. Approval would require T1D screening to be covered by insurance—an important step forward in expanding access.
- Driven by Breakthrough T1D’s advocacy efforts, The Centers for Medicare and Medicaid Services (CMS) established a unique ICD-10 code for stage 2 T1D. ICD-10 codes are used by HCPs to classify and document diagnoses, symptoms, and procedures. These codes provide a unified way for doctors and providers to indicate what diseases or conditions a person has in their electronic health record (EHR), empowering HCPs to document accurate diagnoses and provide the best possible care.
Why this matters: T1D early detection is critically important to prevent life-threatening complications at diagnosis and to give people necessary resources to make informed decisions about their health. Integrating T1D screening into the U.S. healthcare system will increase access to care.
The past year has seen some important advances in glucose management therapies and devices:
- Cadisegliatin, an activator of a blood sugar regulator in the liver, is being investigated in a phase 3 clinical trial (TTP399) as an adjunct therapy to insulin for people with T1D, although it is currently placed on clinical hold. vTv Therapeutics, the trial sponsor, is also a T1D portfolio company.
- The Omnipod 5 app is now available for the iPhone, making it easier to control the Omnipod without the need to carry a controller. It can also integrate with the Dexcom G6 continuous glucose monitor (CGM).
- Eversense 365 is the first FDA-approved year-round sensor that can easily integrate with automated insulin delivery (AID) systems. Other sensors require replacement after 10-14 days.
Why this matters: While advancements in glucose management have been pivotal in improving health outcomes for people with T1D, access remains a challenge. AID systems are globally underutilized, and not everyone has the necessary technology to connect devices. Breakthrough T1D is working to not only support advances in glucose management but also increase access.
Related content: While Breakthrough T1D consistently strives to improve the lives of those living with T1D, as an organization we have made incredible progress in the development of AID systems, also called the artificial pancreas systems. Read a historical perspective written by Breakthrough T1D volunteer Doug Lowenstein that covers conception to FDA approval of the first artificial pancreas systems, which changed the lives of people with T1D.
An inquiry spearheaded by the Breakthrough T1D affiliates in the U.K. uncovered risks of developing T1D eating disorders (T1DE), including bulimia, anorexia, or insulin restriction to lose weight. There is a significant gap in education and clinical guidelines for HCPs, a lack of internationally recognized criteria for T1DE diagnosis, and insufficient care integration, leading to preventable complications and healthy years of life lost. Breakthrough T1D recognizes the importance of spreading awareness and support for T1DE, and much work is needed to improve the lives of those living with T1DE.
Why this matters: There is an urgent need to change the way T1DE is approached, including integrated physical care with mental health services to get people with T1DE the access to care that they need.
In a study that included people with T1D, finerenone (Kerendia®) has been shown to improve cardiovascular outcomes in adults with heart failure. The drug is already approved in the U.S. to treat kidney and cardiovascular disease in people with T2D. Based on these results, Breakthrough T1D is supporting a clinical trial (FINE-ONE) in conjunction with Bayer to investigate the use of finerenone for T1D with the hopes of reducing kidney complications.
Why this matters: Kidney and cardiovascular disease remain significant challenges for those with T1D, especially given the FDA’s recent rejection of an SGLT inhibitor to lower blood glucose in people with T1D and chronic kidney disease. Yet, a new clinical trial (SUGARNSALT) will better assess the benefits versus risks.
Breakthrough T1D is advocating for the regulatory approval of C-peptide, a biomarker for insulin production by beta cells, to be used as an endpoint in clinical trials. An endpoint can accurately predict a meaningful benefit in clinical trials for disease-modifying therapies (DMTs; treatments that can slow, halt, or reverse T1D). To support this endeavor, Breakthrough T1D scientists and an expert consensus panel published research with evidence supporting C-peptide as an endpoint. Breakthrough T1D is continuing to engage with regulators, coordinate with industry, and assess more clinical trial data to drive this effort forward.
Why this matters: Current clinical trial endpoints (HbA1c, hypoglycemia, and complications) are not the best way to gauge the clinical benefits of T1D therapies. If C-peptide gets regulatory approval to be used as an endpoint, clinical trials could be smaller and shorter while still accurately assessing the advantages of a DMT. This means that drug development can move more quickly, and people with T1D will be able to access therapies sooner.
Related content: Two years ago, the T1D community received the incredible news that Tzield® had become the first FDA-approved disease-modifying therapy that can significantly delay T1D onset. Breakthrough T1D volunteer Doug Lowenstein recounts the life-changing drug’s journey nearly 100 years after the discovery of insulin.
The T1D Index is a data simulation tool that measures the global health impact of T1D, bridging gaps in our knowledge of public health statistics. T1D Index 2.0 has new and improved functionality, including advanced simulation capabilities, validation of data, and enhanced user experience. Breakthrough T1D contributed to both the development and improvement of the T1D Index.
Why this matters: The T1D index is critical in defining the intercontinental scope of T1D, driving us toward country-specific solutions and improved global health outcomes.
Earlier this year, JDRF rebranded to Breakthrough T1D. While our mission remains the same, our name needs to better reflect who we are and where we’re going. Our new brand aligns with our mission to accelerate life-changing breakthroughs for those of every age living with T1D as we work toward a world without it.
Why this matters: The proof is in the name—each day we strive to increase and accelerate breakthroughs in T1D, and it’s critical for our brand to accurately reflect our mission.
It’s certainly been an exciting year! While we still have more work to do, it’s crucial to celebrate our wins, both big and small, to see how far we’ve come in our push to make T1D a thing of the past.
Together, we’re accelerating breakthroughs for people with T1D, and the support of the T1D community drives our mission forward every single day, leading the way to lifechanging therapies and cures. Let’s see what 2025 has in store!

