
This article was written by Amanda Gilchrist, a Participant Advisory Council Member (PAC), a Clinical Trial Education Volunteer, and Breakthrough T1D supporter. Amanda’s story details her family’s type 1 diabetes (T1D) journey, why clinical trial participation is important to her, and her experience in the PAC. The views expressed by the author are her own and are not necessarily representative of Breakthrough T1D or our leadership, employees, or supporters.
A family T1D journey

In August 2020, my then 4-year-old daughter Emmie was diagnosed with T1D. Our family had absolutely no knowledge of T1D prior to her diagnosis. It was terrifying to suddenly manage Emmie’s blood sugar every minute of every day. Parenting is challenging enough, but parenting a child with a chronic disease brought it to a whole new level.
Fourteen months after Emmie’s diagnosis, I was diagnosed with T1D at age 36. Suddenly, I had to act as a pancreas for both my daughter and me—all while balancing life as a mom, a wife, and a second-grade teacher. And our T1D story didn’t stop there; in July 2024, my 5-year-old son, Callen, was diagnosed with stage 2 T1D (before insulin therapy is needed). We consider ourselves a family of T1D “Diabesties”!
Participating in clinical trials, together
One silver lining to Emmie’s diagnosis during the COVID-19 pandemic was the ability to connect with others virtually from anywhere. I joined every virtual Breakthrough T1D support group I could find. Through these meetings, I learned about T1D clinical trials. I was shocked to learn that trials can fail due to lack of participation. I remember thinking, “How are we ever going to move technology forward? How will we ever find a cure?”

As it turns out, the brilliant scientists and researchers working toward cures need us—people with T1D and their families—to step up. They literally can’t do it without us. Clinical trials give Emmie and me a chance to take back a little control over our T1D and to contribute to something bigger. Through research, we can be part of the path toward cures.
Emmie and I have participated in a wide variety of trials. We have been on device trials like the Dexcom G7, Tandem Control IQ (for ages 2-5), iLet Bionic Pancreas, and Omnipod 2.0. We’ve also been part of behavioral and observational studies like REDCHiP (Reduce Hypoglycemia Fear in Parents of Young Kids with T1D) and BEAD-T1D (Building the Evidence to Address Disparities in Type 1 Diabetes). We even participated together in a clinical trial for Afrezza inhaled insulin, and I took part in the phase 1, first-in-human TOPPLE (Tolerance Using Plasmid in People with T1D) trial for a potential disease-modifying therapy, just months after my diagnosis.
Although my husband doesn’t have T1D and my son is early-stage, they’ve also joined numerous studies designed for family members of people with T1D. For us, participating in research has become a family mission.
Telling her story through the PAC

I learned about the Breakthrough T1D Participant Advisory Council (PAC) through my volunteer work in clinical trials. As both a clinical trial participant and the parent of a clinical trial participant, I have so much to share about the trial design—the positive experiences we’ve had, as well as the many barriers families face when joining trials. Being a PAC member allows me to share these insights and offer feedback to improve future trial design. As a person with T1D, a T1D mom, and a stage 2 T1D mom, I bring a unique perspective to companies, researchers, and scientists developing the next generation of clinical trials.
Through the PAC, I’ve had the privilege of sharing my family’s lived experience with organizations such as GentiBio, RTI Health Solutions, Einstein Med, and WAVE T1D. By telling our story, I’ve been able to provide a real-world perspective on the constant challenges of life with T1D—missed birthday parties, terrifying ambulance rides, constant supervision, and life without sleepovers. Many researchers have shared that while they understand the science of life with functioning beta cells, hearing our story has helped them better understand the human side of diabetes—the daily struggles, fears, and resilience that define families like mine. The most rewarding feedback I receive is that our story has reignited researchers’ motivation to continue their vital work toward cures.

If you or someone you know may be interested in joining the Participant Advisory Council, please reach out to Michelle Simes-Kennedy at [email protected].
Learn more about clinical trials
Visit Breakthrough T1D’s clinical trials web page to learn more about how you can get involved in clinical trials. Use our clinical trial matching tool to find recruiting trials near you that you may be eligible for. Connect with a Clinical Trial Education Volunteer in your area to better understand the process and get your questions answered.
Taking care of your mental health with type 1 diabetes (T1D) is just as important as managing your blood sugar and taking your insulin.
Statistics show that mental health issues can affect people of all ages living with T1D:
1 in 4
People living with type 1 diabetes affected by depression
Up to 1/3
Number of adolescents living with type 1 diabetes who develop diabetes distress
3x higher
The prevalence of generalized anxiety disorder in people living with type 1 diabetes compared to the general population
There are also anxieties exclusive to people with T1D, particularly fear of hypoglycemia, which is associated with substandard diabetes management and reduced health outcomes.
Breakthrough T1D is working to address mental health concerns for people living with type 1 diabetes through education, research, and community support.
Breakthrough T1D Mental Health Guide
Thriving with T1D starts with your mental and emotional well-being. Our Mental Health Guide offers information to help you better manage your mental health with type 1 diabetes, including:
- Guidance on coping with the stress of T1D
- Tips on how to deal with the loss of sleep with T1D
- Advice on finding a mental health professional
- A deep dive into the differences between anxiety, depression, distress, and burnout with T1D
Funded Research in Mental Health and T1D
For more than three decades, Breakthrough T1D has funded research that addresses the mental health challenges that can come with T1D, including diabetes distress, eating disorders, and anxiety. Some current Breakthrough T1D-supported studies in this area include:
- Reducing Diabetes Distress Using Cognitive Behavioral Therapy in Young Adults with Type 1 Diabetes
Exploring whether the combination of a continuous glucose monitor (CGM) with telemedicine-delivered cognitive behavioral therapy can help reduce diabetes distress in young adults versus the use of a CGM alone.
- iAct for Eating Disorders in Type 1 Diabetes
Investigating the use of cognitive behavior therapy with mobile phone-delivered interventions to improve diabetes management and decrease eating disorder symptoms and emotional distress in adolescents and adults living with type 1 diabetes.
- A Hybrid Effectiveness-implementation Trial to Reduce Diabetes Distress in Teenagers
Testing the effectiveness of a group-based diabetes distress intervention for teens in improving diabetes-specific emotional distress and preventing the worsening of blood sugar management.
T1D Community Support
Voices of T1D
Our new podcast, Voices of T1D, explores what it’s really like to live with type 1 diabetes. Each month, a new episode explores the emotional and social realities of living with T1D, featuring honest conversations with people who navigate it every day.
Living with Type 1 Diabetes: Mental Health and Mindfulness
Pizza: The Most Frustrating Food for T1D
Type 1 Diabetes: The Third Wheel
Community Summits
Breakthrough T1D Community Summits are an educational and networking opportunity for all those impacted by type 1 diabetes. They bring our community together to learn from experts, hear about the latest breakthroughs in research, and build meaningful connections with others who understand the T1D journey.
Local Chapter Support
Your local Breakthrough T1D chapter can also provide valuable support through T1D community connections and events.
Living with the burden of type 1 diabetes can be overwhelming, but you are never alone! Through support, research, and education, Breakthrough T1D is helping to reduce the mental health impact of type 1 diabetes and improve health outcomes for the entire T1D community.
It was identified in the late 1960s. Since then, studies have shown that it is a biomarker for beta cell function. In other words, it’s a measure of beta cell health and insulin production. If it’s low (or you have none), it indicates that your pancreas is producing little or no insulin. There was even a test to measure it in humans 50 years ago. What is it?
C-peptide.
It is a fragment generated during the process of making the active form of insulin that gets released from the pancreas into the body, and it can be easily measured in the blood or urine. C-peptide is an important biomarker that is critical to developing new disease-modifying therapies for type 1 diabetes (T1D).
Biomarkers and surrogate endpoints
A biomarker, or a biological marker, is anything that can be used to measure what’s going on in the body.
Biomarkers are used by doctors to help monitor your health and are often used by researchers to study how the body responds to new therapies. In some cases, biomarkers can be used as a clinical trial endpoint, something that is measured in a clinical study to objectively determine if a therapy is effective.
To be used as a clinical trial endpoint, a biomarker must be a surrogate endpoint, meaning the biomarker has been proven to predict a clinical benefit (that is to say, the biomarker is a surrogate for other clinical benefits). For example, HbA1c is a surrogate endpoint for the risk of diabetes-related eye, kidney, or nerve complications. Surrogate endpoints are important because they allow us to see the effects of a drug much faster, easier, and sometimes more clearly than other endpoints.
Regulators at the U.S. Food and Drug Administration (FDA) and other regulatory agencies around the world classify surrogate endpoints based on the strength of the evidence that they can predict clinical benefit. See below for the different categories of surrogate endpoints and what each means.
| Type of surrogate endpoint | Able to predict clinical benefit? | Able to support drug approval? |
|---|---|---|
| Exploratory | Preliminary evidence | Not at all |
| Reasonably likely | Good but not conclusive evidence | Accelerated approval with post-marketing studies needed to confirm benefit |
| Validated | Definitive evidence | Full approval |
For example, it is very well established that HbA1c is a good predictor of diabetes-related complications. The evidence is robust enough that HbA1c is considered a validated surrogate endpoint, and it has been used to support approval of many T1D therapies.
Challenges with current T1D clinical trial endpoints
Regulators have said the endpoints that can be used for drug approval in T1D trials today are HbA1c, low blood-sugar events, and rates of disease complications. For disease-modifying therapies (DMTs)—those that can change the course of T1D—reaching these endpoints in clinical trials can be a major challenge, especially when tested in people recently diagnosed with T1D.
There are multiple reasons for this. First, measuring the effects of new drug on HbA1c levels is difficult because insulin therapy can also cause improvements in HbA1c, and we need to distinguish between the effects of the two. Second, low blood-sugar events are relatively uncommon, especially if someone experiences a honeymoon period after diagnosis. Third, complications take years to develop, and trials would have to be decades long to directly see a drug’s effects on long-term outcomes. Therefore, trials that use these endpoints often require prohibitively (1) large numbers of enrolled subjects and/or (2) long follow-up, which makes moving DMTs through the pipeline more challenging than ever. Compounding the challenge, large or lengthy trials are expensive, which could hinder industry investment in T1D therapies.
Why C-peptide is important
For more than 40 years, C-peptide has been known as a biomarker for beta cell function. And for 25 years, the research field has agreed it should also be used as a validated surrogate endpoint to predict clinical benefits in DMT clinical trials.
Using C-peptide, DMT studies could require fewer participants, take less time, and cost less money, all while still being able to demonstrate the clinical benefits of a new therapy. This is especially critical for emerging therapies aimed at people in stage 3 T1D—when insulin therapy is needed—who currently don’t have any options to preserve beta cells and delay disease progression. Ultimately, C-peptide as a validated surrogate endpoint would unlock DMTs for the T1D community. In fact, without C-peptide, it will be incredibly difficult for DMTs to move through the drug development pipeline at a reasonable pace—or at all.
Despite widespread scientific consensus, regulators do not yet agree that C-peptide is a validated surrogate endpoint that can support full approval. In recent years, the FDA has stated that C-peptide could be used as a reasonably likely surrogate endpoint that could support accelerated approval. If granted accelerated approval, additional post-marketing studies are required to confirm the drug’s benefits. And the confirmatory trials must use the same old endpoints that are so challenging to study: HbA1c, low blood sugar events, or disease complications. This is a big step forward, but for many companies, the bar is still too high to invest in T1D therapies.
Based on FDA recommendations, almost every DMT trial in stage 3 T1D uses C-peptide as the study endpoint, and the FDA recently agreed to consider C-peptide as a reasonably likely surrogate endpoint that could support accelerated approval for two different therapies from two different companies.
First, the FDA agreed that C-peptide data from the DIAGNODE-3 trial, which investigated whether retogatein (rhGAD65) could preserve beta cells, could potentially support accelerated approval. Second, the FDA is currently reviewing data from the Tzield PROTECT study, which also assessed C-peptide to see if Tzield could preserve beta cells, and the FDA has granted Tzield priority review for stage 3 T1D. Each of these examples demonstrate that regulators believe in the potential of DMTs to change the lives of the T1D community, and they opened the door for C-peptide to accelerate the pace of these therapies. While the interim results from DIAGNODE-3 were negative and the Tzield review is still ongoing, we see clear signs that C-peptide makes the development of DMTs possible.
However, regulators don’t yet consider C-peptide to be a validated surrogate endpoint, and it therefore can’t be used to approve a new drug.
So why isn’t C-Peptide a validated surrogate endpoint?
The story goes back more than 20 years.
Early consensus
In 2001, the American Diabetes Association (ADA) held a workshop to identify appropriate outcome measures in T1D clinical trials. Clinicians and researchers at the workshop agreed that C-peptide is not just a measure of beta cell function, but also directly predicts benefits of other outcomes, including improved HbA1c, lower risk of low blood sugar (called hypoglycemia), and lower risk of diabetic eye disease.
Researchers concluded that drugs that can preserve C-peptide, and therefore beta cell function, would also improve these other clinical outcomes. The results were clear: A consensus-driven conclusion determined that C-peptide is the appropriate outcome measure for T1D clinical trials to preserve beta cell function.
Unfortunately, regulators were not convinced. At the time, researchers could only point to a few investigational drugs that showed the beneficial effects of preserving beta cell function (measured by C-peptide), and some of the most important studies could not definitively prove that C-peptide predicted benefits. Regulators needed more data.
Many more clinical trials
Now, there have been dozens of clinical trials of disease-modifying therapies in stage 3 T1D, and nearly all of them use C-peptide, which scientists can rely on to demonstrate the beneficial effects of preserving beta cells. A meta-analysis, funded by Breakthrough T1D and Diabetes UK through the Critical Path Institute’s Trial Outcome Marker Initiative (TOMI), showed that disease-modifying therapies that preserve beta cell function are effective at improving metabolic outcomes in stage 3 T1D. This, said the authors, “support[s] the use of C-peptide as a surrogate endpoint in clinical trials.”
Breakthrough T1D is a founding member of the Critical Path Institute’s (C-Path) Type 1 Diabetes Consortium. C-Path is a nonprofit organization dedicated to improving and streamlining the process of drug development, and with support from Breakthrough T1D, launched its T1D Consortium (T1DC) in 2017. Initially, the T1DC worked to get regulatory endorsement of diabetes-related autoantibodies as biomarkers to be used in the development of therapies that can delay or prevent T1D. This was achieved by receiving regulatory qualification from the European Medicines Agency (EMA) and published acceptance from FDA. Now, the T1DC is working to develop clinical trial simulation tools to improve T1D prevention and new-onset T1D clinical trials, as well as generating new evidence for the role of C-peptide in clinical trials.
Making the case for C-peptide
A publication, authored by world-renowned investigators (one of which was in the publication that followed the 2001 ADA workshop!) and five Breakthrough T1D employees, summarizes the totality of evidence to date for C-peptide as a validated surrogate that predicts clinical benefits of DMTs in T1D. This publication summarizes data from many different types of studies to make the case for C-peptide. The research presented includes:
- Longitudinal studies (Diabetes Control and Complications Trial (DCCT/EDIC))
- Cross-sectional studies (Scottish Diabetes Research Network Type 1 Bioresource Study (NT1BIO))
- Beta cell transplantation studies (Collaborative Islet Transplant Registry)
- Meta-analysis of clinical trials of DMTs to preserve beta-cell function (TOMI Study)
All of these have identified benefits from the preservation or restoration of beta cell function as measured by C-peptide.
Even more, for the first time ever, last year the FDA participated in a public workshop about C-peptide with researchers, scientists, Breakthrough T1D, companies, and people living with T1D. During this workshop, the FDA gave clear directions to the research community about the evidence needed for them to consider C-peptide a validated surrogate endpoint that can be used for DMT approvals.
As a result of this workshop, C-Path’s T1DC spun out a C-peptide data analytics working group with the key players in the field—including the FDA—that has been working hard over the past year to compile the evidence that the FDA requested. Right now, the FDA is reviewing the statistical analysis plan for C-peptide data. Once approved, the group will move forward, put their analysis plan into action, and submit their results.
The greatest opportunity to intervene with DMTs exists early in the autoimmune process. This requires an endpoint that can identify clinically meaningful impacts in early-stage disease. C-peptide is that endpoint.
Breakthrough T1D hopes that regulators will agree.
Breakthrough T1D is focused on developing drugs, or disease-modifying therapies (DMTs), that change the course of T1D for everyone affected by it—and those yet to be. That means slowing or halting the progression of the disease, preventing it from ever occurring, and reversing it entirely through immune therapies and beta cell therapies.
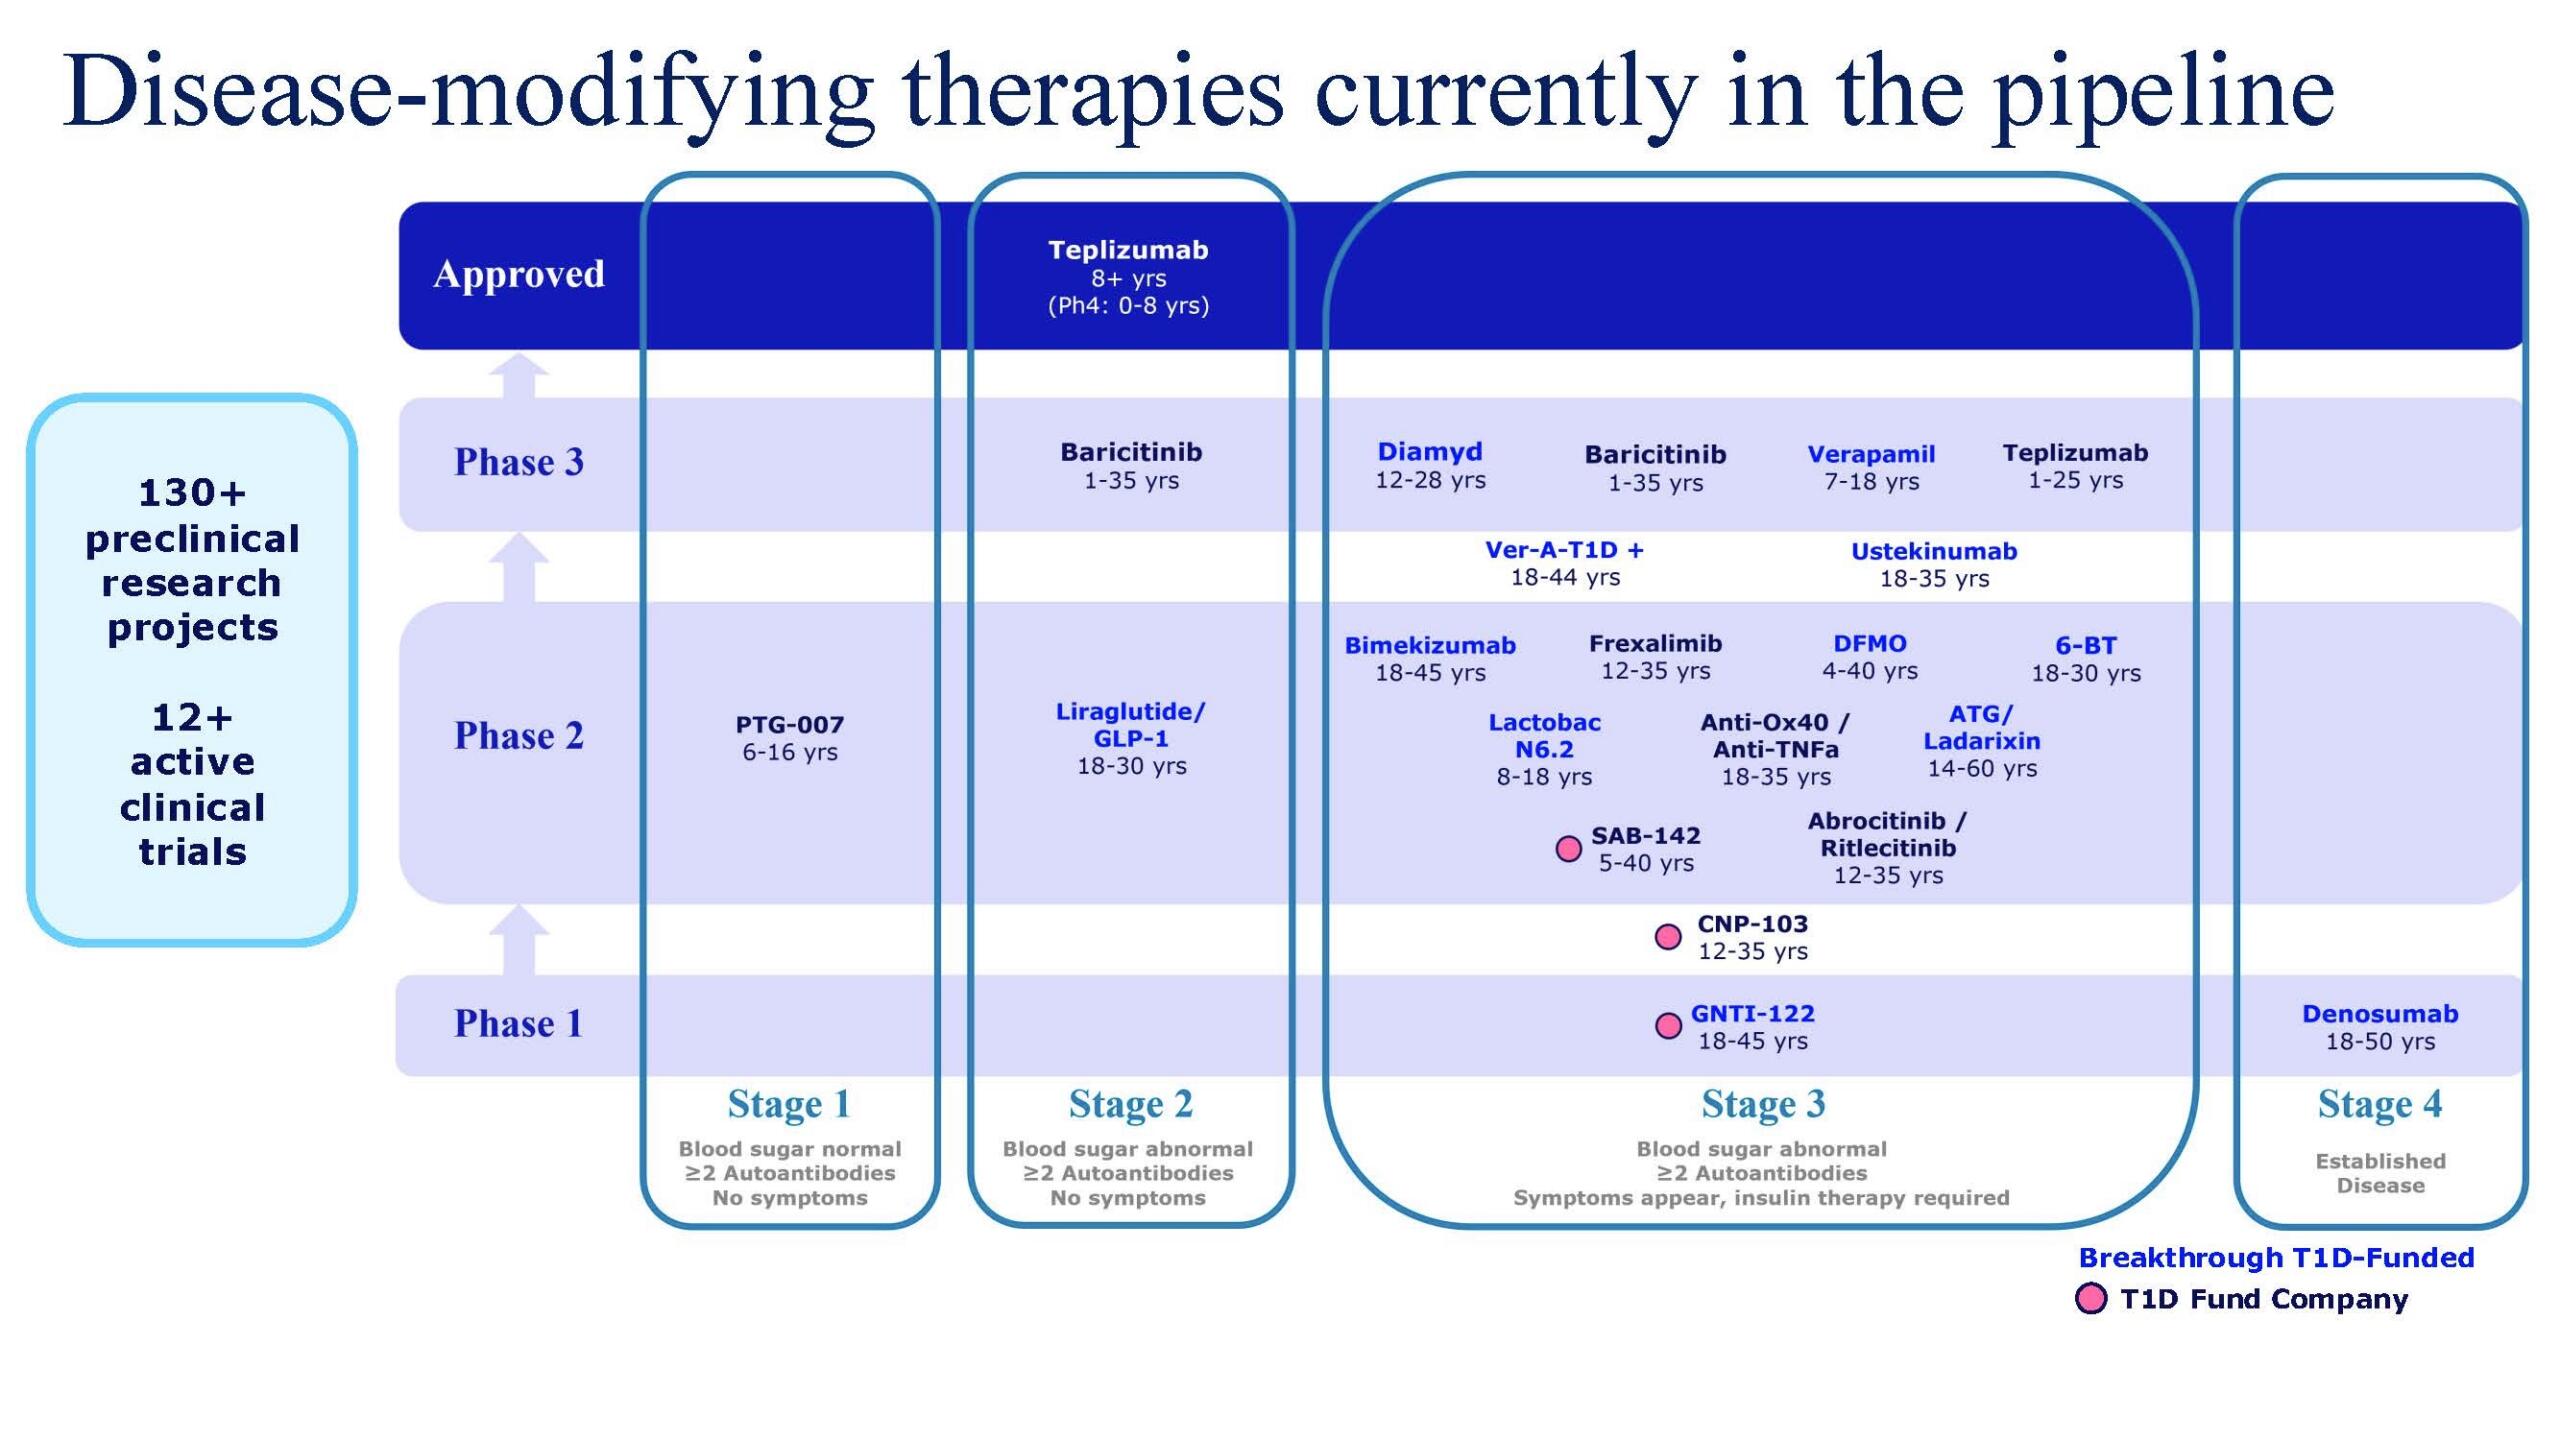
Note: To enlarge the image below, left click on it.
Update on Diamyd’s DIAGNODE-3 Clinical Trial
On March 27, Diamyd Medical announced results from an interim analysis of the Breakthrough T1D-funded Phase 3 DIAGNODE-3 trial, which assessed the ability of of Diamyd (retogatein or rhGAD65) to preserve insulin production (C-peptide) in the first 174 out of 321 participants in the trial.
Phase 3 Clinical Trials pave the way for discussions with regulatory agencies toward approval.
Surprisingly, and contradictory to positive data from prior phases of this clinical trial, the interim analysis showed that there was no observable preservation of insulin production (C-peptide). These results underscore the complexity of immune therapies in T1D and confirm Breakthrough T1D’s continued support of the clinical development of emerging disease-modifying therapies.
Breakthrough T1D’s Perspective on the DIAGNODE-3 Results
While this outcome was not expected, Phase 3 trials provide significant learnings for the development of future therapies and the field overall. Critical insight can be gained through the analysis of the data, even from clinical trials that do not meet their primary endpoint. These moments sharpen our understanding and accelerate better-designed approaches and more targeted application of therapies that are in development.
“Progress in type 1 diabetes research and treatment has always required persistence and learning from every study,” said Josh Vieth, Ph.D., Breakthrough T1D Senior Director of Research. “These results reinforce that immune interventions in type 1 diabetes are complex and highly context dependent. It’s imperative that we take these results seriously, understand what they mean, and use them to make strategic decisions about what’s next for retogatein and other disease-modifying therapies. There remains an unmet need for safe, effective therapies that rebalance the immune system in a targeted way, and Diamyd Medical is a pioneering approach to precision medicine for type 1 diabetes in clinical applications.”
What’s Next
Breakthrough T1D is in contact with the Diamyd team about next steps, which will include careful, collaborative analysis of the data from the trial to understand why these results differ from previous results. Diamyd plans to continue core operations, including manufacturing activities, during this period of analysis before determining the appropriate course of action. This includes the possibility of testing this therapy earlier in the progression of T1D (Stage 1 or 2), for which they have previously received “Fast Track” designation, an FDA program which would expedite this process.
Our Multi-part Strategy for Disease Modifying Therapy Development
Breakthrough T1D has been funding DMT research for decades. Following the 2022 approval of Tzield, the first DMT for T1D, we remain focused on our strategy for the development of disease-modifying therapies that can slow, halt, or reverse the course of T1D.
This strategy aims to both rebalance the immune attack as well as support a person’s own beta cells. Tolerization, or re-training the immune system to stop attacking beta cells without broad immunosuppression is an important part of that strategy. We are currently funding disease-modifying trials with companies like GentiBio to test their engineered Tregs, and trials aimed at repurposing existing drugs including DFMO, Bimekizumab, Denosumab, and ATG for use in T1D. To learn more, consult our previous article about this work.
One of our most promising avenues toward cures for type 1 diabetes (T1D) is cell therapies. Cell therapies replace destroyed beta cells with functional, insulin-producing cells to restore insulin therapy independence. Right now, there are nearly a dozen cell therapies in clinical testing—and OPF-310 is one of them.
OPF-310 cells are derived from porcine (pig) islets. This approach is different from other cell therapies in the pipeline, which are either harvested from human deceased donor pancreases or manufactured in the lab.
Xenotransplantation
Xenotransplantation involves transplanting organs, tissues, or cells from a non-human animal into a human. This approach holds promise to address the shortage of organs from deceased donors and is being investigated in clinical trials for kidney transplantation—and now islet transplantation, too. Yet, this isn’t the first time porcine-derived islets have been tested in T1D. In fact, before human insulin was widely available, insulin derived from pigs was commonly used to manage diabetes.
Porcine islets, like other cell therapies that come from a source other than the recipient, have the potential to activate an immune response after transplantation. To overcome this, OPF-310 uses an encapsulation device that protects the islets from destructive immune cells. This means that no immunosuppression is needed.
Cell therapies and immunosuppressants
Right now, the only approved cell therapy for T1D (Lantidra®) and most cell therapies in clinical testing require immunosuppression to prevent the recipient’s immune system from attacking the transplanted islets. This can often be a barrier to trial participation because standard immunosuppressants can come with side effects. Besides OPF-310, another cell therapy in the pipeline that does not require immunosuppression is Sana Biotechnology’s gene-edited islets.
Read on to learn more about the trial, who may be eligible for OPF-310, and the team in the Windy City performing these transplants.
Essential information about the trial
The OPF-310 clinical trial
- Sponsor: Otsuka Pharmaceutical Factory
- Trial site spotlight: University of Illinois Hospital & Health Sciences System
- Co-Investigator spotlight: Benito Valdepeñas III, Pharm.D., Co-Investigator
- Team member spotlight:
- Miranda Kipp, MSN, RN, Clinical Research Nurse
- Memunat Ogunmefun, MPH, BDS, Clinical Research Coordinator
The goal of this first-in-human, phase 1/2a study is to assess the safety, tolerability, and efficacy of OPF-310 transplantation and to define the recommended phase 2 dose. Right now, the trial is only enrolling at a single location: the University of Illinois Hospital & Health Sciences System (UI Health) in Chicago, IL. For eligible participants that live out of state or more than 100 miles from UI Health, reimbursement for travel expenses (such as flights, hotels, and food) is available.
A glance at the inclusion criteria
- 35 to 65 years old
- At least five years have passed since T1D diagnosis
- Unstable T1D despite using a hybrid closed-loop automated insulin delivery (AID) system under the care of a qualified diabetes team for at least 6 months prior to enrollment
- History of severe hypoglycemic episodes and/or hypoglycemia unawareness
People who enroll in the trial will need to meet with the team at UI Health before and after the transplant as a part of their participation in the study.
These visits include:
- Four onsite visits prior to surgery
- Follow-up visits with the endocrine team within the first four weeks post-transplant
- 18 follow-up visits within the first year after the transplant
- Long-term follow-up visits that continue throughout each participant’s lifetime
These visits include bloodwork and other tests that can let researchers know how well the cells are functioning and making insulin and ensure participants’ continued safety. Also, for a year after the transplant, participants are required to use a second continuous glucose monitor (CGM) so researchers can track changes in blood sugar levels.
As with all new therapies and treatments, there are some risks involved. For xenotransplantation in particular, there is the risk of developing zoonotic infections (those that can be transferred from animals to humans), or passing these infections to close contacts. Safety is the top priority for the study team at UI Health. To help mitigate these risks, the porcine islets undergo testing to ensure that they are sterile before transplantation, and participants are routinely tested for possible infections.
The risks associated with surgical transplantation, such as infections at the transplant site, are managed by detailed pre-operative care and assessments, a top-notch and highly experienced surgical team, and close monitoring post-transplant.
“The OPF-310 trial is an important first step toward new treatments for type 1 diabetes. It uses pig islet cells to help people who have trouble controlling blood sugar or experience severe lows,” explains Benito Valdepeñas, a Co-Investigator on the trial. “If you join, you will be closely monitored by a team of specialists who will guide and support you every step of the way.”
Get involved!
Right now, there are three people enrolled in this study—and ten more are needed. The team needs your help! If you or someone you know may be interested in the OPF-310 trial, learn more about the study or email [email protected] to connect with Dr. Valdepeñas and the study team to see if you are eligible to enroll.
Support OPF-310 clinical trial participation
Spread awareness and encourage participation by circulating information about the OPF-310 clinical trial widely in your communities: on social media, within your networks, at community events, and any other platforms where you can reach people who may be interested. Even more, help reach our community members who might be hesitant by addressing clinical trials misconceptions—and reminding people that safety is always the top priority.
Clinical trials are the key to cures
The team at UI Health agrees: the future is looking bright for T1D. “Every one of these innovations began as an idea and relied on volunteers willing to help bring it to life,” says Miranda Kipp, a Clinical Research Nurse. From the perspective of Memunat Ogunmefun, a Clinical Research Coordinator, “…the work we do now could lead to new and improved treatment options for patients in the years to come.” It’s true: the only way to bring therapies like OPF-310 to life is through clinical trial participation, which can transform the lives of the T1D community now and in the future.

“I’m inspired by the possibility that emerging trials, like OPF-310, could give patients a level of stability and freedom they’ve never had before. Being part of research that could potentially ease their daily burden, prevent complications, and offer a more hopeful future is what drives me. Ultimately, my inspiration comes from the patients themselves.” – Benito Valdepeñas III, Pharm.D., Co-Investigator
“…participation in this trial goes beyond contributing to data, it is about being a part of an effort to explore therapies that could potentially change how we treat type 1 diabetes. Every participant plays a vital role in helping us evaluate both the safety and effectiveness of OPF-310, and their involvement directly shapes the future of care. We recognize that joining a clinical trial is a big commitment, so we prioritize patient safety, transparency, and support at every stage.” – Memunat Ogunmefun, MPH, BDS, Clinical Research Coordinator


“…your safety and support are our top priorities throughout this study. After your transplant, you will receive very close follow-up from the UI Health team to make sure you’re healing well and have everything you need. Once this early period is complete, your care will smoothly transition back to your regular healthcare provider, with our teams staying closely coordinated. Our goal is to make you feel supported at every step while ensuring you continue to receive care from the providers who know you best.” – Miranda Kipp, MSN, RN, Clinical Research Nurse
We’ve come a long way: cell therapies with curative potential, like OPF-310, are in clinical trials. The only way to get these therapies through the testing process and into the hands of people with T1D is through clinical trial participation. We need volunteers from the T1D community to help us get there. Consult our clinical trials web page to learn more about how you can get involved. Use our Clinical Trials Matching Tool to find a trial near you that you or a loved one may be eligible for. Connect with a Clinical Trial Education Volunteer in your area to have all your questions answered. We need your help!
Breakthrough T1D extends a heartfelt thank-you to Dr. Valdepeñas, Ogunmefun, and Kipp for taking the time to speak with us about the OPF-310 trial and what inspires them to do T1D clinical research. Breakthrough T1D also thanks Otsuka Pharmaceutical Factory for making this connection and driving research into cures for T1D.
This article was written by Alecia Wesner (pictured above, right), a Participant Advisory Council (PAC) member, a Clinical Trial Education Volunteer, and long-time Breakthrough T1D supporter. Alecia’s story details her lived experiences with type 1 diabetes, participation in clinical trials, and her journey to joining the PAC. The views expressed by the author are her own and are not necessarily representative of Breakthrough T1D or our leadership, employees, or supporters.
Where it all began

I was diagnosed with type 1 diabetes (T1D) in 1979 in suburban Philadelphia. I had just finished kindergarten, learned to ride a bike, and spent summer days pedaling the block. I was thirsty all the time. I was a new little cyclist and it was summer, of course I was thirsty! One day I drank an entire quart of iced tea, within mere minutes, at a neighbor’s house. That was the red flag. My pediatrician sent us to the local hospital, and multiple nurses and a doctor held me down as they repeatedly struggled to find a vein for a blood draw. My Dad took me for pancakes afterwards—definitely not ideal without insulin. Later, there was a phone call and my Dad left the house. I saw him sitting outside with his head in his hands. It was the first time I saw him cry. My Mom pulled me away from the window.
I spent the next week and a half in a children’s ward of a Philadelphia hospital. My parents were trained to care for me, and I practiced giving insulin shots on an orange while arts and crafts kept me busy. I spoke to my parents every night on a pay phone, whispering, while crying that I wanted to come home. My parents would say the other children in the ward needed me to be brave. This was long before continuous glucose monitors (CGMs) or even portable blood glucose meters. My parents learned to check my glucose by testing my urine with chemicals in test tubes, a non-exact way to measure glucose range. When I came home, neighbors were anxious because many believed diabetes was contagious.
A designer’s perspective on T1D clinical trials

Clinical trials and research have been central to my life. Clinical trials are essential to proving a concept, where ideas are tested rigorously and then refined.
My training as an industrial designer has always been about the intersection of people and systems. Whether designing a lighting fixture, a user interface, or an educational program, I think first about human needs, usability, and empathy.
That design lens informs how I view research. A study protocol is not just a list of procedures. It is a system that has users, interfaces, and outcomes. Participants are the users. Devices and consent forms are the interfaces. The data is the outcome. When design thinking is applied to research, studies become more accessible, clearer, and better aligned with the realities of daily life.
A defining experience
For those of us living with type 1 diabetes, research is not just academic—it is the path to a better quality of life. I have participated in nine clinical trials and numerous studies. I tested early automated insulin delivery (AID) systems over many years, assessing software and hardware which led to commercially available AID systems. I tested an implantable continuous glucose monitor, and I took part in studies that examined complications and diabetes biomarkers. Each trial taught me about technology, the human body (specifically mine), and how research truly impacts lives.
The experience that defined my clinical trial pathway was in my mid-20’s. I developed retinopathy. Due to a great macular specialist, I received aggressive laser treatments for years. It was scary, especially as a young professional starting a career in product development and visual design. The treatments that preserved my vision were possible because others had volunteered for research for years, even decades, before me. That reality gave me enormous gratitude, and it also gave me a sense of responsibility. Participating in research is how I have been able to embrace a life philosophy of “Do good, feel good” and ultimately pay it forward. Clinical trials and research studies are how we learn and design better solutions for everyone who follows.
Joining the Participant Advisory Council

My designer’s perspective led me to join the Breakthrough T1D Participant Advisory Council (PAC). I had been involved with Breakthrough T1D for many years as a Clinical Trial Education Volunteer, an advocate, and former board member. The PAC offered a new opportunity to bring lived experience directly into the research process.
On the council, we review trial designs, advise on participant burden, critique consent language, and recommend practical changes in the hope of lowering barriers to participation. My concern initially was that I’d be a token voice, but we are not. We are advisors who help researchers see the experience through the eyes of the people who will take part in the studies—people who may ultimately benefit from the data gained.
One of the most meaningful ways I contributed as a PAC member was in June 2025, when I spoke on a panel about disease-modifying therapies (DMTs) at the American Diabetes Association Scientific Sessions in Chicago. The panel focused on disease-modifying therapies designed to preserve C-peptide (a biomarker for insulin production) and slow or stop the progression of T1D. I represented the lived experience, and I brought the perspective of a long-term clinical trial participant and an educator who helps others understand and navigate research opportunities.
Using my voice to spread awareness about clinical trials

There were numerous questions to be addressed. One question asked how patients view trials targeted at specific subsets of the T1D population compared to all open trials. My answer was that subsets are still part of the whole community, and a win in one group can expand to broader benefits. At the same time, being excluded from any study can feel deeply personal. People who have made the decision to participate and then hear they do not qualify may feel a sense of loss and frustration. That is where clear communication and education matter. Explaining why inclusion and exclusion criteria exist, offering information about other potential trials, and keeping lines of communication open helps people stay engaged rather than feeling shut out.

Recruitment, especially for new onset trials, is another challenge the panel addressed. Speed matters because opportunities for early intervention are time-sensitive. Effective recruitment requires a network approach. Endocrinologists and clinicians are critical, but so are community organizations, advocacy groups, and peer networks. Many newly diagnosed people search for help and connect with the T1D community to find resources. When trusted peers share information about trials, it not only demystifies the process and reduces the emotional burden for families facing a new diagnosis—it opens doors.
We also discussed patient-relevant endpoints in DMT trials. Clinical metrics matter, but they do not capture everything people live with. Participants prioritize outcomes that reduce daily burden, delay disease progression, improve long-term health, lower the risk of severe hypoglycemia, preserve endogenous insulin, enhance glycemic control, potentially reduce lifetime treatment costs, and sustain hope. These are the practical changes that matter in everyday life.
Education and implementation were the final themes I emphasized. Clinicians and patients alike need clear information about DMTs and about how early interventions would be implemented in real-world settings. Linking DMTs to screening efforts ensures that people in the early stages of T1D are identified and connected with options. Volunteers, advocacy groups, and community programs are essential for amplifying success stories and helping clinicians and patients understand how to access emerging therapies.

“Research is deeply personal”
All of this ties back to design. When we include lived experience in research design, the results are more humane, relevant, and practical. We reduce friction that prevents people from participating, and we improve outcomes by focusing on the needs of real users. My perspective as both a person who lives with T1D and an industrial designer helps me see where small design decisions have large effects.
Looking forward, I remain committed to this work because research is deeply personal. It saved my vision. It offers better tools and brighter possibilities. It is also a way to honor those who volunteered before me and to give others the chance to benefit. Whether I am advising on study protocols, speaking on national panels, or teaching people how to find trials, I see it as part of the same lifelong commitment: to make life with T1D easier, to improve the design of treatments and systems, and to help guide us toward the ultimate goal: cures.

If you or someone you know may be interested in joining the Participant Advisory Council, please reach out to Michelle Simes-Kennedy at [email protected].
Learn more about clinical trials
Visit Breakthrough T1D’s clinical trials web page to learn more about how you can get involved in clinical trials. Use our clinical trial matching tool to find recruiting trials near you that you may be eligible for. Connect with a Clinical Trial Education Volunteer in your area to better understand the process and get your questions answered.
What is the pipeline?
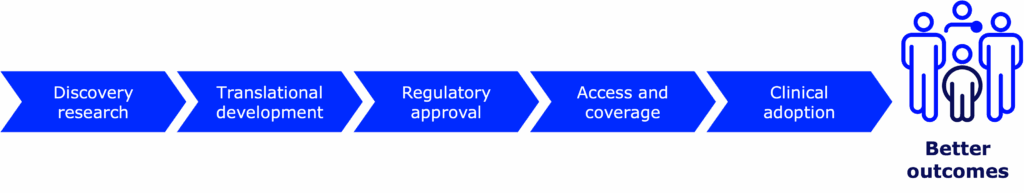
Every new medical device, therapy, treatment, and drug—including those for type 1 diabetes (T1D)—goes through the drug development pipeline. Getting a new therapy or device from the earliest stages of research eventually into the hands of people with T1D is a complicated process. Science takes time (from years to decades!), money (from hundreds of millions to billions!), and brainpower (lots and lots of brilliant scientists, doctors, researchers, and more)—and lots of it.

That’s what drives us and our work in the pipeline: people with T1D doing better.
This process is complex, to say the least. There are safety checks at every step of the way. Data are scrutinized, and preclinical and clinical testing must meet ethical standards. In fact, many new drugs and devices don’t make it very far in the pipeline—and those that do take a long time to get there.
Breakthrough T1D is unique in that we work across the entire pipeline—from start to finish—for every promising therapy or device that we invest in. Between Research, Advocacy, and Medical Affairs, we work at every single step to accelerate progress and get new treatments to people with T1D faster than ever.
That’s our value proposition. That’s what makes supporting us different than supporting an individual researcher, or a university, or a company.
Let’s dive a little deeper into the pipeline—and how we’re turbocharging it.
Time and money
Total money spent in the diabetes space in FY24:
$146 million
By Breakthrough T1D
$521 million
Total T1D research support, including by Breakthrough T1D
$160 million
By the Special Diabetes Program
$412.9 billion
In healthcare
Total investments in new drugs and devices:
12 to 15 years
Estimated time it takes a new drug to get to the clinic
$1 billion
Estimated total cost to bring a new drug from discovery research to the clinic
3 to 7 years
Estimated time it takes a new medical device to get to the clinic
$522 million
Estimated total cost to bring a new medical device from discovery research to the clinic
The pipeline in action: Automated insulin delivery systems
Automated insulin delivery systems vs. artificial pancreas systems
At the very beginning, these devices were called artificial pancreas (AP) systems. Today, they are called automated insulin delivery (AID) systems. We’ll be referring to them as AID systems going forward.
The process at a glance:
$171 million
The amount of money Breakthrough T1D spent on AID system-related research from 2005 to 2024
12 years
The amount of time it took for next-generation AID systems to go from discovery research to clinical adoption after Breakthrough T1D became involved
Hundreds of millions of dollars
Total investment in AID systems from all stakeholders
60+ years
The amount of time it took for AID systems to become a reality, starting with the first experimental AP system in 1964
A deeper dive into the process:
Breakthrough T1D x AID systems
Breakthrough T1D has played a significant role in the evolution of AID systems. Doug Lowenstein, a long-time Breakthrough T1D volunteer and supporter, detailed the history of AID systems from the very beginning, and how we accelerated progress at every step of the way.
Discovery research
It’s the early 2000s. I’m a new AID system, but I don’t exist yet—I’m just an idea. I live in the minds of some scientists and researchers who think that I have the potential to one day become a reality. But, turning an idea into reality can be hard. It’ll take a lot of people, time, and effort for me to exist—but it’s not impossible. The question is: how? Answer: it starts with funding.
2005: Breakthrough T1D launches the Artificial Pancreas Project
Breakthrough T1D dedicates funds to scientists and researchers who have compelling ideas to turn AID systems into a reality, marking the start of the decades-long Artificial Pancreas Project (APP). These investments were key in jump-starting research into all the components needed to make an AID system work.
“[The goal was] to keep people alive and healthy until we find a cure. We were losing people…overnight of low blood sugars. If we could automatically dose insulin and have everybody go to sleep and all wake up, that was an incredible victory.” -John Brady, member of Breakthrough T1D Executive Committee in the early 2000s, former Chair of Breakthrough T1D’s International Board of Directors, and father of a son with T1D
Translational research
It’s 2008. Scientists are making progress on the three key parts that need to work in harmony for me to become a reality: a continuous glucose monitor (CGM), an insulin pump, and an algorithm that lets them talk to each other. But, like most new ideas, before I’m allowed to be tested on humans, I need to be tested in animal models first. Lucky for me, I skipped this step because someone made a tool that could simulate how I would act if I was attached to a human being.
2008: Breakthrough T1D-funded scientists create simulator tool to bypass animal studies
The simulator tool, developed from the initial Breakthrough T1D grants, allowed scientists to model how an AID system would respond to real-life scenarios, like eating a certain amount of carbs or exercising, and how this would translate to blood sugar outcomes like time in range or hypoglycemic events. The FDA accepting the use of this tool was a major win—without animal studies, AID system development was accelerated by years.
“The simulator saved at least five years of animal studies because we didn’t require an algorithm to be tested in an animal model to be deemed safe and effective before going into human studies. That entire chunk was eliminated.” -Sanjoy Dutta, Ph.D., Breakthrough T1D Chief Scientific Officer
Clinical trials
It’s 2012. Scientists have come up with different versions of my components that are ready to be tested in humans. For the next four years, I’ll be attached to people with T1D around the world who courageously volunteered themselves to test if I actually work. Turns out, I do a pretty good job at managing blood sugar—and I’m safe!
2012 to 2016: AID systems make headway in clinical trials
While clinical trials for AID systems started in earnest in 2008, they kicked into high gear in 2012, when investigators started conducting trials using different AID components and algorithms in real-life settings. Progress moved quickly, and results from numerous studies supported the idea that AID systems are both safe and effective. Breakthrough T1D funding—along with the Special Diabetes Program—helped move these trials forward.
“Getting involved in AID system trials to me was my chance to pay it forward for somebody else. I have lived 45 years with T1D…I think there’s something comforting in knowing that my body was used for something that not only had the potential to make me healthier, but really was for other people. I do think there’s something to be said for doing good, feeling good, and this is what it felt like being part of trials.” – Alecia Wesner
Regulatory approval
Flashback to 2009. While scientists are busy figuring me out, people at Breakthrough T1D are already thinking about and planning for my future—and how to work with the decision-makers at the FDA who will ultimately decide my fate. The FDA has also given their two cents about the best ways researchers can test me in clinical trials to get the data needed for me to get approved. Fast forward to 2016, it finally happens: I get FDA approval!
2009 to 2016: From APP roadmap to FDA approval
In 2009, Breakthrough T1D published the AP Roadmap, detailing what the future of AID systems will look like—and how we plan to get there. Two years later, we worked with the FDA on clinical trial design for AID systems so that there was a clear path to approval. After human clinical trials, the FDA approved Medtronic’s hybrid closed-loop MiniMed 670G—officially marking the first AID system to be available in the U.S.
“I do give [Breakthrough T1D] credit for pushing, for saying there’s a real need for this.” -Jeff Shuren, M.D., Head of the Center for Devices and Radiological Health at the FDA at the time
Access
Flashback to 2008. At this time, people were still unsure if one of my main components—a CGM—was a reliable way to measure blood sugar. This all changed when a first-of-its-kind clinical trial showed that CGMs are better than finger pricks and glucose meters, and they were covered by insurance shortly after. This decision paved the way for my future: after my approval in 2016, insurers began offering to cover me.
2008 to 2017: Insurance coverage evolves
The landmark Breakthrough T1D-funded clinical trial in 2008 provided the data to convince private insurers to cover CGMs. Nearly a decade later, Breakthrough T1D launched its “Coverage2Control” campaign to advocate for insurance coverage of T1D treatments, therapies, and devices—including AID systems—ultimately resulting in all major private insurers offering coverage of AID systems by the end of 2017, followed by Medicare shortly after.
“Seeing the artificial pancreas go from concept to reality…is what makes Breakthrough T1D and all of the advocacy volunteers—who sent an email, made a call, signed an action alert, or met with their Member of Congress—very proud of this historic achievement and the impact that these will have on the individual lives of those with type 1 diabetes.” -Cynthia Rice, former Chief Mission Strategy Officer at Breakthrough T1D
Adoption
It’s present day. There are tons of iterations of me, and even more coming. People get to choose which version of me they like best. I’m covered by most health insurance. I’ve come a long way since I was just another thought in the minds of a few scientists who had a vision… and now I’ve come to life! Even so, not everyone has chosen to use me yet—and I will continue to evolve and grow until I can make the lives easier of as many people with T1D as possible.
2017 and on: More and more AID systems come to life
After the first hybrid closed-loop AID system was approved, the flood gates were opened. More and more systems are coming to market each year, and they keep getting better. They’re smaller, easier to use, and better at managing blood sugar. They’re covered by both government and private insurance plans. They’re an integral part of routine discussions between people with T1D and their healthcare providers, and people have options to choose which system is best for them. This is a future that was difficult to imagine two decades ago—and now it’s a reality. Even so, the work continues until AID systems are a reality for more and more people with T1D.
“What we brought to bear is resulting in a safer and easier life for hundreds of thousands, and soon millions, of people with T1D, including my son, that is going to keep them safe until something like a cure comes along,” -Jeffrey Brewer, one of the APP founders
The final stage: Cures and improved lives
It took tons of time, money, people, and effort to get us where we are today, but we’re not at the finish line yet. “The end game for AID systems,” says Breakthrough T1D CEO Aaron Kowalski, Ph.D., “is to have multiple compatible pumps, glucose sensors, and algorithms, so that patients can mix and match what they prefer.”
The end game for T1D as a whole, however, is cures. AID systems have greatly improved the lives of those with T1D—and will continue to do so now and in the future—while we continuously work toward cures that are one day available to everyone with the condition.
The path followed for AID systems is a roadmap for other therapies coming down the pipeline. Breakthrough T1D’s Project ACT is taking a page from the AP roadmap and applying it to cell therapies, so that functional cures can get to people with T1D who want them as quickly and safely as possible.

“While I’m proud of my work as a scientist at Breakthrough T1D on AID systems (and my brother and I currently wear AID systems that are derived from Breakthrough T1D-supported work), more than anything else I want to take off my diabetes devices and achieve what our founders set out to do—find cures for T1D.”
Breakthrough T1D successfully took an idea and turned it into a reality—and we’ll do it again and again until T1D is a thing of the past.
What’s happening?
Today, Bayer shared data from the phase 3 FINE-ONE clinical trial. These results, which were presented at the American Society of Nephrology Kidney Week in Houston, TX, showed that finerenone (Kerendia™/Firialta™) significantly reduces urine albumin-to-creatinine ratio (UACR), a measure of kidney damage, in people with chronic kidney disease (CKD) associated with type 1 diabetes (T1D). This is an exciting win for the T1D community!
Finerenone
Finerenone is a drug that has already been approved for the treatment of CKD in type 2 diabetes. In CKD, the hormone aldolsterone is overactive, leading to kidney damage. Finerenone blocks this hormone’s activity to protect the kidneys from further damage.
What did the FINE-ONE study show?
The global, phase 3 FINE-ONE clinical trial investigated the use of finerenone in people with CKD associated with T1D. This trial achieved its primary outcome: finerenone significantly reduced UACR—a measure of kidney damage—compared to placebo.
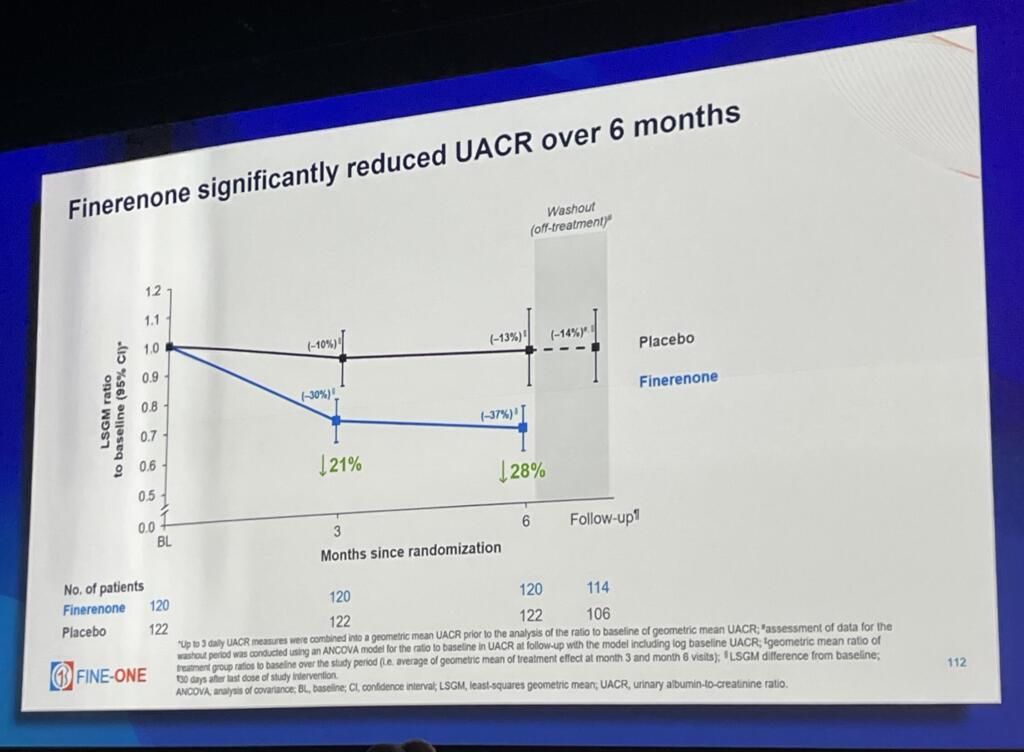
So, what does this mean? Previous clinical trials with people who have type 2 diabetes and CKD have shown that reductions in UACR from finerenone are associated with positive long-term health outcomes. In people with T1D, reductions in UACR caused by finerenone are likely indicative of lower risk of kidney disease progression, kidney failure, and cardiovascular events.
Finerenone was well-tolerated, with no new safety issues reported and few serious adverse events. Based on these results, Bayer intends to submit the data for regulatory review, with the goal of expanding finerenone’s indication to include treatment of CKD in people living with T1D. If finerenone gets approved, this would be an incredible step forward for people living with the burden of both kidney disease and T1D.
Why does this matter for T1D?
CKD is one of the most common complications of T1D. Nearly a third of people living with T1D will develop CKD, increasing the risk of both kidney failure and cardiovascular disease. Right now, the treatment options for people with T1D and CKD are limited—and there is a major need for therapies that can address this.
Finerenone is the first therapy in three decades to achieve positive outcomes for CKD in people with T1D. This is a huge step forward in the right direction, and this exciting data has the potential to transform the lives of people living with T1D with CKD if finerenone gets regulatory approval.
The bigger picture
Breakthrough T1D strategically collaborated with Bayer to support the FINE-ONE clinical trial, and we are committed to further collaboration with Bayer to advance therapies for people with T1D. Working together with Bayer and other companies will allow us to deliver more treatments to people with T1D to address complications like kidney disease.

“People with type 1 diabetes and chronic kidney disease face an immense burden due to their increased risk for both kidney and cardiovascular events,” said Jonathan Rosen, Ph.D., Research Director at Breakthrough T1D. “Breakthrough T1D remains committed to collaborating with Bayer to improve kidney care for people with type 1 diabetes.”
As a part of our Improving Lives portfolio, we aim to identify and support treatments and therapies that can address complications that arise from T1D, like CKD. The FINE-ONE trial opens the door for more therapies to come that could transform the landscape of available therapies for people with T1D, and industry investment in this space helps drive progress forward faster than ever. The T1D community needs more options, and our strategic industry partnerships will help make this possible.
We look forward to seeing the regulatory decisions that stem from FINE-ONE, and we are incredibly excited for what the future holds for CKD and T1D.
What’s happening?
Earlier today, Eli Lilly and Company announced that they are launching two new clinical trials for baricitinib in type 1 diabetes (T1D). These phase 3 trials will investigate whether the drug can delay T1D onset or progression and will open for recruitment soon. Read on to learn more about the trials, why this matters, and what led to this exciting news.
Baricitinib has shown promise for T1D
Baricitinib is a JAK inhibitor that interferes with signaling pathways critical to both immune cells and beta cells. This drug has the potential to extend the “honeymoon period” of T1D, meaning that it could preserve remaining insulin-producing beta cells earlier in disease progression. More beta cells mean better blood sugar management—and potentially reduced long-term complications.
JAK inhibitors
JAK inhibitors, including baricitinib, are already FDA-approved for other autoimmune diseases, such as rheumatoid arthritis, alopecia, and more. JAK signaling pathways are associated with overactive immune responses, so blocking this pathway may turn down the immune response.
The phase 2 Breakthrough T1D-funded BANDIT study was key in showing that this drug is safe and effective in T1D. This study was led by Professor Thomas Kay, MBBS, Ph.D., and his team at St. Vincent’s Institute of Medical Research in Australia. In this trial, more than 90 newly diagnosed individuals with stage 3 T1D between the ages of ten and 30 were treated with either baricitinib (as a single, daily oral tablet) or placebo for 48 weeks.
The results were positive: people treated with baricitinib had increased insulin production, spent more time-in-range, needed less external insulin, and experienced minimal side effects. These data were published in the prestigious New England Journal of Medicine and inspired the launch of another clinical trial (JAKPOT T1D) investigating different JAK inhibitors in preserving beta cells in T1D.
Thanks to the BANDIT study, which stemmed from years of work with Lilly to supply the drug for the trial, we got the convincing data needed to move baricitinib to phase 3—and one step closer to people with T1D.
The new studies
The new studies will be recruiting soon at medical centers around the globe. Participants in either trial will randomly receive either baricitinib or placebo. The studies are also double-blinded, meaning that neither the study team nor individuals will know whether they are administering or receiving baricitinib or a placebo. Importantly, baricitinib is a once-daily oral pill—meaning its use is simple and easy.
BARICADE-DELAY
- Purpose: To determine if baricitinib can delay the onset of clinical stage 3 T1D in people who are at high risk
- Eligibility: Must be between one and 36 years old and be in stage 2 T1D
- Time commitment: Up to approximately five years
- Primary outcome: Time to diagnosis of stage 3 T1D
BARICADE-PRESERVE
- Purpose: To determine if baricitinib can preserve beta cell function in people with newly diagnosed T1D
- Eligibility: Must be between one and 36 years old and diagnosed with stage 3 T1D within the last 100 days
- Time commitment: About 60 weeks
- Primary endpoint: C-peptide preservation (a measure of insulin production)
Breakthrough T1D is a supporter of baricitinib
Breakthrough T1D has been a tireless advocate for the use of JAK inhibitors in T1D. In conjunction with our Australia affiliate, we funded the BANDIT study, which generated the positive data that provided the basis for these new clinical trials.
Baricitinib is a cornerstone of our Disease-Modifying Therapies Program, which aims to find treatments that can delay, halt, reverse, or prevent T1D. The progression of baricitinib through the pipeline is a perfect example of what we do best: identify a promising therapy, collaborate with industry to support or fund initial clinical trials that establish a therapy’s effects in T1D, facilitate the path towards an industry-sponsored phase 3 trial, and help recruit trial participants to accelerate progress.
We will continue to follow these studies closely and look forward to seeing the results. We encourage our community and supporters to spread the word—if you or anyone you know may be eligible for these trials, share this information!
Finally, we thank Lilly for their shared commitment to our mission: a world without T1D. Industry investment in clinical trials for T1D helps us progress faster—and with partners like Lilly, we’ll get more therapeutic options to people with T1D sooner.

“Breakthrough T1D has been a tireless advocate for the use of JAK inhibitors and has seen the promise of baricitinib as a therapy for type 1 diabetes to preserve insulin production and delay disease progression,” said Breakthrough T1D Chief Scientific Officer Sanjoy Dutta, Ph.D. “We’re thrilled that Lilly is advancing clinical research with baricitinib and thank them for moving us one step closer to making it available for people with type 1 diabetes.”
“In the BANDIT trial we tested for the first time whether baricitinib could preserve insulin-producing cells under autoimmune attack in type 1 diabetes. Years of laboratory work indicated that this drug should be effective. Baricitinib given for 12 months maintained insulin production compared with its loss with placebo. We are grateful to Breakthrough T1D and Lilly for their support of the trial. This was a very exciting outcome from our bench to bedside research. Current insulin therapy is life-saving in diabetes but it is imperfect, and new treatments such as baricitinib show promise. Preservation of insulin production allows the body’s own amazing processes to control blood glucose and reduce the burden of type 1 diabetes. We hope that the BARICADE trials will confirm our findings and extend them to people with earlier diabetes, before insulin is required, and lead to the use of baricitinib in clinical practice for type 1 diabetes.” – Professor Tom Kay, Director, St Vincent’s Institute of Medical Research (SVI) in Melbourne, Australia

Get involved in clinical trials
Clinical trials are key to bringing new treatments, devices, and therapies from labs and into clinics. People who choose to participate in clinical trials help drive progress forward for the entire T1D community. If you or anyone you know is interested in participating in a clinical trial, use our Clinical Trials Matching Tool to find a trial that you may be eligible for. You can also reach out to a Clinical Trial Education Volunteer in your area to connect and answer any questions you may have. Information about the new baricitinib clinical trials will be available on our clinical trials web page when enrollment begins.
Breakthrough T1D had the pleasure of speaking with Patti Columbe, a participant in Vertex’s pivotal trial for the manufactured islet therapy zimislecel (formerly VX-880). Patti has been living with type 1 diabetes (T1D) for nearly 39 years. This is one of the most exciting T1D trials in terms of getting us closer to cures for T1D.
In this piece, we’ll talk about Patti’s T1D journey and what led to her successful enrollment in this landmark clinical trial.
The opinions, views, and experiences detailed in the interview below are those of Patti and are not representative of other participants’ experiences in this clinical trial, nor are they representative of Vertex Pharmaceuticals or Breakthrough T1D.
The conversation has been edited for length and clarity.
Q: Patti, can you tell us about your diabetes journey?
A: I was diagnosed with T1D in October 1986. I’ve lived with it for nearly 39 years. As anyone who knows this disease can tell you, it’s very hard. I’ve used every possible management system—pumps, continuous glucose monitors (CGMs), inhaled insulin, and I even have a diabetic alert dog named Otto. Despite these tools, I always struggled with low blood sugars, and I struggled with the mental burden of this disease. I was the kid at diabetes camp who had to get a glucagon injection in the middle of the night.

Q: What did you use to manage your T1D?
A: I’ve done everything—pumps, injections, CGMs, everything. But now I use multiple daily injections. I also rely on my diabetic alert dog—Otto! Otto, my service dog would often jump in my bed 20 minutes before a CGM would go off. And he consistently does that!
How did you hear about the clinical trial?
A: Having been around T1D for so long, I knew about the concept of islet transplants. I also knew that the end goal is making these cells. It was exciting but not something I thought was a reality today.
About two years ago, I heard about a clinical trial being done by Vertex. I found out about it on Instagram, actually. I then reached out to them and began the screening process.
Breakthrough T1D x Vertex Pharmaceuticals: Where it all began
Breakthrough T1D has played a role in the evolution of zimislecel for decades. In 2000, Breakthrough T1D awarded a grant to Douglas Melton, Ph.D., who developed a cutting-edge protocol to grow beta cells in a lab. Dr. Melton later founded Semma Therapeutics to turn these cells into curative therapies for T1D. In 2017, The T1D Fund made a catalytic investment in Semma, which was then acquired by Vertex in 2019—accelerating zimislecel’s development and leading to where we are today. We’ve been working closely with them ever since.
Q: What was the screening process like?
A: The screening was extremely thorough. I answered a ton of questions about my insulin usage, diet, blood type, history of hypoglycemia, and more. I even had to prove I had had T1D for all these years. They tested me for autoantibodies. They tested me for seemingly everything!
Q: How did it feel to make it into the trial?
A: Clinical trials like this are important. Clinical trials have to happen. We can’t get a cure without them, so somebody has to step up. I am lucky enough that I can step up—and I’m so glad to.
Participate in clinical trials
Clinical trials are an essential step in bringing new treatments and devices from labs to clinics. People who courageously choose to participate in clinical trials, like Patti, help drive progress for the entire T1D community. If you’re interested in participating in a clinical trial, use our Clinical Trials Matching Tool to find a trial near you. You can also connect with a Clinical Trial Education Volunteer in your area to answer any questions you may have.
Why this matters
Breakthrough T1D extends a heartfelt thank you to Patti for courageously sharing her story with us so we can truly understand why the work we’re doing is critically important. If you choose to participate in a clinical trial, like Patti, you have the potential to provide transformative benefits to the entire T1D community by accelerating the pace of clinical research. Learn more about clinical trials and how you can get involved. If you’re interested in the zimislecel clinical trial, check out the trial sites and eligibility criteria.
To accelerate T1D cures faster than ever, Breakthrough T1D’s Project ACT (Accelerate Cell Therapies) is simultaneously advancing research, development, regulatory policies, access, and adoption of manufactured islet therapies that do not require broad immunosuppression. We will not stop until these therapies are available to everyone with T1D who wants them—and clinical trial participants like Patti are getting us there faster.
We are well on our way to seeing manufactured cell therapies like zimislecel come to life. We owe a huge thank you to our supporters and the broader T1D community for inspiring us every day to keep pushing forward until functional cures for T1D are a reality.
Disclaimer: Vertex Pharmaceuticals has donated to Breakthrough T1D.
This article was written by both Brian Herrick and Sandy Vogt.

